What Actually Happens When the Conus Medullaris Gets Involved
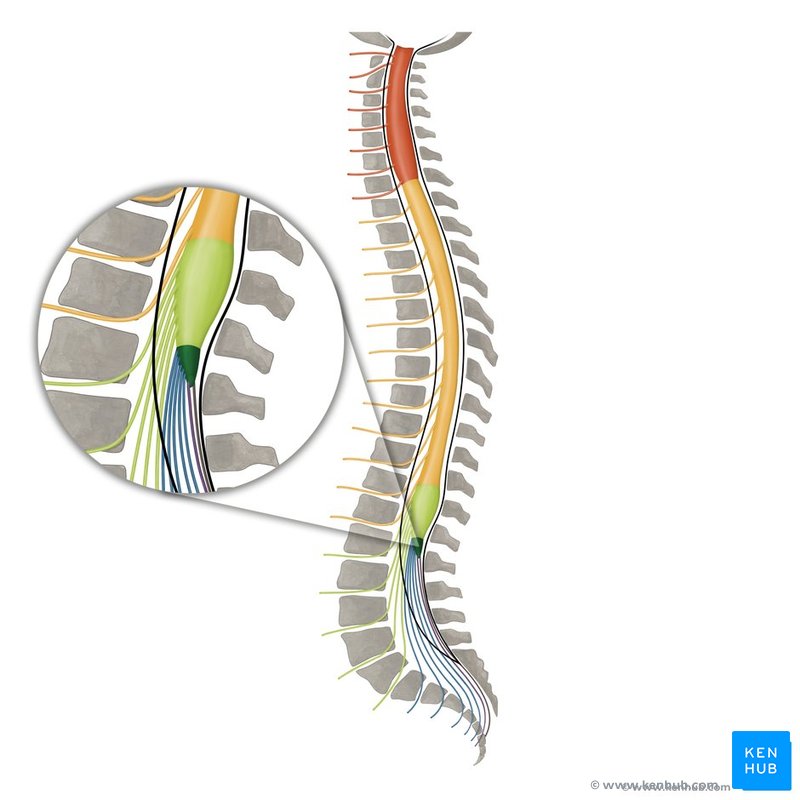
The conus medullaris sits around L1-L2 in most adults, where the spinal cord finally tapers into the filum terminale. It is a compact structure, and because of that compactness, lesions there produce a very specific constellation of symptoms. I have seen more than one case where the imaging looked borderline normal on first read and the patient was sent home with a diagnosis of lumbar strain. That is a mistake you can live with if you know what to look for. The key differentiator from cauda equina syndrome is that conus lesions tend to be bilateral and symmetric from the start, while cauda equina is often asymmetric and unilateral initially. Both can progress to the same grim outcome if you wait too long. Time matters, but it is not the only thing. The level of the lesion, the cause, and the patient's baseline anatomy all shift the timeline.
The Conus Medullaris Syndrome A Critical Review Of The Anatomy Symptoms And Treatment Options
I will walk through the anatomy, the clinical picture, the diagnostic trap, and the treatment branches. This is not a beginner overview. If you are reading this because someone handed you an MRI report with a vague note about "conus abnormality," you need to understand the next steps yourself. The conus medullaris contains the sacral and lower lumbar segments of the spinal cord. It houses the parasympathetic nuclei responsible for bladder and bowel control. It also carries the S2-S4 fibers that govern sexual function. When a compressive mass, hematoma, abscess, or tumor hits this region, you lose those functions relatively early compared to pure root compression higher up. The blood supply comes mainly from the artery of Adamkiewicz when it arises in the lower thoracic or upper lumbar range, plus contributions from the anterior and posterior spinal arteries. Occlusion or severe hypotension in that zone can cause ischemic conus infarction. It is rare but devastating. I dealt with one where the patient had a spinal epidural abscess that was misread as a simple disc herniation on CT. The MRI with contrast would have shown it immediately, but the initial scan was non-contrast and the abscess blended into the surrounding soft tissue.
The pia mater invests the conus, and from its lateral aspects emerge the nerve roots that form the cauda equina below it. This anatomical relationship explains why conus lesions often combine upper motor neuron signs in the legs with lower motor neuron bladder dysfunction. The mix is confusing at first. It is also one of the reasons this syndrome gets missed.
Get the Full Details

Symptoms and Clinical Presentation
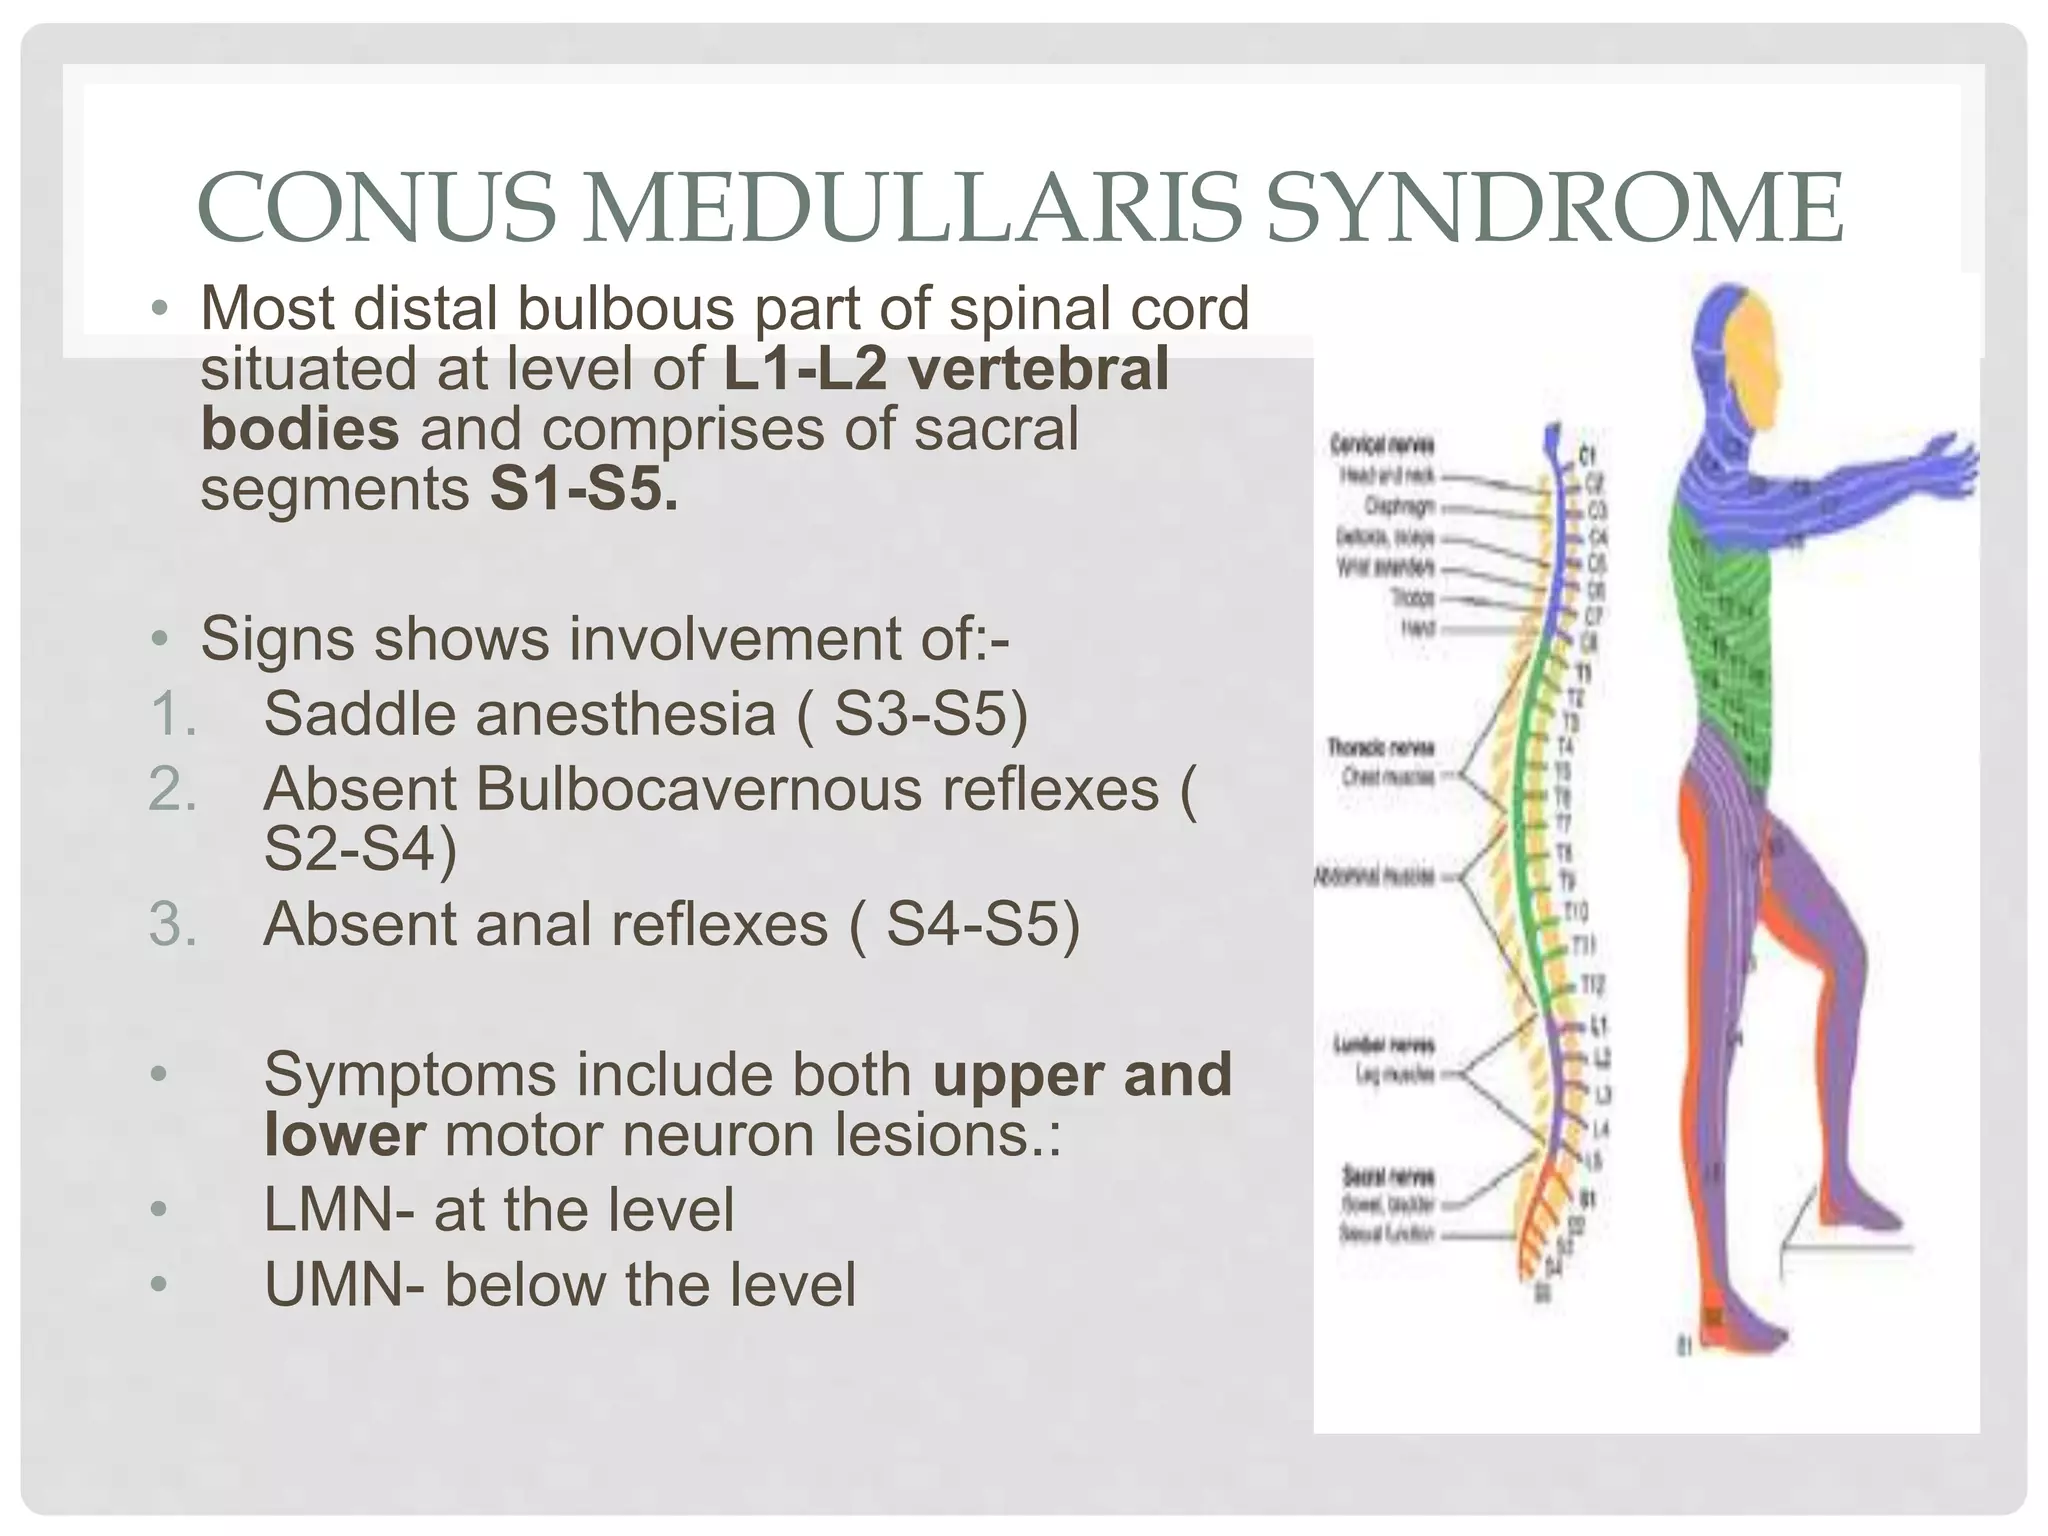
Saddle anesthesia is the hallmark. Numbness in the perineum, inner thighs, and buttocks. Not always complete. Sometimes it is just reduced sensation to pinprick or temperature. A simple bedside test with a safety pin or light touch can catch it before the formal neuro exam does. Bladder dysfunction appears early. Urinary retention with overflow incontinence is common. Patients may complain of straining to void, or they may present with an unexpectedly full bladder on palpation. Post-void residual volume over 200 mL in a patient with back pain should trigger a conus workup without waiting for weakness to develop. Bowel dysfunction follows the same pattern. Constipation, fecal incontinence, and loss of anal sphincter tone. On digital rectal exam, the resting tone is decreased or absent. You can also check the bulbocavernosus reflex. Absence of that reflex suggests conus or cauda equina involvement.
Motor weakness tends to be mild compared to pure cauda equina syndrome. If present, it affects hip flexion, knee extension, and ankle dorsiflexion depending on which segments are compressed. Reflexes are variable. Achilles and patellar reflexes may be reduced. Upper motor neuron signs like a Babinski response can appear if the compression extends upward. Pain is often less severe than in disc herniation. That is counterintuitive for people who associate back pain with structural problems. Conus compression can be surprisingly painless in the early stage, which delays presentation. A patient of mine came in three weeks after noticing urinary hesitancy because the back pain was minimal. By then, the compression had progressed to near-complete loss of sphincter control.
Diagnostic Approach
MRI of the lumbosacral spine with and without contrast is the gold standard. You need to see the conus itself, not just the disc spaces. Axial and sagittal T2 sequences will show compression, edema, or signal change within the conus. Gadolinium enhancement helps distinguish tumor, abscess, and inflammatory conditions from simple mechanical compression. CT myelography is an alternative if MRI is contraindicated. It is less sensitive for intramedullary lesions but excellent for showing bony stenosis and calcified discs. I have used it when a pacemaker prevented MRI, and it still gave us the surgical roadmap we needed. Urodynamic studies can quantify bladder dysfunction, but they should never delay surgical decompression if the clinical picture is clear. A uroflowmetry showing poor stream and high residual volume supports the diagnosis, but the decision to operate is clinical, not urodynamic.
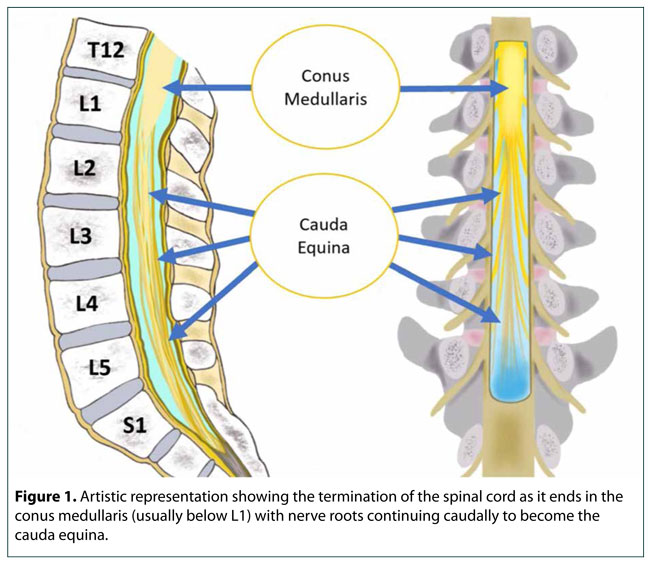
EMG and nerve conduction studies help differentiate conus from cauda equina and peripheral neuropathy. Conus lesions show denervation in sacral myotomes. Cauda equina shows a more patchy radiculopathic pattern. The distinction matters for prognosis and surgical planning.
Treatment Options and Timing
Surgical decompression is the primary intervention for compressive lesions. The window for acceptable outcomes is narrow. Most surgeons aim for decompression within 24 to 48 hours of symptom onset, and sooner is better for bladder and bowel recovery. After 48 hours, the chance of full neurological recovery drops significantly. After 72 hours, permanent dysfunction is likely. The surgical approach depends on the level and pathology. A laminectomy at L1-L2 is standard for most conus lesions. Tumors may require a more extensive resection. Abscesses need drainage and antibiotics. Hematomas need evacuation. I have seen epidural hematomas from anticoagulation present exactly like conus syndrome, and reversal of the anticoagulant plus urgent decompression saved that patient's sphincter function. Conservative management has a role only in very specific cases. Mild disc protrusions without neurological deficit can sometimes be observed with close monitoring. Steroids may reduce edema around inflammatory lesions. But any progressive neurological deficit is an automatic referral to neurosurgery or orthopedic spine surgery.
Rehabilitation after decompression is critical. Physical therapy for gait and lower extremity strength. Urological follow-up for bladder retraining. Bowel management programs for constipation or incontinence. Sexual function counseling when relevant. Recovery is slow and incomplete in many cases, especially if decompression was delayed.
Common Pitfalls and Edge Cases
The first pitfall is assuming all back pain with saddle numbness is cauda equina. The two syndromes overlap but are not identical. Conus lesions can produce earlier sphincter dysfunction and less pain. If you treat a conus compression as a cauda equina case and do a lower laminectomy, you may miss the lesion entirely. The second pitfall is normal initial imaging. A CT without contrast can miss early ischemic changes or small epidural masses. I encountered a case where the initial CT was reported as normal, but repeat MRI with contrast eight hours later revealed a small epidural abscess at the conus level. The patient deteriorated in those eight hours. Early MRI is essential if clinical suspicion is high. A third pitfall is attributing urinary symptoms to prostate issues in older men. A 65-year-old man with urinary retention and back pain will often get a urology consult first for BPH. If the digital rectal exam shows decreased anal tone, stop and image the spine. Do not assume benign prostatic hyperplasia until the spine is cleared.
The fourth pitfall is underestimating vascular causes. Spinal cord infarction of the conus can present identically to compressive syndrome but requires completely different management. Anticoagulation is contraindicated in some cases. Blood pressure support is critical. Surgical decompression will not help and may harm. MRI with diffusion-weighted imaging can distinguish infarction from compression.
Prognosis and Long-Term Outcomes
Motor function recovery is generally good if decompression is timely. Bladder and bowel recovery is less predictable. Some patients regain continence within weeks. Others require lifelong catheterization or bowel programs. Sexual function recovery is variable and rarely discussed but important to patients. Chronic pain after conus syndrome is common. Neuropathic pain in the saddle region or lower extremities can persist despite successful decompression. Medications like gabapentin or pregabalin help some patients. In refractory cases, spinal cord stimulation has been used with modest success. The mortality rate for isolated conus syndrome is low, but the morbidity is significant. Any patient with this diagnosis should have a multidisciplinary follow-up plan involving neurology, urology, rehabilitation medicine, and pain management. Leaving them to manage alone after discharge is a recipe for preventable deterioration.
When to Refer Immediately
Saddle anesthesia of any degree. New urinary retention or incontinence with back pain. Decreased anal tone on rectal exam. Bilateral lower extremity weakness. Any combination of the above in a patient with known cancer, infection, or coagulopathy. These are red flags that do not wait for elective imaging. The patient needs an MRI within hours, not days. I keep a standing order with our radiology department for emergent lumbosacral MRI with contrast. It has saved time in multiple emergencies. The protocol takes about 20 minutes, and the images are usually available within an hour of the order. That hour can be the difference between full recovery and permanent disability.
Key Takeaways
Conus medullaris syndrome is a clinical diagnosis supported by imaging. The anatomy is compact, so the symptoms are concentrated and specific. Early recognition and decompression are the only things that matter for functional outcomes. Mimics exist, especially cauda equina syndrome and spinal infarction. Do not confuse them, do not delay imaging, and do not manage conservatively in the face of progressive neurological deficit. The literature supports urgent surgical intervention, but the real-world bottleneck is often recognition at the front line. Train for that. It is where the syndrome is won or lost.

