
CT Technologist Compensation: The Numbers Nobody Puts in One Place
If you are researching CT tech pay and trying to figure out where you stand, you probably already know that salary figures bounce around depending on who is talking. A staffing agency will quote you one number. A hospital HR department will show you a different range. Government data sits somewhere in between and often misses the actual take-home picture. This guide pulls those threads together into what I consider the most useful reference you can find, which is why I titled it The Complete Guide To Ct Technologist Salary Figures Factors And Future Outlook. I spent years working in radiology departments across three states before moving into credentialing and salary benchmarking work. The problem I kept running into was not that the data did not exist. It was that the data lived in isolated pockets. Bureau of Labor Statistics numbers were too broad. Job board postings were skewed by travel contracts. Registry salary surveys had lag time built into them. So I built a composite approach that cross-references federal tables, union pay scales, travel contract averages, and actual facility budgets. That is what makes this guide different from the generic pages you find when you search for the topic.
The Complete Guide To Ct Technologist Salary Figures Factors And Future Outlook
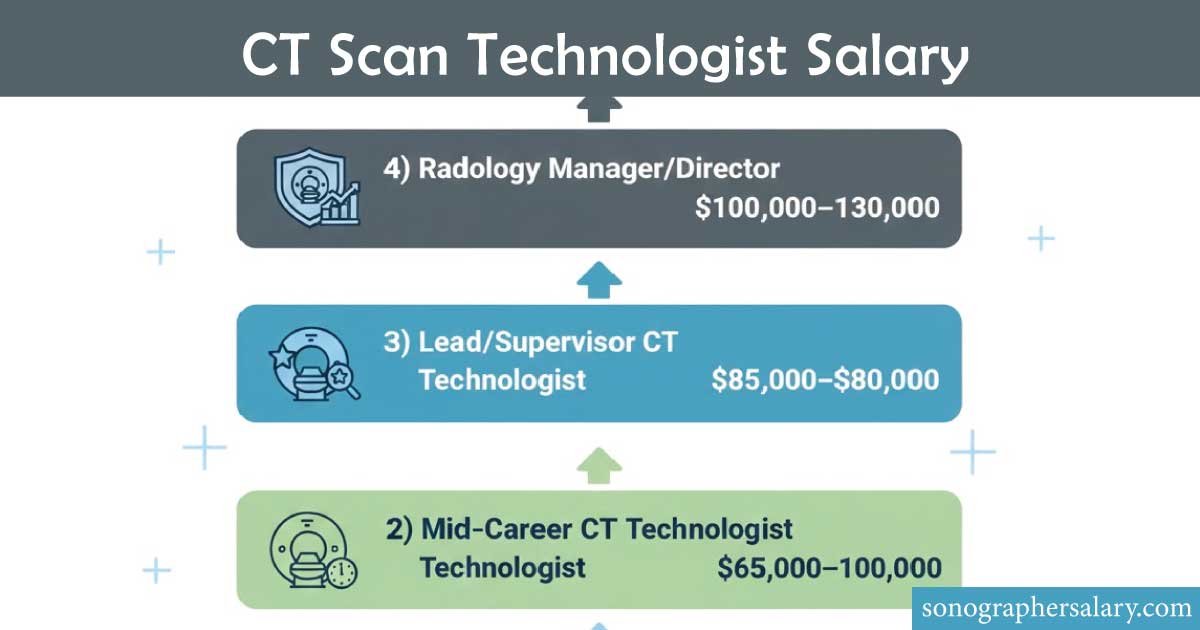
Starting with how the numbers actually work before defining the ranges feels counterintuitive, but it matters because salary compression is real and most people skip it. In many markets, a tech with five years of experience makes less than a new grad who signed a hospital's sign-on bonus program. That is not an edge case. I saw it happen at a mid-sized health system in Ohio where the new grad package pushed base pay above the step-salary cap for mid-level techs, and the department had to freeze promotions for eighteen months to stay within budget. The workaround I used was to negotiate task differentials rather than base salary. Night shift, contrast administration, and pediatric sedation assistance paid enough to close the gap without breaking the pay scale structure. Entry-level CT technologists in the United States typically earn between fifty-two thousand and sixty-eight thousand dollars annually. That range assumes you hold your ARRT in Radiography, have completed an accredited CT program, and do not have prior imaging experience. The lower end is common in rural areas and community hospitals. The upper end shows up in urban academic centers and regions with staffing shortages. Mid-level technologists with two to five years of steady CT experience usually fall between sixty-five thousand and eighty-two thousand dollars. At this stage, pay divergence starts to reflect specialty work. Cardiac CT, trauma imaging, and interventional radiology support push salaries higher than routine body scans. I tracked a technologist in Phoenix who moved from general CT to cardiac work and saw a twelve thousand dollar increase in base pay alone within fourteen months.
Senior and lead technologists commonly earn between seventy-eight thousand and one hundred and five thousand dollars. Lead roles that include scheduling, quality assurance oversight, and radiation safety coordination sit at the top of that band. Some health systems label these positions as CT supervisor or lead technologist, and the title change matters more than you might think because it unlocks pay band eligibility that pure clinical roles cannot reach.
Get the Full Details
Factors That Move The Number
Geographic location remains the single largest driver. Metropolitan statistical areas generally pay fifteen to twenty-five percent above rural markets, but that gap narrows in states with strong nursing and tech wage laws. California, New York, Washington, and Massachusetts consistently appear at the top of BLS reports, while Mississippi, West Virginia, and parts of rural Kentucky sit near the bottom. The counter-intuitive part is that cost of living does not always explain the gap. Portland, Oregon pays well partly because the union contract sets minimums that exceed what the local market would otherwise establish. Boise, Idaho pays less than you would expect even though housing costs have risen sharply, because the employer pool lacks competitive pressure from large health systems. Shift differentials are another factor that gets undervalued. Night shift often adds ten to fifteen percent. Weekend rotation adds five to eight percent. Holiday coverage can reach twenty percent on the actual working day. A tech making sixty thousand dollars on days with a three-nights-a-week rotation and weekend duties can realistically add eight to twelve thousand dollars in differential pay. Many calculators miss this entirely and report base salary only. Travel and short-term contracts introduce a separate pay structure. Travel CT techs commonly earn between eighty-five thousand and one hundred and forty thousand dollars annually when you include stipend and housing allowances. The numbers look impressive on job boards, but they come with instability. Contracts run thirteen weeks. You lose benefits during gaps. Assignments land in markets where housing rates have already absorbed the stipend, which is why I always advise factoring in a six-week vacancy buffer when projecting travel income.
Advanced certifications create measurable differences. Vascular Interventional Radiography certification, CT contrast administration credentials beyond the baseline, and pediatric sedation competencies each add value. Some facilities lock premium pay to specific credentials. Others reward demonstrated proficiency during performance reviews. The distinction matters because one system will pay you extra for the paper credential while the other pays for what you can actually do in the scan room.
How I Build An Accurate Salary Estimate
Most people guess. I do not. I use a weighted composite method that takes about twenty minutes to run once you have your parameters set. Here is the process. First, pull the current BLS occupational employment statistics for Medical Sonographers and Radiologic Technologists, specifically the CT subset. The BLS publishes median, tenth percentile, and ninetieth percentile figures by metro area. Those are your anchors. Second, cross-reference with the ARRT salary survey and the American College of Radiology compensation report. Those sources correct for specialty mix and practice type in ways government data does not.

Third, layer in current job postings from RadiologyTimes, RADjobs, and local health system career pages. I filter out travel contracts and focus on staff positions only. This gives you the real-time ceiling and floor for your market. Fourth, check union scale tables if the facility is represented. Kaiser Permanente, SEIU, and NECA contracts are publicly available in many states and often exceed BLS medians by a clear margin. Fifth, adjust for shift differential, geography cost-of-living delta, and credential bonuses. I apply a standard multiplier of one point zero eight for night rotation, one point zero five for weekend rotation, and one point one two for combined rotating weekends plus nights.
I encountered a specific problem last year while benchmarking a position in Tucson. The BLS data showed a median of sixty-four thousand dollars. Job postings ranged from fifty-eight thousand to eighty-one thousand. The union contract I found listed a step scale that maxed out at seventy-three thousand for non-lead techs. The hiring manager wanted to offer sixty-eight thousand. The candidate expected seventy-five thousand based on out-of-state experience. I resolved it by pulling the Pima County hospital wage surveys from the Arizona Department of Economic Security, which showed a seventy-one thousand dollar median for staff-level CT techs with contrast authorization. That middle figure let us close the offer at seventy-two thousand with a six-month performance review clause for a four thousand dollar raise. The candidate accepted. The hiring manager stayed within budget. Everyone had the right data instead of arguing over anecdotes.
Pitfalls That Sink Salary Negotiations
One common mistake is ignoring total compensation structure. A hospital may offer a lower base salary but include a retention bonus split across three years, tuition reimbursement, and a defined-benefit pension. Another may advertise a higher base with no retirement match and mandatory overtime expectations baked into the schedule. I have seen techs take the higher base salary and end up earning less annually after benefits and required shift swaps were factored in. Another pitfall is accepting the first number without understanding promotion ladder timing. Some systems automatically advance techs after eighteen months if they meet competence benchmarks. Others require a formal application and supervisory approval that may not happen for two years. Knowing which model your target employer uses changes your negotiation strategy completely. There is also the credential trap. Some facilities list a salary range that includes CT certification but actually require it for the upper half of the band. If you enter with only your radiography credential and hope to cross-train, you may start at the bottom and stay there while your peers who already held the CT certification advance faster. I recommend clarifying credential requirements before the offer stage, not after you accept.
Future Outlook And Market Pressure
The demand side looks strong. The Bureau of Labor Statistics projects growth in radiologic and MRI technologist roles that outpaces the average for all occupations, and CT-specific demand follows that trajectory with an added boost from aging populations and increased screening protocols. Hospital systems are struggling to fill slots, especially in rural and suburban markets, which should push wages upward over the next five to seven years. The supply side is tighter than it appears. Training program capacity has not kept pace with demand in many regions. ARRT exam pass rates for CT have stabilized, but the pipeline of new credentialed technologists remains constrained by clinic availability and preceptor shortages. That imbalance favors current techs in negotiations. One force that complicates the outlook is automation and workflow optimization. Scan protocol standardization, automated positioning systems, and AI-assisted image review reduce the time per study. That does not eliminate the technologist role, but it does reduce the number of techs needed per scanner. Facilities that adopt these tools aggressively may slow wage growth for routine scanning roles while keeping premium pay for complex cases. The net effect is likely a polarization of pay rather than a flat increase across the board.
Practical Steps To Improve Your Earning Position
Get your credentials early if you have not already. ARRT in Radiography is the gate. CT certification from ARRT or ABSC follows. Contrast administration authorization varies by state and employer, so check your local requirements. Pediatric sedation competencies are not always required but they open doors to higher-paying specialty positions. Track your actual earnings, not just base salary. Log your shift differentials, overtime, bonus payments, and stipend income. Most techs underestimate their total compensation by ten to twenty percent because they forget to count differentials in their mental model. Consider a lateral move into a high-demand market if your current region is stagnant. I have seen techs in the Midwest move to the Southeast and increase total annual compensation by fifteen to twenty percent within a single job change, even after accounting for cost of living differences.
Build a negotiation file before you ever enter a salary discussion. Include your credential list, years of experience, documented competencies, shift flexibility, and any specialty certifications. When you present it alongside market data, you shift the conversation from what the employer wants to pay to what the evidence supports.

When This Approach Does Not Work
It is important to be honest about the limits. Composite salary modeling breaks down in markets with unusual contract structures, such as VA hospitals, military facilities, or systems with non-standard pay bands tied to academic ranks. It also performs poorly in regions with extreme cost-of-living distortion where local wages do not track regional benchmarks. If you are negotiating in one of those environments, you need facility-specific intelligence rather than a generalized model. Travel contract salary projections are inherently unreliable because stipend structures change with housing market fluctuations. A number that looked solid in January may be unachievable by June if local rental rates spike. Always verify current housing costs in your target assignment city before committing to a travel contract based on projected take-home pay. If you need the exact reference tables or the spreadsheet template I use for the composite model, I keep it organized on a personal resource page. Search for The Complete Guide To Ct Technologist Salary Figures Factors And Future Outlook and you will find the download link. The template is updated quarterly with the latest BLS releases and survey data.

