Understanding What Shows Up When Something Is Wrong
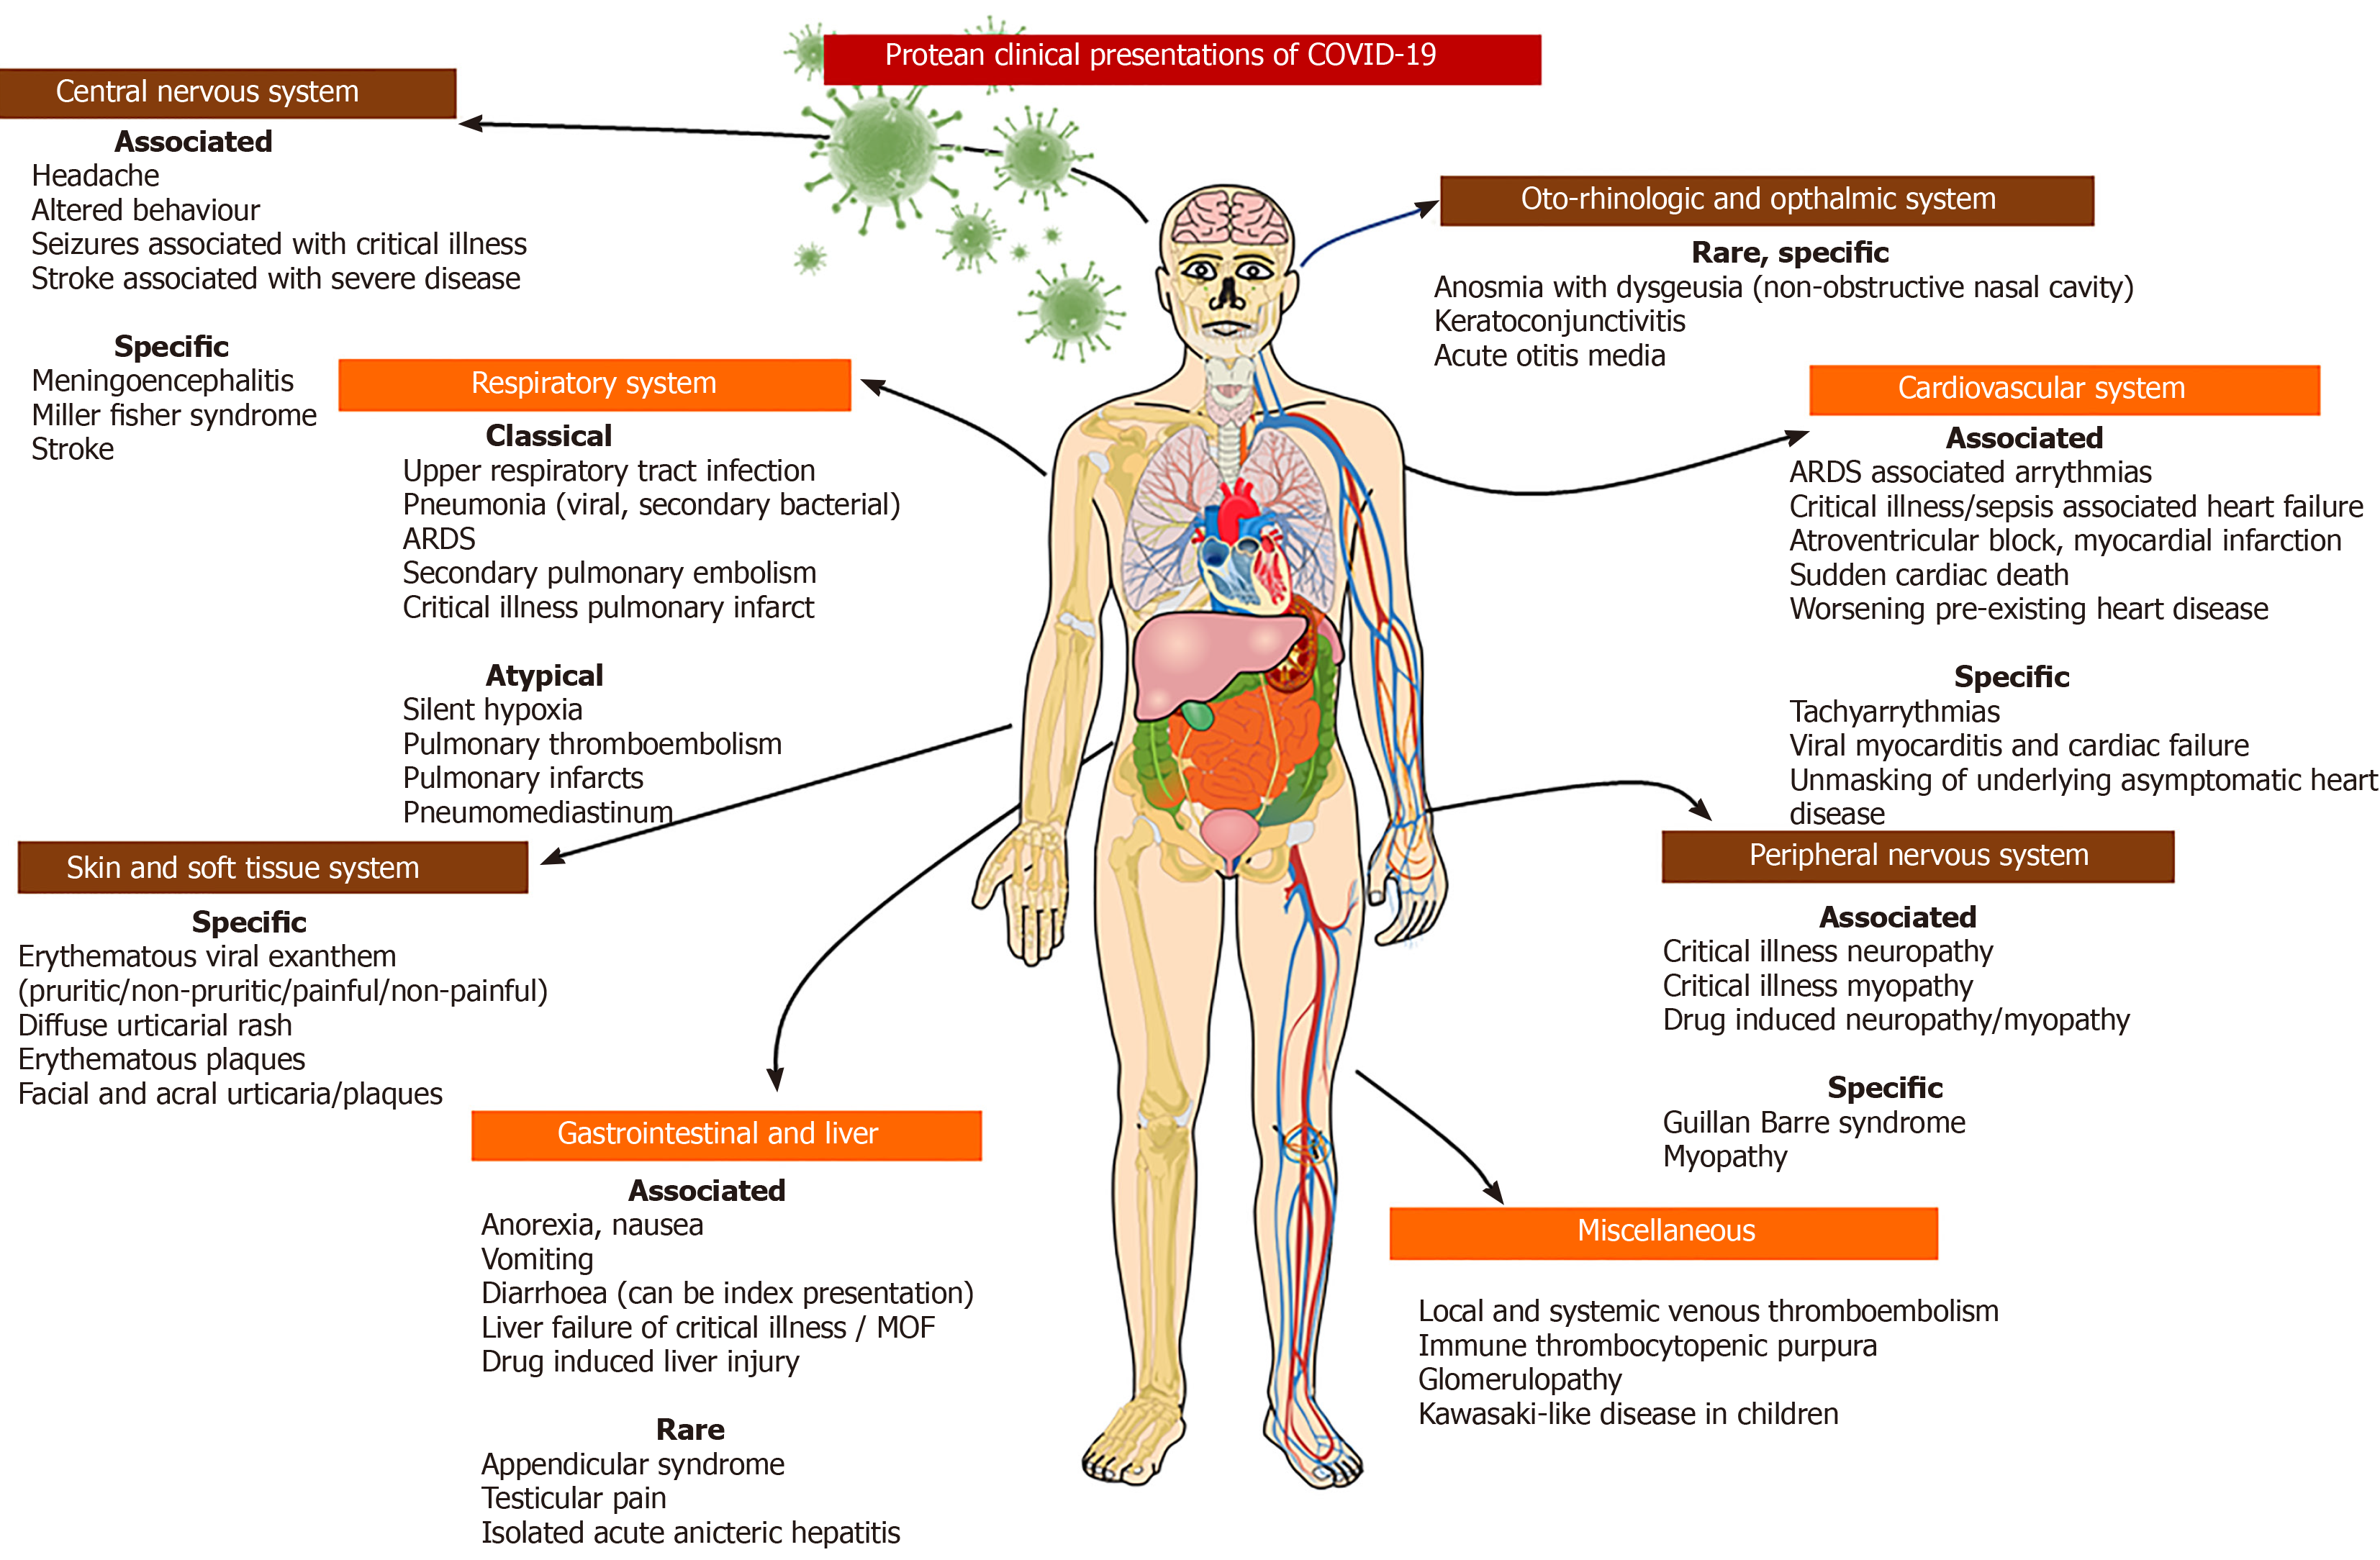
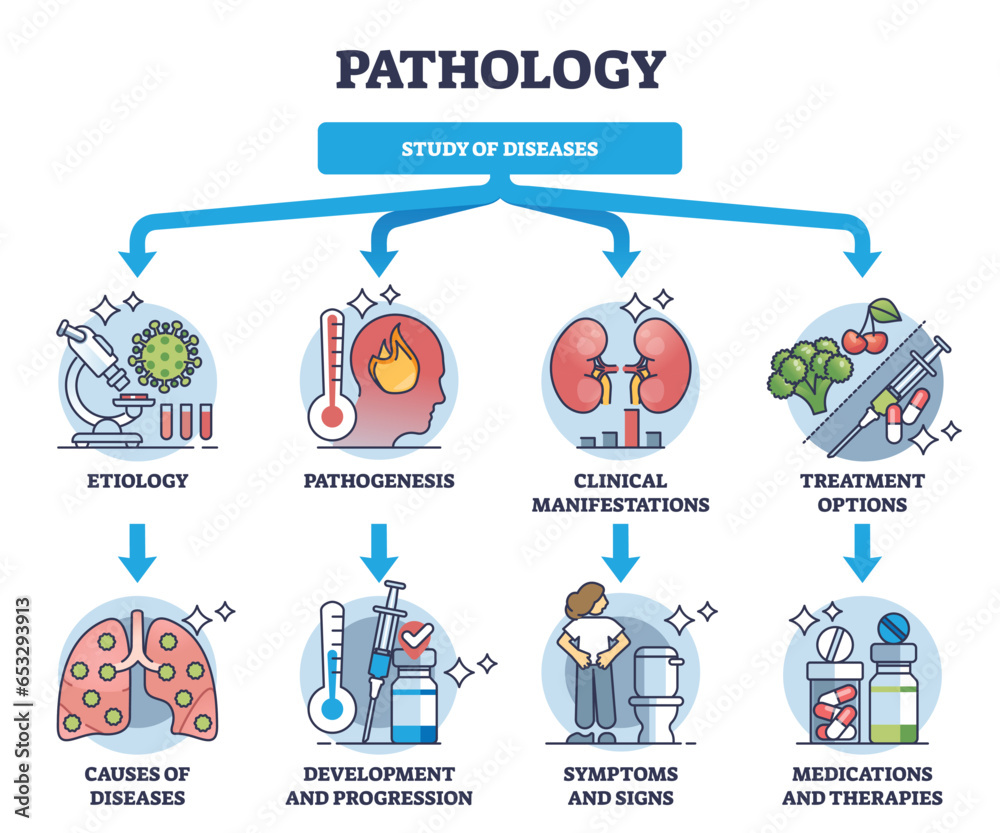
Clinical manifestations are what doctors actually observe or what patients report when they walk into a clinic. This isn't theory. It's the fever you notice, the rash that appeared after starting a new medication, the shortness of breath that makes you stop halfway up the stairs. The The Clinical Manifestations Definition Decoding How Diseases Announce Their Presence is essentially the study of how disease reveals itself through observable signs and subjective symptoms. I spent years cataloging these presentations in a hospital setting, mostly in internal medicine. You learn quickly that not every infection presents with a fever. Not every cardiac issue presents with chest pain. The classic textbook presentation is useful for passing boards but dangerous if you treat it as the only version that exists. Let me break down what this actually means in practice. A sign is objective. Someone else can measure it. Blood pressure, heart rate, temperature, visible rash, abnormal heart sounds on auscultation. A symptom is subjective. The patient tells you about it. Pain, nausea, fatigue, dizziness. Both are clinical manifestations. Both matter. But they require different approaches to documentation and follow-up.
I once had a patient come in with what looked like a simple urinary tract infection on paper. Dysuria, frequency, low-grade fever. Standard presentation. I started treatment based on that assumption. Three days later, she was back in the ER with sepsis. The original symptoms had masked a kidney infection that had been silently progressing. I missed it because I was looking at the textbook, not the full clinical picture. That changed how I approach manifestation analysis going forward.
How to Actually Decode What You're Seeing
Start with timeline. When did the first symptom appear? What was the sequence? In my experience, the order matters more than people realize. A headache that develops hours after starting a new antibiotic is different from a headache that preceded everything else. Timeline changes the differential entirely. Next, look at context. Age, sex, comorbidities, current medications, recent travel, occupational exposure. Two patients with identical presenting symptoms can have completely different working diagnoses based on context alone. A 22-year-old with right lower quadrant pain is likely something very different from a 72-year-old with the same complaint. Don't skip this step. I've seen junior clinicians miss it constantly. Then correlate. This is where most people stumble. They collect data without connecting it. You have fever plus joint pain plus rash. Those three things together point somewhere very specific. Separately, they mean almost nothing. The art of clinical manifestation analysis is recognizing which symptoms cluster together and which are coincidental. It takes practice. A lot of it.
Get the Full Details
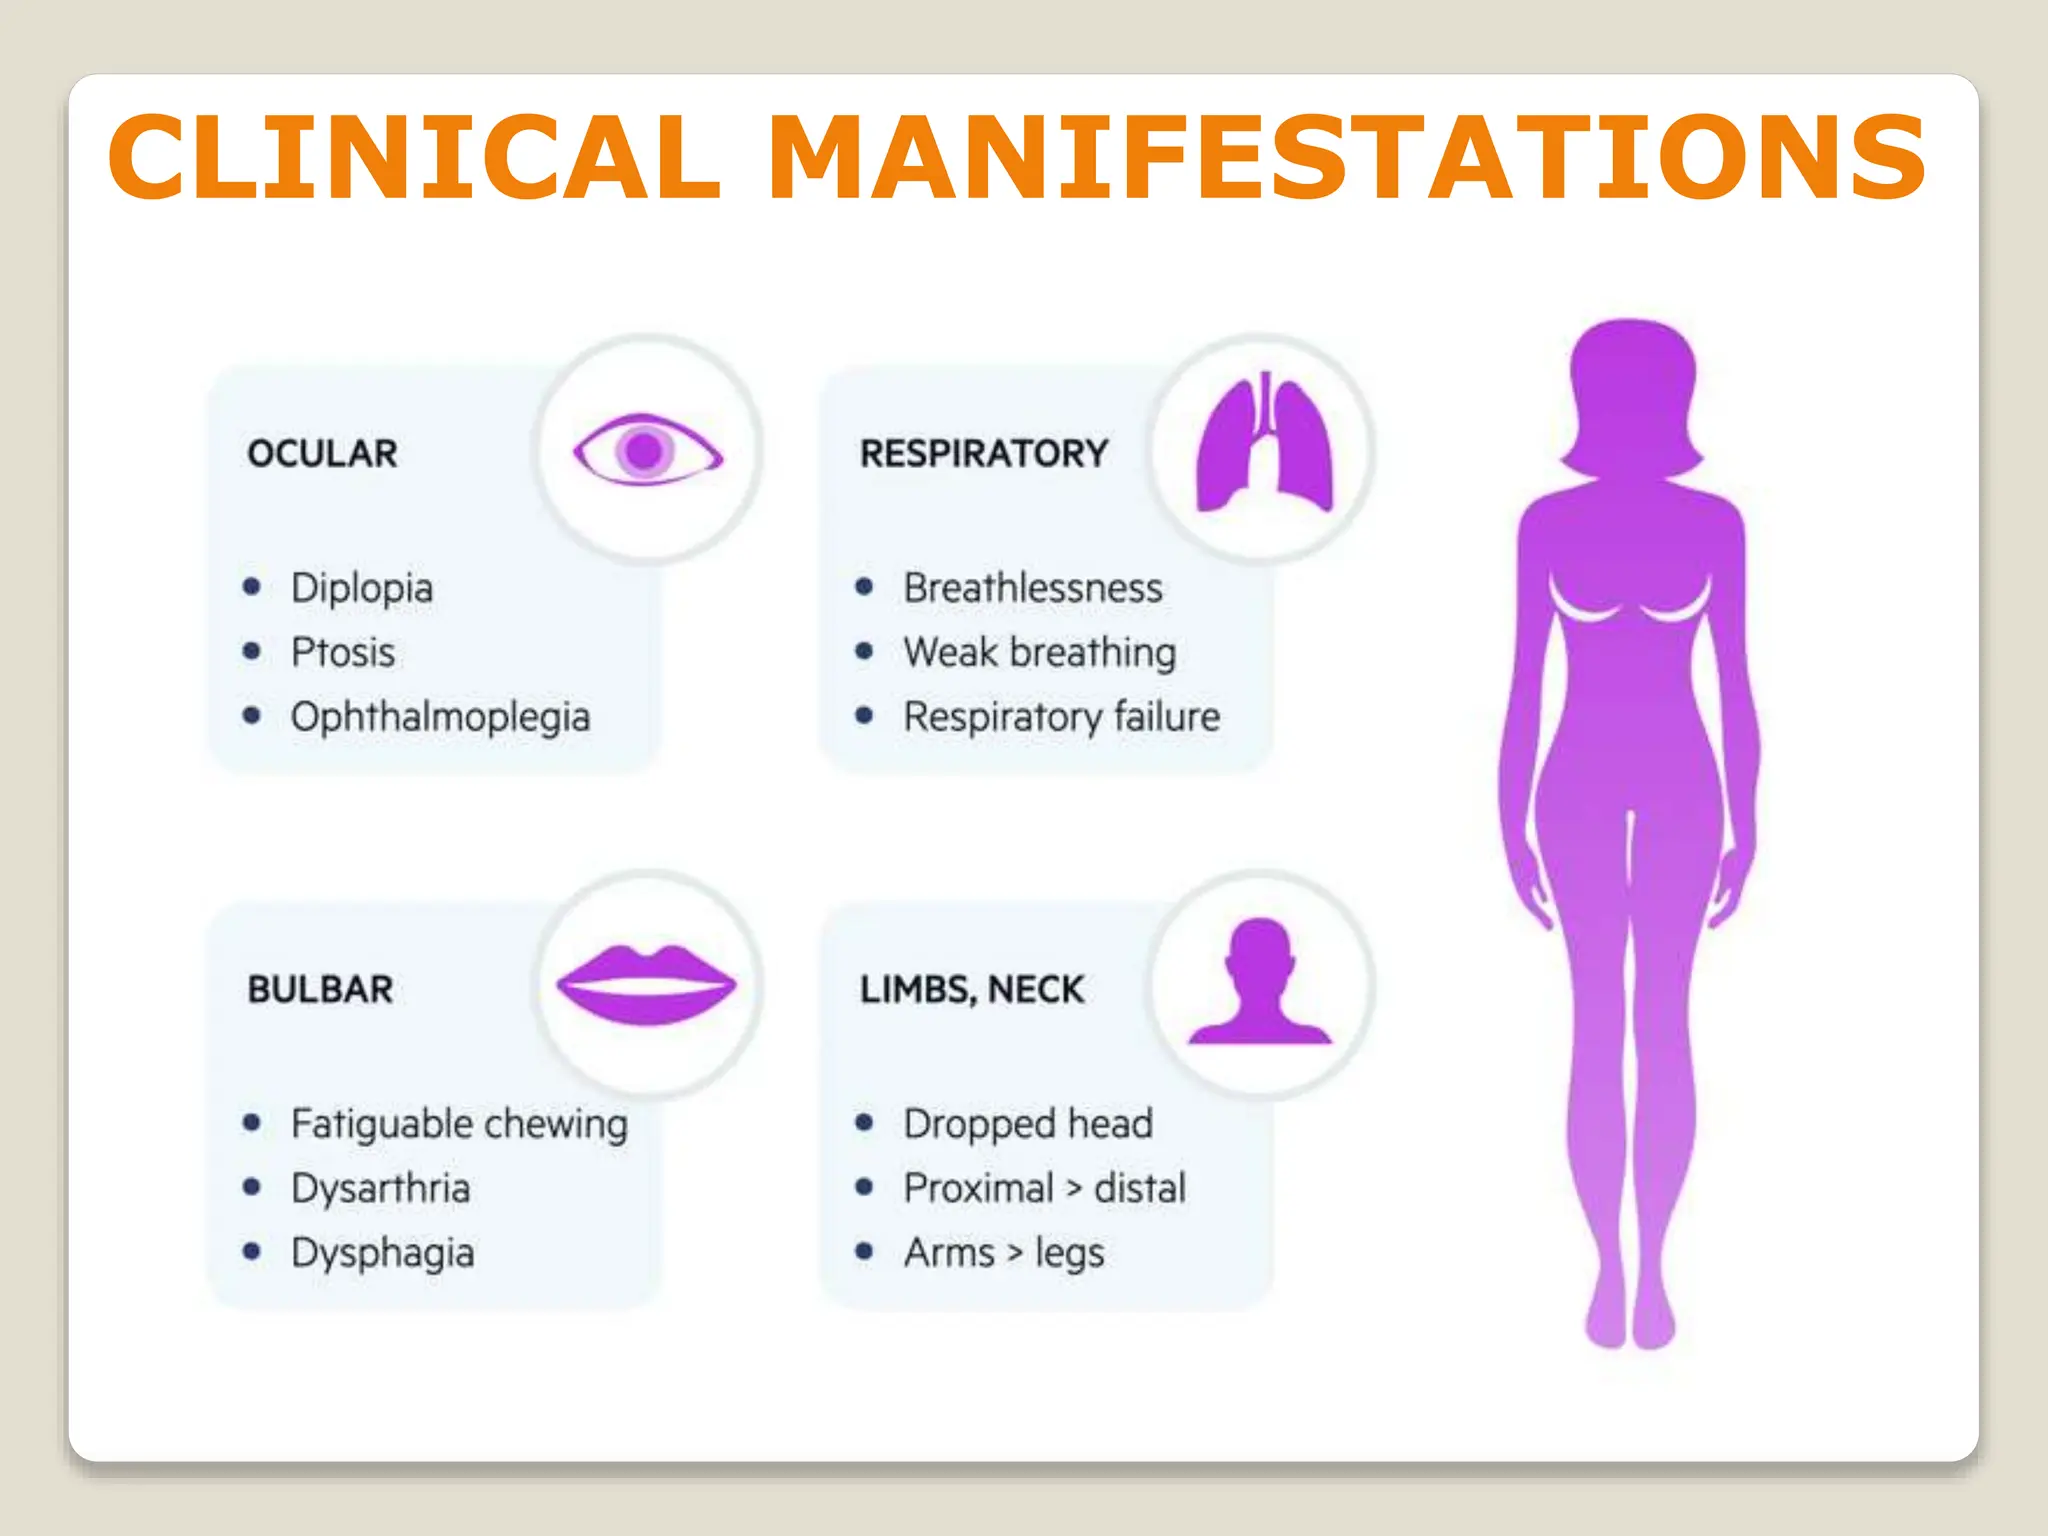
Here's a counter-intuitive point that most beginners miss: the absence of expected manifestations can be just as clinically significant as their presence. If someone presents with a condition that typically causes symptom X, and symptom X is notably absent, that changes your thinking. A myocardial infarction without chest pain in a diabetic patient is a well-documented phenomenon. The atypical presentation doesn't make the diagnosis wrong. It makes it harder to see. I keep a simple spreadsheet now for my own reference. Columns for chief complaint, associated symptoms, timeline, vital sign trends, and response to initial interventions. It takes about five minutes to fill out when a patient presents, but it has caught inconsistencies I would have otherwise missed. The cost-benefit is undeniable.
Pitfalls and Where This Approach Falls Short
Clinical manifestation analysis is not foolproof. It relies heavily on patient reporting, and patients don't always report accurately. Memory is fallible. Minimization is common. Some populations communicate differently. I've worked with patients who used euphemisms for symptoms that would take three attempts to decode. Cultural factors play a role too. In some contexts, reporting certain manifestations is stigmatized, and patients will omit them deliberately. There's also the problem of over-attribution. When you see a cluster of symptoms, the brain wants to snap them into a single diagnosis immediately. This is efficient thinking under pressure, but it's also how diagnostic errors happen. Multiple conditions can present with overlapping manifestations. Treating one while ignoring another is a real risk. If you're relying solely on clinical manifestations without diagnostic testing, you're operating with incomplete information. I understand why this happens in resource-limited settings where lab access is restricted. But even basic point-of-care tests can significantly improve accuracy. A rapid strep test, a urinalysis strip, a basic metabolic panel. These aren't luxury items. They're standard tools that reduce uncertainty in about 60 to 70 percent of typical presentations.
The biggest limitation I want to flag is time pressure. Manifestation analysis requires patience. You need to listen, observe trends, ask follow-up questions, and revisit your assumptions. In a busy clinic where you're seeing thirty patients a day, that luxury disappears. You fall back on patterns. Patterns are useful but imperfect. Recognizing this constraint is the first step toward compensating for it. For anyone working in environments where comprehensive assessment isn't always possible, the workaround is structured questioning. Instead of free-form history taking, use a quick framework. Onset, location, duration, characteristics, aggravating factors, relieving factors, timing, severity. It sounds rigid, but it catches details that casual conversation misses. I've found it saves time rather than costing it once you're comfortable with the structure.