Understanding Cellular Respiration at the Bench Level
When you look at a cell under a fluorescence microscope and watch the mitochondria light up with JC-1 dye, you're seeing the direct result of something happening every millisecond. Glucose enters through GLUT transporters, gets chopped down through glycolysis in the cytoplasm, and the resulting pyruvate moves into the mitochondrial matrix where the real work happens. This is not abstract biology. It's measurable biochemistry that you can track with the right equipment.The Cellular Engine How Glucose And Oxygen Power Human Life Through Respiration
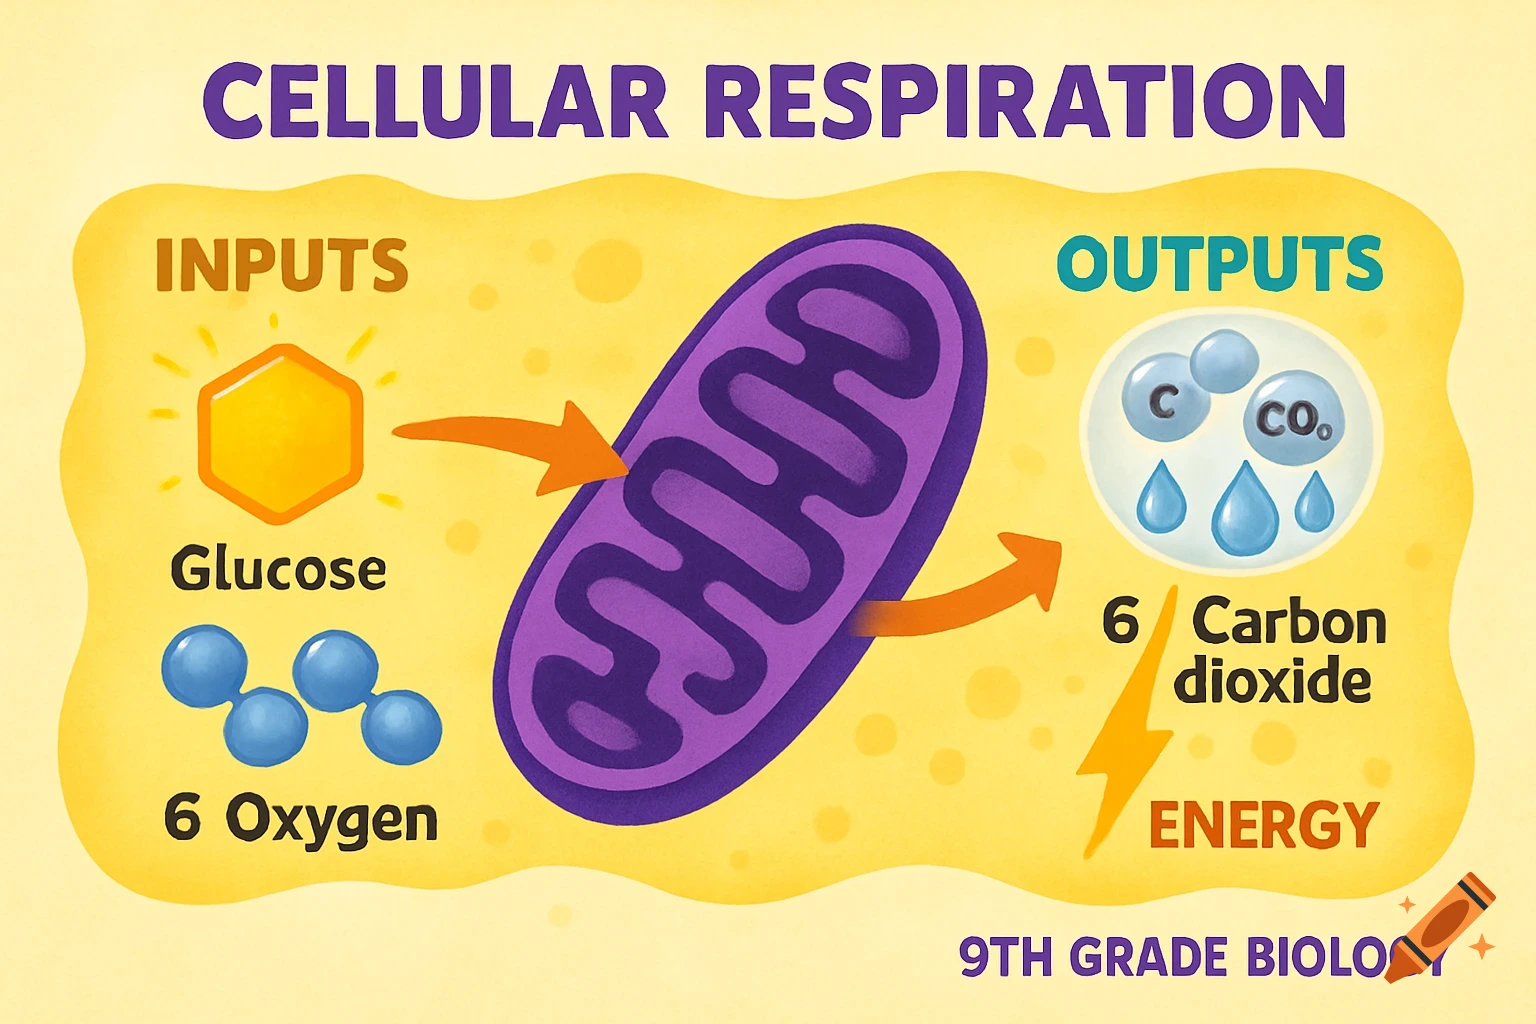
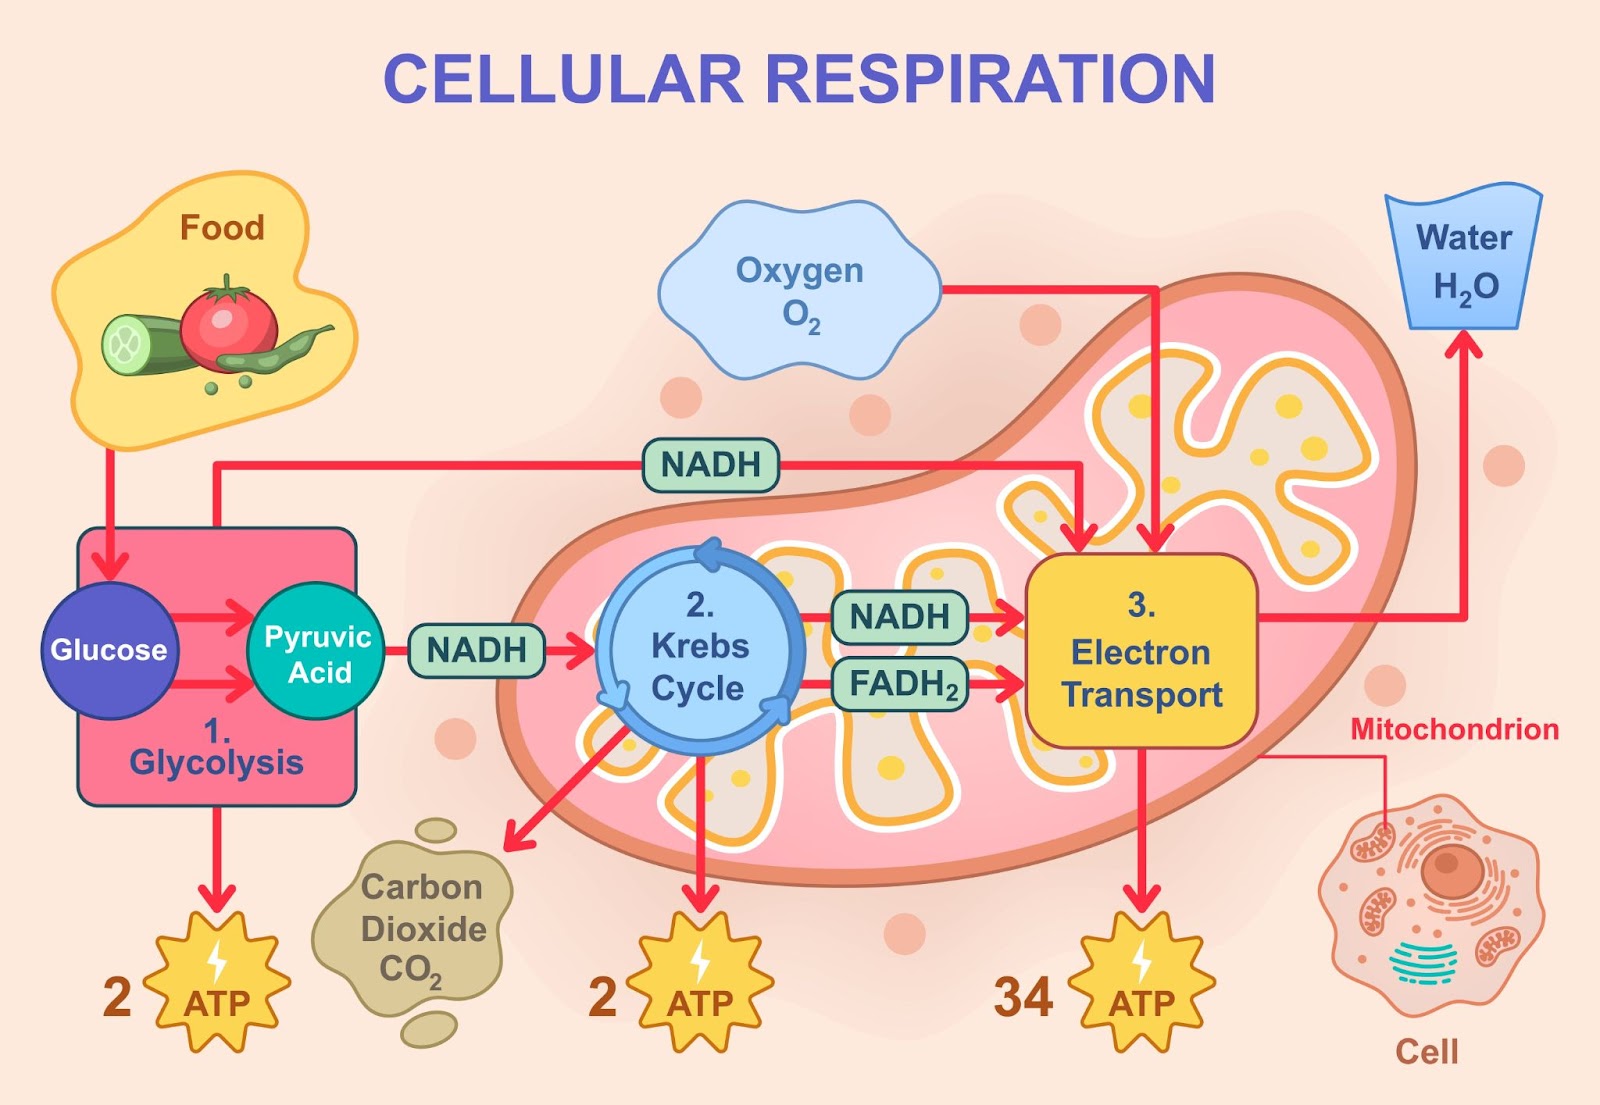
The overall equation is straightforward on paper: one molecule of glucose plus six molecules of oxygen yields six molecules of carbon dioxide, six molecules of water, and roughly 30 to 32 ATP molecules under aerobic conditions. But the actual pathway is where things get complicated. Glycolysis alone produces a net of two ATP and two NADH. The pyruvate dehydrogenase complex then converts each pyruvate into acetyl-CoA, releasing one CO2 and generating one NADH per pyruvate. That means from one glucose you get two acetyl-CoA, two additional NADH, and two more CO2 before the citric acid cycle even starts. Inside the TCA cycle, each acetyl-CoA produces three NADH, one FADH2, one GTP (convertible to ATP), and two CO2. So per glucose, the cycle turns twice and generates six NADH, two FADH2, and two GTP. Add the NADH from glycolysis and pyruvate decarboxylation and you're looking at ten NADH and two FADH2 feeding into the electron transport chain. The exact ATP yield depends on which shuttle system moves cytoplasmic NADH into the mitochondria. The malate-aspartate shuttle preserves the full reducing potential and gives you closer to 32 ATP. The glycerol-3-phosphate shuttle costs you about two ATP worth of potential because it dumps electrons onto FAD rather than NAD. I ran into a real problem during a metabolism lab a few years back where we were measuring oxygen consumption rates in isolated hepatocytes using a Clark-type electrode. The baseline respiration looked normal, but when we added oligomycin to block ATP synthase, the drop in oxygen consumption was far smaller than expected. We spent two days troubleshooting before realizing the hepatocyte prep had significant uncoupling from baseline mitochondrial damage during isolation. The cells were burning oxygen without making ATP because the inner membrane was leaky to protons. Once we switched to freshly isolated cells from perfused livers and kept everything on ice during preparation, the oligomycin response matched textbook P/O ratios. The takeaway is that your experimental conditions can completely change what the respiration data means. A bad prep makes everything look like efficient oxidative phosphorylation when it's actually just proton leak.
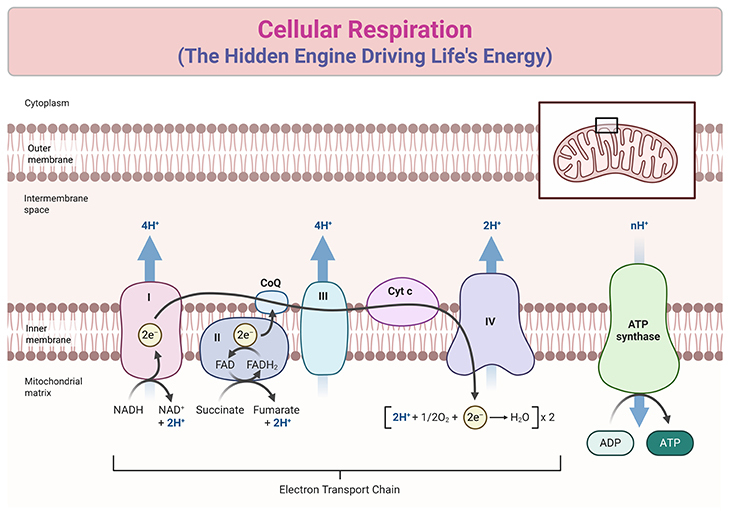
The electron transport chain itself consists of four protein complexes embedded in the inner mitochondrial membrane. Complex I accepts electrons from NADH and pumps four protons across the membrane. Complex II doesn't pump protons at all - it just passes electrons from FADH2 to ubiquinone. Complex III takes electrons from reduced ubiquinone and pumps another four protons while passing them to cytochrome c. Complex IV reduces oxygen to water and pumps two more protons. The total proton gradient generated per glucose molecule drives ATP synthase, which typically requires about four protons to produce one ATP because the phosphate transporter exchanges ATP for ADP across the membrane. Here's something most introductory courses gloss over: the proton motive force has two components, the electrical potential across the membrane and the pH gradient. In many cell types, the electrical component dominates. This matters because ionophores like FCCP collapse both components simultaneously, causing maximum oxygen consumption as the cell tries desperately to restore the gradient by running the electron transport chain at full tilt. That's actually the principle behind some metabolic assays - you add FCCP and measure the maximal respiratory capacity, which tells you about mitochondrial health independent of ATP demand. Glycogen stores complicate the glucose picture significantly. A resting adult carries roughly 400 grams of glycogen in liver and muscle combined. Liver glycogen maintains blood glucose between meals, while muscle glycogen feeds local demand during contraction. When you're fasting for more than 24 hours, gluconeogenesis becomes the primary source of blood glucose, pulling from lactate, glycerol, and amino acids. The Cori cycle shuttles lactate from muscle back to the liver for reconversion to glucose, which costs the liver six ATP per glucose regenerated but saves the muscle from acidosis during intense exercise.
There are pathological states where this system breaks down in predictable ways. In thiamine deficiency, pyruvate dehydrogenase can't function properly because thiamine pyrophosphate is a required cofactor. Pyruvate accumulates and gets shunted to lactate, causing lactic acidosis. This is why Wernicke-Korsakoff patients often present with elevated lactate. Similarly, cyanide poisoning blocks Complex IV by binding to the heme-a3 iron center, freezing the entire electron transport chain. Oxygen consumption drops to near zero within seconds because nothing can accept the electrons. The cells essentially suffocate despite normal arterial oxygen levels, which is why cyanide is so rapidly fatal. If you want to measure these processes experimentally, Seahorse XF analyzers have become the standard for profiling cellular respiration in cultured cells. You get baseline OCR and ECAR, then inject rotenone and antimycin A to isolate non-mitochondrial respiration, oligomycin to measure ATP-linked respiration, FCCP to determine maximal capacity, and the same inhibitors again to confirm the baseline. The resulting parameters - basal respiration, ATP production, proton leak, maximal respiration, spare respiratory capacity, and non-mitochondrial respiration - give you a complete picture of mitochondrial function in under an hour. One thing to watch for when using Seahorse data: cell density dramatically affects your readings. Too few cells and the signal gets lost in background noise. Too many and you create diffusion gradients where the outer layers of cells consume all the oxygen before it reaches the bottom layer, making the data artificially low. I've seen papers where the experimental group appeared to have lower respiration simply because they plated cells slightly more densely. Always normalize to protein content or cell count measured at the end of the assay, not at the beginning.
Get the Full Details

The Pentose Phosphate Pathway operates in parallel with glycolysis and branches off at glucose-6-phosphate. It doesn't produce ATP directly but generates NADPH for reductive biosynthesis and reactive oxygen species defense, plus ribose-5-phosphate for nucleotide synthesis. In rapidly dividing cells, this pathway can consume up to 30 percent of glucose flux. Cancer cells in particular show elevated PPP activity because they need both biomass precursors and antioxidant capacity to handle the oxidative stress from uncontrolled proliferation. Exercise physiology adds another layer. Type I slow-twitch fibers have far more mitochondria per unit volume than Type IIx fibers. They rely heavily on oxidative phosphorylation and can use fatty acids as fuel, while fast-twitch fibers default to glycolysis during high-intensity effort. This is why endurance training increases mitochondrial biogenesis through PGC-1alpha activation - it's not just more capillaries or more myoglobin, it's genuinely more mitochondrial machinery. After eight weeks of structured endurance training, studies consistently show 30 to 50 percent increases in citrate synthase activity as a marker of mitochondrial content. Age is another factor that tends to get understated. Mitochondrial DNA accumulates mutations over time because mtDNA lacks histones and sits close to the electron transport chain where reactive oxygen species are generated. The mutational load correlates with decreased respiratory capacity in skeletal muscle after age 60. This isn't just theory - you can measure it directly with high-resolution respirometry showing reduced Complex I and IV activity in older subjects. The practical implication is that older adults extract less ATP per molecule of glucose, which partially explains the decreased exercise tolerance and higher relative effort required for the same physical task.
Caloric restriction studies in mammals show improved mitochondrial efficiency and reduced ROS production despite no change in maximum respiratory capacity. The mechanism likely involves increased SIRT1 activity deacetylating PGC-1alpha targets, upregulating antioxidant enzymes, and improving the fidelity of the electron transport chain. Whether this translates to meaningful lifespan extension in humans remains an open question, but the metabolic signatures are consistent across species. For practical purposes, understanding glucose and oxygen metabolism isn't about memorizing the citric acid cycle intermediates. It's about recognizing that every physiological state - fasting, feeding, exercise, stress, disease - shifts the balance between these fuel sources and the efficiency with which cells convert them to ATP. The numbers on paper are clean. The biology is messier, and that's where the interesting questions live.