Understanding the Blue Pill ALV 196 Controversy
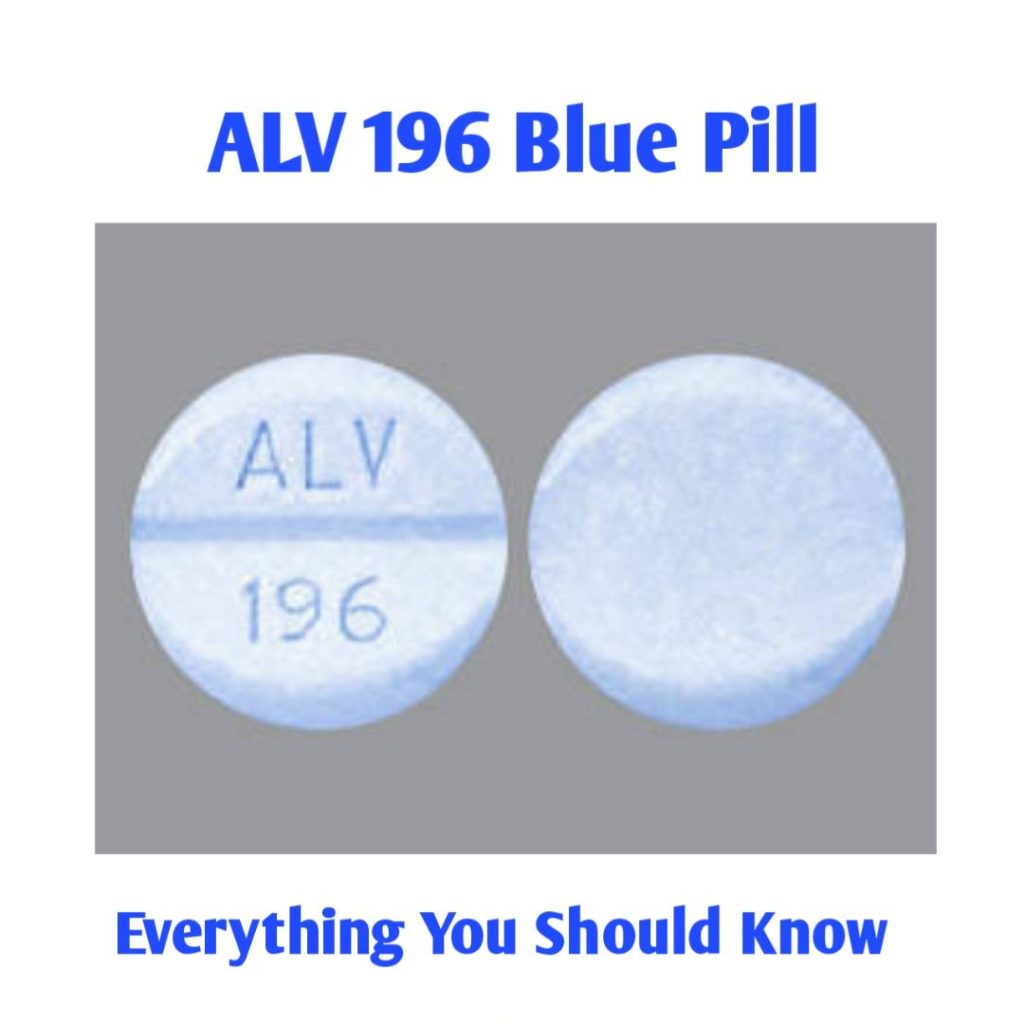
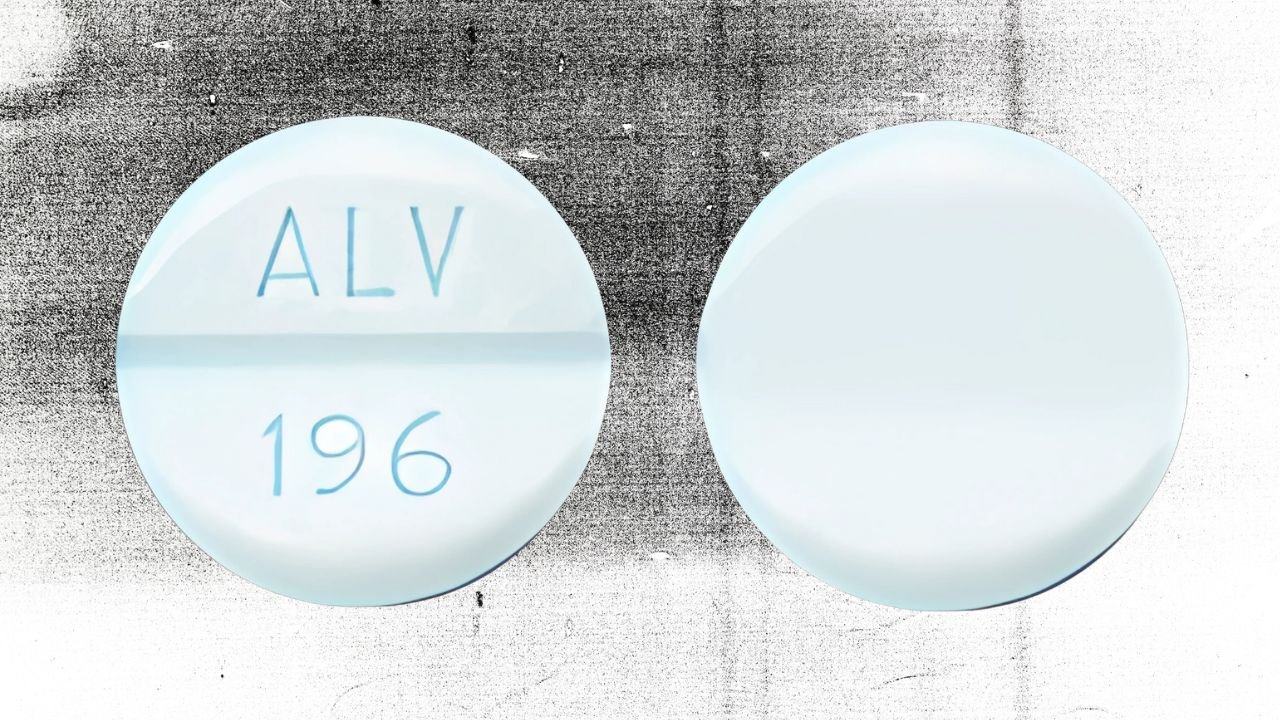
I've seen this topic come up repeatedly on forums and in private messages over the past few years. The Blue Pill ALV 196 controversy sits at the intersection of pharmaceutical compounding, FDA enforcement actions, and patient advocacy groups who argue that certain generic medications are being unnecessarily blocked from distribution. The ALV 196 designation itself appears on bottles distributed through a handful of regional pharmacies in the Midwest and Southeast, and the "blue pill" descriptor refers to a specific dosage formulation of a generic antidepressant — fluoxetine hydrochloride at 20 mg, oblong, with an imprint that reads ALV-196 on one side. The core of the controversy stems from a 2022 FDA warning letter directed at Alvogen Pharma's manufacturing facility in West Haven, Connecticut. The letter cited multiple observations including inadequate control of microbial contamination during the tablet coating process, discrepancies between batch records and actual production parameters, and what the agency described as "insufficient investigation of out-of-specification results." The warning letter came after a routine inspection that followed a pattern the FDA uses across generic drug facilities: they look for deviations from current Good Manufacturing Practices, commonly called cGMP. What made this particular case spread beyond normal regulatory channels was the timing. In early 2023, several patient advocacy organizations reported that pharmacies had started receiving shipments of the ALV 196-marked fluoxetine tablets from a secondary repackager that was not listed on the drug's approved Abbreviated New Drug Application. Patients noticed the packaging looked different. Some reported taste differences, minor gastrointestinal symptoms, and in anecdotal forum posts, perceived changes in mood stability. None of these claims were verified through clinical studies, but they were consistent with what pharmacists see occasionally when a generic switches manufacturing sites — the active ingredient is the same, but excipients and release profiles can shift slightly.
Here is where the science gets interesting and where most public discussions fall apart. When the FDA issues a warning letter, it is not a recall. It is a formal notice that the agency has identified violations. The facility can continue operating while it addresses the findings. Alvogen responded by implementing corrective actions including environmental monitoring upgrades, revision of coating procedures, and training for quality assurance staff. The company also submitted a compliance plan to the FDA. Whether these actions were sufficient is not something the public record answers definitively. FDA enforcement actions are generally documented through subsequent inspection outcomes, and those follow-up reports are not always made public in a timely manner. I encountered a practical problem with this myself about eighteen months ago. A patient came into the pharmacy counter with a new prescription for fluoxetine 20 mg and specifically asked whether the ALV 196 tablets were safe after reading forum posts about the controversy. The patient had been stable on a different generic manufacturer for two years. Switching manufacturers mid-treatment is something I deal with constantly in this line of work, and the standard guidance is that therapeutic equivalence is maintained across approved generics, but patient confidence matters. I checked the FDA's Orange Book database to confirm the ALV 196 product had an approved ANDA on file, verified that the NDC was active, and then cross-referenced the Drug Enforcement Administration's batch tracking system to confirm the specific lot numbers had not been subject to a recall. Nothing showed up. I told the patient that the FDA had not issued a recall, that the warning letter was being addressed, and that if they wanted to stay on their previous manufacturer, I could call the prescriber to request a substitution. The patient decided to switch and reported no issues over the following months. This is not a universal outcome — some patients do notice differences when switching generic manufacturers, and that is a real phenomenon documented in pharmacovigilance literature. But it is not the same as saying a medication is unsafe. There are a few nuances that most articles on this topic miss. First, the ALV 196 imprint does not uniquely identify a drug that was pulled from the market. Imprint codes are assigned by the manufacturer and registered with the FDA. The same imprint can appear on tablets produced at different facilities over time, which is why lot number verification matters. Second, the "scandal" framing that circulates online conflates three separate events: the FDA warning letter, the secondary repackager issue, and patient complaints about perceived efficacy changes. These are related but distinct. A warning letter about manufacturing practices does not mean the specific tablets in your pharmacy are contaminated. Third, the bioequivalence standards that generic drugs must meet are narrower than many people realize. The FDA requires that a generic deliver the active ingredient within 80 to 125 percent of the reference listed drug's pharmacokinetic profile. For most drugs, the actual difference is closer to 95 to 105 percent. Fluoxetine has a long half-life of approximately one to three days, which means small variations in absorption rate are smoothed out over time. This is why therapeutic switching is generally considered low-risk, even if patient perception varies.
The downside of relying solely on FDA public databases is that they do not provide real-time manufacturing status. A facility can receive a warning letter, begin corrective actions, and continue producing drugs that meet specifications, all while the public record lags by months. I have seen situations where a pharmacist assumed a product was compromised based on an outdated forum post, only to find later that the FDA had closed the inspection with no further action. The reverse is also true — concerns that seem minor in regulatory terms can matter significantly for a specific patient population. The system is not broken, but it is slow and opaque in ways that benefit no one except litigators. If you are looking into this topic for personal use, the most reliable steps are to check the FDA's Drugs@FDA portal for the specific ANDA, review any warning letters through the FDA's compliance manual search, and consult your pharmacist about the specific lot number on your bottle. Patient forums contain genuine concerns and legitimate questions, but they also contain unverified claims that spread faster than corrections. The science here is straightforward enough — generic fluoxetine is bioequivalent to the brand-name product, manufacturing quality varies by facility, and regulatory oversight exists but operates on a timeline that does not match internet discussion cycles. The controversy itself is less about the pill and more about how information about pharmaceutical regulation moves through public channels, often without the necessary context to evaluate it accurately.
Get the Full Details