What You Actually Need to Know About Stratified Squamous Epithelium
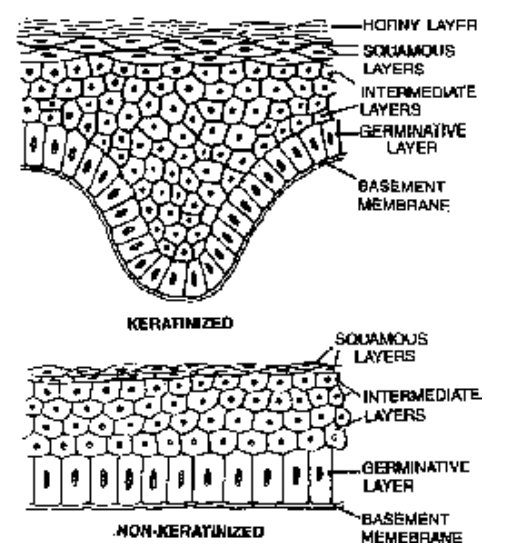
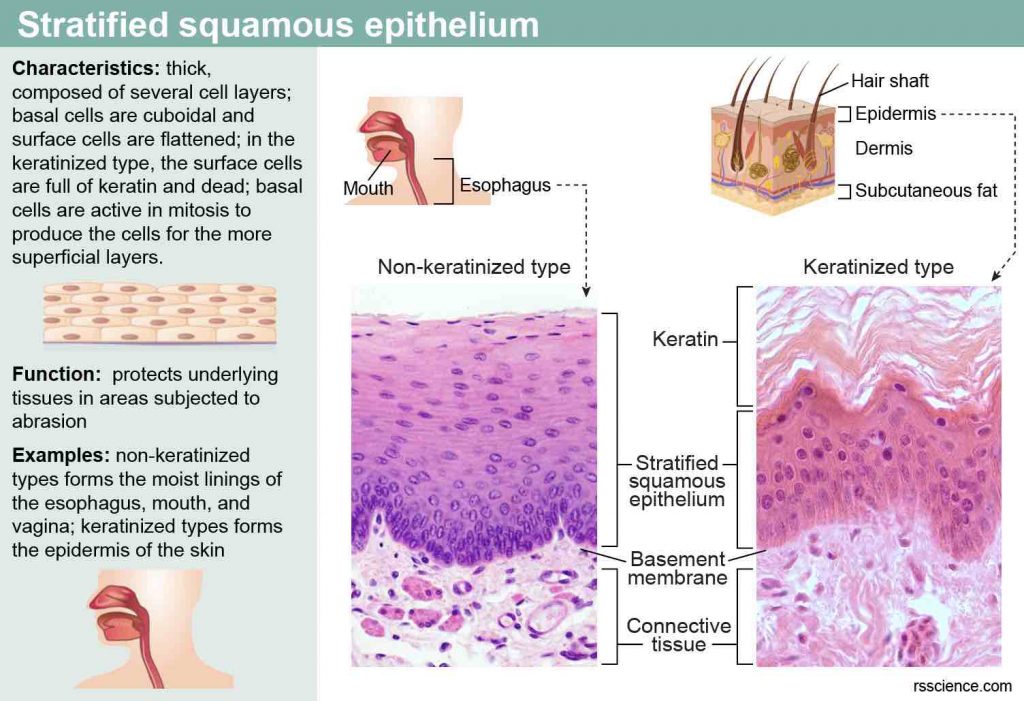
Stratified squamous epithelium is the most common epithelial tissue type in the human body, and it comes in two main forms that serve completely different functions. Keratinized and nonkeratinized varieties are often taught side by side in histology courses, but the practical differences matter a lot more than most people realize. I spent three years working in a dermatopathology lab and spent countless hours distinguishing these under a microscope, so I learned quickly that memorizing textbook diagrams doesn't translate directly to interpreting real tissue samples. The basic architecture is straightforward: multiple layers of cells stacked on top of a basement membrane, with the surface cells being squamous (flat) rather than cuboidal or columnar. What changes between the two types is whether those surface cells contain keratin and eventually undergo complete cornification. The keratinized version loses its nucleus and organelles as cells migrate outward, becoming a dry, tough barrier. The nonkeratinized version keeps its nucleus and remains moist, flexible, and permeable.
The Battle Beneath Your Skin How Keratinized And Nonkeratinized Stratified Squamous Epithelium Safeguard Your Body
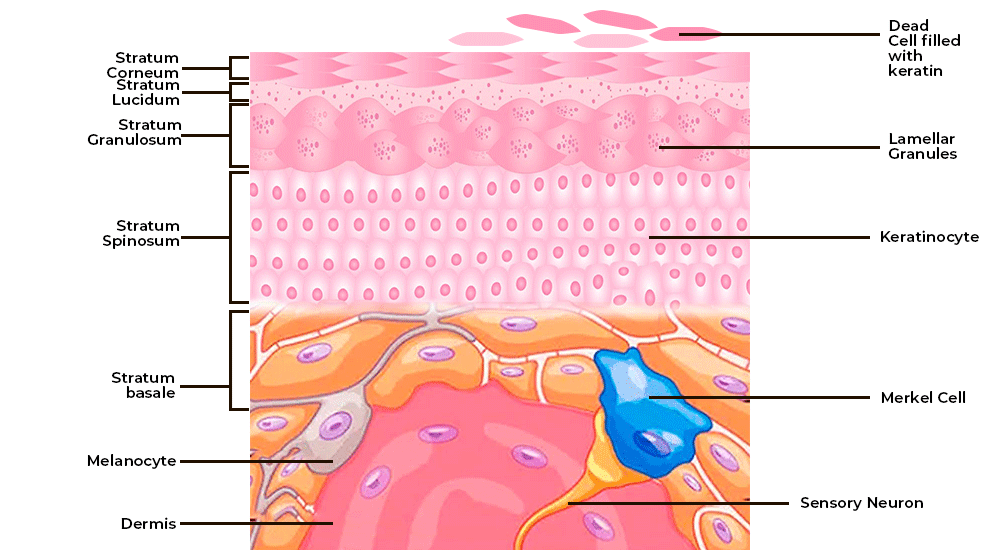
Keratinized stratified squamous epithelium is what you find in the epidermis of your skin. It's exposed to mechanical stress, dehydration, and microbial assault on a daily basis. The keratinocytes in the stratum basale divide continuously, push their way upward through the stratum spinosum and stratum granulosum, and finally become the anucleate corneocytes of the stratum corneum. This process — transepidermal differentiation — takes roughly 28 days in healthy adult skin. Each layer contributes something functional. The granulosum produces keratohyalin granules rich in filaggrin, which cross-links keratin intermediate filaments and creates the structural backbone of the barrier. Nonkeratinized stratified squamous epithelium lines the oral cavity, esophagus, vagina, and anal canal. These surfaces need to stay moist and flexible. They still provide protection, but through a different mechanism. The surface cells remain nucleated and hydrated, which means they're more permeable to water and small molecules. That's actually by design, not a flaw. The oral mucosa, for example, allows some drug absorption through its epithelium — sublingual nitroglycerin works because of exactly this property. One thing many students miss is that keratinization isn't a simple on-off switch. There's a spectrum. Masticatory mucosa in the hard palate and gingiva shows parakeratinization, where nuclei are retained in the superficial keratin layer but the tissue is still relatively tough. This is an adaptation to the specific mechanical demands of chewing. True orthokeratinization occurs in the plantar skin of the feet and the palms, where friction is highest. Calling these "types" rather than "versions along a gradient" gets you a better understanding of how the tissue actually responds to injury and repair.
I ran into a problem once when interpreting a biopsy from a patient with chronic lip biting. The lab report initially classified the lesion as straightforward hyperplasia, but the parakeratinized epithelium was showing focal basal cell atypia that was easy to overlook at low magnification. The atypia wasn't malignant — it was reactive, driven by the chronic trauma. The workaround was switching to a higher power objective, staining for p53 to confirm the proliferative activity was benign, and correlating with the clinical history of habitual lip trauma. If you're working with these tissues and see any atypia, always rule out mechanical irritation before jumping to dysplasia. The morphology can look deceptively concerning. Another counter-intuitive point: the nonkeratinized epithelium isn't weaker than keratinized tissue. It's just weak in a different way. It resists abrasion through high cellularity and rapid turnover rather than through a hardened surface. The epithelial ridges in the esophagus, for instance, interdigitate with the underlying connective tissue papillae to anchor the epithelium firmly while still allowing a slippery surface for food bolus transit. Think of it like carpet fibers versus a concrete floor — both protect, but through entirely different physical principles. There's also a common misconception that the nonkeratinized variant lacks a stratum granulosum. It has one, but it's thinner and less pronounced. The granular layer still exists because the cells still need to organize their cytoskeleton, they just don't complete the terminal differentiation program that leads to full cornification. The difference comes down to gene expression patterns in the uppermost layers, not a fundamental architectural absence.
Get the Full Details
How These Tissues Fail and What That Tells You
When keratinized epithelium is compromised — say, in a severe burn or advanced psoriasis — the barrier function deteriorates rapidly. Transepidermal water loss increases dramatically, electrolyte imbalance follows, and infection risk spikes. The body attempts to compensate by accelerating keratinocyte proliferation, which is why psoriatic plaques are so thick. But this repair mechanism is itself dysfunctional because the newly produced cells don't differentiate properly. The result is a vicious cycle of thickened but leaky skin. Nonkeratinized epithelium has its own failure modes. Chronic candidal infection in the oral cavity or esophagus exploits the moist surface, leading to pseudomembranous plaque formation. The epithelium thickens in response, a condition called epithelial hyperplasia, but the underlying vulnerability to fungal invasion remains until the moisture balance and immune environment are corrected. Immunosuppressed patients are particularly susceptible because their nonkeratinized mucosal barriers lose the inflammatory surveillance that normally keeps commensal organisms in check. A practical limitation worth noting: histological distinction between these two types on routine H&E staining can be ambiguous in small biopsies. Artifacts from fixation, sectioning thickness, and staining variability all affect how clearly keratinization appears. Parakeratin vs. orthokeratin can look nearly identical to an inexperienced eye. Special stains like PAS help visualize the fungal components in nonkeratinized mucosa, and immunohistochemistry for keratin subtypes — K1 and K10 for differentiated epithelium, K5 and K14 for the basal layer — provides additional clarity when the morphology is unclear.
I also learned the hard way that clinical correlation changes everything. A biopsy from the same anatomical site in two different patients can show radically different histological appearances depending on their history. Smokers, for example, develop focal hyperkeratosis and acanthosis in their oral epithelium that can mimic early dysplasia. Without knowing the patient's smoking history, you might overcall the severity. With it, you recognize a predictable reactive change. The tissue doesn't lie, but it doesn't tell the whole story either.
Functional Implications You Shouldn't Overlook
The keratinized epithelium of the skin also plays a role in vitamin D synthesis. UVB radiation converts 7-dehydrocholesterol in the keratinocyte-rich layers to pre-vitamin D3. This is one reason why people with extensive skin damage or those who strictly avoid sun exposure can develop deficiency despite adequate dietary intake. The nonkeratinized variants don't participate in this process because they're not exposed to sufficient UV radiation, and their cellular environment lacks the same concentration of this precursor molecule. Sweat gland ducts traverse the keratinized epidermis on their way to the surface. The surrounding epithelium adapts by forming a tight junctional seal around the duct, preventing pathogens and environmental irritants from following the gland tract inward. This is a localized modification of the keratinized epithelium that demonstrates how context-specific adaptations occur even within a single tissue type. The same principle applies to hair follicles and sebaceous glands, which modify the surrounding epithelium to support their appendage structures. If you're studying this material, don't just memorize where each type is found. Understand why it's found there. The hard palate has parakeratinized epithelium because it needs to withstand masticatory forces while remaining somewhat flexible. The vaginal epithelium is nonkeratinized and responsive to estrogen, which drives glycogen accumulation in the superficial layers — glycogen that lactobacilli ferment into lactic acid to maintain the acidic pH protective against pathogens. Every structural detail has a functional reason behind it, and connecting the two makes the material stick far better than rote recall ever will.

The take-home point is that keratinized and nonkeratinized stratified squamous epithelium represent two evolutionary solutions to the same problem: protecting the body from its environment. One hardens the surface. The other keeps it supple. Neither is universally superior. They're optimized for different conditions, and when those conditions change — through disease, trauma, or chronic irritation — the tissue responds in predictable but sometimes misleading ways. Understanding those responses requires looking beyond the textbook diagram and paying attention to what the tissue is actually doing in context.