Understanding The Axial Skeleton: Structure, Function, And Common Pitfalls
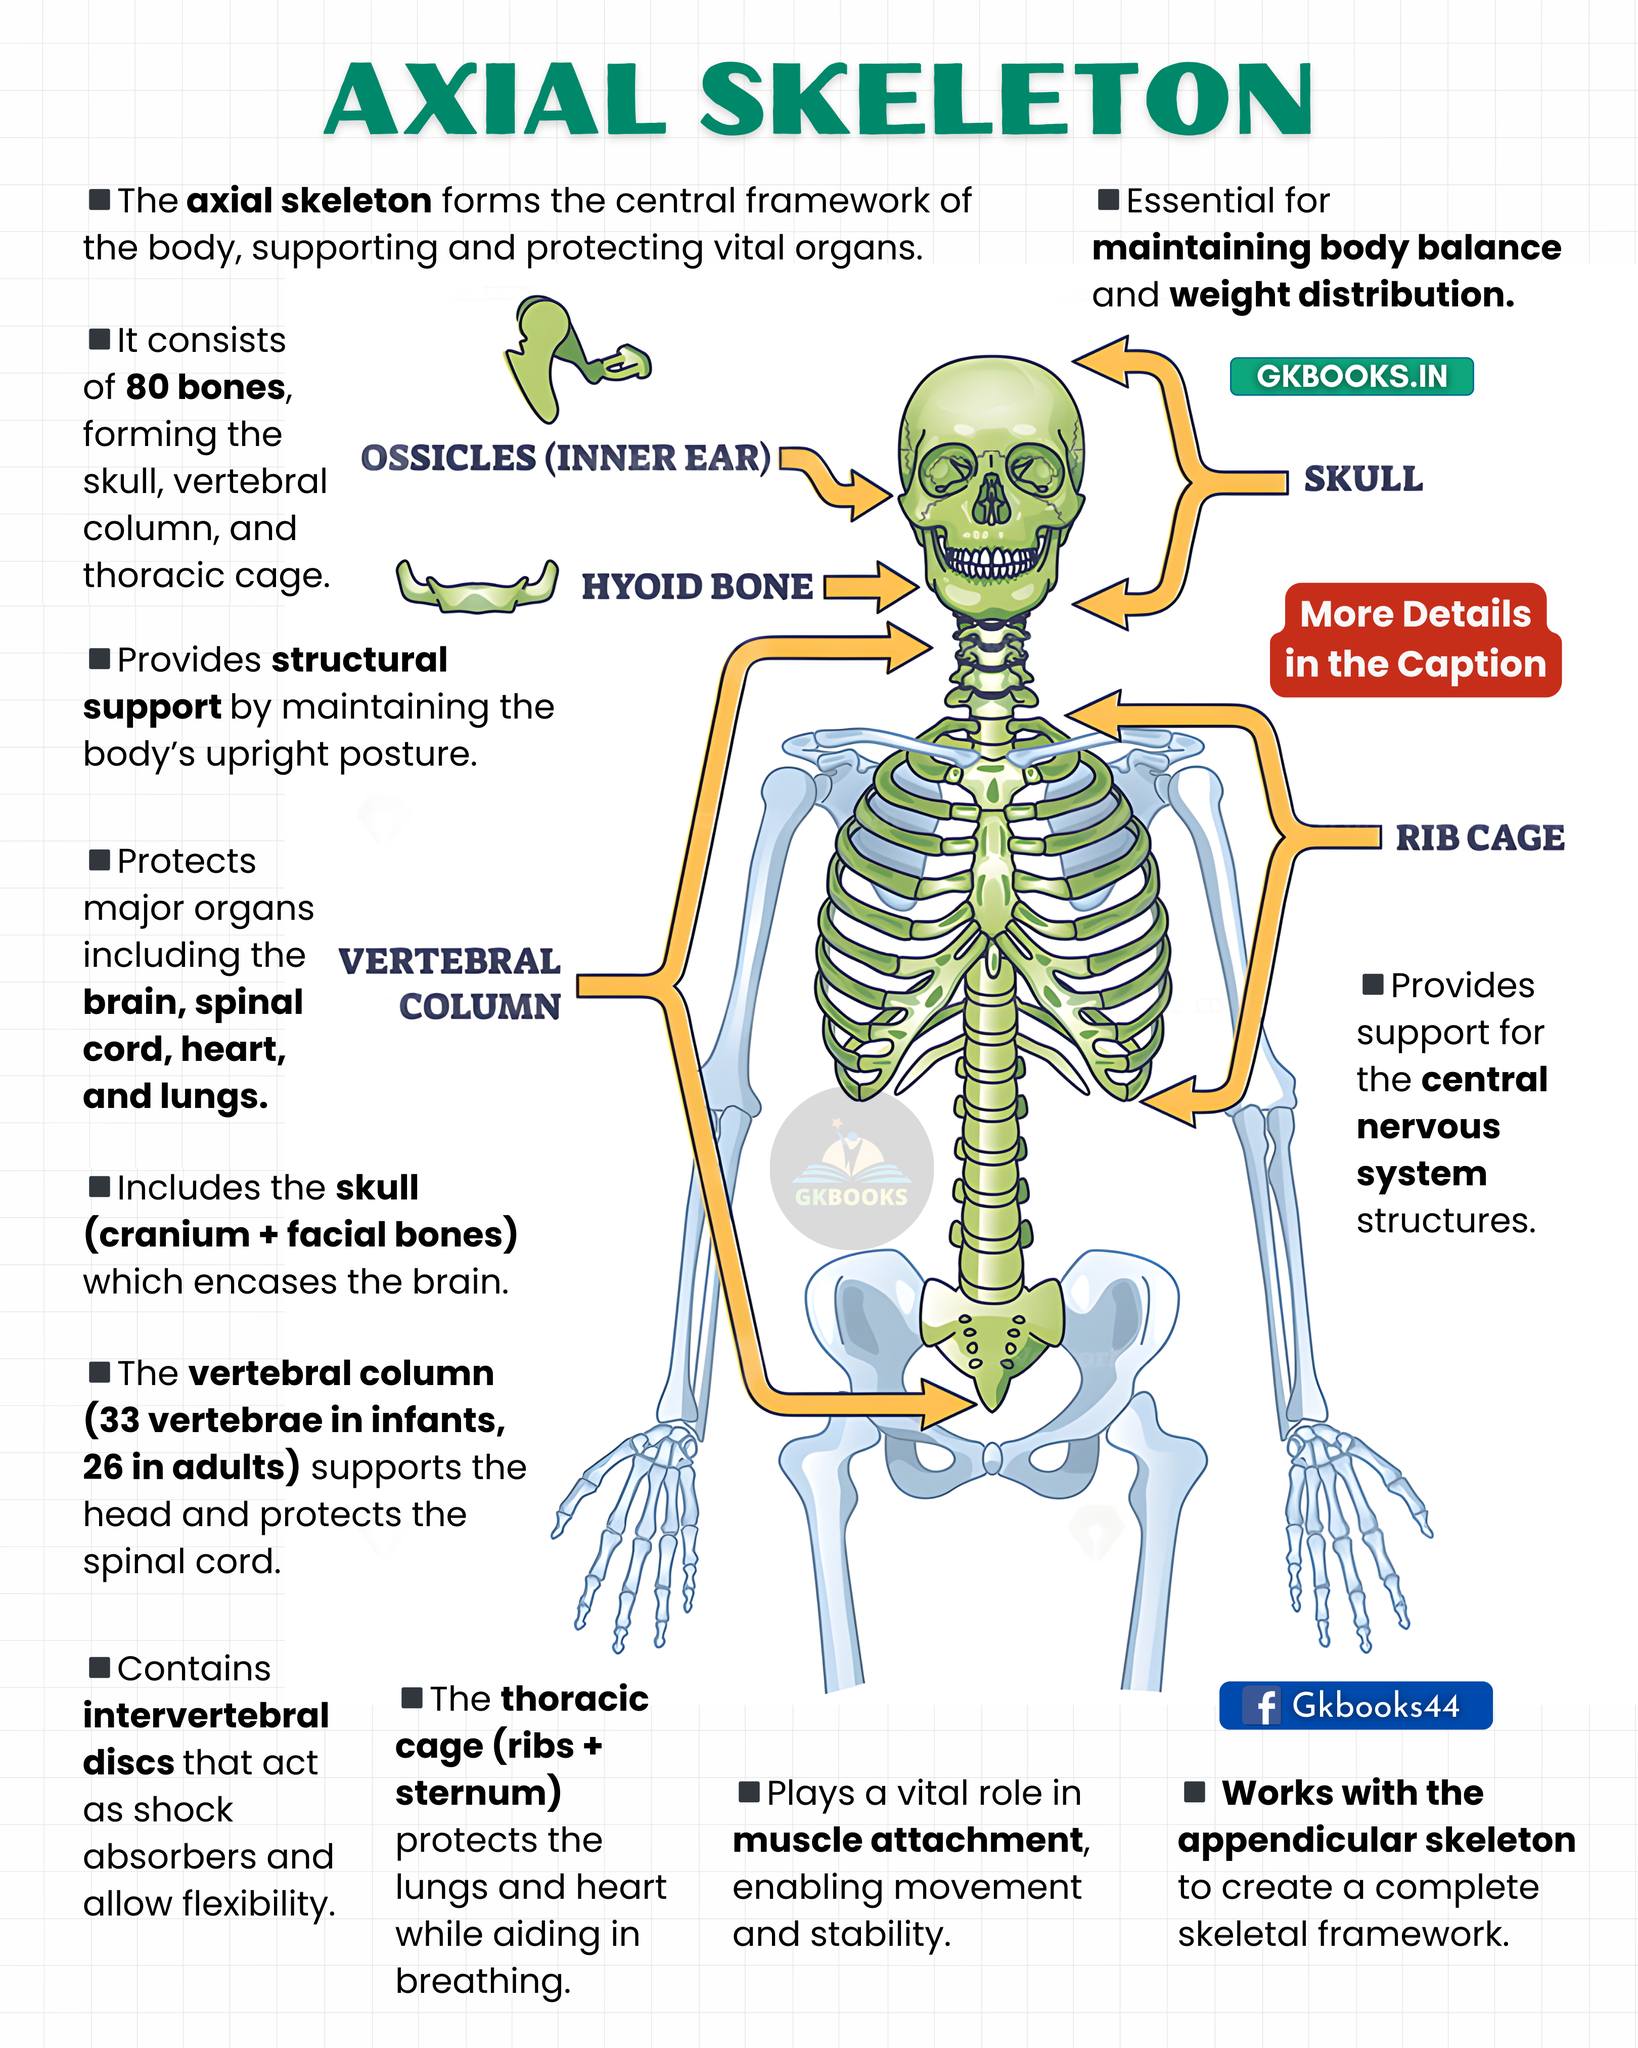
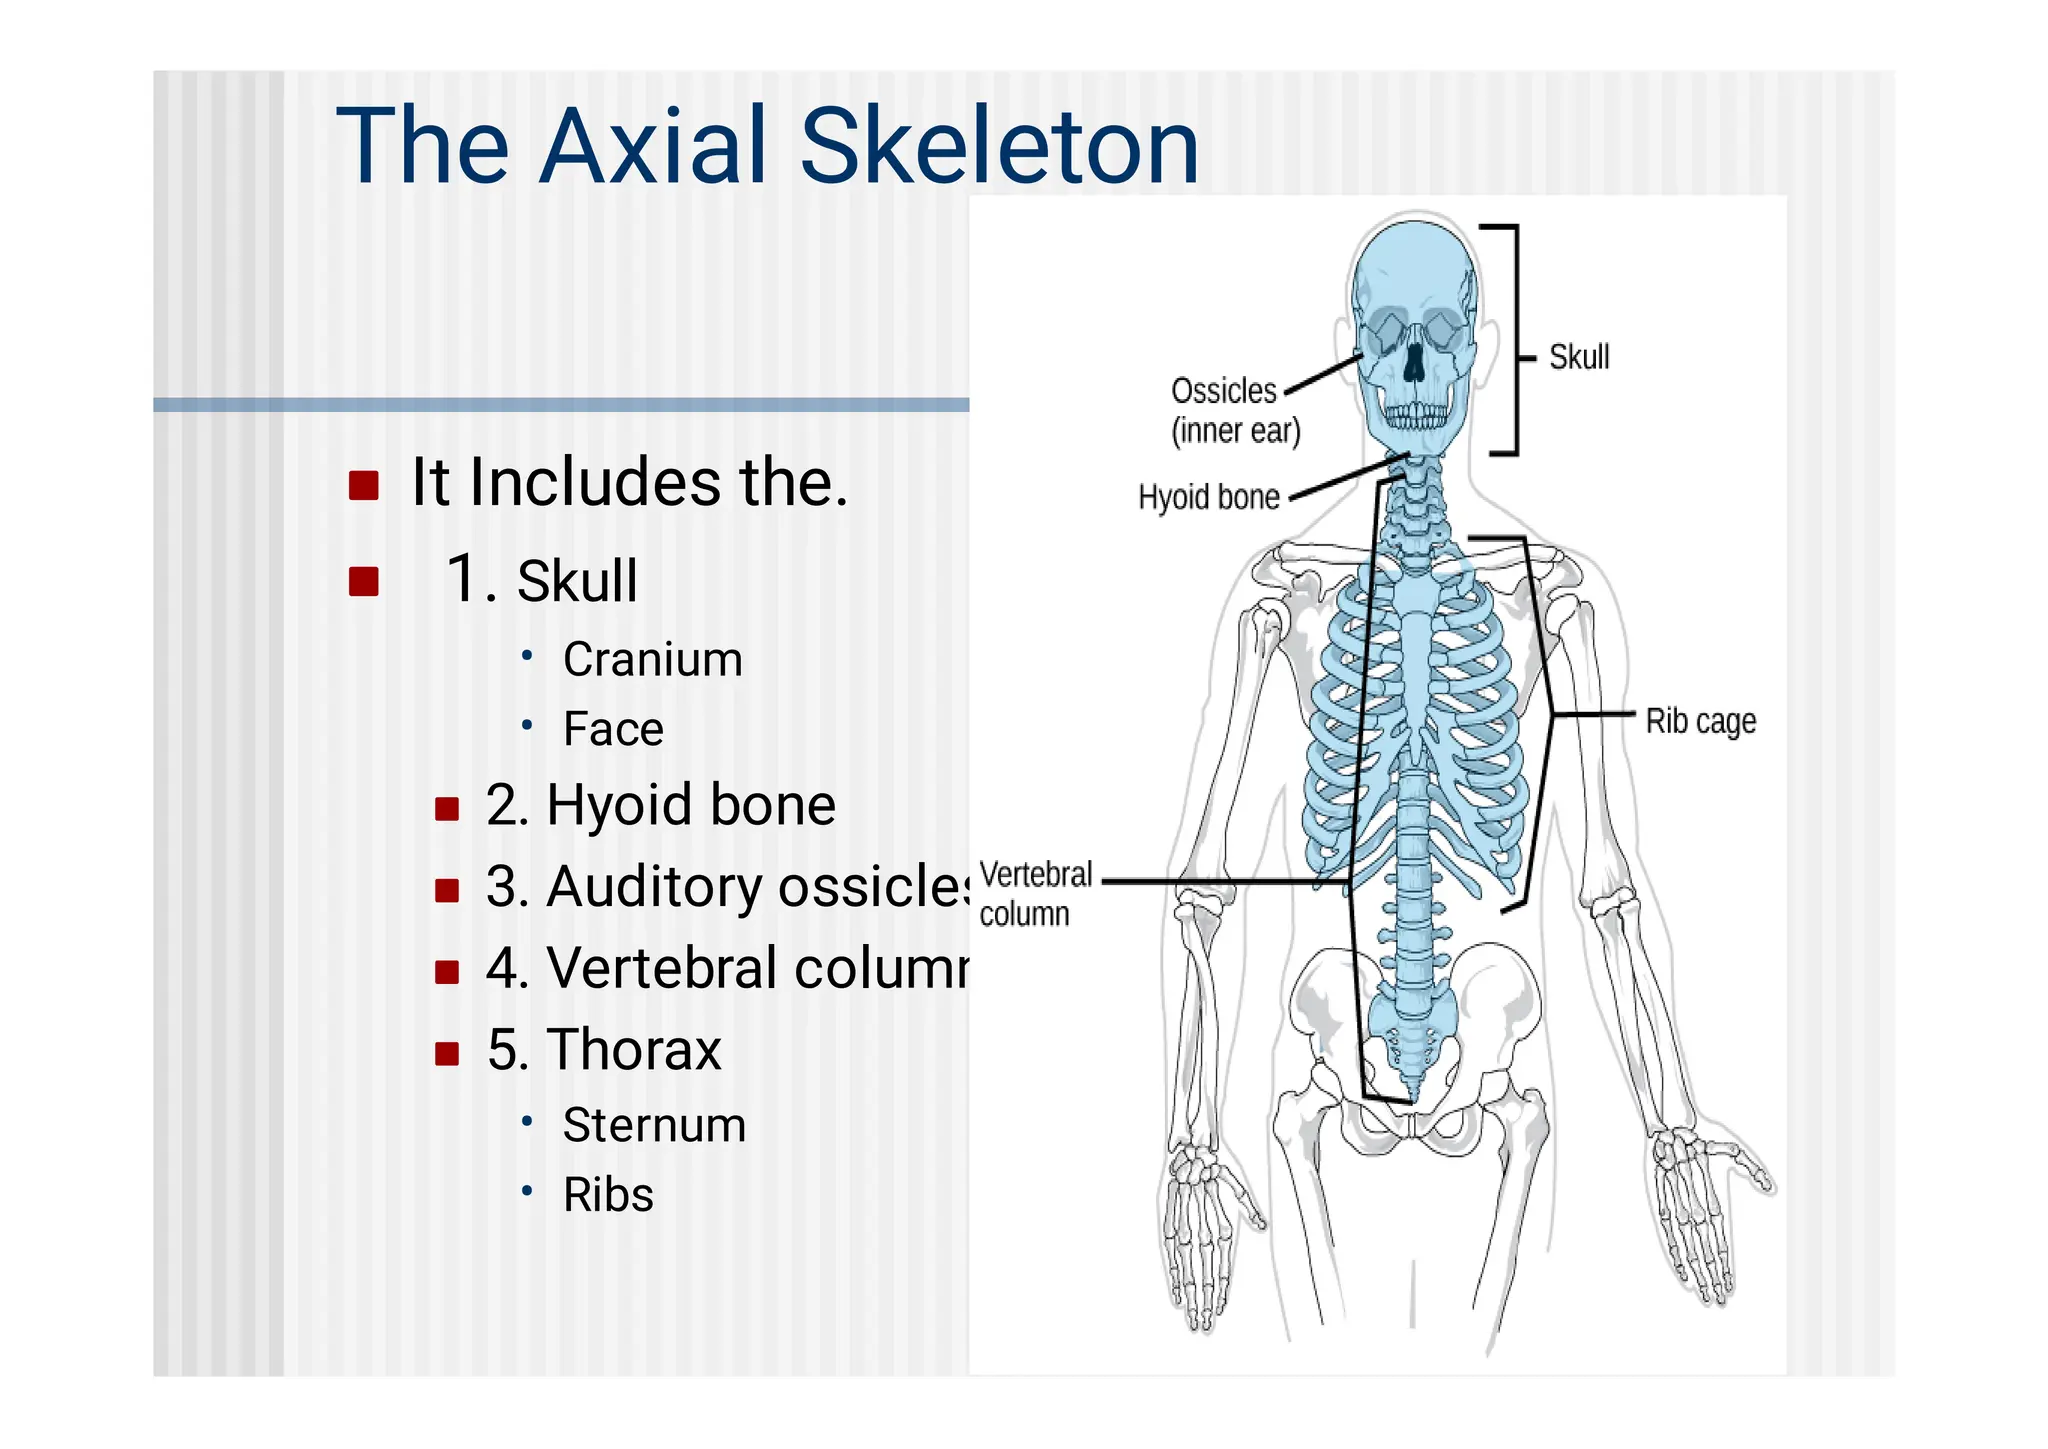
The axial skeleton is the central framework of the human body. It consists of eight skull bones, twenty-three thoracic cage bones, the vertebral column with thirty-three vertebrae, seven cervical ossicles, and the hyoid bone. That totals around fifty-eight bones that form the head, neck, and trunk axis. The appendicular skeleton attaches to this core and handles limb movement. Understanding how the axial components work together matters more than memorizing individual bone names for anyone studying anatomy or working in a clinical field. Support and mobility are not opposing functions here. The vertebral column provides structural support while maintaining extraordinary range of motion through intervertebral discs, facet joints, and ligamentous arrangements. Each functional spinal unit—two vertebrae plus the intervening disc and ligaments—moves as a coordinated segment. The skull does not sit passively on top of the spine. It articulates through the atlanto-occipital and atlantoaxial joints, which together allow approximately fifty percent of neck flexion-extension and nearly all cervical rotation. Clinicians who ignore this biomechanical coupling often misinterpret upper cervical dysfunction as a purely muscular issue. I spent years interpreting imaging and physical exams before I truly understood how the base of the skull interacts with the upper thoracic spine. A patient came in with chronic tension headaches that standard cervical treatment never resolved. The pain pattern traced clearly to the suboccipital region, but the real driver was degenerative change at T4-T5 causing compensatory hypertonicity in the suboccipital muscles. Treating only the neck gave temporary relief. We had to address the thoracic stiffness first through targeted mobilization and postural retraining, then the headaches subsided for good. I learned that lesson from watching patients bounce back from recurring symptoms because someone kept working on the wrong spinal level.
The thoracic cage is another area people routinely underestimate. The ribs are not rigid protectors. They move during respiration through costovertebral and costotransverse joints, expanding the thoracic volume by roughly three liters during a deep breath. Rib mobility decreases with age, and restricted upper thoracic rib movement forces the accessory respiratory muscles to compensate. This changes shoulder mechanics, contributes to scapular dyskinesis, and can trigger what many providers label as unexplained neck pain. Fixing breathing mechanics through rib mobilization and diaphragmatic work often resolves symptoms that otherwise get stuck in a referral chain between physiatry, orthopedics, and neurology.
Structural Details And Clinical Significance
Skull bones. The neurocranium contains eight bones: frontal, two parietal, two temporal, occipital, sphenoid, and ethmoid. The facial skeleton has fourteen bones including the maxillae, zygomatics, nasal bones, lacrimal bones, inferior nasal conchae, palatine bones, vomer, and mandible. Cranial sutures provide slight flexibility in infancy and fuse progressively over decades. Coronal, sagittal, lambdoid, and squamous sutures are the major ones. Syndactylism and craniosynostosis involve premature suture fusion and require surgical intervention, usually within the first year of life. Vertebral column. The spine divides into five regions. Cervical vertebrae C1 through C7 are the most mobile. C1, the atlas, lacks a body and supports the skull directly. C2, the axis, has the dens that serves as a pivot point for rotation. True cervical vertebrae feature transverse foramina through which the vertebral arteries pass. This anatomical detail matters because vertebral artery compression or dissection during extreme neck manipulation can cause posterior circulation strokes. I have seen cases where aggressive cervical manipulation before imaging led to devastating outcomes, especially in patients with underlying fibromuscular dysplasia of the vertebral arteries. Cervical lordosis typically measures between forty and sixty degrees. Loss of this curve, called cervical kyphosis, reduces the spine's ability to absorb axial loads and shifts stress to the disc annulus and posterior elements. Thoracic kyphosis normally ranges from twenty to forty degrees. Excessive thoracic kyphosis—often seen in elderly patients with vertebral compression fractures—increases the risk of neurological compromise and reduces pulmonary capacity significantly. Lumbar lordosis averages forty to eighty degrees. Hyperlordosis commonly associates with anterior pelvic tilt, weak abdominals, and tight hip flexors, while hypolordosis often results from prolonged sitting and deconditioning of the core stabilizers.
Get the Full Details
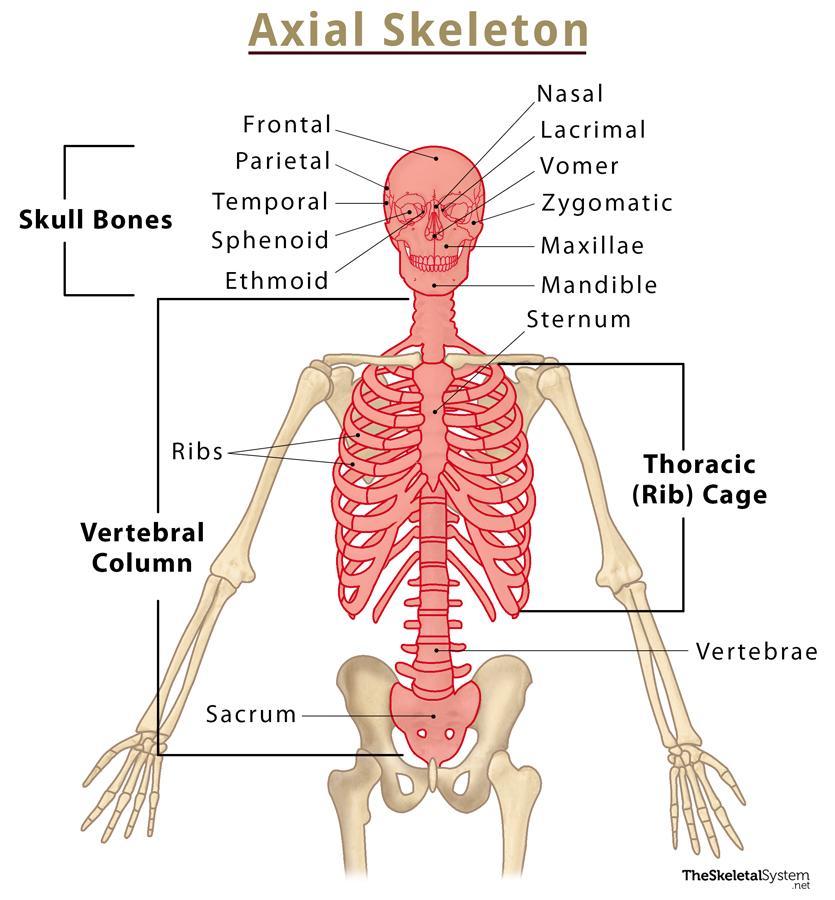
Thoracic cage. The sternum comprises three parts: the manubrium, body, and xiphoid process. True ribs connect directly to the sternum via costal cartilage. False ribs attach indirectly or not at all. Floating ribs lack anterior attachment. Rib fractures at levels one through three suggest high-impact trauma due to their proximity to the clavicle and scapula. Fractures at levels nine through twelve risk injury to the spleen, liver, and kidneys. This regional variation in fracture significance is something every trauma provider needs to internalize rather than treat all rib fractures identically. Hyoid bone. The hyoid is unique because it does not articulate with any other bone. Its in the anterior neck supported by muscular and ligamentous attachments from the styloid processes, thyroid cartilage, and scapula. Its position changes during swallowing, speaking, and breathing. Fracture of the hyoid is a hallmark finding in manual strangulation, though it occurs in only about fifty percent of confirmed cases and is more common in older adults due to progressive calcification of the hyoid cartilage. This statistical reality means a negative finding does not rule out strangulation as a mechanism.
Practical Assessment Approaches
Assessing the axial skeleton requires both structural evaluation and functional testing. Postural assessment should begin with a standing posterior view. The spinous processes should form a vertical line without lateral deviation. Shoulders should sit at equal height. Scapular positioning matters too—winging or asymmetry often reflects thoracic spine dysfunction rather than a primary shoulder problem. From the lateral view, the earlobe should align vertically with the acromion process, which should align with the greater trochanter. Forward head posture shifts this relationship and increases compressive load on the cervical spine by approximately ten pounds for every inch of anterior displacement. Range of motion testing needs region-specific norms. Cervical rotation should exceed sixty degrees bilaterally. Lateral flexion should reach approximately forty-five degrees on each side. Thoracic rotation is best assessed seated with the pelvis stabilized, expecting at least thirty-five degrees of rotation in each direction. These values drop significantly in sedentary populations and older adults, but the decline is not solely age-related. Years of repetitive unilateral loading—think painters, musicians, or assembly line workers—produces asymmetrical restrictions that standard reference values do not capture. Palpation reveals more than trigger points. Spinous process tenderness at specific levels correlates with underlying pathology more reliably than generalized back pain descriptions. Paraspinal muscle texture changes indicate chronic loading patterns. The suboccipital triangle, bounded by the rectus capitis posterior major, obliquus capitis superior, and obliquus capitis inferior, is a frequent source of referral headaches when hypertonic. I learned to palpate this region systematically after a mentor showed me that suboccipital release alone reduced headache frequency from daily to twice weekly in a cluster headache patient who had failed multiple pharmacological protocols.
Imaging interpretation requires knowing what is normal at every age. Childhood vertebrae are more wedge-shaped anteriorly. Adolescent spine imaging often reveals Scheuermann disease presenting as progressive kyphosis with vertebral endplate irregularities. Adult degenerative changes—disc space narrowing, osteophyte formation, facet arthropathy—are expected but not inevitable explanations for pain. I have seen too many patients labeled with "degenerative disc disease" at L4-L5 based on MRI findings that were actually asymptomatic age-related changes. The discrepancy between imaging findings and clinical symptoms is one of the most important gaps in spinal care today.
Limitations And When The Axial Framework Falls Short
The axial skeleton provides support and mobility, but it has clear limitations. It cannot compensate indefinitely for poor soft tissue mechanics. Chronic forward head posture, collapsed thoracic extension, and flattened lumbar curves create structural adaptations that bone alone cannot correct. Physical therapy, ergonomic modification, and movement retraining address the soft tissue and neuromuscular components that skeletal assessment misses entirely. Vertebral fractures illustrate another limitation. A compression fracture at T12 from osteoporosis may cause minimal axial pain but dramatically alters load distribution through the entire column. Without addressing the underlying bone density and the kinetic chain above and below the fracture site, subsequent fractures become likely. This cascade effect means axial skeletal problems rarely stay isolated. The skull offers rigid protection for the brain but transmits impact forces directly to the cervical spine. Concussion management must consider cervical involvement because cervical proprioceptive input contributes significantly to balance and vestibular function. A concussion protocol that ignores cervical assessment leaves a substantial portion of recovery unaddressed. I worked with a sports medicine team that added cervical screening to their concussion baseline tests and found that nearly thirty percent of athletes with persistent post-concussive symptoms had concurrent cervical dysfunction that wasnging their return to play.
When axial skeletal issues involve neurological deficits—numbness, weakness, bowel or bladder dysfunction—referral to a spine specialist is non-negotiable. Conservative management has its place, but cauda equina syndrome and progressive myelopathy require urgent surgical consultation regardless of how minor the initial presentation appears. I once managed a patient with progressive bilateral lower extremity weakness who initially presented with what seemed like routine lumbar radiculopathy. The diagnosis was a large central disc herniation at L2-L3 causing cord compression. Early recognition changed the outcome from potential permanent paralysis to full recovery after surgical decompression. Delaying referral in similar presentations remains one of the most common and costly errors in primary spinal care. The axial skeleton is not a static framework. It is a dynamic load-bearing structure that adapts continuously to mechanical demands. Understanding how its components interact, where failure patterns emerge, and when to escalate care beyond structural assessment separates competent practitioners from those who treat symptoms in isolation.