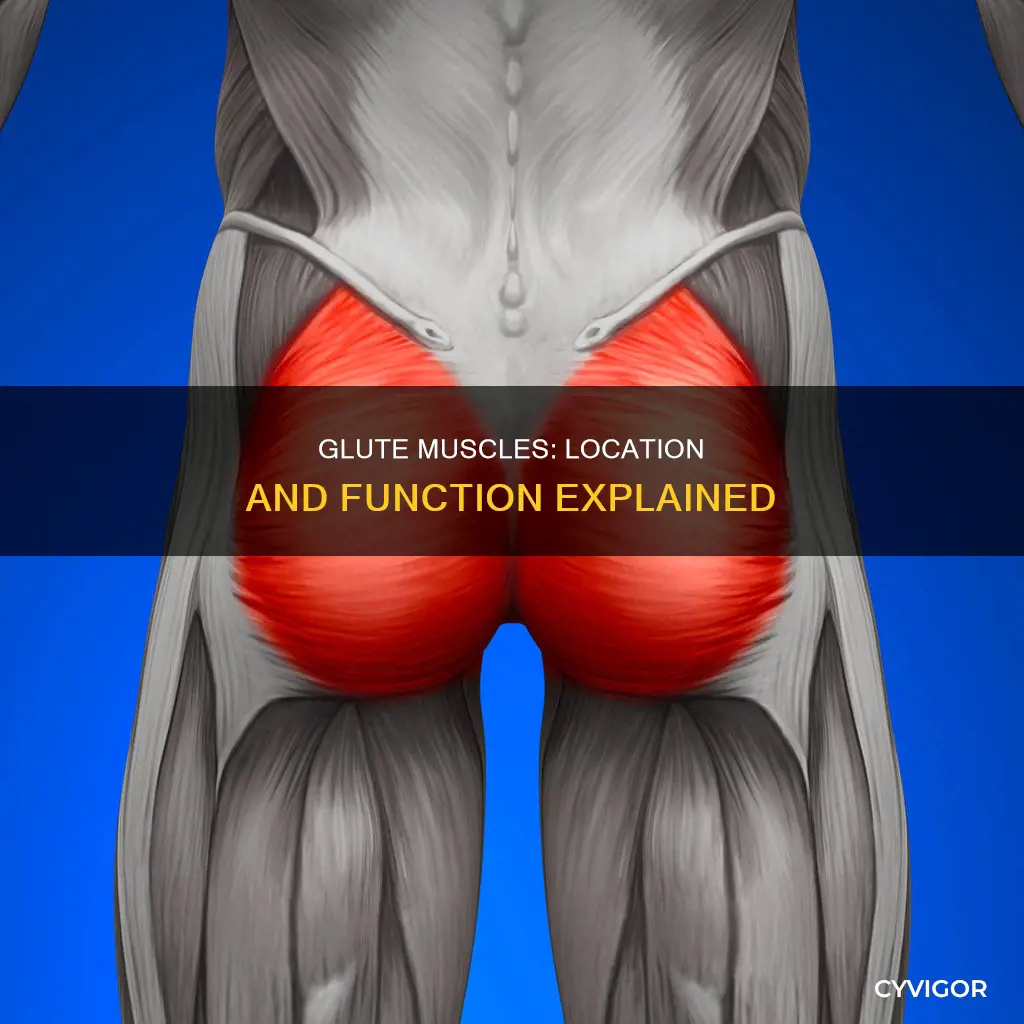
Getting Past the Simplified Diagrams Most People Use
The glute diagram you find in most fitness apps shows three blobs labeled gluteus maximus, medius, and minimus. That's useful if you're trying to explain the concept to a complete beginner in ten seconds. It's not useful if you're actually trying to train someone who keeps getting hip pain during squats. The reality is messier, and understanding that mess is what separates people who recover from glute-related injuries from people who just keep pushing through until something snaps. I spent years watching coaches use the same three-muscle model and get frustrated when their athletes couldn't unlock proper hip extension. The issue wasn't the diagram itself, but how it was being applied. A standard anatomy atlas treats these muscles like discrete switches. In practice they're a coordinated system, and when one part shuts down, the others overcompensate in ways that aren't obvious from a static image.
The Anatomy Atlas Decoding The Glute Muscle Diagram For Strength Function And Injury Prevention
How The Muscles Actually Work Together
Gluteus maximus is the big one. It's a hip extensor, external rotator, and abductor depending on which part of it you're looking at. The upper fibers extend and abduct. The lower fibers extend and adduct. The middle fibers handle horizontal abduction. This matters because when someone comes in with a weak glute max, you can't just say "weak glute max" and move on. You need to figure out which fiber group is the problem. A barbell hip thrust that loads the posterior chain through full extension might be perfect for someone whose issue is upper-fiber dominance, but it could make things worse for someone whose lower fibers are already overactive and contributing to pelvic tilt problems. Gluteus medius is where most injury prevention work actually happens. It's not a hip flexor or extensor. Its job is frontal plane stability. It keeps your femoral head centered in the acetabulum when you're standing on one leg, which is basically every movement involving a single limb. When this muscle fatigues or inhibits, the knee collapses inward, the hip drops on the opposite side, and the lumbar spine compensates. I've seen this pattern so consistently that I now screen for medius function before I ever look at a squat or lunge. If the medius isn't firing, nothing downstream matters much. Gluteus minimus sits right under the medius and does nearly the same thing, though it's harder to isolate in training because of its position. It contributes to internal rotation when the hip is extended, which is a detail most diagrams completely omit. This internal rotation component becomes relevant when you're dealing with someone who has excessive external rotation at the hip during athletic movements. The minimus might be part of the problem, or it might be the solution depending on the direction of the fault.
Piriformis is the other muscle people either overexplain or underexplain. It's a lateral rotator that also assists with abduction when the hip is flexed and adduction when the hip is extended. The problem is that piriformis syndrome gets diagnosed way more often than it actually exists. Real piriformis involvement usually presents as deep buttock pain that radiates, not just general glute tightness. Most people with "tight piriformis" actually have a medius that's locked in a shortened state from chronic compensation.
Get the Full Details

Why The Standard Model Falls Apart Under Real Training Conditions
Here's something that doesn't come up in introductory courses: the glute max is not always the primary hip extensor. During slow, controlled hip extension like a Romanian deadlift, it fires heavily. During rapid, explosive hip extension like a jump or sprint, the hamstrings take over a significant portion of the load. I had a track athlete come to me with what I initially thought was a glute max issue. Hip extension strength was adequate in the gym. But during sprinting, she was clearly hamstring-dominant with minimal glute recruitment. We spent six weeks retraining her to activate the glute max during the acceleration phase specifically, not during hip thrusts. The difference in her mechanics was noticeable after about eight sessions. The lesson was that glute max function isn't a yes-or-no condition. It's context-dependent. Another overlooked point is that glute medius inhibition doesn't always present as weakness. Sometimes it presents as overactivity that's actually dysfunctional. I worked with a client who had severe valgus collapse during single-leg movements, but her medius felt rock-hard on palpation. She didn't have a weak medius. She had a medius that was firing at the wrong time and in the wrong pattern. Normalizing the activation timing took longer than building strength would have. This happens more often than you'd think, especially in people who've been doing banded lateral walks and clamshells for months without addressing the underlying motor control issue.
Practical Screening That Actually Predicts Problems
The single-leg hip raise is the most practical test I use. Have the person lie on their side, bottom leg bent for stability, top leg straight. Lift the top hip off the ground without leaning the torso. Watch for three things: does the hip actually elevate, does the pelvis drop on the opposite side, and does the lumbar spine laterally flex to compensate? A person who can lift their hip but immediately drops the opposite side within two repetitions has medius fatigue or inhibition. A person who can't lift their hip at all has a more fundamental activation problem. A person who compensates with lumbar flexion is using their erectors to substitute for glute function, which is a common pattern in desk workers. The Thomas test variant for glutes is another useful tool. Instead of testing hip flexor length, have the person lie prone with one knee flexed to ninety degrees and let the leg fall toward the table. If the thigh doesn't drop close to the surface, the hip flexors are tight enough to be interfering with full hip extension during loaded movements. This is especially relevant for anyone doing heavy squats or deadlifts. Tight hip flexors change the starting position of the glute max, putting it at a mechanical disadvantage from the bottom of the movement.
What To Actually Do About It
For glute max activation issues, isometric holds at end range tend to produce better recruitment than dynamic movements for most people. A four-second isometric hold at the top of a hip thrust, repeated for three to five sets, will often restore activation patterns faster than adding weight or reps to a dynamic exercise. This isn't the most efficient use of training time in general, but it's effective for the specific problem of a muscle that won't turn on. For medius work, the sequence matters more than the exercise selection. Get the person firing the muscle in a non-weight-bearing position first. Side-lying abduction with a slight internal rotation bias tends to recruit the anterior medius, which is the part most people need to address for frontal plane control. Then progress to weight-bearing single-leg holds. Then progress to dynamic single-leg movements. Skipping steps here is why most programs fail. People jump into single-leg squats with poor medius activation and reinforce the compensation pattern instead of fixing it.

When This Approach Won't Help
Structural issues don't respond to glute retraining. If someone has femoral retroversion, a narrowed acetabulum, or significant femoral neck anteversion changes from a prior injury, no amount of medius work will normalize their hip mechanics. The anatomy is mechanically different, and the glute diagram you're working from doesn't account for skeletal variation. In these cases, the goal shifts from correction to management. You work with what the person has, you adjust exercise selection to avoid positions that compress the problematic structures, and you accept that the movement pattern will always look different from the textbook ideal. Referred pain from the lumbar spine is another scenario where glute diagrams mislead people. L4 through S1 nerve root irritation can produce pain in exactly the same region as gluteus medius trigger points. The pain location overlaps significantly enough that treating the glutes for months when the actual issue is a disc problem is a common mistake. If someone has neurological symptoms like tingling, numbness, or weakness that extends below the knee, the glute atlas is the wrong place to start looking. The most important thing to understand about the glute diagram is that it's a map, not the territory. Maps are useful. They help you navigate. But they're not the terrain, and walking around with a map doesn't mean you've actually learned how the land works.