Getting Your Astigmatism Lens Calculations Right
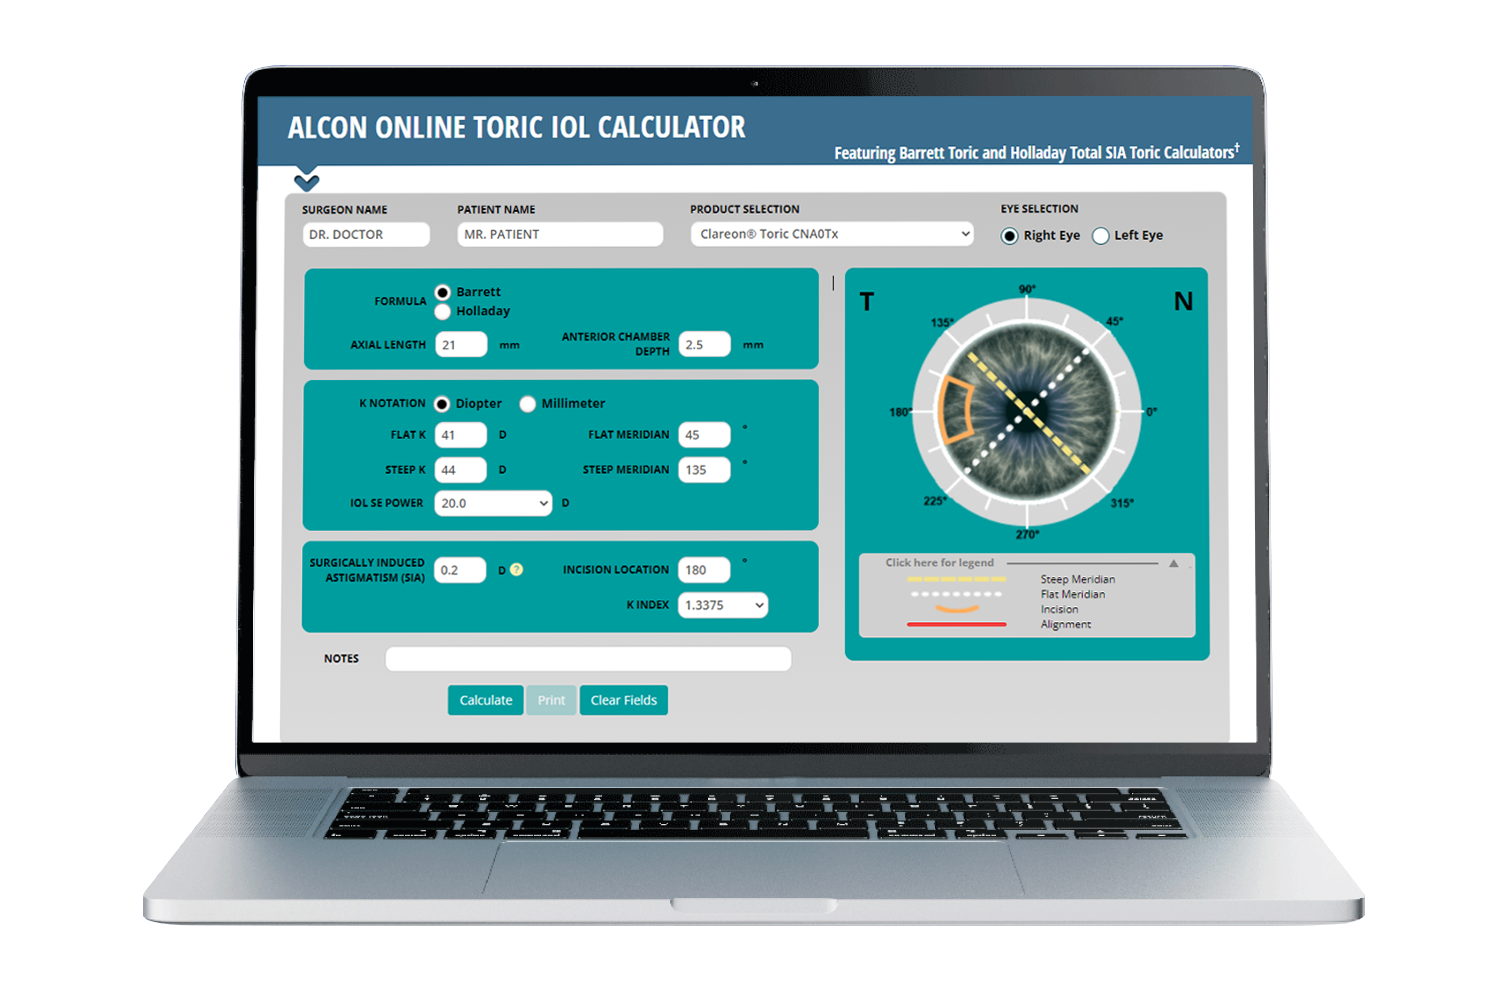
I spent years doing toric IOL calculations the old way, punching numbers into nomogram tables and hoping the math worked out when the lens landed. It didn't always. The Alcon Toric Calculator How Precision Technology Is Revolutionising Astigmatism Lens Fittings has changed that process from guesswork into something you can actually depend on, but only if you feed it the right inputs and understand what it's doing. The core idea is straightforward. You enter keratometry readings, axial length, target refraction, and some surgical parameters, and the calculator spits out a recommended cylinder power and axis for the toric lens. The precision comes from Alcon's own formulae and their real-world outcome database, which the software draws on to adjust predictions based on thousands of actual surgeries. That matters more than any textbook formula ever did.
Where Most Surgeons Go Wrong
Keratometry accuracy is where everything falls apart if you're not careful. I had a case recently where the AL scan looked fine, axial length reading 23.12 mm, but the K readings were inconsistent between eyes. Left eye showed a steep meridian of 44.50 D, right eye was 42.80 D. The calculator would have given me wildly different cylinder recommendations for each side. I repeated the measurement with a topographer instead of relying on the biometer's keratometry values, and the K readings shifted by nearly 0.75 D. That shift completely changed the toric recommendation. I ended up fitting a different lens power than the biometer data suggested, and the post-op result was spot on. Don't skip verification steps because the calculator promises accuracy. The garbage-in-garbage-out principle applies harder here than anywhere else in cataract surgery. Start with a quality SS-OCT biometry scan. The lens capsule and retina need to be clearly visualized. If you're getting multiple measurements with a standard deviation above 0.05 mm on axial length, rerun the scan before proceeding. Enter your effective lens position prediction as either the barometric or SRK/T default based on your surgeon's preference, since the Alcon calculator uses this to refine the calculation. The target refraction should account for your patient's lifestyle needs, not just a nominal zero distance. A -0.25 D myopic target often makes more sense for patients who do near work than chasing exact emmetropia. Once you input the data, the calculator provides a recommended toric IOL power and axis. The axis is calculated relative to the corneal steep meridian, so make sure your reference mark is placed correctly before surgery. I always verify the cyclotorsion estimate that the system applies, especially for patients who sit up frequently or have notable head tilt. Cyclotorsion errors of even 5 degrees can rotate the lens off-axis enough to leave residual astigmatism in the post-operative result.
Edge Cases That Break the Calculator
Post-LASIK eyes are the most common problem. The Alcon calculator assumes natural corneal power, so if the patient has had refractive surgery, you need to adjust the keratometry inputs manually or use a separate post-refractive formula. I use the Korth modification or the Barrack Adjusted K approach for these cases, then cross-check against the calculator's output. Another tricky scenario involves high corneal astigmatism above 3.00 D. The calculator may recommend a lens power that pushes beyond the standard toric IOL inventory. In those situations, I consider combining a toric IOL with limbal relaxing incisions or opting for a monofocal accommodating lens if the patient's lifestyle allows it. Patients with prior corneal pathology, such as keratoconus or pellucid marginal degeneration, are essentially off-limits for standard toric calculations regardless of what the tool suggests. The underlying corneal irregularity means the axis can shift unpredictably after surgery, and no calculator accounts for that.
Get the Full Details
Common Pitfalls
The biggest mistake I see is assuming the calculator gives a single fixed answer. It doesn't. The recommended cylinder is based on current measurements, but surgical factors like wound construction, viscoelastic removal technique, and even the surgeon's injection speed can affect final lens position and rotation. I routinely account for an expected 3 to 5 degree clockwise rotation during capsular bag implantation by adjusting the marked axis slightly preoperatively. The calculator doesn't build this into its recommendation, so you have to factor it in yourself. Another issue is relying solely on the calculator without clinical correlation. If the recommended axis seems far from where your preoperative corneal topography indicates the steep meridian should be, double-check your K readings and confirm the axis mapping. A mismatch like that usually signals an input error rather than a flaw in the calculator itself.
Building Trust Through Verification
The calculator is a tool, not an authority. Run every toric case with a post-operative refraction check at one month, and track your outcomes. I maintain a spreadsheet of calculated versus achieved cylinder power and axis alignment, and over time you'll notice patterns in your own surgical results. Some surgeons consistently over-rotate; others might have a systematic error in their axis marking technique. The calculator can't correct for those personal variables, but your own data can. If you're still debating whether to adopt this workflow, start with straightforward cases first. Regular corneas, normal axial lengths, no prior refractive history. Get comfortable with the interface and the way it presents its recommendations. Then gradually move into more complex scenarios as your confidence grows. The technology works well when you understand its limits, and it delivers consistently good results when you don't treat it as infallible.


