The Bone That Stands Between Pain-Free Arms and Chronic Shoulder Trouble
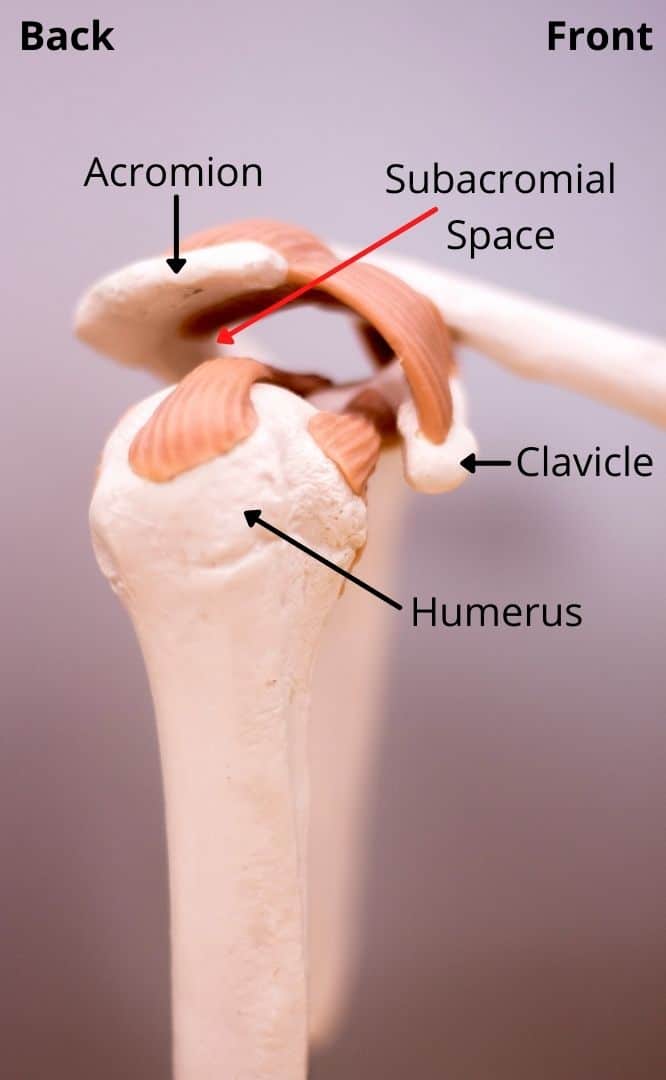
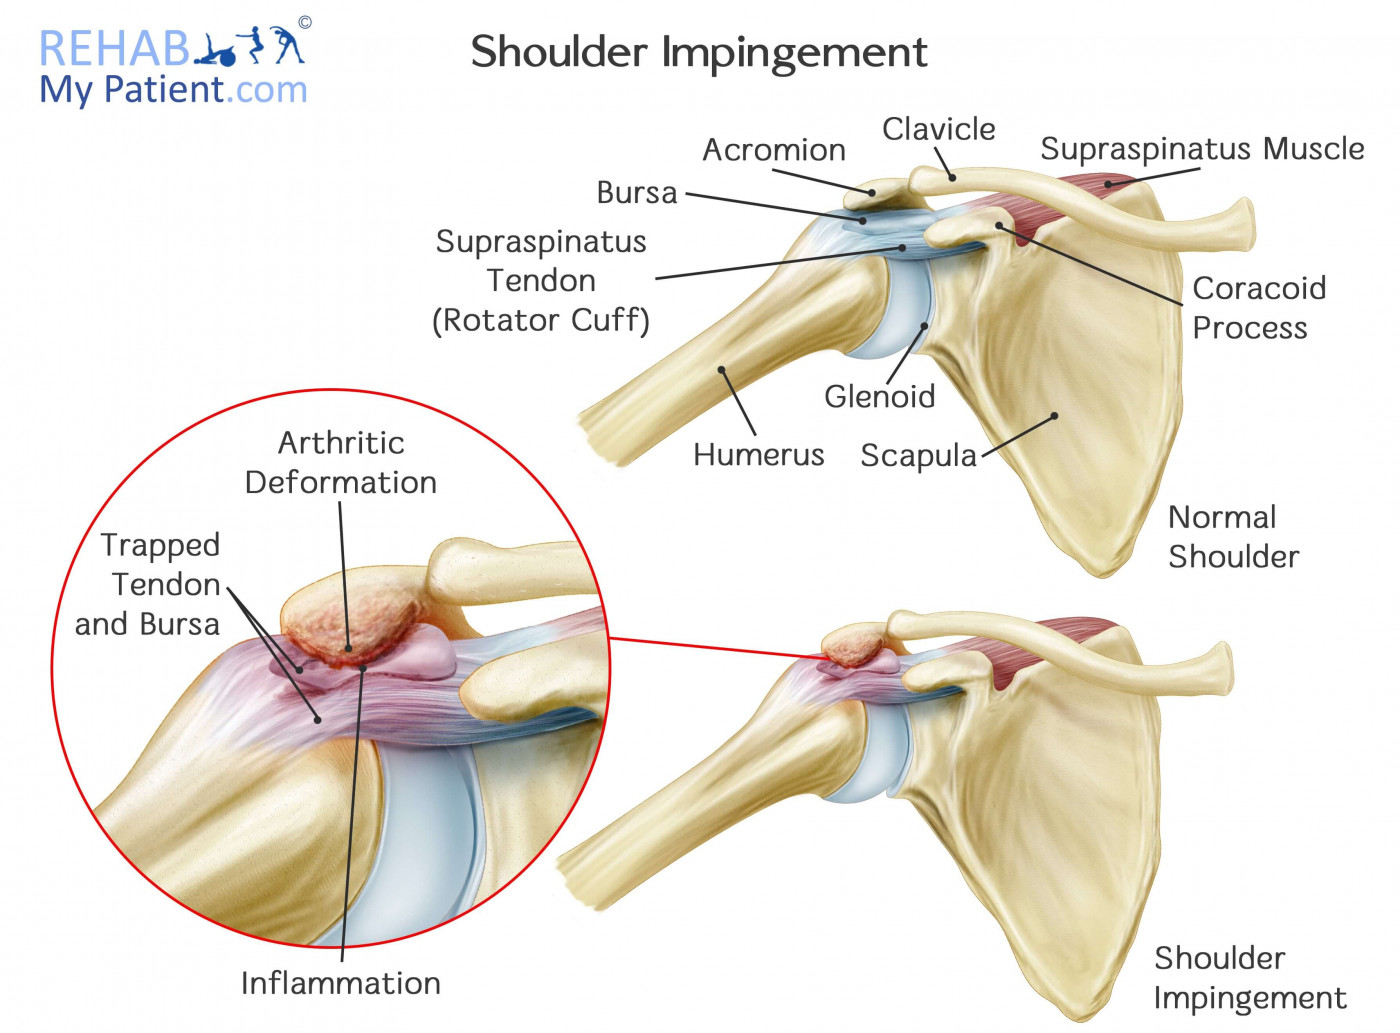
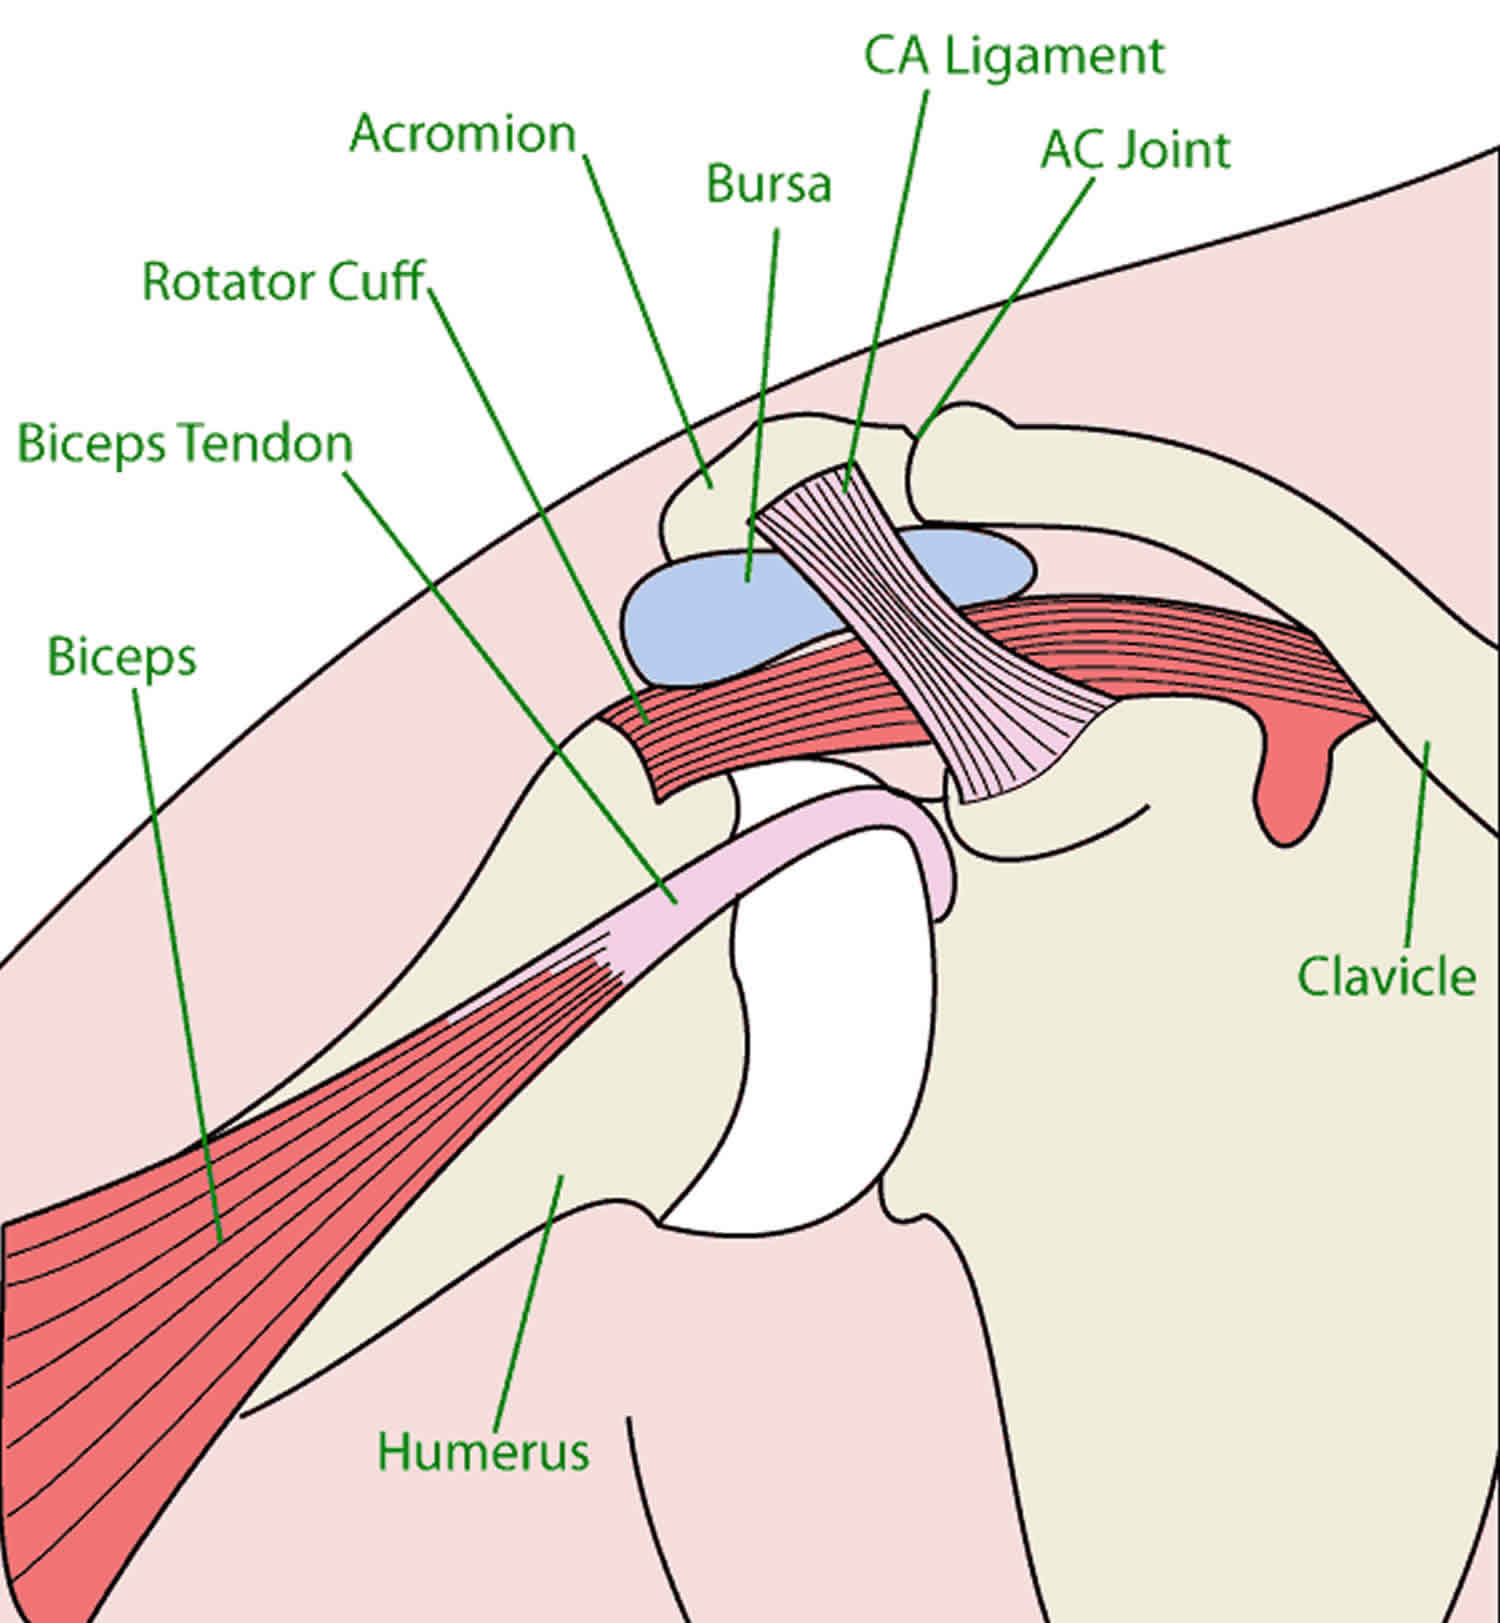
The acromion is the flat, curved bone at the very top of your shoulder blade. It juts out forward and forms the highest point of the shoulder girdle. It is not some mysterious structure. It is a bony arch that sits directly above the ball of your shoulder joint, and it works with the collarbone to form a bridge—the acromioclavicular joint. Underneath that bridge runs the rotator cuff tendons and the supraspinatus muscle. Most people never think about this bone until it starts causing problems. Here is what actual clinical work teaches you that anatomy textbooks do not always make clear. The shape of the acromion matters far more than its size. There are three main morphological types: Type I is flat, Type II is curved, and Type III is hooked. A hooked acromion (Type III) narrows the subacromial space significantly, which means the rotator cuff tendons get squeezed during overhead motion. This is the single biggest structural predictor of impingement syndrome. A flat acromion, by contrast, gives those tendons more room to glide. I once had a patient who could lift her arm to about 110 degrees without pain, then hit a hard wall. MRI showed a Type III acromion with a small bone spur on the underside. Standard conservative treatment—ice, NSAIDs, physical therapy—did nothing after six weeks. The spur was physically catching the supraspinatus tendon every time she raised her arm above shoulder height. We tried a single subacromial corticosteroid injection to reduce the swelling around the tendon, which bought enough space for her to complete a focused strengthening program. That approach got her back to normal function in about eight weeks. Without that injection, she would have been stuck in a loop of pain and further inflammation.
The coracoacromial ligament attaches to the lateral edge of the acromion and crosses over the rotator cuff like a tightrope. When that ligament thickens or calcifies, it reduces the space even more. This is why some people with perfectly healthy tendons still develop impingement symptoms. The problem is not the tendon itself. It is the architecture above it. Another counter-intuitive point: not all shoulder pain in this region comes from impingement. AC joint arthritis, which is degeneration at the joint where the acromion meets the collarbone, can produce nearly identical symptoms. The differentiating test is the Cross-Body Adduction test. If bringing your arm straight across your chest reproduces the pain right at the top of the shoulder rather than deeper underneath, the issue is likely the AC joint, not the subacromial space. These two conditions require very different treatment approaches. Common pitfalls people run into:
Many practitioners default to imaging before trying targeted physical therapy, but for a first episode of subacromial pain without trauma, the evidence supports a trial of conservative care for at least four to six weeks before ordering an MRI. Imaging findings like acromial spurs are extremely common in asymptomatic people. I have seen multiple MRIs showing significant bone spurs in patients who had zero shoulder problems. Treating the image rather than the patient leads to unnecessary surgery. The presence of a spur on an X-ray does not automatically mean that spur is the source of pain. What actually helps most people: Scapular stabilization exercises are the foundation. The acromion moves with the scapula, and if the scapula does not rotate properly during arm elevation, the subacromial space narrows dynamically. Weak lower trapezius and serratus anterior muscles are the usual culprits. A practical progression I recommend is wall slides with a focus on keeping the shoulder blade pressed down and back, followed by prone Y raises with light weights. Two sets of ten repetitions, three times per week, typically shows measurable improvement in four to six weeks. Range of motion usually improves first, then strength follows.
Get the Full Details

When conservative care is not enough: Subacromial decompression surgery—either arthroscopic or open—removes the bottom portion of the acromion and any bone spurs to create more space for the tendons. Success rates are generally around 70 to 80 percent for well-selected patients, but recovery takes approximately twelve to sixteen weeks before returning to heavy overhead work. This is not a procedure to rush into. Patients who have failed at least three months of structured physical therapy and one or two steroid injections are better candidates. Surgery on a Type I flat acromion with no visible spur and unclear impingement signs has significantly lower success rates, and that is worth considering before booking an operative slot. Prevention and long-term management:
If you work overhead—construction, painting, firefighting, certain warehouse roles—the risk of acromial-related problems compounds over years. The cumulative microtrauma to the supraspinatus tendon beneath a rigid bony arch is real. Rotator cuff tears in this population are often degenerative rather than traumatic. Maintaining scapular strength and shoulder mobility through the decades is the most practical defense available. Stretching the posterior capsule regularly also helps, because a tight posterior capsule pulls the humeral head upward into the acromion during elevation. Not every shoulder issue originates at the acromion. Cervical radiculopathy from a pinched nerve in the neck can refer pain to exactly the same region. If your shoulder pain is accompanied by numbness or tingling down the arm, or if neck movement changes the pain level, the problem may be cervical rather than acromial. A thorough exam should rule this out before any shoulder-specific treatment begins.