Understanding the Acromion
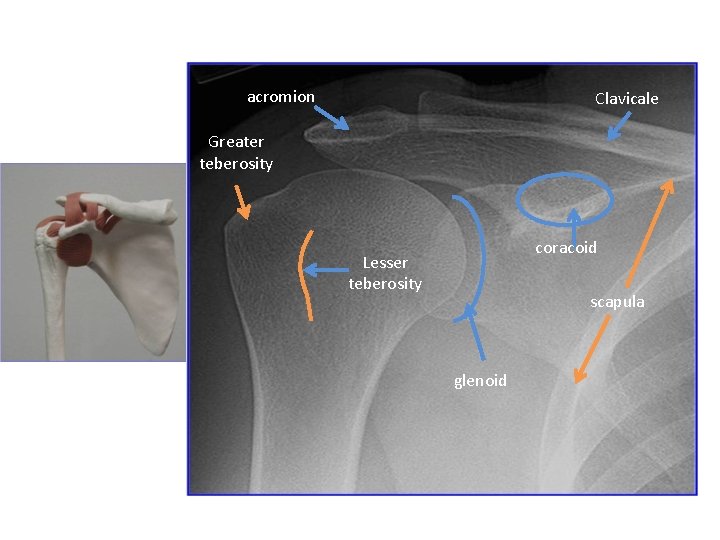
The acromion is a flat, triangular process projecting from the spine of the scapula. It forms the most lateral point of the shoulder girdle and articulates with the clavicle at the acromioclavicular joint. Most textbooks describe it as just a bony landmark, which is technically correct but misses why it matters when you're actually dealing with shoulder pathology. The shape of the acromion varies between individuals. Zide and Drehmann classified them into three types: type I is flat, type II is curved, and type III is hooked. This isn't just anatomical trivia. Type III acromions are associated with higher rates of rotator cuff tears, and the distinction matters when you're planning a decompression or assessing impingement risk. I once had a patient whose MRI looked completely normal on standard sequences until I went back and looked specifically at the undersurface of the acromion on a dedicated oblique sagittal view. There was a small but sharp osteophyte that wasn't visible on the axial slices. It was touching the supraspinatus tendon every time he abducted past 70 degrees. We ended up doing an open acromioplasty and his symptoms resolved within six weeks post-op. If you're only reading standard MRIs without focusing on that undersurface, you'll miss things like that.
The Acromion Unveiled Decoding The Shoulders Architectural Keystone
What makes the acromion functionally important is that it serves as the anterior anchor for the coracoacromial ligament, which together with the acromion itself forms the coracoacromial arch. This arch sits directly above the rotator cuff tendons and the humeral head. When the arm is elevated, the supraspinatus tendon and subacromial bursa pass beneath this arch. Any reduction in that space — whether from acromial morphology, bone spurs, or thickening of the ligament — can compress those structures. That's the basic mechanism of subacromial impingement, and it's been described since Neer wrote about it in 1972. Here's what most people don't emphasize enough: the acromion isn't a static structure. It moves. During arm elevation, the acromion translates slightly anteriorly and tilts. A study by Harryman and colleagues using fluoroscopy showed that in shoulders with rotator cuff tears, the acromion often tilts downward instead of upward, which actually narrows the subacromial space during movement. This is counter to what you'd expect. The assumption used to be that the acromion just sits there and gets in the way. But in reality, the dynamic behavior of the acromion during motion is what determines whether impingement occurs, and static imaging alone won't tell you that. When I'm assessing a patient for possible impingement, I don't rely on imaging alone. I do the Neer and Hawkins-Kennedy tests, but I also watch the scapula. If someone has scapular dyskinesis — which is more common than people realize — the acromion doesn't clear the humeral head properly during overhead movement. I had a painter who came in with what looked like straightforward rotator cuff tendinopathy. All the impingement signs were positive. But when I had him do a slow overhead motion, the scapula was winging and the acromion was dipping. We worked on scapular stabilizers for eight weeks and his pain dropped from an 8 out of 10 to a 3 without any injection or surgery. The acromion itself was fine. The problem was everything around it.
Surgical approaches to the acromion have evolved. Arthroscopic acromioplasty has largely replaced open procedures for most cases. The key is removing enough bone to create clearance without destabilizing the AC joint or weakening the deltoid attachment. I've seen complications when surgeons resect too far laterally — you can compromise the deltoid origin and end up with a weak and painful shoulder that's worse than the original problem. The rule of thumb is to remove no more than 5 to 7 millimeters of anterior acromion and to preserve the coracoacromial ligament whenever possible. That ligament is a secondary stabilizer, and taking it out changes the biomechanics of the shoulder. Fractures of the acromion are uncommon but serious. They usually result from direct trauma or a forceful contraction of the deltoid against resistance. Because the deltoid inserts along the inferior border of the acromion, a displaced fracture can disrupt deltoid function significantly. These are often missed on initial X-rays because the acromion overlaps with the clavicle and rib structures on a standard AP view. An axillary lateral view or a CT scan will clarify the displacement. If the fragment is displaced more than 1 centimeter, surgical fixation is usually recommended because conservative treatment tends to result in nonunion and chronic weakness. Acromioclavicular joint arthritis is another common issue that involves the acromion indirectly. The distal clavicle articulates with the acromion, and degenerative changes here can refer pain to the lateral shoulder and upper arm. I've treated patients who were misdiagnosed with rotator cuff pathology when the real source was the AC joint. A topical anesthetic injected directly into the AC joint is a useful diagnostic tool — if the pain disappears after the injection, you've found your problem. This saves patients from unnecessary MRIs and potentially unnecessary rotator cuff surgery.
Get the Full Details
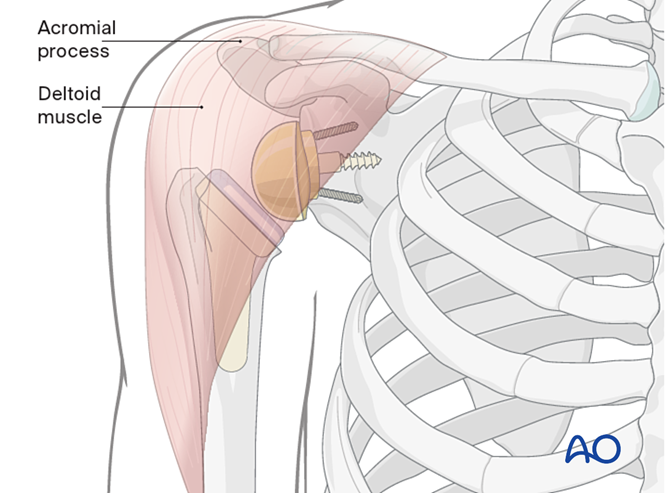
The acromion also plays a role in shoulder prosthetics. During reverse total shoulder arthroplasty, the position of the acromion relative to the new humeral component is critical. If the acromion is too close to the glenosphere, it can cause impingement and limit range of motion. Surgeons measure the acromial index — the distance from the lateral edge of the acromion to the glenoid — to plan the procedure. An acromial index greater than 0.72 is associated with a higher risk of acromial stress fractures after reverse replacement. This is something I wish more patients understood before surgery. It's a real complication that can require additional operation. There's no quick fix or single test that tells you everything about the acromion and its relationship to shoulder function. You need a combination of clinical exam, dynamic assessment, and targeted imaging. And even then, the shoulder is one of the most complex joints in the body, so assumptions based on a single finding are risky. I've changed my surgical recommendations after seeing post-operative imaging that revealed something different from what the pre-op evaluation suggested. That's just part of working with this anatomy over a long period.


