Understanding the Acromion Without the Drama
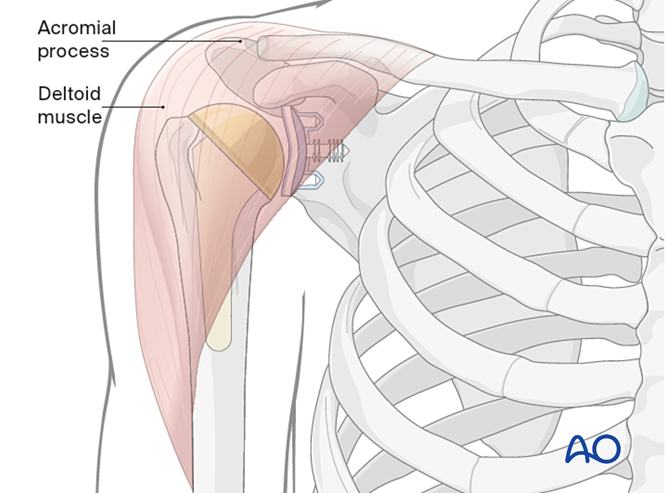
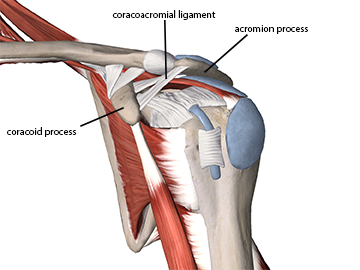
The acromion is a bony projection off the scapula that sits directly above the glenohumeral joint. It forms the roof of the subacromial space. Most people talking about shoulder pain eventually circle back to it whether they realize it or not. I am going to walk through why this small piece of bone matters so much, how to assess it properly, and where the common mistakes happen. I have spent years reading imaging and doing exams on shoulders that refuse to cooperate, and the acromion is usually the part everyone gets wrong. The term "architect" is not meant to be poetic here. It is literally structural. The acromion shapes the subacromial tunnel along with the coracoacromial ligament above it and the rotator cuff tendons below. The supraspinatus tendon passes directly underneath. The distance between the inferior acromion and the humeral head defines the subacromial space, and when that space narrows, everything compresses. That compression is what creates the painful impingement syndrome most clinicians talk about. But it is not as simple as "bone rubs on tendon." The shape of the acromion varies enough that two people with identical symptoms can have completely different problems at the same level. Wright's classification divides the acromion into three types. Type I is flat. Type II is curved. Type III is hooked. Beginners fixate on the hooked acromion as the obvious culprit. It is not always the culprit. A hooked type III can sit on someone's shoulder with zero symptoms for decades. Meanwhile, a type II curved acromion might be the one causing recurrent impingement because of how it interacts with the coracoacromial arch during abduction. The morphology matters, but so does the dynamic relationship between the acromion and the humeral head during movement. Static imaging alone will miss half the relevant information.
I had a patient recently who presented with classic lateral shoulder pain and a positive Neer impingement sign. The MRI showed a type II acromion with moderate rotator cuff tendinopathy but no full-thickness tear. Standard conservative care failed over eight weeks. We ended up getting a dynamic ultrasound exam while the patient abducted the arm, and we saw the supraspinatus getting pinched specifically at 70 to 110 degrees of elevation. The problem was not the shape alone. It was the humeral head migratio superior during that arc, driven by subtle rotator cuff dysfunction. Fixing the shift with targeted scapular stabilization work changed the whole picture. The acromion did not need to change. The mechanics around it did.
How to Assess the Acromion Properly
Start with inspection and palpation. The acromion is easily palpable along the lateral border of the scapula. Mark its inferior border with a pen. From there, you can estimate the subacromial space. Do Noter and Hawkins-Kennedy tests for anterior and superior impingement respectively. Add Jobe's test for supraspinatus integrity. If you want to get more specific, use the empty can test with slight internal rotation to isolate the supraspinatus. These are basic movements, but they are easy to do poorly under time pressure. Take your time with each one. Imaging should include an axillary lateral radiograph and preferably an outlet view. The outlet view shows the acromial shape and the distance from the inferior acromion to the humeral head. Anything less than 7 millimeters is a red flag for significant subacromial compromise. MRI is useful for soft tissue evaluation. Ultrasound gives you dynamic assessment capability at a lower cost. Use what fits the clinical question. Do not order an MRI on every shoulder pain case just to check the acromion. Most of the time it will not change management.
Get the Full Details

Treatment Approaches That Actually Work
Conservative management remains the first line for the majority of cases. This means activity modification, NSAIDs if tolerated, and physical therapy focused on rotator cuff strengthening and scapular stabilizer conditioning. The goal is to improve the position and movement of the humeral head so it does not jam into the acromion during elevation. I usually prescribe prone horizontal abduction, sidelying external rotation, and scapular retraction holds as foundational exercises. You would think these are straightforward, but I see patients doing them wrong constantly. They shrug their shoulders instead of depressing them. They use momentum instead of controlled muscle contraction. Watch the patient perform at least the first few reps. Correct the form before anything else. If conservative care fails after six to eight weeks, subacromial corticosteroid injection is a reasonable next step. It reduces inflammation in the bursa and can break the pain cycle enough to allow more effective rehabilitation. Do not use injections as a permanent solution. They wear off. The underlying mechanics do not change from the injection itself. If you rely on repeated injections without addressing the movement dysfunction, you will end up with a patient who keeps coming back every three months. Surgical intervention comes into play when there is a structural problem that cannot be resolved conservatively. Acromioplasty involves removing the anterior-inferior portion of the acromion to decompress the subacromial space. It is not the miracle cure some people treat it as. Studies show mixed long-term outcomes. The best surgical candidates are those with a clearly deformed acromion, confirmed impingement on dynamic imaging, and failure of thorough conservative care. I have seen surgeons remove too much acromion and create new problems with deltoid attachment instability. Leave enough bone behind to preserve function. A partial acromioplasty removing just the anterior edge is usually sufficient and safer than a full resection.
Common Pitfalls and What I Have Learned the Hard Way
The biggest mistake I see is treating the acromion as the sole problem. Shoulder pain is rarely just one structure. A rotator cuff tear can coexist with biceps tendinopathy, labral pathology, and cervical radiculopathy simultaneously. If you fixate on the acromion and miss the other issues, the patient stays stuck. Always do a thorough exam covering the cervical spine, scapulothoracic joint, and glenohumeral joint before committing to a subacromial diagnosis. Another pitfall is assuming that a larger or more curved acromion automatically means surgery. Size alone does not predict symptoms. I once worked with a patient who had a dramatically hooked acromion on imaging but minimal pain and full function. Surgery was discussed but ultimately avoided because the clinical picture did not support it. The imaging looked worse than the person felt. Do not let the X-ray dictate the treatment plan. Let the patient's functional limitations and exam findings lead. Post-operative rehab after acromioplasty also deserves attention. Some protocols immobilize too long and then rush back into aggressive motion. The sweet spot is early protected range of motion within the first week, gradual progression of active motion over two to four weeks, and strengthening starting around week four if pain allows. Returning to overhead activities before eight weeks significantly increases the risk of recurrence. I have seen it happen more times than I want to count.
When the Acromion Is Not the Issue
Sometimes the pain that seems subacromial actually originates elsewhere. Cervical nerve root irritation at C5 can refer pain directly to the lateral shoulder and mimic impingement perfectly. Glenohumeral osteoarthritis can present with similar symptoms. Adhesive capsulitis restricts movement and causes pain that overlaps with impingement patterns. If the exam does not fit cleanly and the response to treatment is poor, widen your differential. Do not keep chasing the acromion when the problem is elsewhere. A diagnostic injection into the glenohumeral joint rather than the subacromial space can help differentiate internal derangement from external impingement. There is also the matter of calcific tendinitis, which can cause acute severe shoulder pain that is sometimes mistaken for impingement. The calcium deposits sit in the rotator cuff tendons, often near the greater tuberosity insertion, and the pain can be excruciating. Imaging will show the calcification clearly. Treatment differs entirely from impingement management and may require needling or lavage rather than the usual anti-inflammatory approach.
Practical Takeaways
The acromion is a key structural element in shoulder biomechanics, but it is not the only thing to consider. Assess it in the context of the entire shoulder girdle. Use dynamic imaging when static images are inconclusive. Reserve surgery for clear structural indications after exhaustive conservative management. Watch your patients perform exercises and correct their form. And remember that a problematic acromion on paper does not always equal a problematic shoulder in practice. The clinical picture should always guide the decision, not the other way around.