Corpus Luteum Hemorrhagicum: What It Actually Is and What To Expect
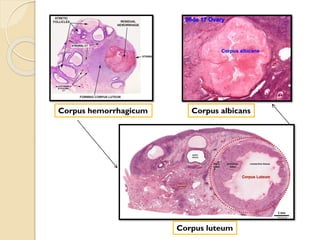
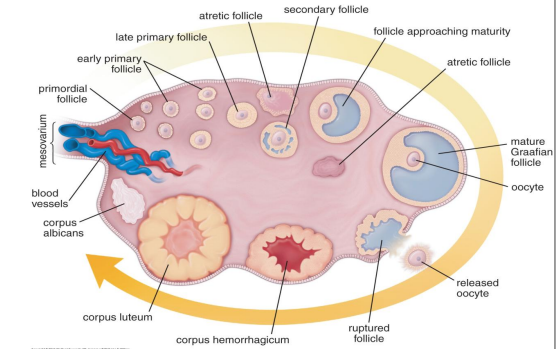
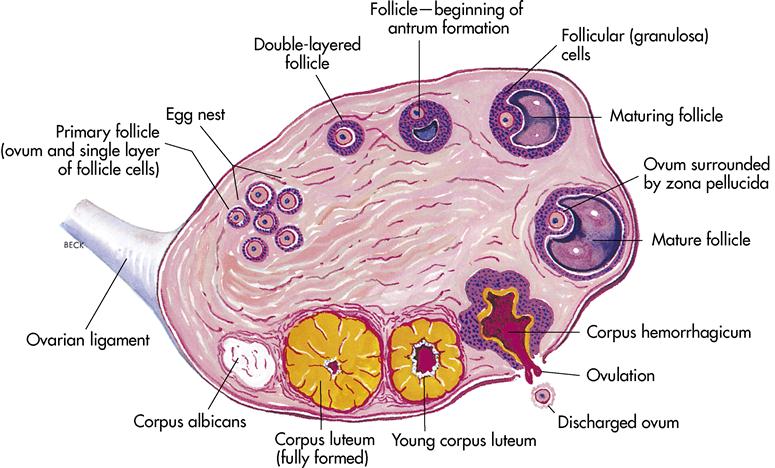
A corpus luteum hemorrhagicum is a functional ovarian cyst that forms when the corpus luteum bleeds into itself during the luteal phase of the menstrual cycle. It is common. It is usually benign. And it typically resolves on its own within one to three menstrual cycles without any intervention. The thing that makes it worth understanding is that the presentation can be surprisingly variable. I spent several years reading ultrasound reports and managing follow-up cases, and the pattern I kept seeing was that most hemorrhagic corpus luteum cysts are completely asymptomatic. They show up incidentally on scans done for other reasons. The cyst appears as a complex intraovarian mass with a characteristic reticular or lace-like internal echo pattern. That pattern is the key differentiator from other cyst types because it represents the fibrin strands forming within the blood clot inside the cyst cavity. Without that specific sonographic appearance, it is easy to mistake it for something more concerning. The size range matters more than people realize. Cysts under 5 centimeters almost never require anything beyond watchful waiting. Between 5 and 7 centimeters is the gray zone where your doctor may recommend a repeat scan in 6 to 8 weeks. Above 7 centimeters, the risk of ovarian torsion increases and the management conversation changes significantly. I once had a patient with a 9-centimeter hemorrhagic corpus luteum who presented with acute pelvic pain and nausea. The ultrasound confirmed the diagnosis but also showed mild free fluid in the pouch of Douglas, which suggested some degree of cyst rupture. We managed conservatively with pain control and close monitoring rather than surgery, and the cyst resolved over the next two weeks. That outcome was not guaranteed. About 1 to 2 percent of hemorrhagic corpus luteum cysts rupture and cause significant hemoperitoneum requiring surgical intervention.
Here is what most sources do not emphasize enough: hormonal contraception does not prevent the formation of corpus luteum hemorrhagicum cysts in the way people assume. Combined oral contraceptives suppress ovulation, which eliminates the corpus luteum entirely, so cysts cannot form. But progestin-only methods and copper IUDs do not consistently suppress ovulation, so these cysts can still develop. If you are on a progestin-only method and get diagnosed with a hemorrhagic corpus luteum, it is not a sign that the method is failing. It is just what happens when ovulation occurs. The symptoms that prompt someone to get scanned usually include unilateral lower abdominal pain, sometimes described as sharp or crampy, that appears in the second half of the menstrual cycle. Mild vaginal spotting can occur. Nausea is common if the cyst is large enough to cause mass effect. Fever and severe persistent pain are red flags that suggest complications like rupture or torsion. When I saw patients with these warning signs, I always checked serial beta-hCG levels to rule out an ectopic pregnancy, because a hemorrhagic corpus luteum can mimic an ectopic on early ultrasound. That misdiagnosis risk is real and it is one of the most important differential diagnoses to consider. Diagnosis is primarily ultrasonographic. Transvaginal ultrasound provides the best resolution for characterizing the internal architecture of the cyst. Doppler flow imaging can help distinguish a hemorrhagic corpus luteum from other ovarian masses because the peripheral vascularity pattern, often called the ring of fire, is typical of a corpus luteum. CT and MRI are rarely needed unless the ultrasound findings are ambiguous and there is concern for a neoplastic process. Laboratory markers like CA-125 are sometimes ordered but are generally unhelpful in premenopausal women because CA-125 can be elevated in a number of benign gynecological conditions including endometriosis and menstruation itself.
The management approach depends almost entirely on three factors: cyst size, symptom severity, and patient age. For a premenopausal woman with a small to moderate sized asymptomatic cyst, the standard protocol is expectant management with a follow-up ultrasound in 6 to 12 weeks. The vast majority of these cysts decrease in size or resolve completely on their own. Pain management with NSAIDs is usually sufficient. For postmenopausal women, the threshold for intervention is much lower because any complex ovarian cyst in that population carries a higher baseline risk of malignancy. A hemorrhagic corpus luteum should not form after menopause since ovulation has ceased, so a complex cyst in a postmenopausal patient warrants more aggressive workup regardless of how typical the ultrasound appearance might seem. One practical issue that comes up repeatedly is the timing of the follow-up scan. The optimal window is 6 to 8 weeks after the initial diagnosis, timed to capture at least one full menstrual cycle. Scanning too early can be misleading because the cyst may still appear complex even though it is in the process of resolving. Scanning too late means you are waiting unnecessarily. I used to see patients come back at 4 weeks and get anxious when the cyst still looked complicated. It usually still looks complicated at 4 weeks. Patience here prevents unnecessary procedures. Surgery becomes necessary when the cyst causes persistent severe pain, shows signs of torsion, grows despite expectant management, or has features on imaging that raise suspicion for malignancy. The preferred surgical approach is laparoscopic cystectomy when possible. Oophorectomy is reserved for cases where the ovarian tissue is extensively damaged or when malignancy cannot be ruled out. Postmenopausal patients with hemorrhagic corpus luteum are much more likely to undergo surgical removal than their premenopausal counterparts because the risk benefit calculation shifts significantly after menopause.
Get the Full Details

The recurrence rate is approximately 20 to 30 percent, mostly because the underlying mechanism is a normal physiological process that can happen in any cycle where ovulation occurs. There is no reliable way to prevent it other than suppressing ovulation with hormonal contraception, and even that is not 100 percent effective with all methods. Recurrence does not indicate a pathological process. It simply means ovulation happened again and the corpus luteum formed and bled into itself again. That is not a disease state. It is a normal variant of normal ovarian function. What I want to make clear here is that while most cases are straightforward, there are scenarios where conservative management is the wrong choice. If the pain is severe and worsening rather than stable or improving, if the cyst is larger than 7 centimeters in a woman who is sexually active and pregnancy has not been definitively ruled out, or if the ultrasound shows solid components or papillary projections within the cyst, those are circumstances where you need prompt gynecological evaluation rather than a wait and see approach. These features cross the line from likely benign functional cyst to potentially serious pathology.