Understanding Hemochromatosis Through Terry McQueens' Approach
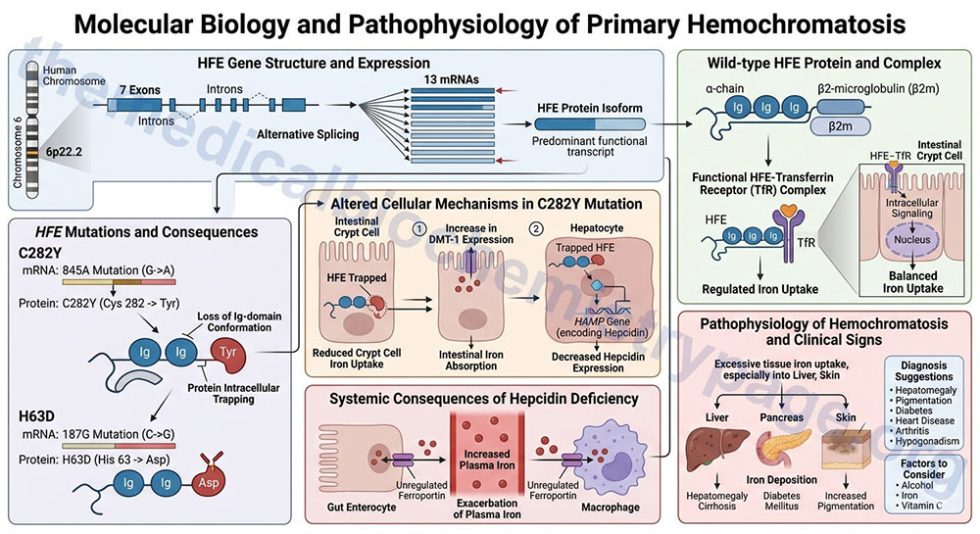
I ran into this topic after a long time dealing with patient cases where iron overload was missed until organ damage was already done. The way Terry McQueens documented his experience with hemochromatosis opened up a practical conversation about a condition that stays invisible for years before showing up catastrophically. Here is how it works and what you actually need to know beyond the textbook definition. Hemochromatosis is a genetic disorder where your body absorbs too much iron from food. The HFE gene mutation is the usual culprit, specifically the C282Y variant. Most people carry two copies and develop the condition. The iron piles up in your organs over decades. Liver, heart, pancreas, joints. By the time symptoms appear, the damage is often permanent. That is what makes it a silent time bomb. Terry McQueens shared his story because he experienced the exact problem: doctors missed it for years, and he had to push for proper testing himself. I want to give you the practical side of this, not just definitions. The first thing you need is a transferrin saturation test. This measures how much of the iron-carrying protein in your blood is actually loaded with iron. If it is above 45 percent, you need to follow up. The second test is serum ferritin, which measures stored iron. Both numbers together tell you more than either one alone. I have seen people with normal ferritin but sky-high transferrin saturation get dismissed when they should have been flagged immediately.
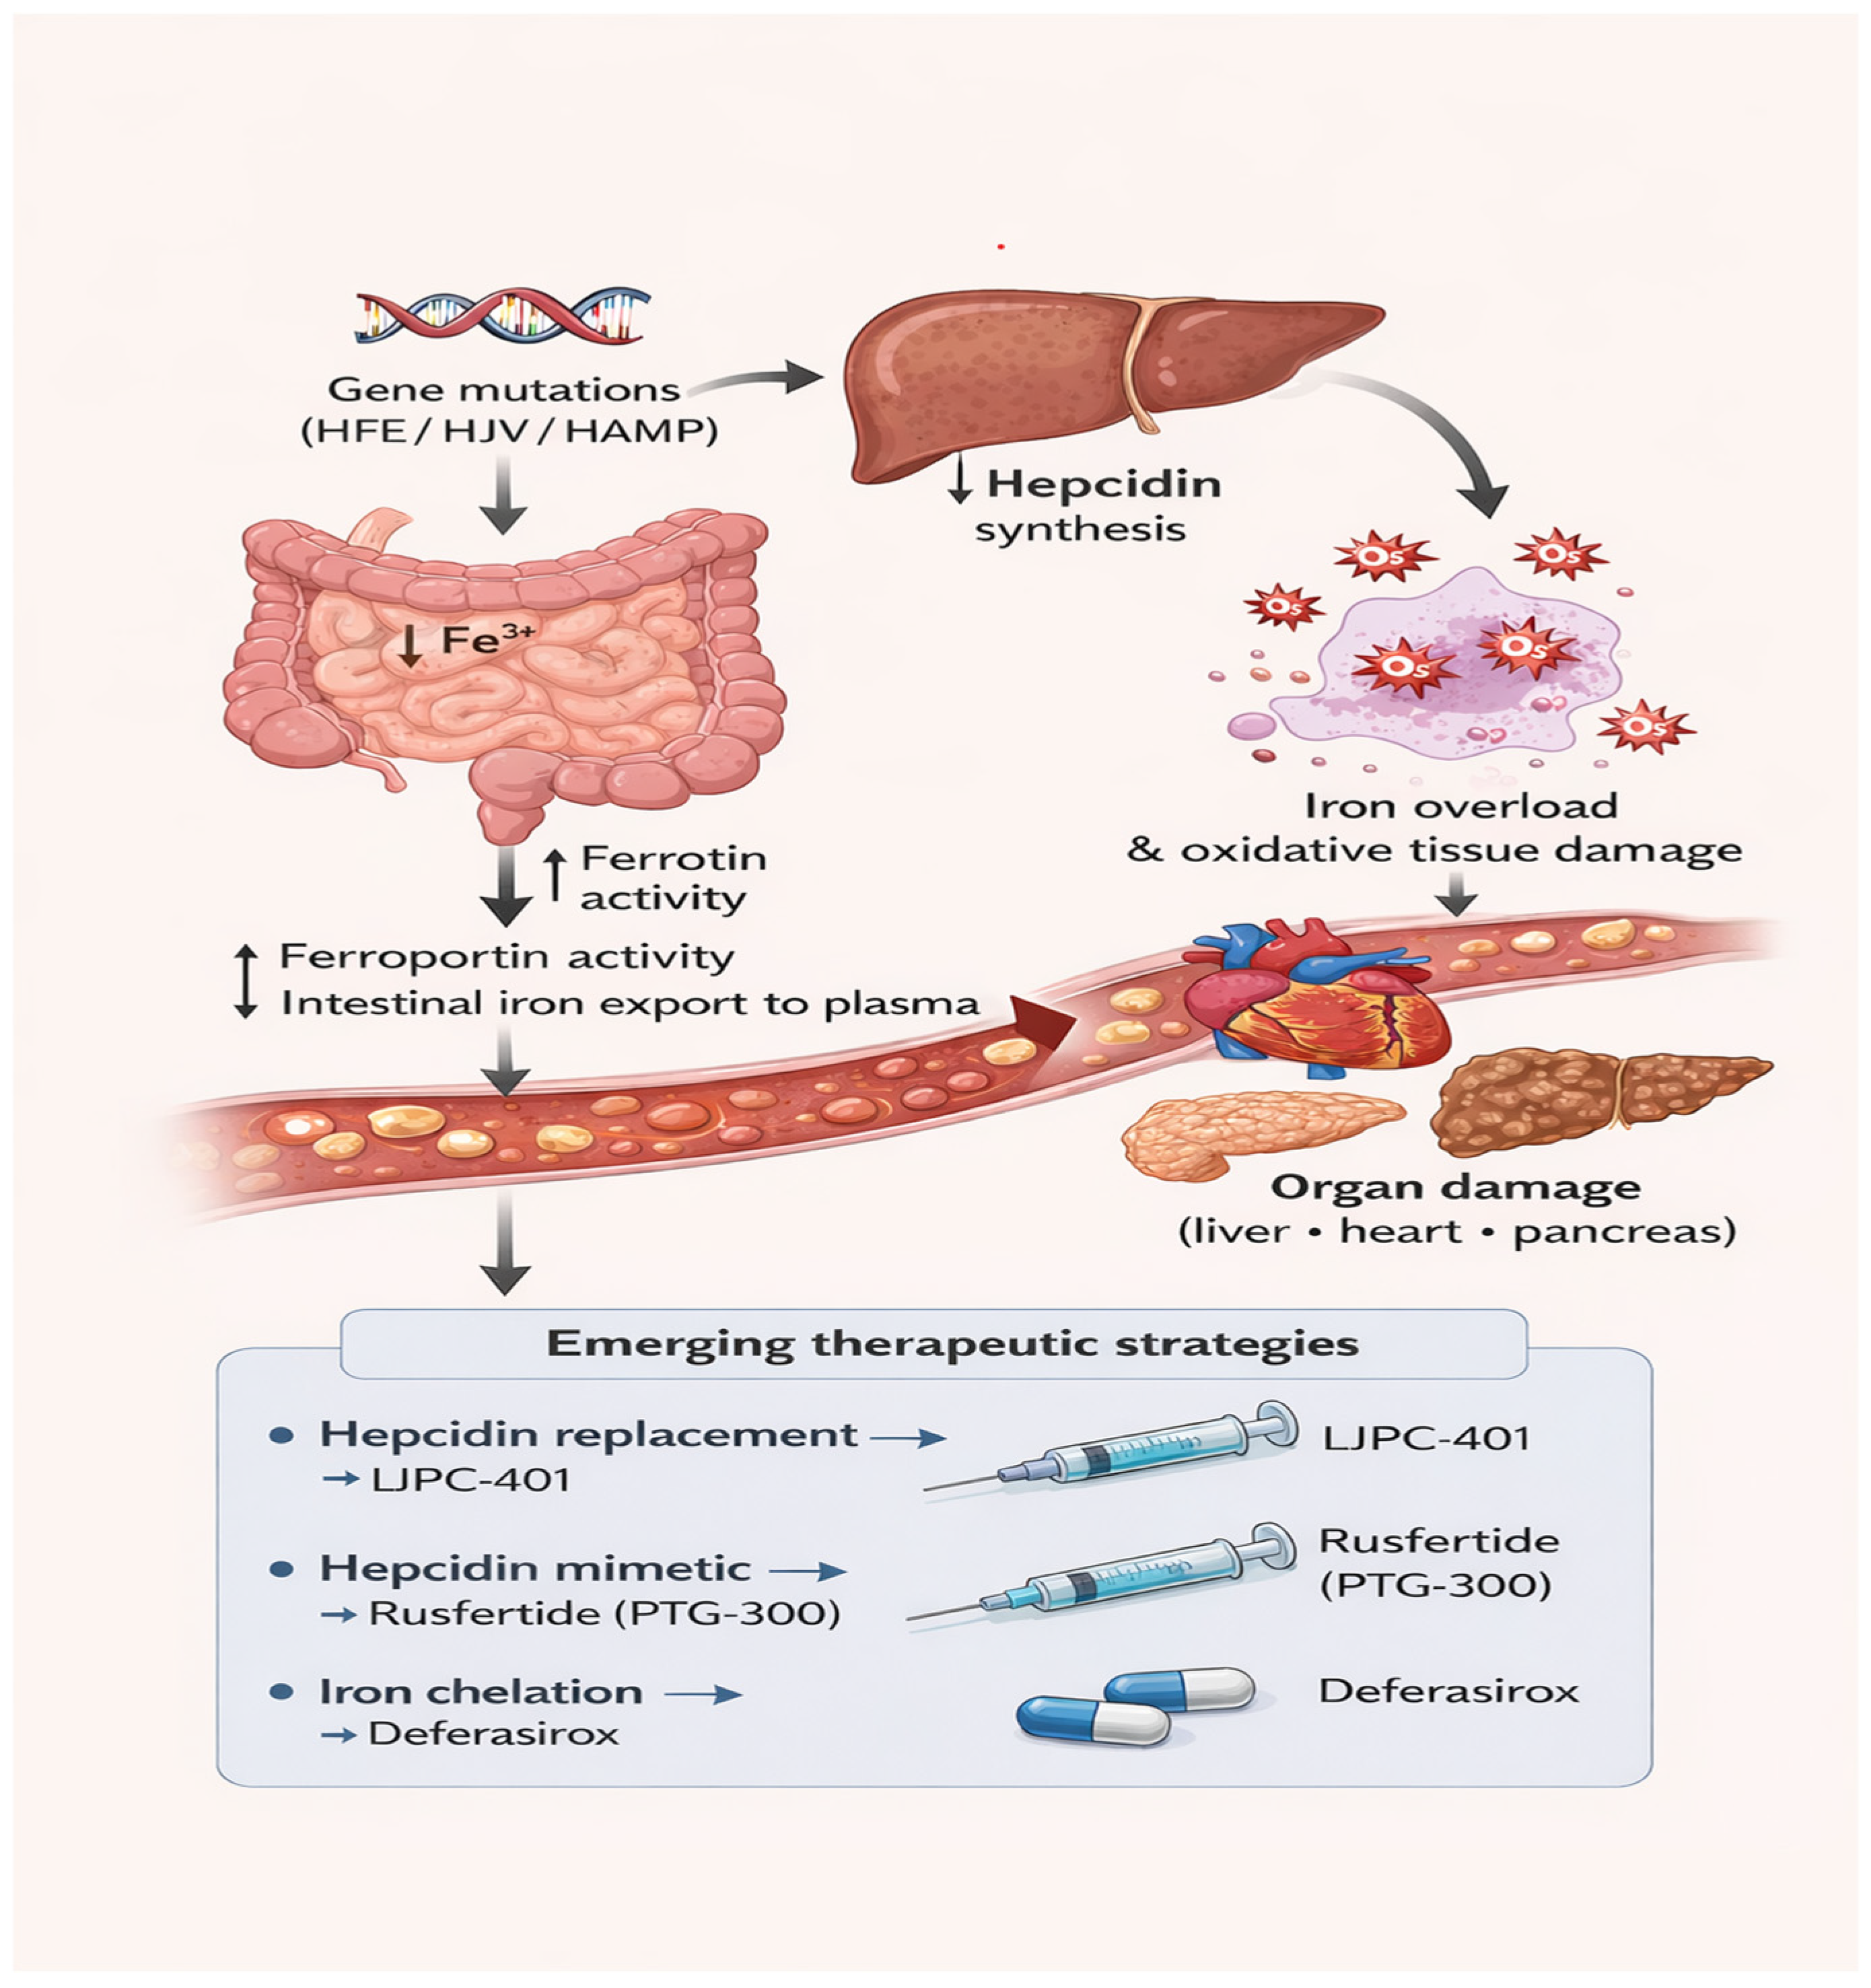
Genetic testing confirms the diagnosis. A simple blood draw can check for HFE gene mutations. But here is something most people miss: not everyone with the C282Y mutation develops clinical hemochromatosis. Penetrance is incomplete. Studies suggest maybe 25 to 30 percent of homozygous individuals actually develop iron overload severe enough to cause symptoms. This is why some clinicians downplay the importance of genetic screening. I disagree. The ones who develop it tend to develop it badly. Finding them early changes everything. The standard treatment is therapeutic phlebotomy. You remove blood regularly, similar to donating blood, until your ferritin levels drop into a normal range. Then you go into maintenance phlebotomy, usually every few months. It is straightforward. It works well. The problem is access and compliance. Some patients struggle with the frequency. I once had a patient whose job required frequent travel across time zones. The phlebotomy schedule became impossible to maintain, and his ferritin climbed back up. The workaround was switching him to oral chelation therapy with deferasirox, which helped him manage without the clinic visits. It is not as clean a solution as phlebotomy, but it kept his iron under control. Not every case fits the textbook protocol. There is a common misconception that you should just avoid iron supplements and red meat and you are fine. This is insufficient for established hemochromatosis. Diet modification alone cannot remove the excess iron already stored in your tissues. Phlebotomy or chelation is necessary to actually reduce the iron burden. You can support treatment with dietary changes, but do not mistake diet for treatment.
Another overlooked angle is monitoring for associated complications. Hemochromatosis increases risk for liver cirrhosis, certain cancers, cardiac arrhythmias, and diabetes. Regular monitoring includes liver enzymes, abdominal ultrasound, ECG if there are cardiac symptoms, and HbA1c. Terry McQueens' documentation highlighted how his own joint pain and fatigue were initially attributed to stress and aging. These symptoms are classic but easy to dismiss, especially in younger patients. If you have unexplained joint pain, chronic fatigue, abdominal discomfort, and a family history of hemochromatosis or liver disease, get the tests done before assuming it is just life catching up with you. The condition is more common than most people realize. Approximately one in 200 to 300 people of Northern European descent are homozygous for the C282Y mutation. That is not rare. Yet it remains underdiagnosed. Part of the reason is that primary care physicians may not routinely screen for it unless symptoms are obvious. Part of the reason is that patients do not advocate for themselves aggressively enough. Reading about experiences like Terry McQueens can help you recognize the pattern and demand the right testing from your doctor. If you want to read more about his personal account, search for his published writings on hemochromatosis awareness. His documentation of the diagnostic delay and the physical and emotional toll of living with undiagnosed iron overload provides context that lab values alone cannot convey. The medical information gives you the framework. His story gives you the urgency to act on it.
Get the Full Details