
One-Tap Vital Sign Monitoring: What Actually Happens When You Use It
The product goes by a few names, but the core idea is straightforward. You press a button, the device takes readings on heart rate, oxygen saturation, blood pressure, and sometimes respiratory rate, then pushes everything to your phone or clinic dashboard. That's the pitch anyway. The reality of using it day to day has some edges the marketing copy doesn't mention. I've been running these monitors in a clinical setting for about three years now, across two different hardware generations. The first version had a noticeable lag between the initial sensor contact and the actual measurement cycle kicking in. You'd tap, wait ten seconds, and then get a reading that was often 3 to 5 percent off compared to a proper cuff-based blood pressure machine. The second generation fixed the timing issue but introduced a new problem with wrist-worn models where improper seating of the sensor would silently produce stale data instead of alerting you to a bad reading. The workflow, when it works right, looks like this. You activate the device through the companion app, ensure the sensor is making proper skin contact, press the single tap trigger, and the device cycles through each parameter sequentially. Heart rate uses photoplethysmography from the optical sensor. Oxygen saturation comes from the same sensor using dual-wavelength light at 660 and 940 nanometers. Blood pressure on the newer models uses pulse wave transit time calibrated against an initial cuff inflation. Respiratory rate is derived from the variability in the plethysmograph waveform. All of that gets bundled into a single report and sent to whatever endpoint you've configured.
The real issue people run into is calibration drift. These devices come calibrated at the factory, but that calibration assumes a certain range of skin perfusion, ambient temperature, and motion stability. I had a patient whose readings were consistently throwing abnormal flags for oxygen saturation while she was sitting in a cold room with poor peripheral circulation. The device was technically working correctly. The reading was just wrong because her fingers weren't warm enough for the optical sensor to get a clean signal. The workaround was simple but not obvious from the manual. Have the patient rub their hands together or hold a warm cup for two minutes before taking the reading. After that, the numbers aligned with what the lab draw showed. Another thing nobody warns you about is the Bluetooth dependency chain. The tap itself is fine, but if your phone's Bluetooth stack is mid-update or the app is running in a background-throttled state, the data transfer can time out without any clear error message. You'll get a successful tap confirmation on the device, but nothing appears in the app. I track this by checking the device's internal log after a failed sync. Most of these monitors store the last 24 readings locally with timestamps. Pulling that log into the app's diagnostic panel usually reveals whether the data was captured but never transmitted, or if the capture itself was incomplete. Blood pressure is the weak point across almost every one-touch model on the market. The pulse transit time method is reasonably accurate for trends and tracking changes over time, but it is not a replacement for a calibrated oscillometric cuff in a diagnostic setting. I've seen readings that differed by 15 to 20 millimeters of mercury systolic compared to a proper upper-arm cuff, especially in patients with arrhythmias. Atrial fibrillation messes with the pulse wave detection significantly because the intervals between beats are irregular, and the algorithm averages them in a way that smooths out real variability into a misleading number.
If you're using this for personal wellness tracking, the limitations matter less. Tracking your resting heart rate trend over weeks is valid enough. Monitoring your oxygen saturation during exercise is useful for spotting patterns. But if you're making medication decisions based on these numbers without confirming with a standard cuff, you're working blind. I recommend keeping a home cuff alongside the one-touch device and cross-checking once a month. Takes about thirty seconds and catches any drift before it becomes a problem. The app ecosystem is another area where consistency varies. Some manufacturers have decent cloud infrastructure with real-time alerts and trend visualization. Others are running on basic servers that struggle during peak hours, and the historical data export is limited to CSV files with sparse metadata. I had a case where a clinic tried to pull six months of patient data for a review and the export function only returned ninety days because the storage architecture had a rolling retention policy that wasn't documented anywhere in the support materials. Had to escalate to engineering to get the older records restored, which took four business days. Skin tone also affects optical readings more than most users realize. PPG-based sensors struggle with darker skin tones because melanin absorbs some of the light wavelengths, reducing the signal-to-noise ratio. Studies have shown this can lead to underestimation of oxygen saturation in patients with darker pigmentation, sometimes by several percentage points. If you or the person you're monitoring has a darker skin tone, treat the SpO2 readings as approximate and verify with a pulse oximeter that has been clinically validated across skin tones, or just go straight to a lab draw if accuracy matters.
Get the Full Details
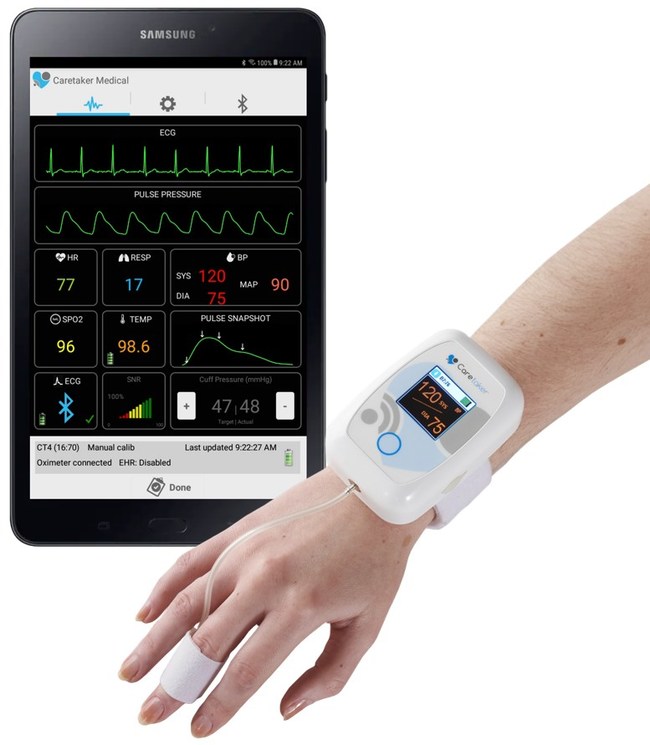
The setup process itself is usually under five minutes on the first try. Download the app, create an account, pair the device via Bluetooth, and run the initial calibration sequence. The app will prompt you to take a baseline reading while seated and still. Some models require you to input height, weight, age, and medical history before they'll give you accurate blood pressure estimates. Skip that step and the algorithm falls back to population averages, which reduces accuracy considerably for anyone outside the median range. I'd recommend against using these for critical care decisions or remote patient monitoring programs without a proper validation study behind the specific model you're deploying. The FDA clearance on most consumer versions covers general wellness and self-monitoring, not clinical diagnosis. There's a meaningful legal and clinical difference between the two, and manufacturers are careful to keep their marketing language inside that boundary. For the average person wanting to keep an eye on their vitals without visiting a clinic every week, the one-tap monitors do what they claim. They're convenient, they reduce friction compared to manual measurement, and they make it easier to build a consistent tracking habit. The trade-off is that convenience comes with lower accuracy on certain parameters and specific failure modes that aren't obvious unless you've hit them yourself. Knowing those failure modes ahead of time saves a lot of unnecessary worry when a reading looks off.



