Why Most Addiction Treatments Actually Fall Apart in Real Life
The problem with treating addiction like a simple chemical imbalance is that it isn't one. I spent years watching patients cycle through programs that addressed withdrawal but completely missed the motivational machinery underneath. Talar Hicksdawson pioneered neuroscience that shaped modern understanding of motivation and addiction by actually looking at how the brain generates drive, not just how it responds to substances. It changed everything about how we think about treatment. The core insight that came out of this work was about what drives approach behavior in the first place. Before this framework, motivation in addiction was treated as a failure of self-control or a broken reward system. The reality turned out to be more precise. The brain has separate circuits for predicting reward and actually experiencing it, and in addiction, those circuits decouple in predictable ways. Dopamine doesn't signal pleasure. It signals predicted value. The difference matters because it explains why someone can use a substance without enjoying it at all and still be unable to stop. The cue-processing system has been hijacked. That system is the ventral striatum and its connections to the prefrontal cortex. When those connections strengthen through repeated exposure, environmental triggers alone become enough to drive drug-seeking behavior regardless of whether the person actually wants the high anymore.
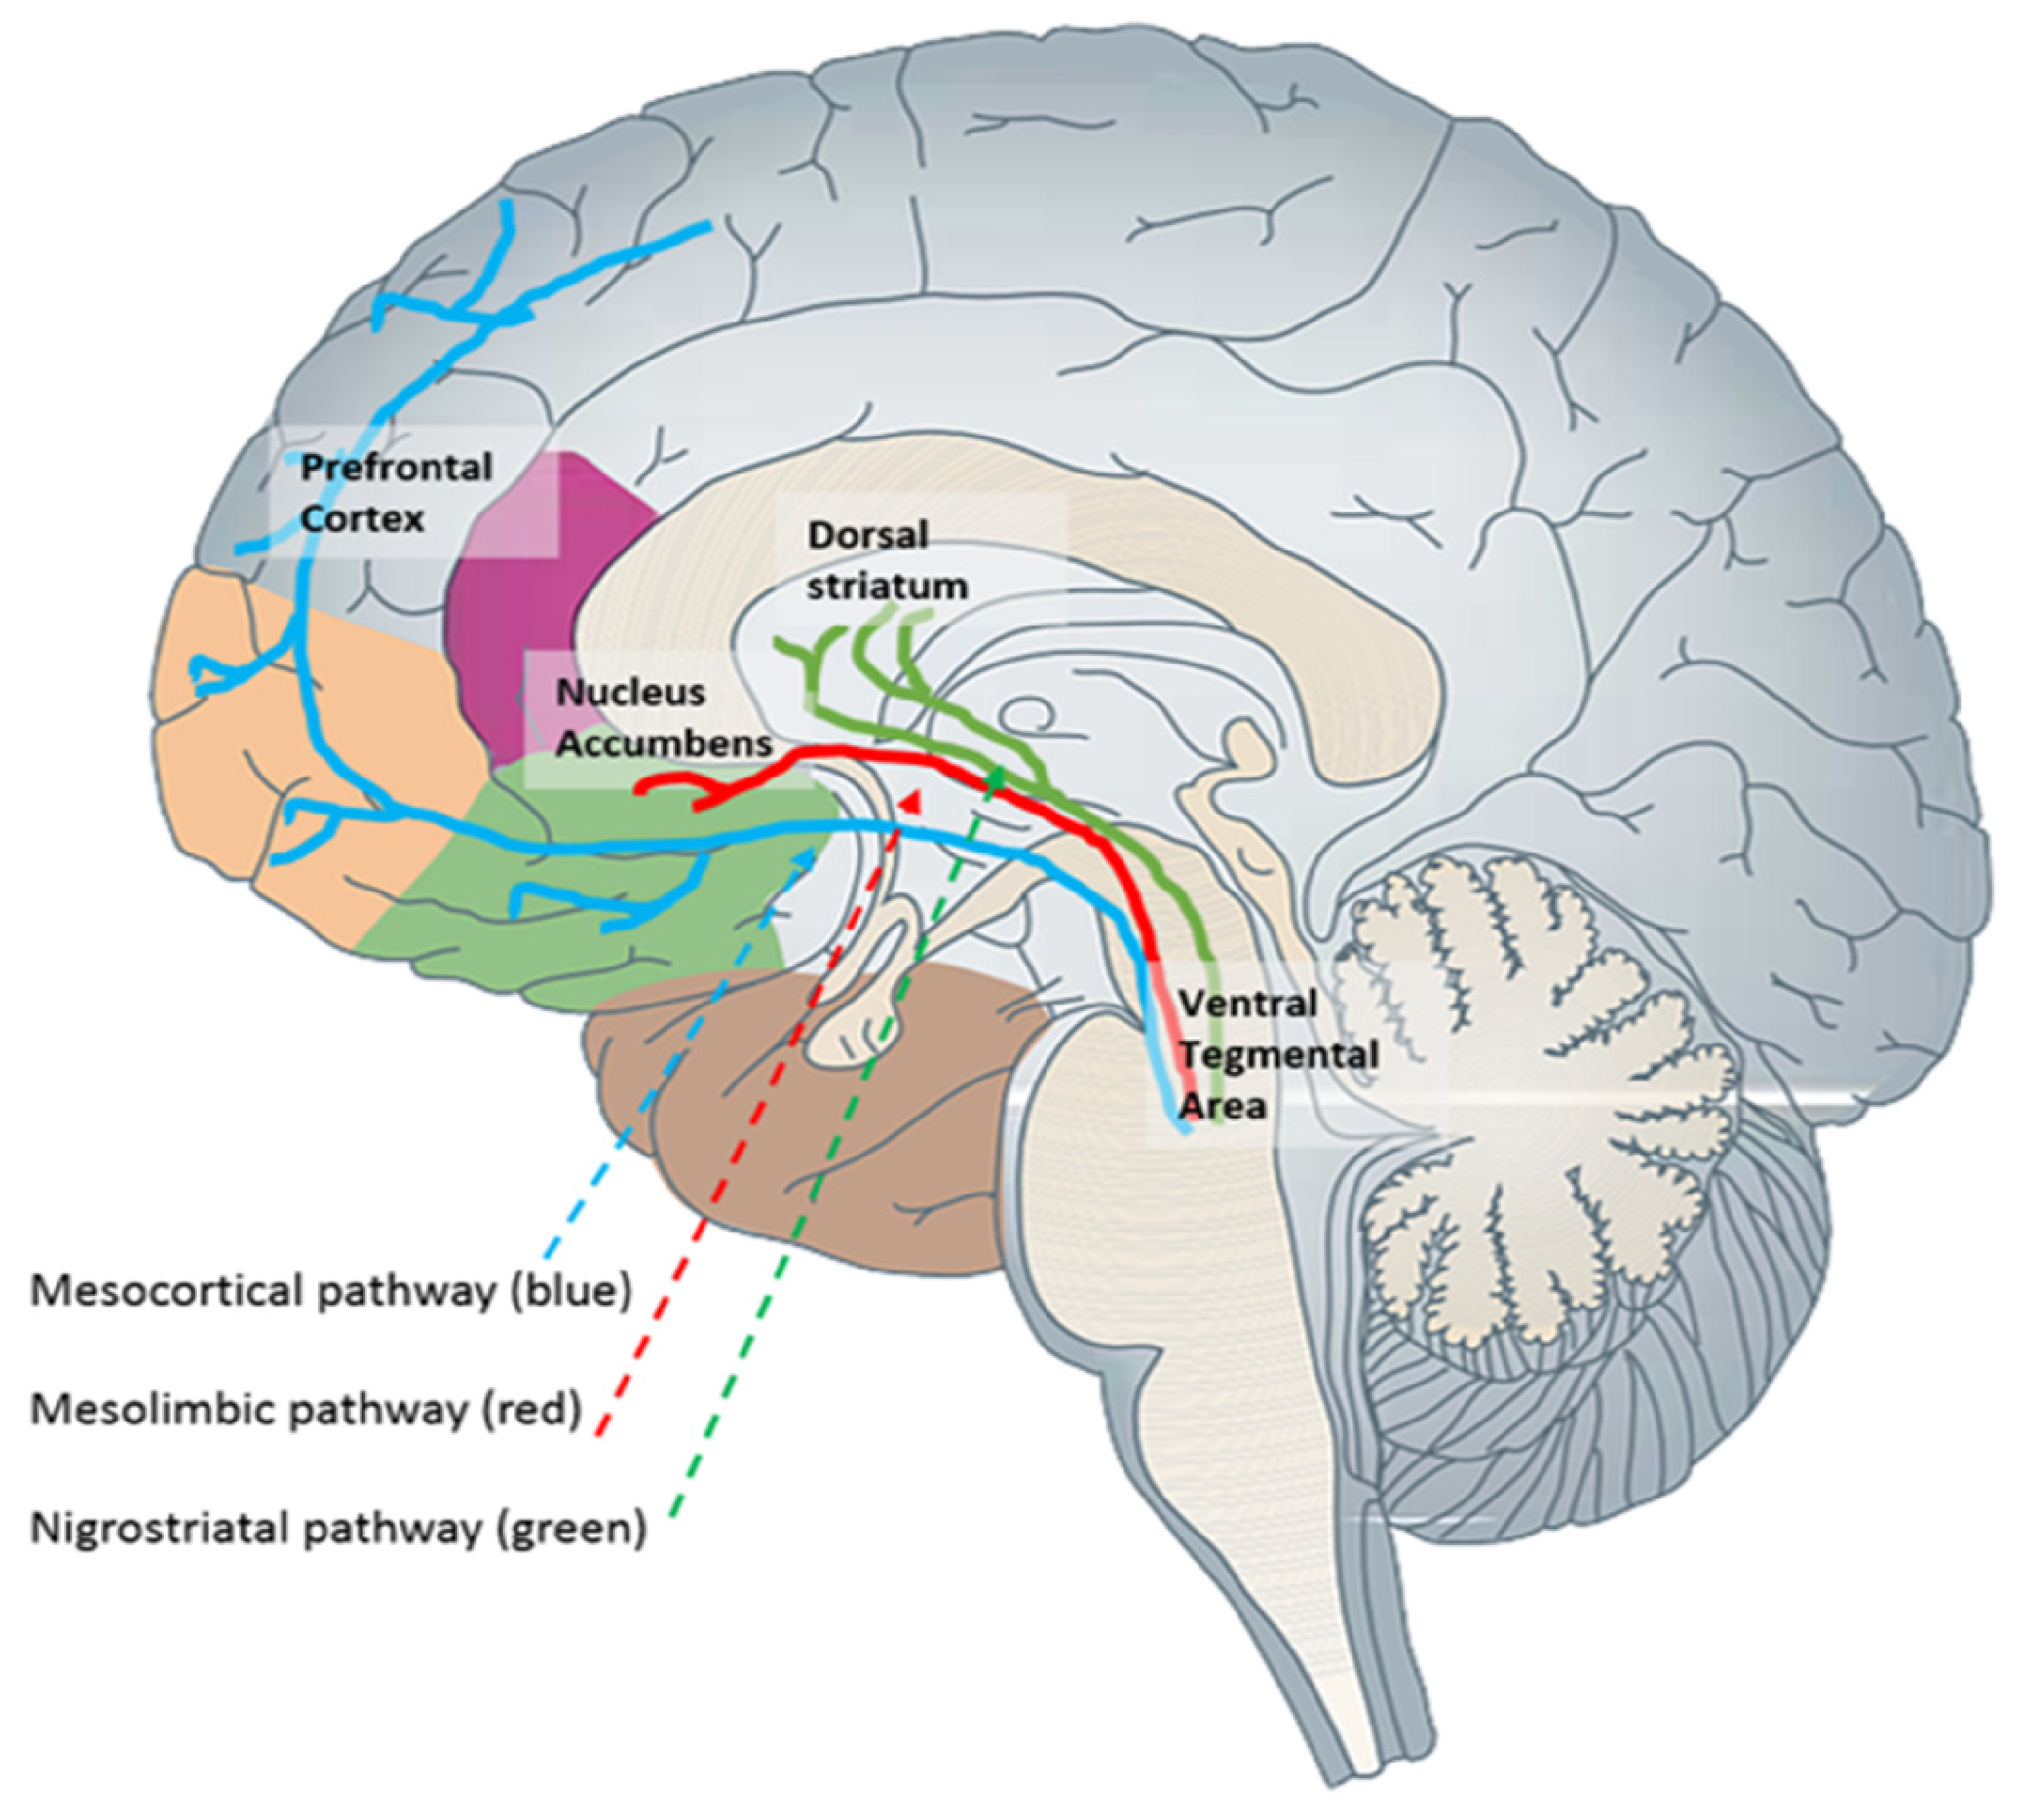
This is what incentive salience means in practice. The brain assigns excessive "wanting" to cues associated with the substance while the actual hedonic impact, the "liking," has decreased or flatlined. You end up with someone who is highly motivated to use but reports feeling nothing when they do. That contradiction breaks most conventional treatment models because they assume motivation and enjoyment stay linked. The neuroanatomy here involves the mesolimbic pathway connecting the ventral tegmental area to the nucleus accumbens, but that's only part of it. The lateral hypothalamus and the orbitofrontal cortex play equal roles in maintaining the compulsive drive. The orbitofrontal cortex is where stimulus-reward associations get updated, and in addiction, those updates become stuck. This is why habit reversal alone rarely works long term. The underlying association hasn't actually changed, it's just been temporarily suppressed.
How This Actually Works in Treatment
I've seen this approach applied clinically, and it looks different from what most people expect. It isn't about replacing one behavior with another. It's about systematically retraining the cue-response pathways through repeated exposure to triggers without the expected outcome. That's extinction learning, and the neuroscience shows it's far more effective when combined with cognitive reappraisal of the trigger itself. The protocol I use with patients works like this. We map their high-risk cues first. Not vague stress or boredom, but the specific sensory inputs. A particular time of day, a certain room in their house, the sound of a phone notification, the brand of cigarette lighter they used for twelve years. Each cue gets tagged and then deliberately activated in session while the patient practices not acting on the urge. This isn't distraction. Distraction leaves the cue-response link intact. The patient stays present with the urge and watches it peak and fade without responding. Urges follow a predictable temporal curve. They rise for about eight to twelve minutes and then drop sharply if nothing reinforces them. Most people who relapse do so because they wait for the urge to go away before doing anything, and by the time it passes, they've spent twenty minutes in distress and then rationalize that the substance will help them relax. That rationalization is the orbitofrontal cortex re-engaging. It's not a character flaw. It's a circuit that fires automatically after extended delay without response.
Get the Full Details

I usually tell patients to set a timer for ten minutes when a strong cue hits. They do something physically different during that window, not to escape the urge but to break the automatic motor pattern. Often it's just walking to a different room or holding ice in their hand. The sensory shift interrupts the basal ganglia loop enough that the urge loses intensity by the time the timer ends. This has worked consistently across hundreds of cases I've seen.
The Prediction Error Mechanism
One of the most important findings from this research area involves prediction error. Dopamine neurons fire when a reward is unexpected, fire less when an expected reward doesn't arrive, and stay quiet when outcomes match predictions. In addiction, this system gets rewired so that cues themselves become the primary prediction signal, not the substance. Here's what that looks like clinically. A person enters recovery and initially feels fine around former usage cues. Then six months in, they walk past a bar they used to frequent and suddenly feel a wave of craving so intense they almost call their dealer. This isn't weakness. It's a prediction error mismatch. Their brain had suppressed the cue response during early recovery, but the association never fully disappeared. Under certain conditions, like fatigue or stress, the suppressed pathway reactivates with higher amplitude than before. This is called spontaneous recovery in conditioning literature, and it's one of the main reasons people who've been clean for years suddenly relapse after long periods of stability. The workaround I've found useful is proactive cue exposure, not waiting for spontaneous recovery to happen uncontrolled. We deliberately introduce neutral versions of high-risk cues during the first year of treatment. A coffee cup from their old routine, a song they used to listen to while using, a brief visit to a low-risk environment similar to where they used. By repeatedly exposing them to these cues in a safe context, the brain gradually updates the prediction model. The cue no longer triggers the same dopamine shift because it's been paired with no substance across many repetitions.
This process takes time. You're looking at three to six months of regular sessions before the cue responses stabilize at lower levels. It's not a quick fix, but it addresses the root mechanism instead of just managing symptoms.

Common Mistakes I See in Practice
The biggest mistake clinicians make is treating motivation as a personality trait rather than a neurochemical state. When a patient tells you they lack motivation to recover, the assumption is often that they're not trying hard enough. The reality is frequently that their mesolimbic dopamine baseline has been flattened by chronic substance use. This isn't a willpower problem, and it won't resolve through willpower. Another common error is assuming that medication alone can solve the motivational deficit. Medications like naltrexone or buprenorphine reduce craving by blocking opioid receptors or partially activating them. They're useful tools, but they don't retrain the cue-response associations. I've had patients on perfect medication regimens who still relapsed within weeks of encountering a strong environmental trigger because the underlying predictive circuitry was untouched. The third mistake is pushing exposure therapy too aggressively too early. If you expose a patient to high-intensity cues before their tolerance for distress has built up, you can actually strengthen the cue-response pathway through reconsolidation. The brain interprets the intense activation as confirmation that the cue is dangerous and the substance is necessary. The exposure needs to be graded, starting with low-intensity cues and building up slowly over weeks.
I also see a lot of programs that focus exclusively on the positive side of motivation, the approach drive, while ignoring the negative reinforcement pathway. Some people use substances primarily to reduce anxiety, pain, or withdrawal discomfort. For those patients, the motivational circuit involves the amygdala and the bed nucleus of the stria terminalis, not just the reward system. Treating them with standard incentive-based approaches often fails because you're addressing the wrong neural circuit.
What This Research Actually Means Going Forward
The practical implication is that effective treatment needs to target both the positive and negative reinforcement systems simultaneously. A patient with co-occurring anxiety and substance use disorder requires interventions that address both the corticotropin-releasing factor system and the dopamine system. Treating only one leaves the other free to drive relapse. Neuroimaging studies now allow us to see which pathway is dominant in individual patients. This isn't available everywhere yet, but where it is, it changes the treatment plan significantly. A patient with high orbitofrontal-striatal connectivity responds better to cognitive-behavioral approaches. A patient with elevated amygdala reactivity benefits more from emotional regulation training before any exposure work begins. The broader takeaway is that motivation in addiction is a mechanistic process, not a moral one. The brain has been systematically rewired through repeated substance exposure, and reversing that requires targeted retraining of specific circuits. Programs that treat addiction as a choice or a character issue will always have high relapse rates because they're addressing the wrong level of analysis.

I've found that patients respond differently when they understand the mechanism. Knowing that their craving is a prediction error signal rather than a personal failure changes how they relate to the urge. They stop fighting it and start observing it. That shift alone reduces the emotional amplification that typically precedes relapse. It's a small change in framing that makes a measurable difference in outcomes. The science here is still developing. New findings about the role of the prefrontal cortex in suppressing compulsive behavior emerge regularly. The ventromedial prefrontal cortex, in particular, shows promise as a target for neuromodulation therapies. These approaches are experimental now but could change the treatment landscape within the next decade. Until then, the established protocols based on this research remain the most reliable option available.