Setting Up a Swedish Health Service Integration: What Actually Works
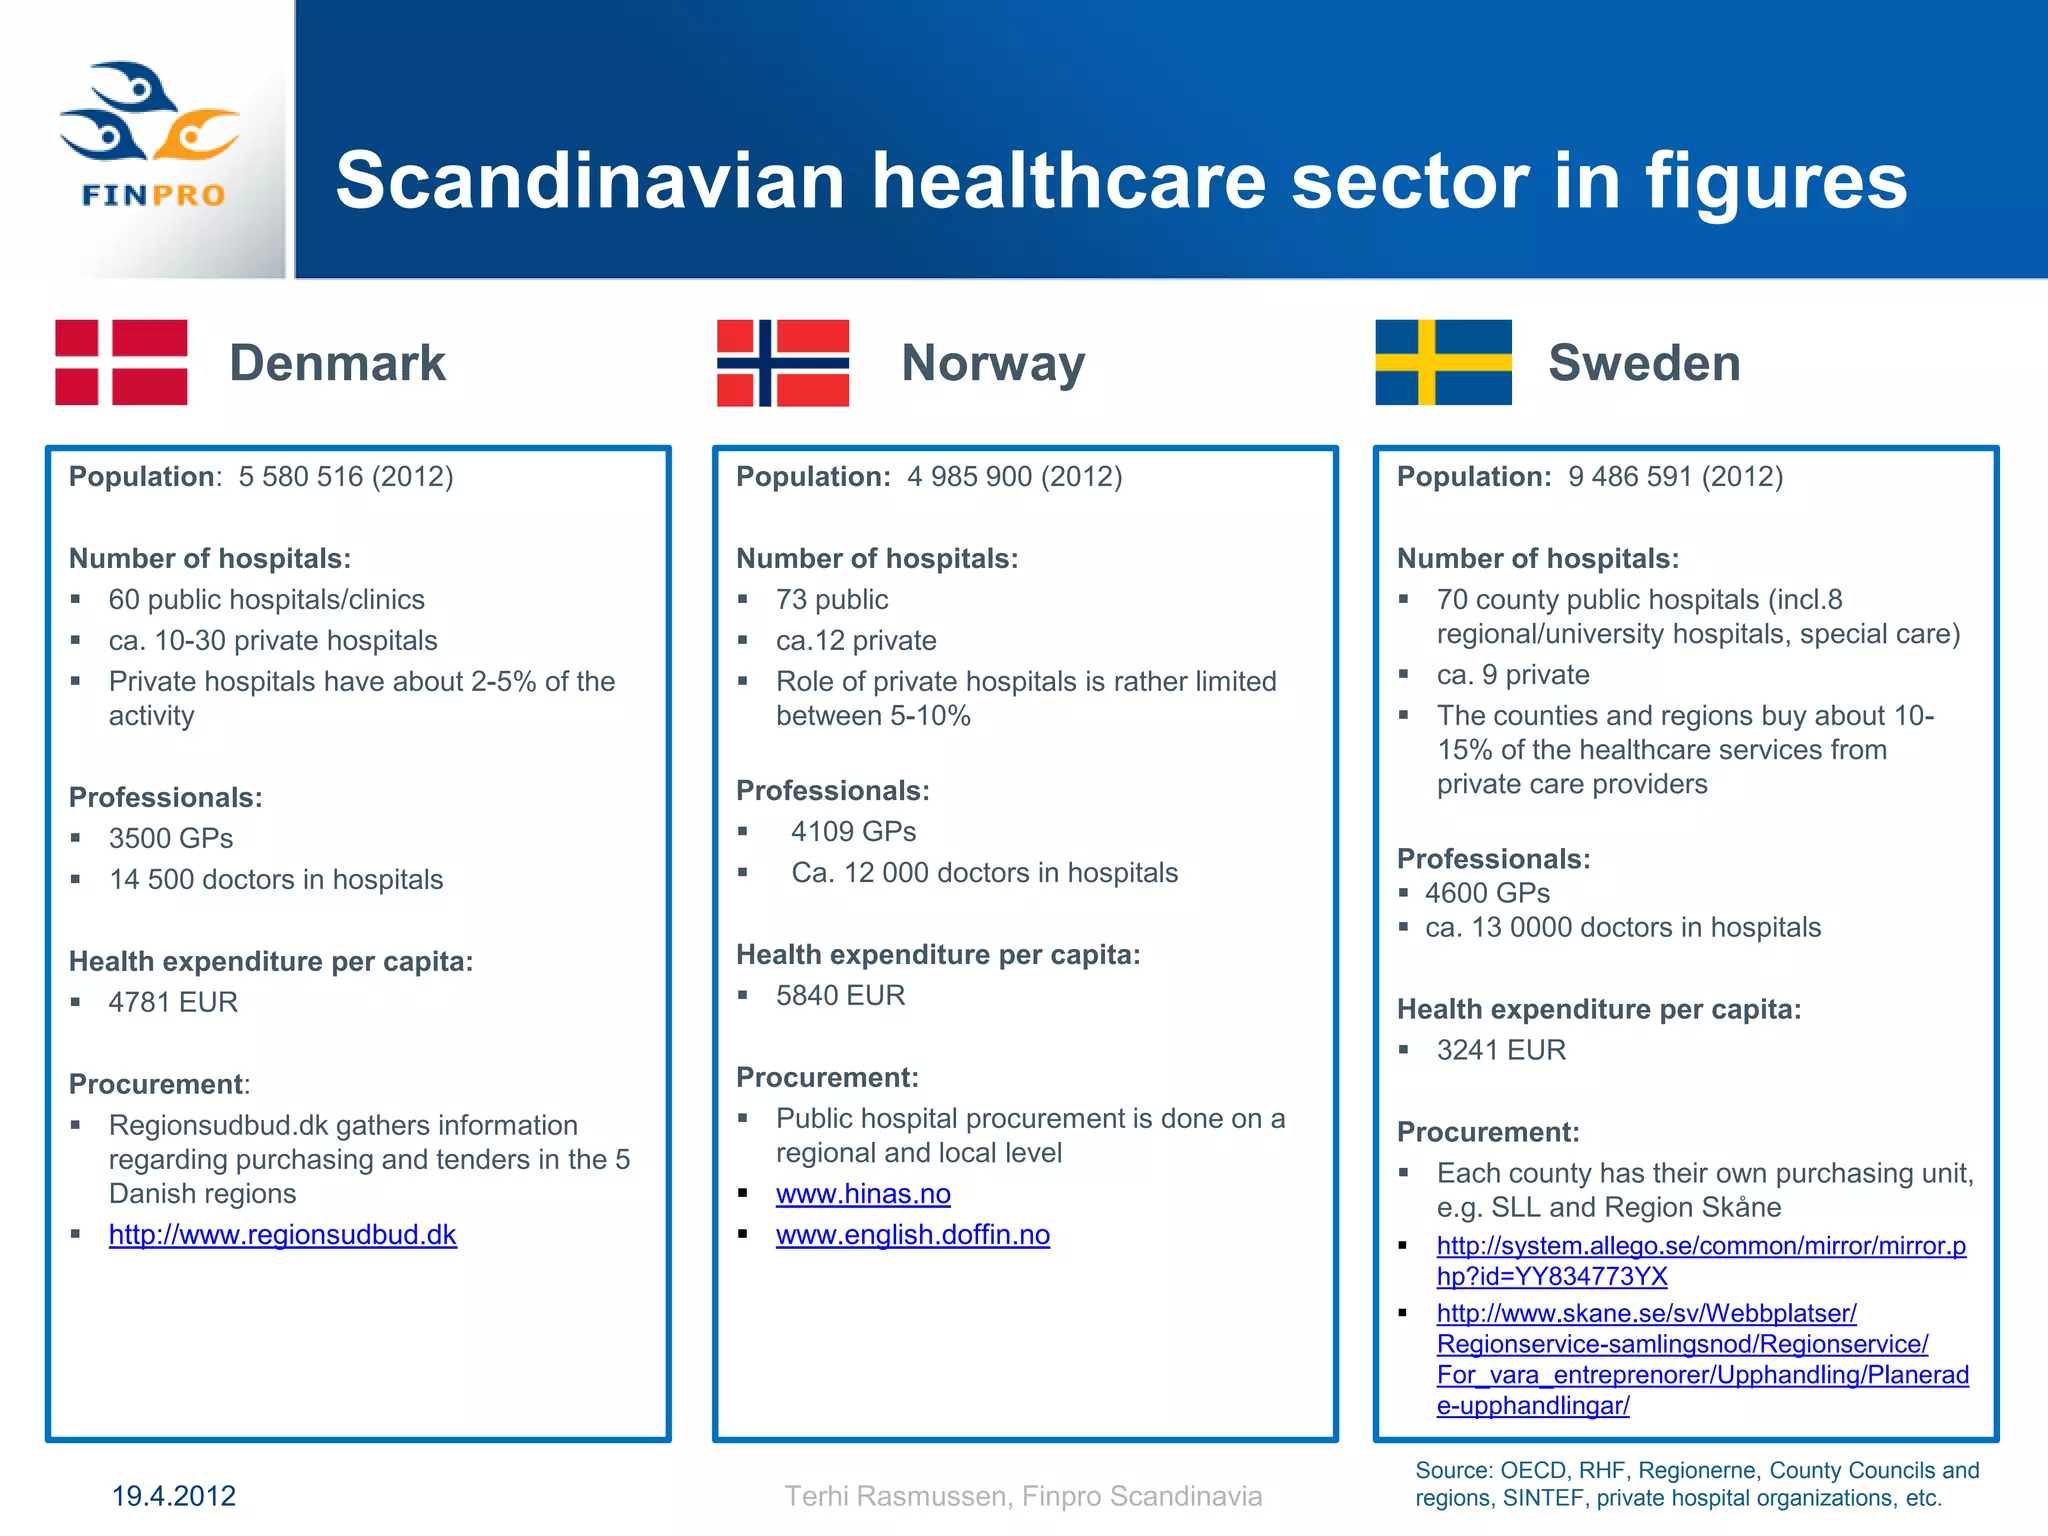
I spent about nine months building a data pipeline that pulled patient-level outcomes from the Swedish National Health Registry into a US-based analytics platform. It wasn't the marketing version of the Nordic model that sounds great in conference keynotes. It was a frustrating, bureaucratic, technically messy process that involved three different API gateways, a lot of email chains with people who controlled access keys, and a moment where I realized the entire project hinged on a single person's understanding of Datainspektionen compliance rules. The Nordic healthcare model works differently from what most American hospitals are used to because the data infrastructure came first. Sweden built centralized registries starting in the 1960s. That means real-world clinical data exists in structured, interoperable formats across the entire population. Most other countries are still trying to get their providers to use the same specialty code in two different systems. Sweden already had that solved before EHRs became a thing. The catch is that access isn't open. It's gated through regional health authorities and requires formal data processing agreements under GDPR and Swedish Specific regulations. The system relies on two main components. The first is the patient registries maintained by each region. Sweden has 21 regions, and each one runs its own electronic health record system. The second is the national layer, which includes the National Patient Registry, the Swedish Cancer Registry, and several quality registries that feed into clinical guidelines. These national registries aggregate anonymized data from the regional systems. When you're integrating Swedish Health Services How The Nordic Model Is Reshaping Global Healthcare Innovation into your own platform, you're typically connecting at the regional level first, then pulling aggregated national data through separate requests.
I learned the hard way that these two layers don't sync on a schedule you can rely on. The regional data flows in near real-time for most registries. The national layer updates quarterly at best, sometimes biannually for less commonly used datasets. If you're building something that depends on current patient counts or recent procedure volumes, and you pull from the national registry expecting today's numbers, you'll be off by up to six months. My workaround was to maintain two parallel data sources and flag any national-level metrics with a freshness timestamp in the database schema. It added about three days of dev time but prevented four months of confused stakeholder questions later.
The Interoperability Layer That Makes It Possible
Sweden uses HL7 FHIR as its standard exchange format, but with a Swedish profile that extends certain resources to match local administrative structures. This is important because if you're using a US-centric FHIR implementation and expecting to parse Swedish clinical data without adjustment, you'll hit encoding issues on diagnosis codes and encounter types. The Swedish profile maps ICD-10SE diagnoses, SKILL procedure codes, and regional organization identifiers into the standard resource definitions. You need a mapping table for each code system. Here's something most tutorials don't mention. The FHIR endpoints are authenticated through a national federation called SwEDU, which acts as a centralized identity provider. Getting your organization added to SwEDU takes anywhere from two weeks to three months depending on whether you're a public institution or a private company. Private companies have consistently reported longer review cycles. During the waiting period, which I experienced personally, you can work against sandbox instances but nothing touches production data until the credentials are verified. Plan your timeline around that delay, not the other way around.
Get the Full Details

Where the Model Falls Apart
The Nordic approach sounds perfect on paper because it produces excellent outcomes data. In practice, it has structural weaknesses that anyone trying to replicate it elsewhere should understand upfront. The first is fragmentation between regions. Each of the 21 regions funds and manages its own healthcare delivery. They share national registries, but the regional EHR vendors differ. Some regions use Epoc, others use Sunrise or Avante. This means your integration code will need region-specific adapters even when you're using the same national FHIR standard. I ended up writing a region routing middleware that translated the same query into three different request formats depending on which region's data was requested. The second weakness is data completeness. Not every clinical event gets registered. Outpatient visits, especially in primary care, have known gaps in certain registries. The quality registries cover specific conditions like cancer and cardiovascular disease very well. For general ambulatory care, you're looking at somewhere between 60 and 80 percent capture depending on the procedure type and the region. If your research or product depends on complete ambulatory data, the Swedish model alone won't give you that. You'd need to combine it with regional claims data, which requires a completely separate application process.
A Practical Approach to Building the Integration
Start with the national registries before touching the regional data. The national layer has cleaner documentation, more consistent schema, and faster support response times. Use the National Patient Registry to validate that your authentication and parsing pipeline works. Once that's functioning, apply the same logic to one or two regional APIs. Don't try to connect all 21 regions at once. Pick the ones most relevant to your use case. You'll need a Data Processing Agreement with each region you connect to. These documents run 40 to 80 pages and include clauses about data retention, breach notification timelines, and sub-processor restrictions. Have a lawyer who understands GDPR review them. The standard template from the region will favor the region. You can negotiate certain terms, but the core data protection clauses are non-negotiable. Factor in four to six weeks for legal review per region if you're working with multiple jurisdictions.
The Hidden Bottleneck: Ethics Review
Even when you have regional approval and a signed DPA, many projects require ethics review through the Swedish Ethical Review Authority before you can access identifiable data. This is separate from the data governance process and completely independent. The review timeline averages four months. For purely aggregated or anonymized datasets used in quality reporting, you may qualify for an exemption. The exemption request itself takes about six weeks to process. If you're unsure whether your use case needs full review or qualifies for exemption, submit the exemption request first. It's faster to get a rejection and then apply for full review than to get stuck in review and then discover you needed different permissions all along. The combination of regional fragmentation, ethics review timelines, code system variations, and data completeness gaps means the Nordic model isn't a plug-and-play solution for global healthcare innovation. It's a high-quality but complex infrastructure that rewards patience and punishes assumptions. Organizations that treat it like a straightforward API integration tend to underestimate the administrative overhead by a factor of three. Those that budget for the legal and governance work end up with something usable and often superior to what they'd get from less coordinated national systems. The trade-off is real, and it's worth understanding before you start.