Getting Back To Basics On Fascia Repair
Fascia tears don't always announce themselves loudly enough in the early post-op period. By the time you see that wound beginning to gape at the edges or feel that give under your finger during a routine dressing change, you're already dealing with dehiscence, not prevention. The technical definition is straightforward—suturing is the mechanical approximation of fascial edges using suture material passed through the tissue in a deliberate pattern—but the clinical reality is messier than any textbook makes it look. I'm going to walk through what actually happens in the room when you're facing a torn fascia, what patterns hold and what doesn't, and where I've seen this go wrong in practice. The protocol is fundamentally about restoring the tensile strength of the fascial layer so the wound can heal without reopening under normal intra-abdominal pressure. You're working with tissue that has already been damaged by a tear, so you're not healing virgin fascia—you're healing a junction between healthy tissue and an older, compromised site. That changes everything about needle selection, bite depth, and suture tension. Start with the suture material. I use non-absorbable or long-term absorbable monofilament for most primary fascial closures—0 or 1-0 on a taper-point body needle, depending on fascial thickness. Vicryl Rapide or PDS around 0 is my standard for repairs where the tissue quality is decent but you need the support to last through the early proliferative phase. If the fascia is friable or the patient has significant comorbidities affecting collagen synthesis, I drop to a delayed absorbable like PDS and space the bites further apart to compensate. Absorbable braided is a mistake here—the knot security feels good initially but the tissue reaction and loss of tensile strength around week three is exactly when you'd rather have something holding.
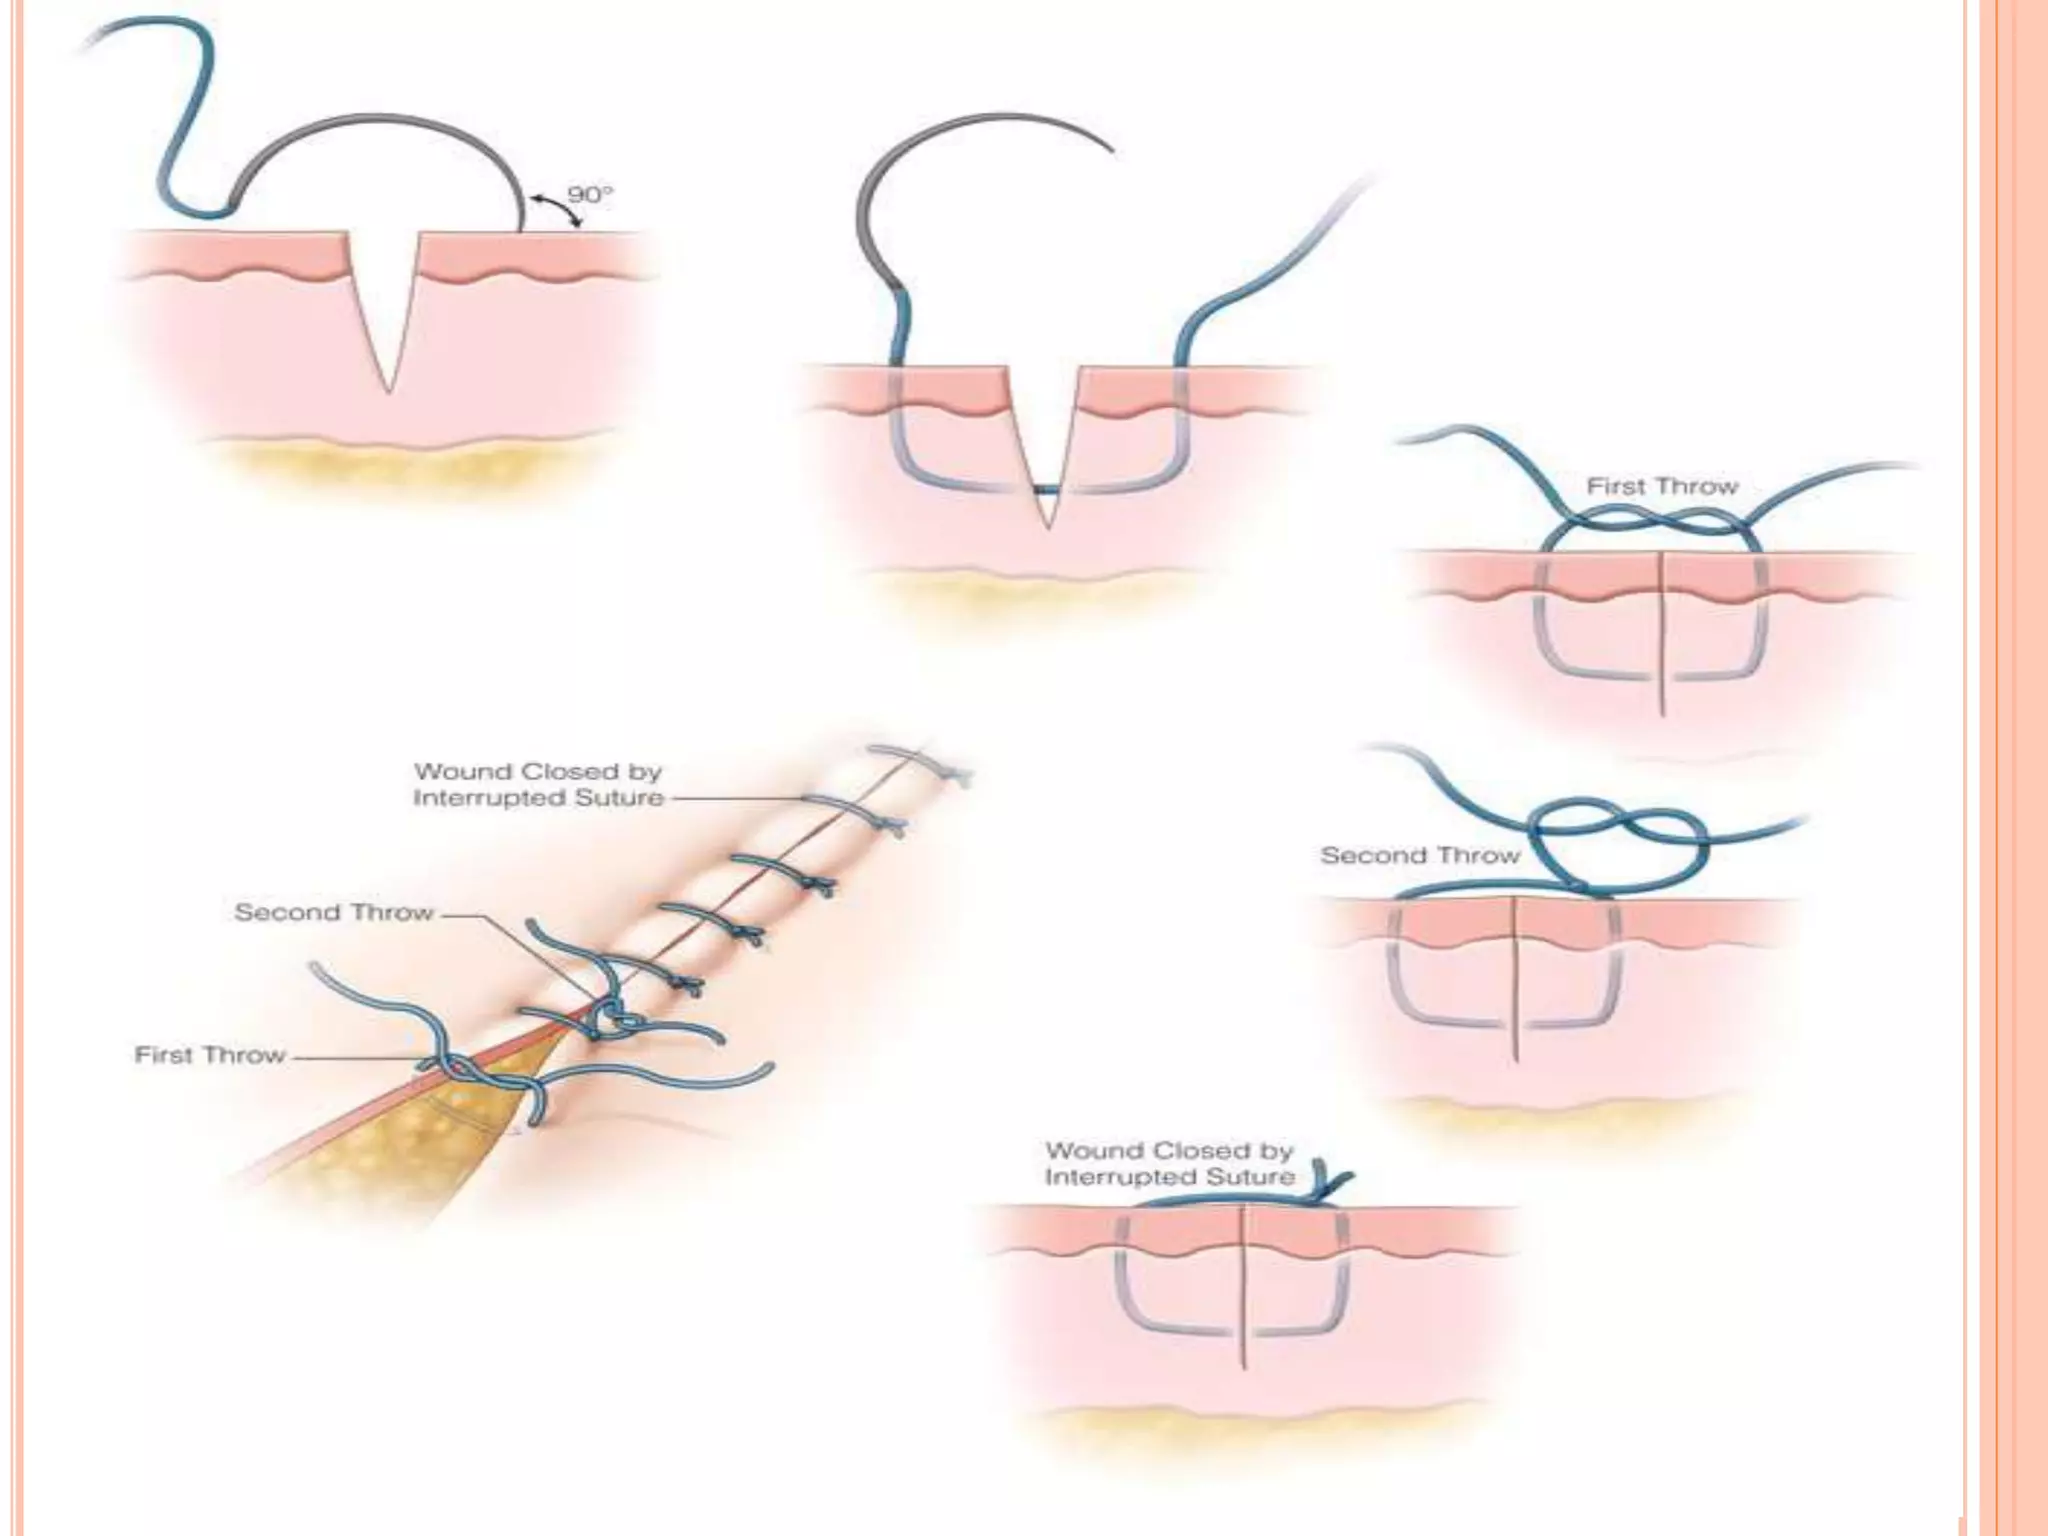
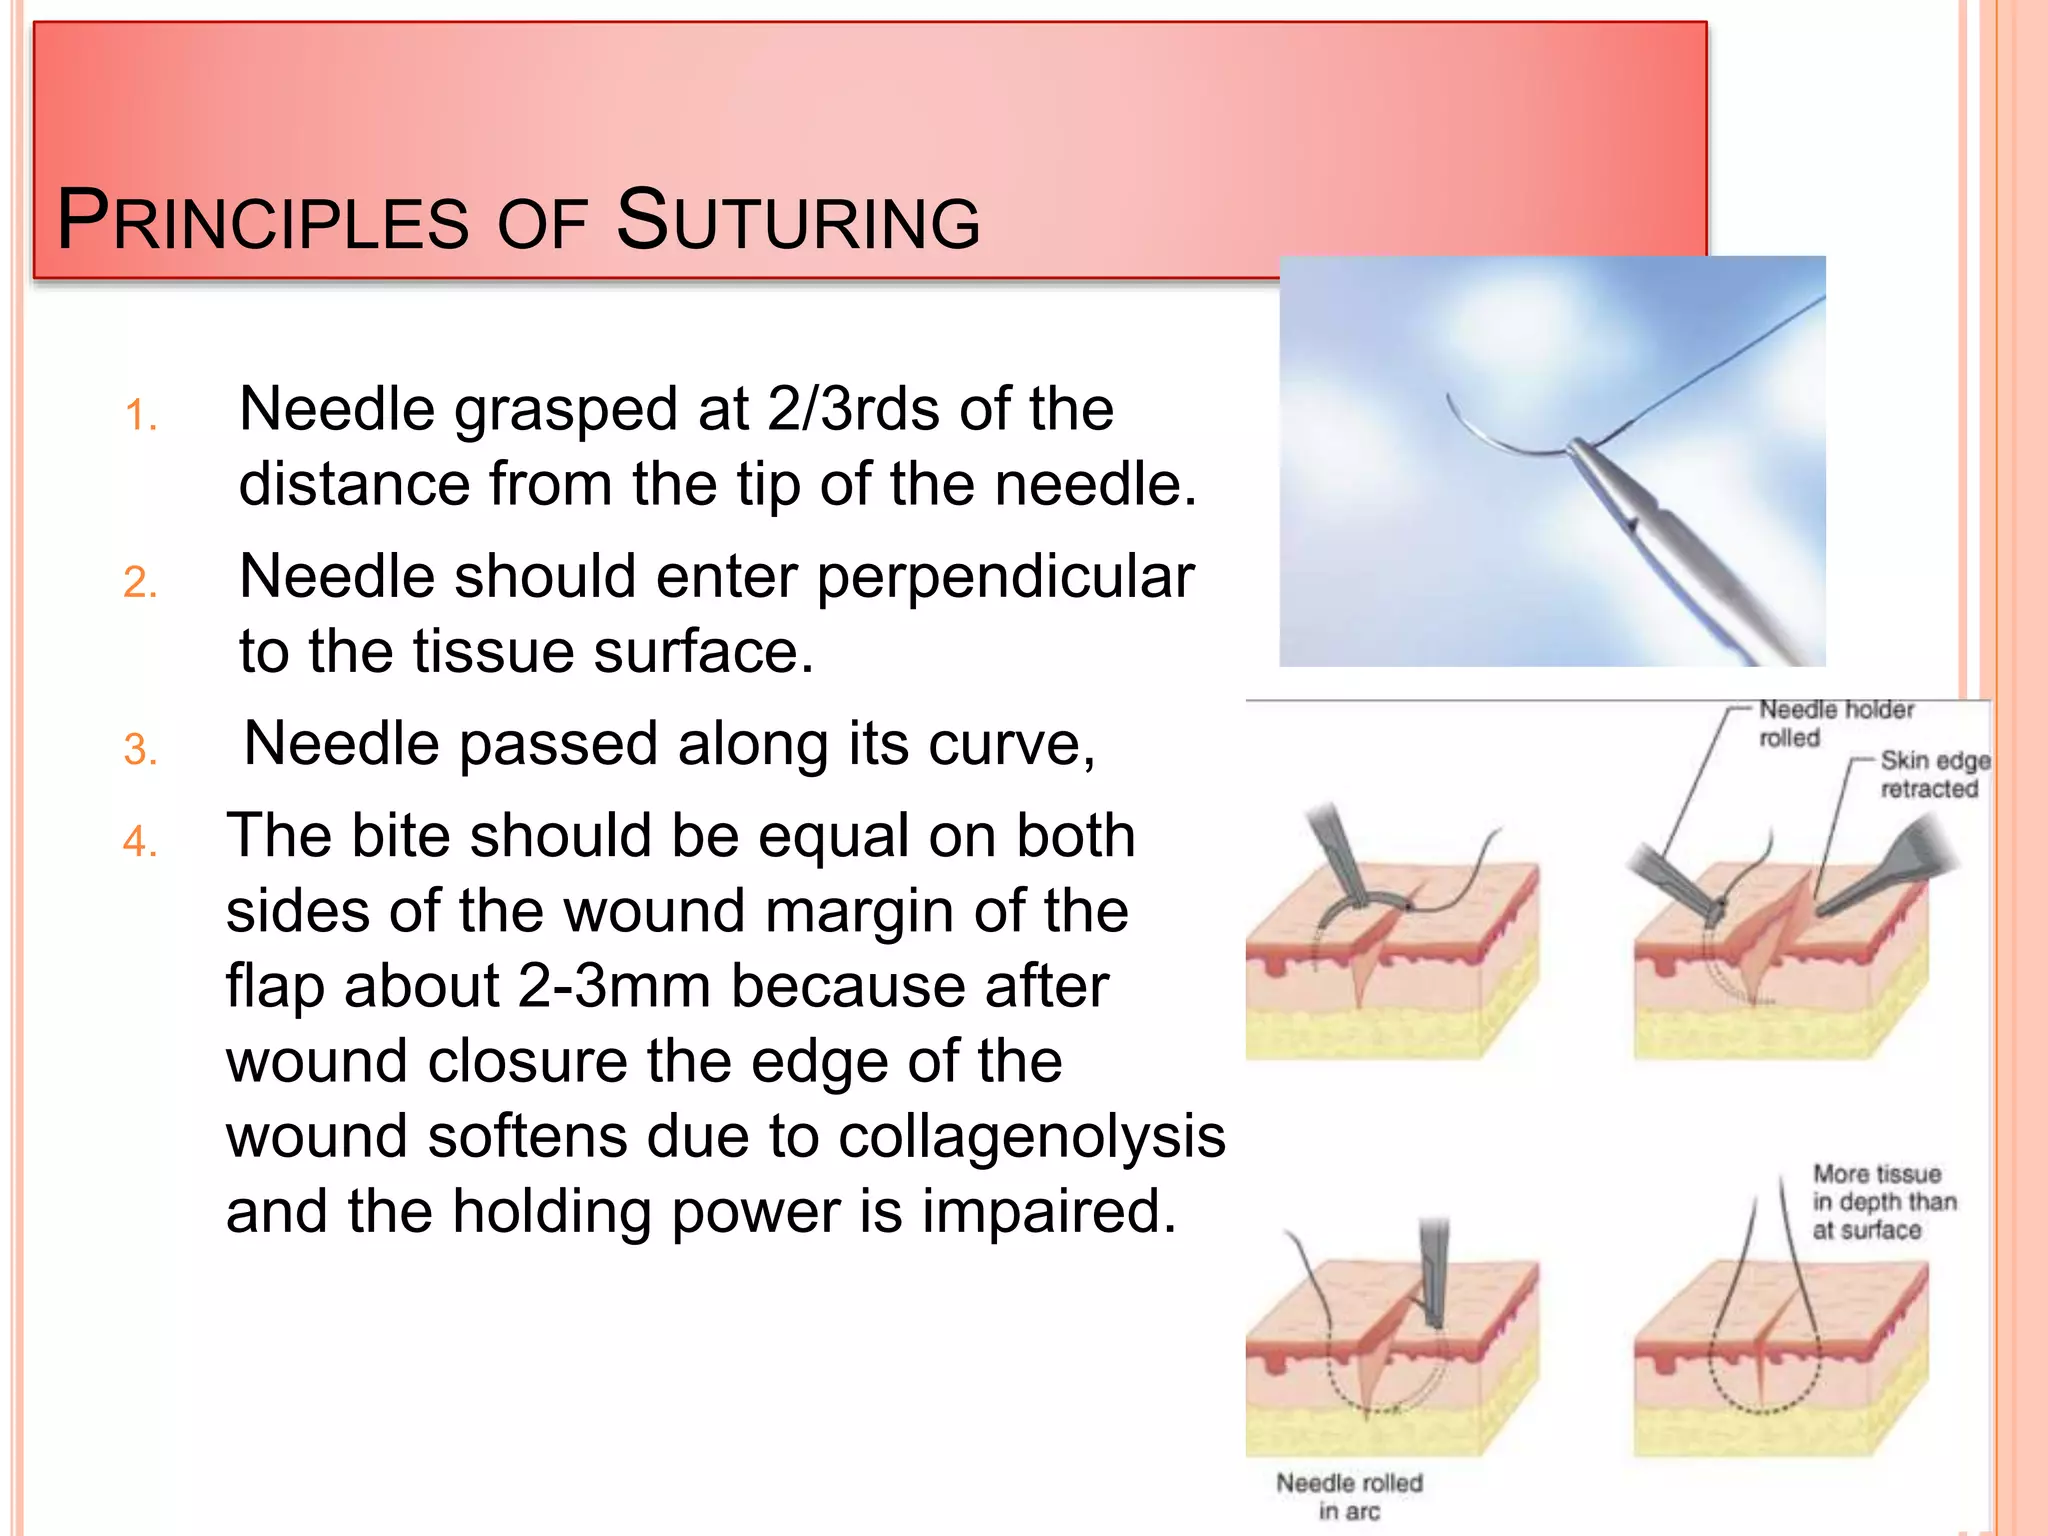
The bite technique matters more than people admit. Full-thickness bites through the fascia, not just the superficial layer. I'm talking 1 centimeter from the edge with a bite depth that captures the entire fascial thickness—that's usually 5 to 8 millimeters depending on the patient and the anatomical site. Too shallow and the suture cuts through like it's pulling through wet paper. Too deep and you're catching muscle or bowel without meaning to, and then you're dealing with a completely different problem set. A single running locking stitch is fast but it concentrates force along the entire length of the closure, which means if one point fails, the whole thing comes apart. I prefer interrupted vertical mattress or horizontal mattress sutures for initial repair. Each stitch carries its own load, and a failure in one doesn't cascade. I ran into a case last year—belly surgery, patient was diabetic with a BMI over 35, fascia tore about 4 centimeters lateral to the midline around the inferior aspect of the incision. The original closure had been a running single-layer technique with too-small bites, maybe 3 millimeters from the edge, which is a common failing when the surgeon is rushing. When the dehiscence became apparent, I couldn't just put the same sutures back in the same spots. The tissue at the old suture tracks was already necrotic and shredded. What worked was debriding back to healthy bleeding fascia, switching to interrupted 0 PDS horizontal mattress sutures with 1.5 centimeter edge bites, and leaving a drain because this patient was going to produce seroma fluid regardless of how well I approximated the edges. Took me twenty-two minutes longer than a straightforward closure but that's the cost of doing it right when the first attempt was substandard. Tension management is where most repairs break down. You should be able to approximate the edges without strangulating the tissue. If you're pulling hard enough that the fascia turns white at the suture site, you've got two options: place more sutures with smaller individual tension, or convert to a retention suture strategy. Subcuticular sutures placed through the skin and anchored to a bolster are useful adjuncts in high-tension closures, especially on the abdomen. They don't replace deep fascial sutures but they offload some of the shear stress during patient movement and coughing in the first post-operative days.
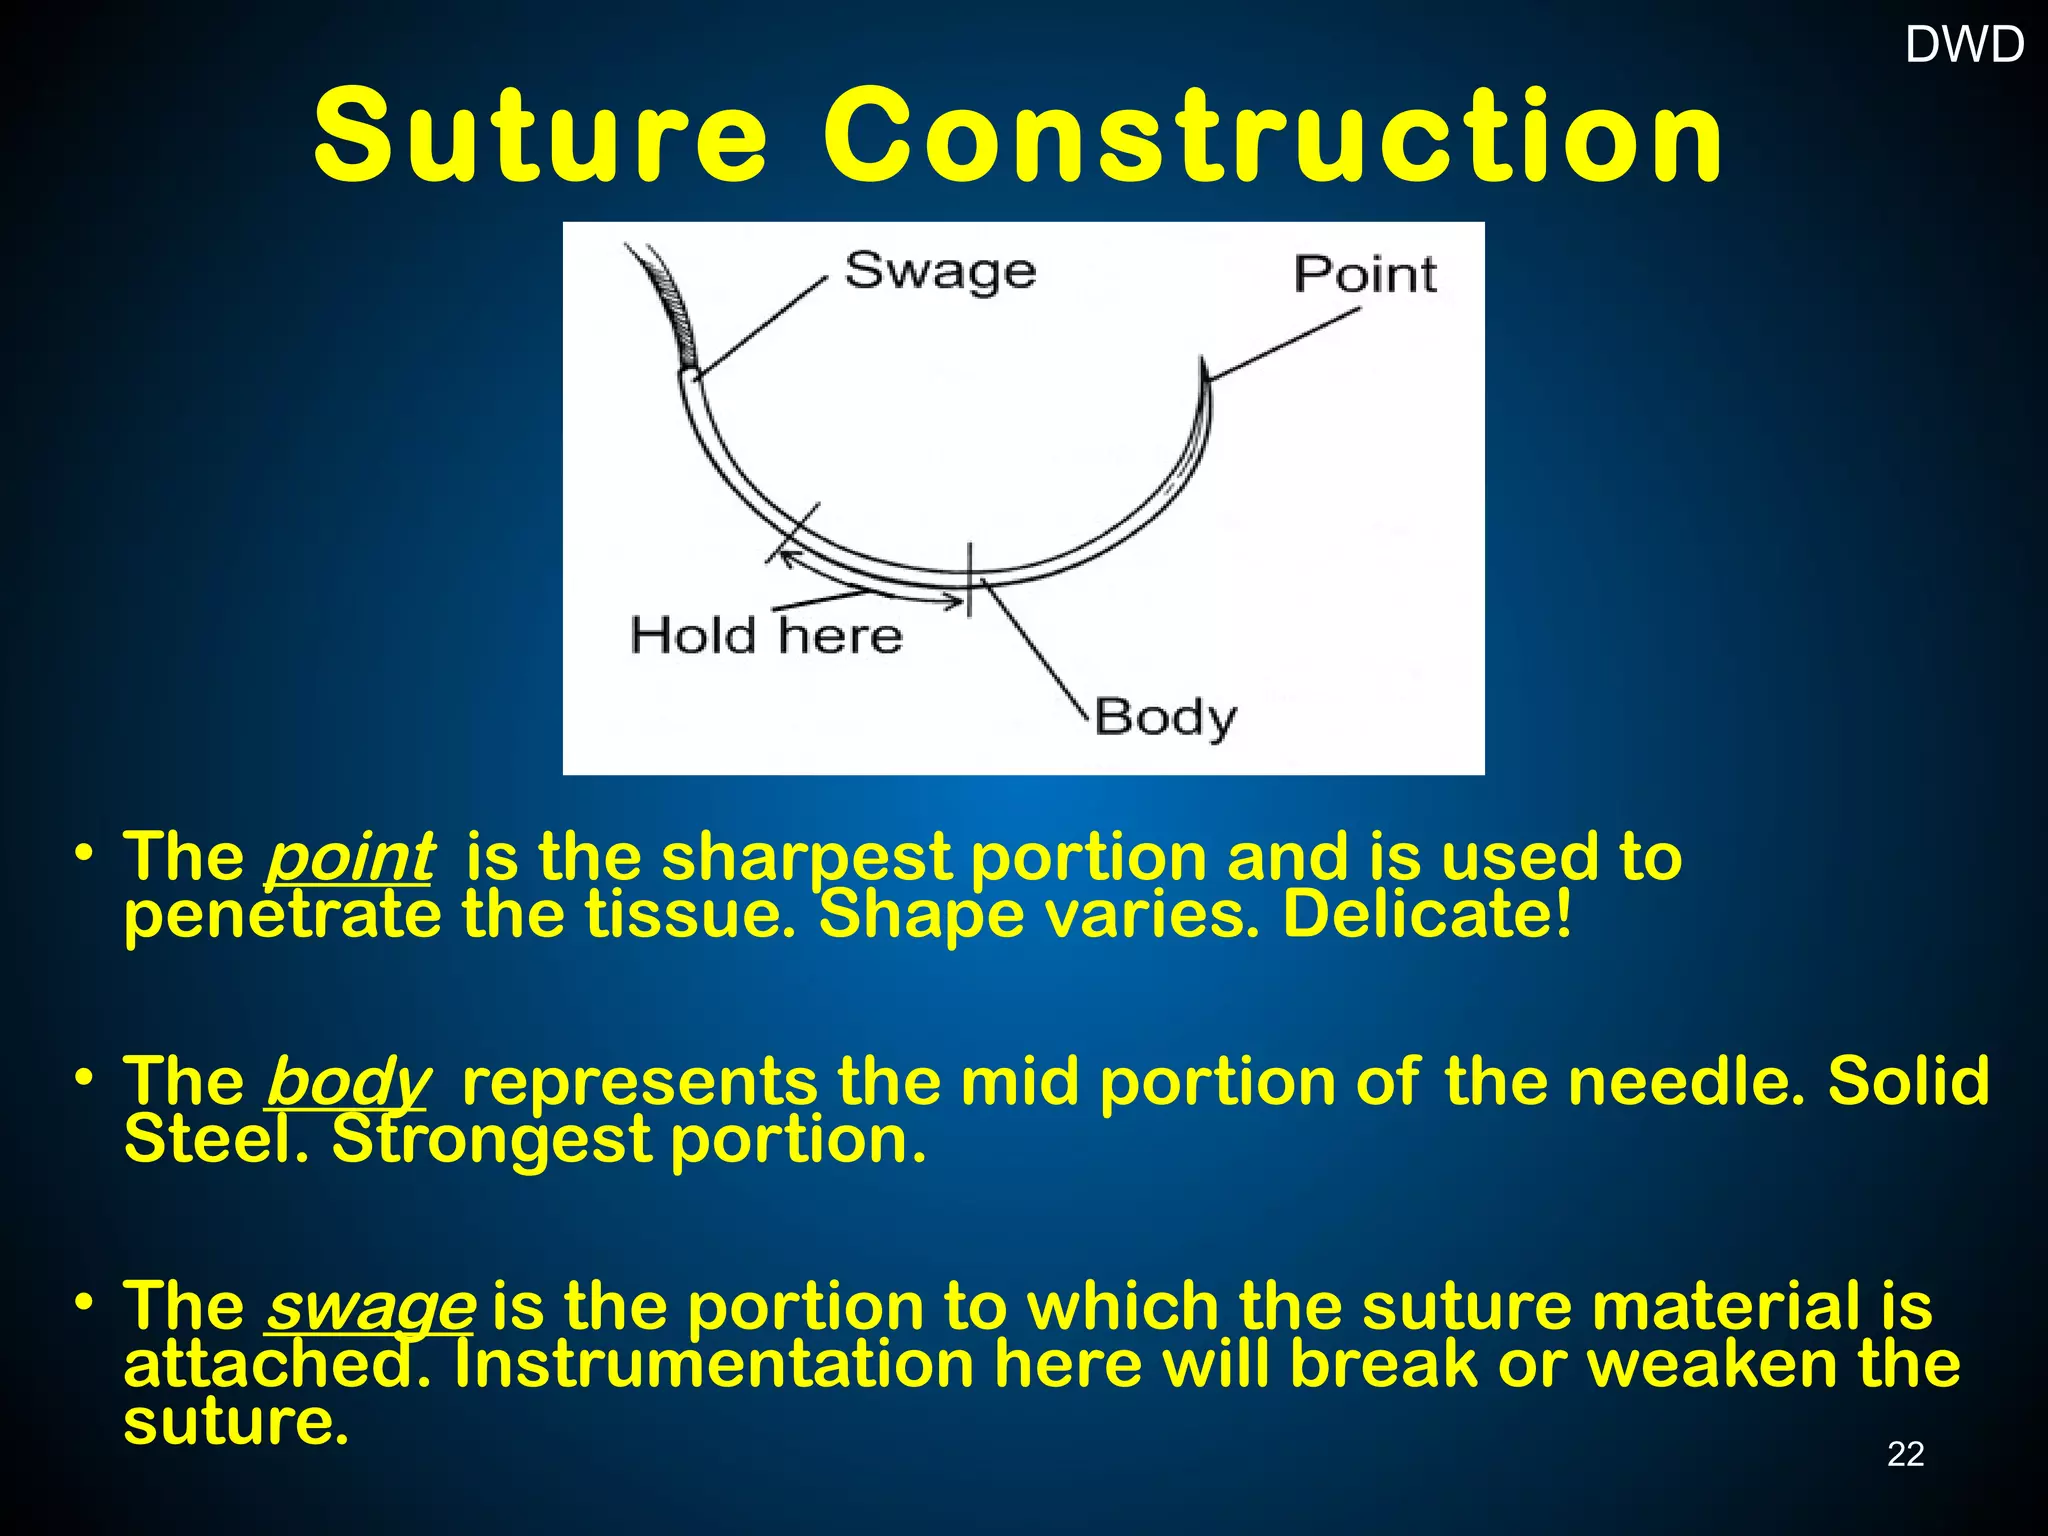
Needle handling during fascia work requires a different grip than subcutaneous or skin suturing. A 3/8 circle needle with a firm, confident wrist motion through fascia takes less force than people expect—the needle does the work if you're not trying to saw through the tissue. Forcing a needle that's angled wrong or dulling it through repeated passes just creates a wider track and more tissue trauma. I replace the needle if it's dragging or if the fascial bite requires more than moderate pressure. That's not being careful, that's being economical about tissue preservation.
Get the Full Details

What Nobody Tells You About Fascial Healing
Fascia regains about 70 to 80 percent of its original tensile strength by six weeks post-operatively. That number sounds reassuring until you realize that the worst complication rate for fascial dehiscence happens between days 5 and 14, when the wound is at its weakest and the sutures are still doing all the work. The tissue hasn't built enough collagen to share the load and the absorbable sutures haven't started losing strength yet, but any surge in intra-abdominal pressure—coughing, vomiting, straining—can exceed what the suture alone can hold. I've seen continuous suture techniques fail spectacularly in patients who were constipated and pushing hard on day 4. The entire line of closure pulls through because the force is distributed along one continuous strand. Interrupted sutures isolate the failure to a single point. It's a simple distinction that makes a huge difference in outcomes, and it's something I've seen residents miss repeatedly during their first independent fascial closures. The anatomical plane matters too. In the abdomen, you're closing the linea alba or the rectus sheath depending on the incision type. The linea alba is relatively avascular and has good suture-holding capacity when healthy. The rectus sheath anteriorly is thinner and more prone to tearing, especially in patients who've had multiple prior surgeries. Posterior layer closure is often neglected but it contributes meaningfully to overall strength. A two-layer closure—deep and superficial fascial layers—adds roughly 30 percent more tensile strength compared to single-layer in experimental models, and that difference shows up clinically in reduced hernia rates at the one-year mark.
There are scenarios where fascial suturing simply won't work and you need to pivot. Heavily contaminated fields with gross bacterial load, fascial edges that are devitalized beyond debridement, or patients with severe protein-calorie malnutrition where the tissue won't hold anything. In those cases, mesh reinforcement or planned ventral hernia management with delayed closure is the better call. Primary suture repair in a grossly contaminated field has a recurrence rate approaching 40 to 50 percent in the literature. Mesh in that same context is risky but far less likely to fail catastrophically than a suture line pulling through necrotic tissue. Post-operative care is where protocol meets reality. The patient needs to avoid heavy lifting for six weeks, but "heavy lifting" means different things to different people. I tell my patients nothing heavier than a grocery bag for the first month, and even then, only if it doesn't make them wince. Core engagement during basic movement—getting out of bed, standing up from a chair—creates more tension on a fresh fascial closure than most people realize. Teaching the patient to log-roll and use their arms to push up rather than engaging their core directly is a small intervention that prevents a lot of problems.
Practical Steps When You're In The Middle Of A Repair
If you're already at the point where the fascia is torn and you need to suture it, the sequence is: assess the extent of the tear, debride nonviable edges, select the appropriate suture and needle, plan your bite pattern before you make the first pass, execute with controlled tension, and verify the closure by gently inspecting for gaps or excessive tightness before closing the subcutaneous layer. I always do a quick saline leak test after the fascia is closed. Fill the abdominal cavity with warmed saline, have the anesthesia team apply gentle positive pressure, and watch the suture line. Any bubbling or escape of fluid indicates a gap. It takes ninety seconds and it catches errors that you'd otherwise miss until later. I've caught three small gaps this way in the last six months that would have been catastrophic to discover on post-op day 3. Documentation matters more than you'd think for a procedure like this. Recording the suture type, size, needle type, pattern, number of stitches, approximate tension, and any intra-operative complications gives you a clear record if the patient returns with problems later. It also helps the next surgeon understand exactly what was done, which is critical if there's a recurrence or hernia down the line.