What Actually Happens When You Need a Stoma
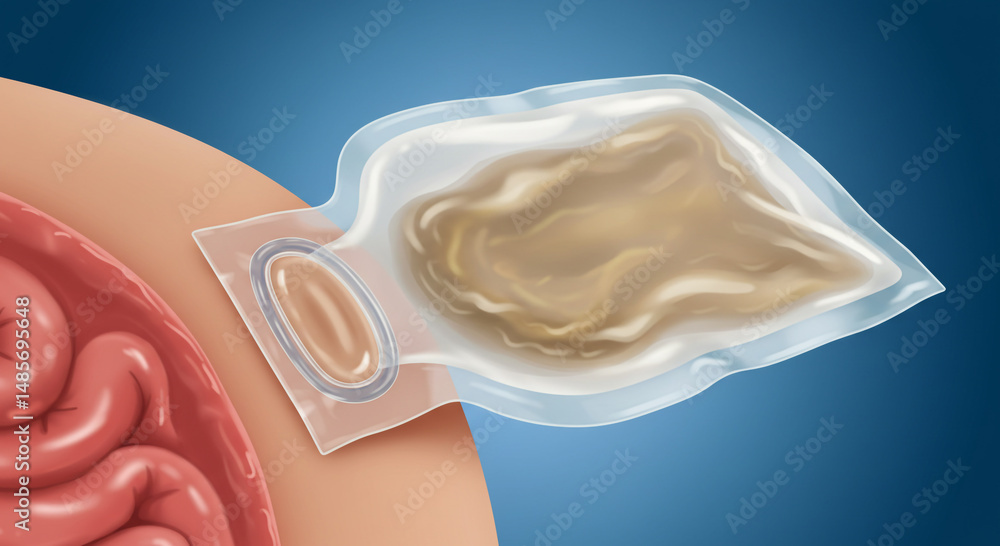
I first encountered this situation during a trauma rotation when a young patient came in with a complete mesenteric avulsion after a motorcycle accident. The bowel was viable but there was no way to preserve continuity, so we had to create an emergency colostomy. What I learned from that case still shapes how I approach these procedures today. The term you are looking at surgically refers to creating an artificial opening from an internal organ or vessel to the exterior surface of the body. In clinical practice, this usually means bringing a segment of intestine through the abdominal wall to form a stoma. The output then collects in an external pouching system rather than passing through the normal anal route.
Surgical Creation Of An Artificial Opening The Lifesaving Procedure Known As Ostomy
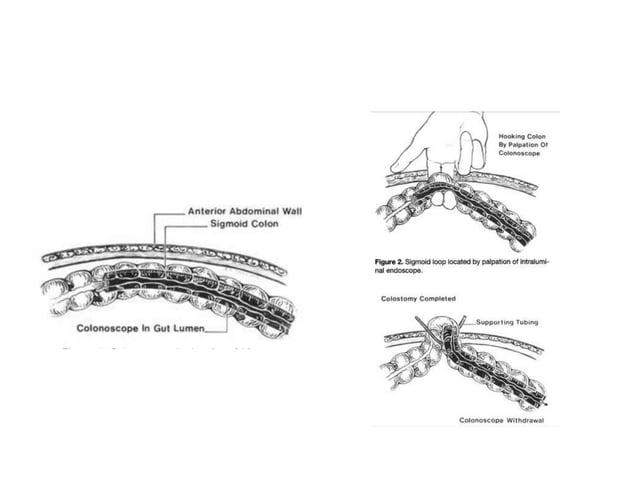
Before I talk about the technical steps, let me address something most patients never ask about. A stoma is not a wound that heals closed. It is permanent tissue that will continue functioning as long as blood supply is maintained. When I show patients what their stoma will look like, I use actual surgical photos from prior cases because descriptions never prepare people for the reality of pink-red tissue protruding two centimeters above the skin line. The basic procedure follows a straightforward sequence. First, you select the site. Right upper quadrant for ileostomy, left lower quadrant for colostomy. I always mark the patient preoperatively while they are sitting, standing, and lying down because posture changes shift the abdominal contour significantly. A stoma placed on a skin fold or within a belt line becomes a nightmare for pouching later. Next comes the actual surgical creation. You make a circular incision through the fascia at the marked site. The diameter matters. Too tight and you risk ischemia and retraction. Too loose and parastomal hernia becomes almost inevitable. I typically use a fascial opening equal to the width of my index finger, roughly two to three centimeters for most adults.
Then you bring the bowel through. For an ileostomy, I prefer a terminal ileostomy over a loop technique when possible because loop ileostomies have higher output and more skin complications. The bowel is everted and sutured to the dermis with absorbable material in a running fashion. Six to eight interrupted sutures work better than continuous for maintaining even eversion.
Get the Full Details

What Goes Wrong That Nobody Warns You About
I spent three years dealing with high-output stoma patients before I understood why some cases simply would not respond to standard management. The issue usually involves sodium handling and fluid balance that most general practitioners completely miss. When I had a patient losing four liters daily from a small bowel resection with end ileostomy, IV fluids alone failed because the output remained uncontrolled. The workaround I eventually used involved combining oral rehydration solution with specific dietary modifications. Loperamide before meals, avoiding hyperosmolar drinks, and adding soluble fiber like psyllium to thicken the effluent. This reduced output from four liters to approximately one liter per day over two weeks. Another problem that catches people off guard involves parastomal hernia development. I initially thought this only affected elderly patients with poor tissue quality. Then I treated a thirty-two-year-old accountant whose stoma appliance leaked daily due to herniation around the fascial defect. The hernia had developed despite proper surgical technique because he returned to heavy lifting too soon postoperatively. I learned to emphasize strict lifting restrictions and abdominal support garments for at least eight weeks in all cases.
The Realities of Living With an Ostomy
Most patients focus entirely on the surgery itself. They rarely consider what daily life actually involves. A stoma requires constant monitoring of output volume, frequency of pouch changes, and vigilance for skin complications around the peristomal area. I recommend patients start practicing pouch management before discharge. Most hospital ostomy nurses provide excellent instruction, but learning on yourself matters more than watching someone else do it. I always have patients handle the appliances themselves during the preoperative marking session when possible. The psychological adjustment deserves equal attention to the physical aspects. I once treated a patient who hid her stoma from her spouse for six months despite successful surgery. Body image disturbance after ostomy creation affects roughly forty percent of patients, yet most surgeons only address the technical outcome. Support groups and counseling should be routine recommendations, not optional referrals.
When Ostomy Is Not the Right Choice
I cannot stress enough that these procedures carry real risks and limitations. Parastomal hernia develops in approximately twenty-five percent of patients within five years. Skin breakdown around the stoma affects thirty to forty percent. High output from small bowel ostomies can cause severe dehydration if not managed aggressively. Certain patient populations simply do not tolerate ostomy well. Severe cognitive impairment prevents adequate self-care. Untreated psychiatric conditions compromise compliance. Morbid obesity creates technical challenges that often outweigh benefits. In these cases, I consider alternative approaches or involve multidisciplinary teams early in the decision-making process. The decision to create an ostomy should never be rushed, but it also should not be delayed unnecessarily. I balance the immediate surgical needs against long-term quality of life considerations carefully. Every patient deserves honest discussion about both the benefits and the substantial lifestyle modifications that accompany permanent stoma creation.