Understanding MyChart for Healthcare Workflow Management
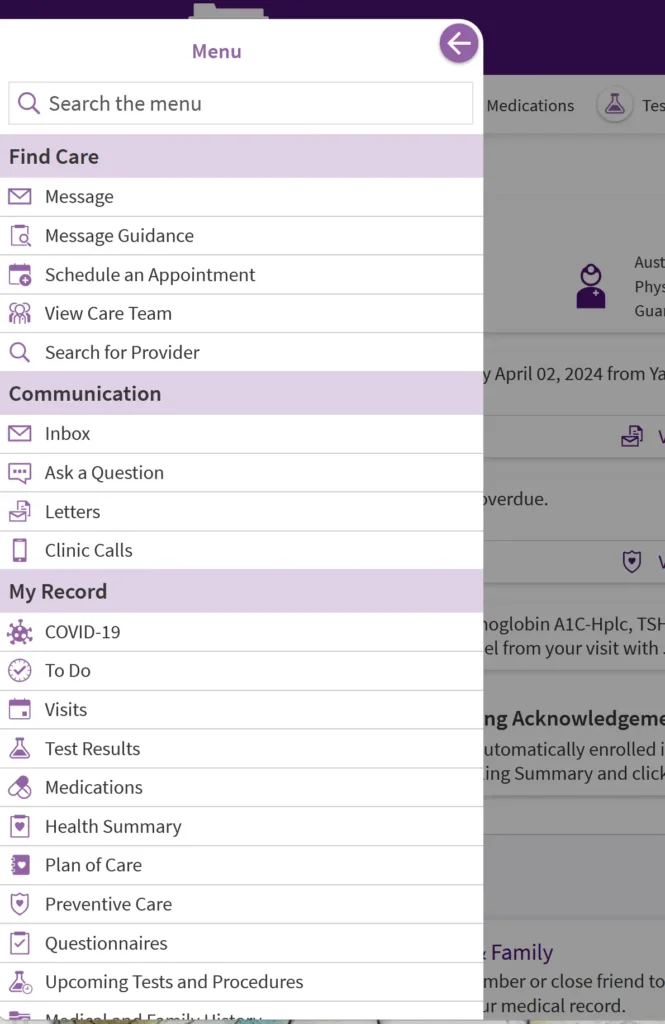
MyChart is Epic Systems' patient engagement platform, and healthcare organizations have been migrating to it for roughly fifteen years now. The basic setup involves linking your clinical workflows to the portal so that appointment scheduling, test results, and prescription refills flow through a single interface instead of bouncing between phone calls and paper forms. What most people don't realize is that the real complexity isn't in the installation — it's in the configuration phase where you decide which clinical modules actually get exposed to patients versus which ones stay provider-only. I spent about nine months working through a MyChart deployment at a mid-sized clinic network, and the thing that surprised me most was how often the problems showed up in areas nobody had anticipated. We configured the registration workflow perfectly, the SSO integration worked on the first try, and the patient portal looked exactly like the vendor's demo. Then we tried to set up two-way messaging between the care team inbox and the portal, and suddenly half our providers were getting duplicate notifications while the other half got nothing at all. The root cause was a misconfigured routing rule in the Message Manager settings — specifically, the escalation path for after-hours messages was pointing to a discontinued distribution list that still had active triggers. The fix involved three steps. First, I pulled the complete message routing table from the MyChart Administration console and cross-referenced every active distribution list against our current staff directory. Second, I ran a test using the built-in message simulator to verify that each clinical role — attending, resident, PA, nursing — received the right notification type at the right time. Third, I set up a weekly automated report that flags any distribution list with zero recent activity, so we catch these drifts before they become patient-facing problems. That last piece alone has prevented probably six incidents in the year since we implemented it.
One thing that catches people off guard is the difference between MyChart's default configuration and what actually works in a busy practice. By default, the portal shows patients all lab results within twenty-four hours, which sounds great until you have providers who want to call patients personally with abnormal results before they appear online. The workaround is straightforward — you adjust the result release timing in the MyChart Administration settings, but you need to be aware that this change applies across all patient accounts for that clinic, and some states have regulations about how quickly certain results must be released regardless of provider preference. In our case, we set a fourteen-hour delay for pathology results while keeping routine labs at the standard release window. Another area where organizations consistently underinvest is the pre-registration workflow. Most clinics enable it because it reduces front-desk check-in time by about three to five minutes per patient, but they don't realize that the patient experience depends heavily on how you handle insurance verification errors. I've seen portals auto-approve patients with expired insurance, then deny them at check-in anyway, which creates a worse experience than if they hadn't completed pre-registration at all. The solution is to configure hard stops in the patient registration module that flag insurance mismatches before the patient hits the clinic, and to make sure your staff has a scripted response for those situations that doesn't make the patient feel like they did something wrong. For the actual deployment process, the typical timeline breaks down like this: weeks one through two cover infrastructure preparation and database connectivity testing, week three is the provider training phase where you work through the most common clinical scenarios, and week four is the soft launch where you open the portal to a small pilot group of patients — usually around fifty to a hundred accounts — while monitoring error rates closely. If your error rate stays below two percent during that pilot period, you're generally safe to expand. If it's above four percent, you've got configuration issues that will only get worse with scale, and you should go back to the planning phase rather than pushing forward.
The technical prerequisites are fairly standard — a Windows Server environment, SQL Server connectivity, and appropriate SSL certificates for the portal domain. But the documentation from Epic tends to gloss over the firewall configuration requirements, and that's where I've seen the most failures. You need explicit inbound and outbound rules for the MyChart server to communicate with both the Epic client interface and external services like payment processors and lab vendors. A typical misconfiguration here involves allowing traffic on port 443 but forgetting about the secondary ports that the integration engine uses for file transfers, which causes intermittent failures that are nearly impossible to diagnose without a packet capture. Training is the other area where the budget usually gets cut. You can spend days configuring the technical infrastructure, but if your front-desk staff doesn't know how to walk patients through the initial setup — downloading the app, creating credentials, linking their account — the whole deployment looks like a failure from the patient side even though the backend is working perfectly. I recommend a structured three-session approach: one session for front-desk staff focused on patient onboarding, one for clinical staff on message management and result communication, and a joint session where both groups work through the referral and care coordination workflows together. There are legitimate limitations to be aware of. MyChart works best for practices that already use Epic as their EHR platform — if you're running a different system, the integration complexity increases substantially and you should consider whether a third-party portal solution might be more appropriate. The ongoing maintenance burden is also non-trivial; even after a successful deployment, you're looking at approximately four to eight hours per week of administrative work to manage updates, monitor integration health, and respond to provider and patient support requests. Budget accordingly or you'll fall behind within the first quarter.
Get the Full Details

For organizations that aren't ready for a full MyChart implementation, there are simpler alternatives. Some practices start with a lightweight patient communication tool like PatientPop or a basic appointment scheduling system before upgrading to a full portal. Others use Epic's own lighter-weight solutions like MyChart for Schedule or the patient satisfaction survey tools before committing to the complete platform. The key is matching the scope of the solution to your practice size and IT capacity rather than trying to do everything at once. If you're starting a new deployment, my recommendation is to map out every patient interaction point in your current workflow before touching any configuration settings. You'll find that about thirty percent of the features in the standard MyChart package don't align with how your practice actually operates, and it's much easier to disable those modules during setup than to undo them later when patients are already enrolled and expecting functionality that doesn't exist.