What Stratified Squamous Epithelium Actually Does
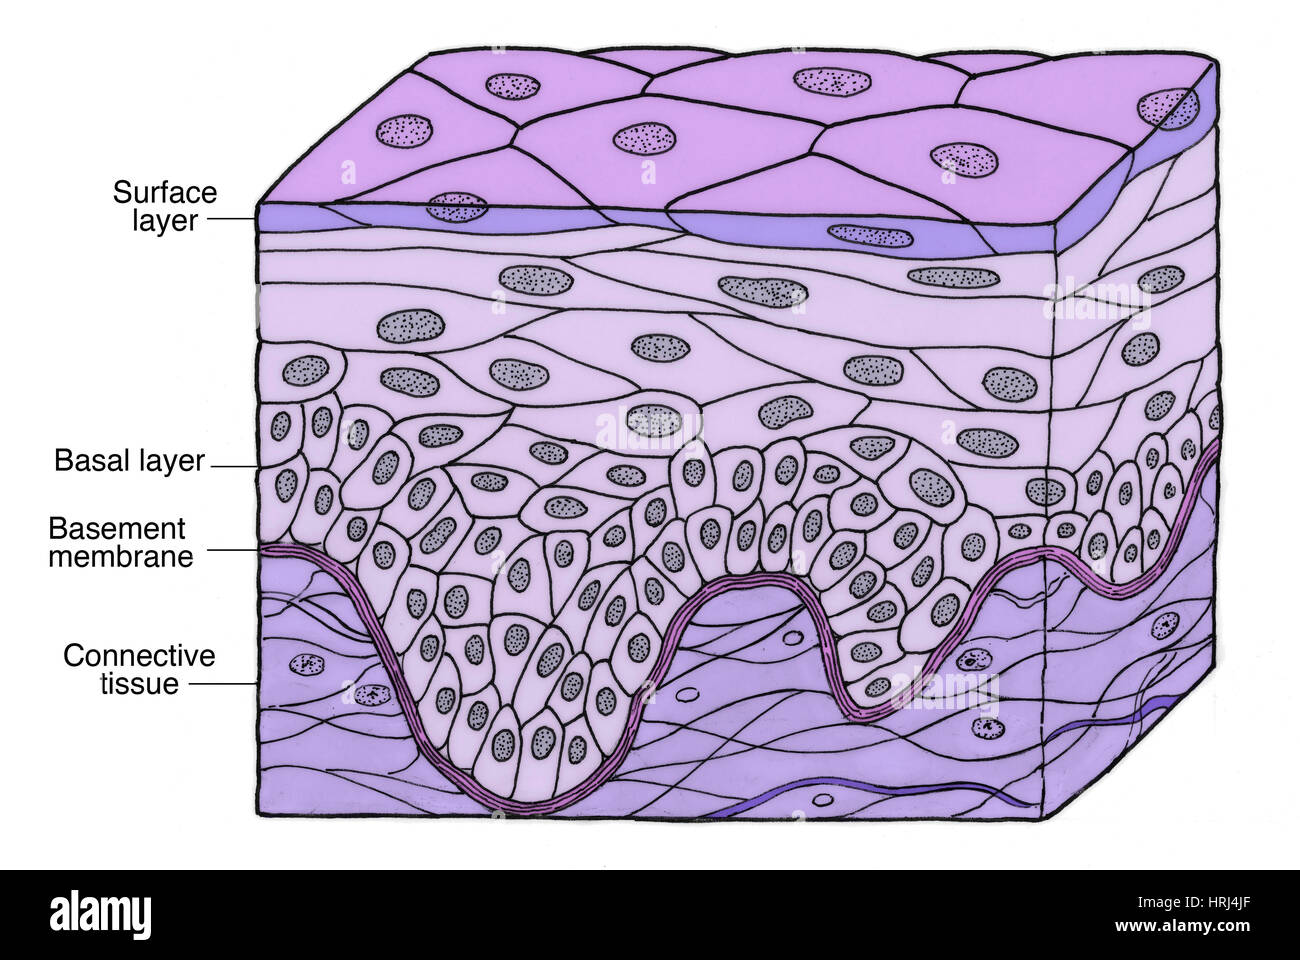
Most people think of their skin as just a barrier, but the tissue underneath is far more complex than a simple wall. Stratified squamous epithelium The Unseen Shield Protecting Your Bodys Surfaces is the histological term for a multi-layered cell structure designed for protection against mechanical stress, abrasion, and dehydration. It lines your entire outer surface, from the epidermis down through your esophagus, vagina, and anal canal. The name itself describes the architecture: "stratified" means stacked layers, "squamous" refers to the flat, scale-like appearance of the outermost cells. I spent three years in a histology lab before I ever fully understood why this tissue is organized the way it is. The key insight most people miss is that the cell shape you see at the surface doesn't determine the tissue type — the layering does. You can have stratified squamous epithelium that appears columnar at the basal layer and completely keratinized at the surface, or non-keratinized where the surface cells stay plump and nucleated. The difference between keratinized and non-keratinized is critical and usually ignored in introductory courses. Keratinized stratified squamous epithelium is what you find in the epidermis. The dead, flattened cells on top are packed with keratin protein and form a waterproof barrier. Non-keratinized versions line the moist cavities inside your body, and those surface cells still retain their nuclei. This distinction matters when you're looking at biopsy slides or studying pathology, because disease processes affect each version differently. A fungal infection will present differently on keratinized versus non-keratinized tissue, and the immune response varies accordingly.
Cell Turnover and Regeneration
The basal layer contains stem cells and rapidly dividing progenitor cells that continuously push new cells upward. As these cells migrate toward the surface, they undergo a process called keratinization or cornification. They lose their organelles, flatten out, and eventually slough off. In the epidermis, this entire turnover cycle takes roughly 28 to 42 days depending on age, location on the body, and overall health status. The mucosal surfaces turn over much faster, sometimes in just a few days. I once had a student who couldn't understand why a throat swab for strep testing doesn't come back with false positives from normal flora as often as you'd expect. The answer is the rapid turnover rate of the non-keratinized stratified squamous epithelium in the pharynx. Old cells shed constantly, which means pathogens have less time to establish deep attachment. That said, this also means some antibiotics penetrate less effectively because the target tissue is actively renewing itself.
Where This Tissue Fails and What Happens
The biggest limitation of stratified squamous epithelium is that it has no intrinsic mechanism to repair itself when the damage is severe enough to destroy the basal layer. Burns, chronic friction, or autoimmune blistering diseases like pemphigus vulgaris can compromise the stem cell population, and without those cells, regeneration stalls. The body responds with scar tissue, which is fibrous connective tissue, not epithelium. Scar tissue lacks the protective and sensory functions of the original epithelium. Another issue that doesn't get enough attention is the trade-off between thickness and sensation. The thicker the stratified squamous epithelium, the better the mechanical protection, but the more the nerve endings are buffered from the surface. This is why the soles of your feet are tough but relatively insensitive compared to your fingertips, even though both areas have stratified squamous epithelium. The mechanoreceptors in thick skin are located deeper in the dermis, not in the epithelial layer itself.
Get the Full Details

Practical Considerations
If you're working with tissue samples, the orientation of the cut matters enormously. A tangential section through stratified squamous epithelium can look completely different from a perpendicular one, and beginners often misidentify the tissue type based on a poor slice. Always confirm that you're seeing the basal layer attached to the basement membrane before drawing conclusions about cell morphology. Staining techniques also influence interpretation. Hematoxylin and eosin (H&E) is standard, but PAS staining reveals the basement membrane zone more clearly, which is essential when evaluating conditions like lichen planus or lupus erythematosus where the interface between epithelium and connective tissue is the primary site of pathology. There's no downloadable resource that replaces actual practice with a microscope, but if you're looking for reference slides, the digital pathology collections at major medical schools are generally free and high quality. Search for "stratified squamous epithelium H&E" along with the specific anatomical site you're studying, because the same tissue type looks subtly different in the esophagus versus the cervix versus the skin.


