Understanding Post-Coital Bleeding in the Context of Fertility Tracking
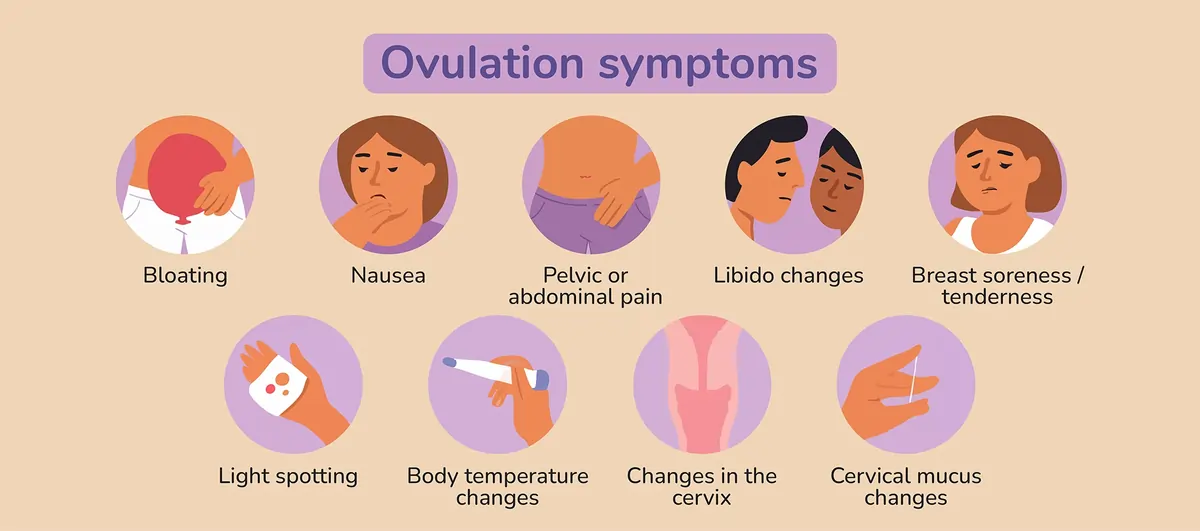
Spotting after intercourse during the ovulation window is something I see come up constantly in consultations, and most people either panic or completely ignore it. Both reactions miss the point. The bleeding itself is usually mechanical — the cervix becomes more vascular and sensitive right before and during ovulation due to hormonal shifts, and friction from intercourse can easily rupture tiny surface blood vessels. That part is straightforward. What matters is whether that spotting lines up with other fertility markers or stands alone as an anomaly. Here is the practical breakdown of what this actually tells you about your cycle and fertility. The timing of the spotting relative to your ovulation signal is the key variable. If you are tracking with basal body temperature, cervical mucus, and possibly LH strips, and the spotting shows up at the same time as peak fertility indicators, it is likely just cervical irritationed on top of ovulatory changes. The cervix is softer, more ectopic, and engorged with blood at that point. Intercourse is essentially a minor trauma event to tissue that is already in a fragile state. However, if the spotting appears consistently after sex but does not coincide with your fertile window, or if it is accompanied by other symptoms like unusual discharge, pelvic pain, or bleeding between periods, that moves into a different category entirely. Polyps, cervical ectropion, infections, or even early pregnancy changes can present this way. I had a patient last year who tracked her cycles meticulously and noticed a very specific pattern: light pink spotting always appeared roughly 24 hours after intercourse, never during ovulation, and it lasted about half a day. She was convinced it was ovulation-related because she had read articles online linking post-coital bleeding to fertility. We ran a pelvic ultrasound and found a small cervical polyp. Removal resolved it completely. The lesson here is that timing assumptions based on internet reading can mislead you. Real tracking means correlating the bleeding with your actual data, not with what you expect to see.
From a fertility perspective, a single episode of light spotting after intercourse during your fertile window does not indicate a problem with conception. Sperm viability is not affected by the presence of a small amount of blood in the vaginal canal. The blood does not wash sperm out, and it does not change cervical mucus function enough to block sperm transit. What it can indicate is that your cervical tissue is responsive to hormonal changes, which is actually a sign of a hormonally active cycle. Some fertility specialists note that women who experience mild ovulatory spotting sometimes have slightly longer luteal phases, though this is not a reliable diagnostic marker on its own. The counter-intuitive part that most people miss is that some spotting during the fertile window can be a useful data point if you are trying to conceive without medical monitoring. If you do not use ovulation predictor kits, noticing that spotting occurs on the same day or the day after your peak cervical mucus can help you refine your understanding of your personal ovulation timeline. I keep a simple spreadsheet for my own tracking: date, mucus observation, spotting yes or no, temperature, and intercourse. Over six months, the pattern became clear enough that I could predict my ovulation window within a two-day margin without any test strips. That kind of calibration only works if you record everything honestly, including spotting that feels embarrassing or inconvenient to log. There are limitations to this approach that nobody talks about enough. Cervical spotting can be caused by things unrelated to ovulation or fertility, including rough intercourse, new sexual partners, changes in contraception, or even aggressive internal cleansing. If you introduce any of those variables, the spotting loses its informational value as a fertility marker. You cannot cleanly separate the cause without looking at the full picture. Additionally, if you are trying to conceive and notice spotting every cycle after intercourse, it is worth discussing with a clinician. Recurrent post-coital bleeding is not normal, even if it is often benign. Cervical screening, STI testing, and a basic pelvic exam should be the first step, not assumption.
For people who want to use this observation practically, the method is simple. Track your cycle for at least three months using one reliable fertility indicator — cervical mucus is the most accessible. Note the day you observe clear, stretchy, egg-white consistency mucus, then note whether spotting occurs within 48 hours of intercourse on or near that day. If the correlation is consistent across multiple cycles, you have a real data point. If it is sporadic, treat it as noise. Do not build a conception strategy around sporadic spotting because it will lead you to misidentify your fertile window, which is far more costly than any amount of light bleeding. I also want to address a common pitfall: assuming that any brown or old blood after intercourse means implantation or early pregnancy. This is a persistent myth in fertility communities. Implantation bleeding, when it occurs, typically happens 6 to 12 days after ovulation and is independent of intercourse. Spotting that appears hours or a day after sex is cervical in origin, not uterine. Confusing the two can lead to false hope or unnecessary anxiety, both of which distort your ability to track accurately. Keep the signals separate. Cervical irritation is cervical. Uterine bleeding is uterine. The timing and color are usually telling: bright red and immediate points to the cervix or vaginal canal, while brown or dark spotting that appears days later is more likely to be hormonal or uterine in origin. If you are actively trying to conceive and want to maximize the useful information from your cycle, consider pairing your spotting observations with LH testing. The combination gives you a clearer picture than either method alone. LH surge typically precedes ovulation by 24 to 36 hours, and if spotting appears around that window after intercourse, you can confidently mark it as ovulation-adjacent cervical irritation rather than something else. This reduces guesswork and helps you time intercourse with more precision, which is the actual goal here.
Get the Full Details

Ultimately, spotting after intercourse during ovulation is neither a fertility blessing nor a red flag by itself. It is data. Like any data, its value depends on how carefully you collect it and whether you interpret it in context. The people who get the most out of this observation are the ones who track consistently, cross-reference with other markers, and know when to stop interpreting and start investigating with a professional.