
Understanding and Addressing Speech Delay in Children
Speech Delay Can It Be Cured Unlocking The Path To Clearer Communication
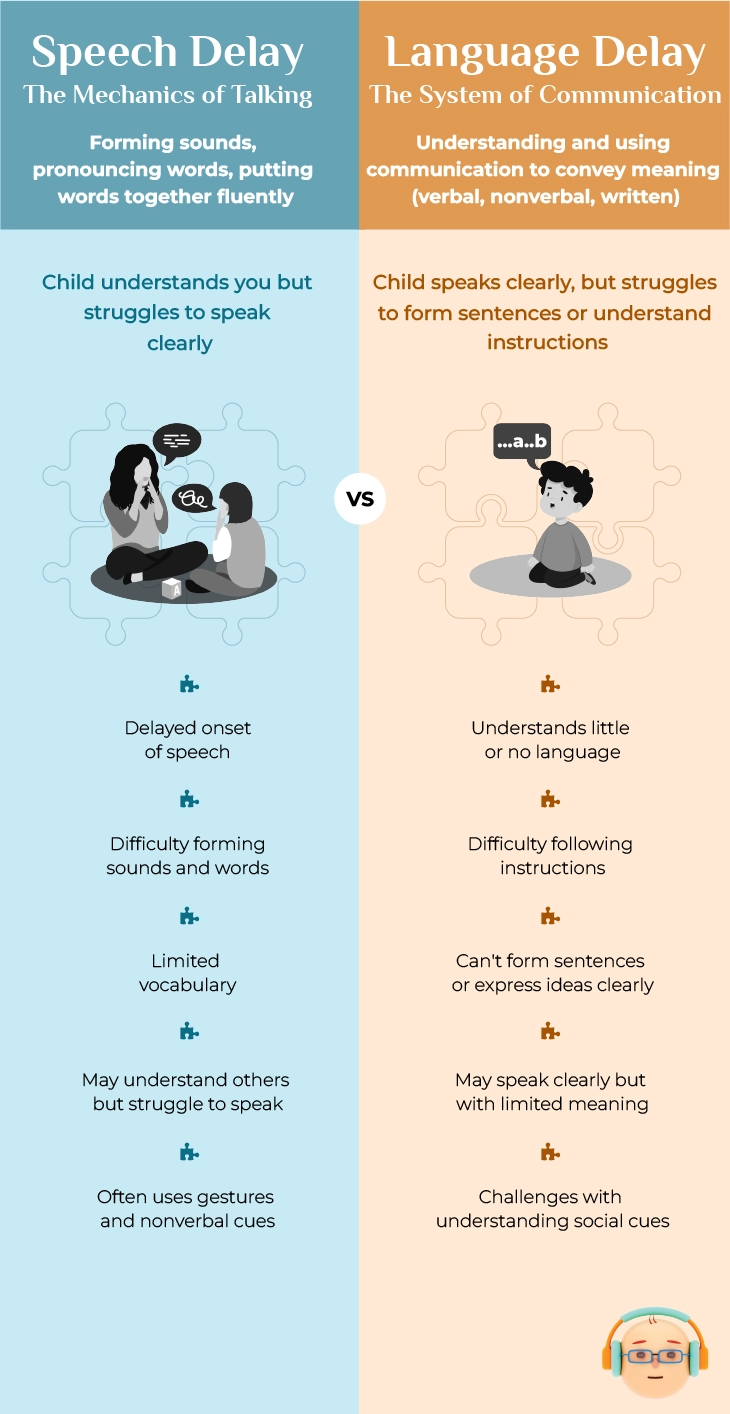
Speech delay is not a single condition with a single fix. It is an umbrella term for kids who are not meeting language milestones at the expected age. Some children catch up on their own. Others need structured therapy. The difference usually comes down to identifying the underlying cause early enough. I worked in pediatric speech-language pathology for over a decade, and the thing that surprised me most was how often parents missed the early signs simply because they were comparing their child to an older cousin or a neighbor's kid who spoke early. Milestones vary, but there are hard cutoffs where delay becomes clinically significant. By 18 months, a child should have at least 50 words and be combining two words together. If not, it is worth getting an evaluation before the preschool years. The first step is always a hearing test. I cannot stress this enough. Conductive hearing loss from chronic ear infections is one of the most common and most overlooked causes of speech delay. A child who cannot hear clearly will not produce clear speech. It is that direct. We had a case where a three-year-old was not talking past tense at all. His parents thought he was just stubborn. An audiologist found a significant middle ear effusion. Once the tubes were placed and his hearing normalized, his speech improved dramatically within six months. The "delay" was never neurological. It was mechanical.
When a child does present with true developmental language delay, the gold standard intervention is speech-language therapy. But not all therapy is created equal. The most effective programs use a combination of parent-mediated strategies and direct clinician sessions. Research shows that involving caregivers in therapy sessions improves outcomes significantly compared to clinician-only models. Parents do not need special training to implement basic strategies. They need consistency. One counter-intuitive finding from the literature is that reading to a child is valuable, but passive reading is not enough. Dialogic reading — where the adult asks open-ended questions, expands on what the child says, and encourages the child to narrate — produces measurably better language outcomes than simply reading aloud. A study from the Journal of Speech, Language, and Hearing Research found that children who engaged in dialogic reading four times per week showed a 30 percent faster rate of vocabulary growth over six months compared to the control group. That is a meaningful difference. It compounds over time. Another area where people frequently go wrong is correcting a child's speech. The instinct is to say "no, say it like this." That approach actually increases anxiety and can reduce a child's willingness to attempt words. The better technique is recasting. If a child says "I runned fast," you respond with "You ran fast!" without directly correcting them. You model the correct form naturally within conversation. This preserves the child's confidence while still providing the linguistic input they need.
Sometimes the root cause is not language at all but motor speech planning. Childhood apraxia of speech is a neurological disorder where the brain has difficulty coordinating the movements needed for speech. It is often misdiagnosed as a standard speech delay because the symptoms overlap. Key distinguishing features include inconsistent error patterns — the same word pronounced differently each time — and difficulty with syllable transitions. If a child's speech looks erratic rather than consistently simplified, it warrants a referral to a specialist familiar with apraxia. Standard therapy approaches often fail for these children because the issue is motor planning, not language comprehension. I once worked with a five-year-old boy who had been in therapy for two years with minimal progress. He had been diagnosed with a general speech delay. We reevaluated and discovered subtle signs of childhood apraxia that had been missed. Switching to a motor-based approach — specifically the DLM (Dynamic, Motor-Learning) method — produced results in three months that the previous two years had not. The lesson here is that misdiagnosis is common, and second opinions matter. If a child is not progressing after six months of consistent therapy, it is reasonable to seek a comprehensive reassessment. Technology can support therapy but it cannot replace it. Apps and programs claim to address speech delay, and some have genuine evidence behind them. However, screen time alone does not teach language. Language is learned through social interaction. A child watching a video about animal sounds is not getting the same neural stimulation as a caregiver naming animals during play. The American Academy of Pediatrics recommends limiting screen time for children under five anyway, so using apps as a supplement rather than a primary intervention is the more reasonable approach.
Get the Full Details
Autism spectrum disorder and speech delay frequently co-occur. About 30 percent of autistic children are minimally verbal. If speech delay exists alongside other developmental concerns — limited eye contact, repetitive behaviors, sensory sensitivities — a comprehensive developmental evaluation should be pursued alongside speech therapy. Treating the speech delay in isolation when an underlying neurodevelopmental condition is present will yield incomplete results. The prognosis for most children with speech delay is positive. Early intervention is the strongest predictor of outcome. The earlier therapy begins, the less compensatory work is needed later. Children who start therapy before age four tend to catch up to their peers by elementary school. Those who wait until after kindergarten often carry their delays into adolescence and beyond, which can affect academic performance and social development. If you suspect your child has a speech delay, the path forward is straightforward. Start with a hearing evaluation. Then consult a speech-language pathologist for a comprehensive assessment. Take the assessment results seriously. Commit to the recommended therapy plan. Reinforce skills at home through the strategies discussed. Monitor progress every three to six months. Adjust the approach if there is no measurable improvement.
There is no single cure for speech delay because it is not a disease. It is a descriptive term for a collection of possible conditions. Some resolve with time. Some require targeted intervention. A few have no complete resolution but can be managed effectively with the right supports. The goal is not perfection. The goal is functional communication that allows the child to participate fully in life.



