Integumentary System Anatomy: A Practical Walkthrough
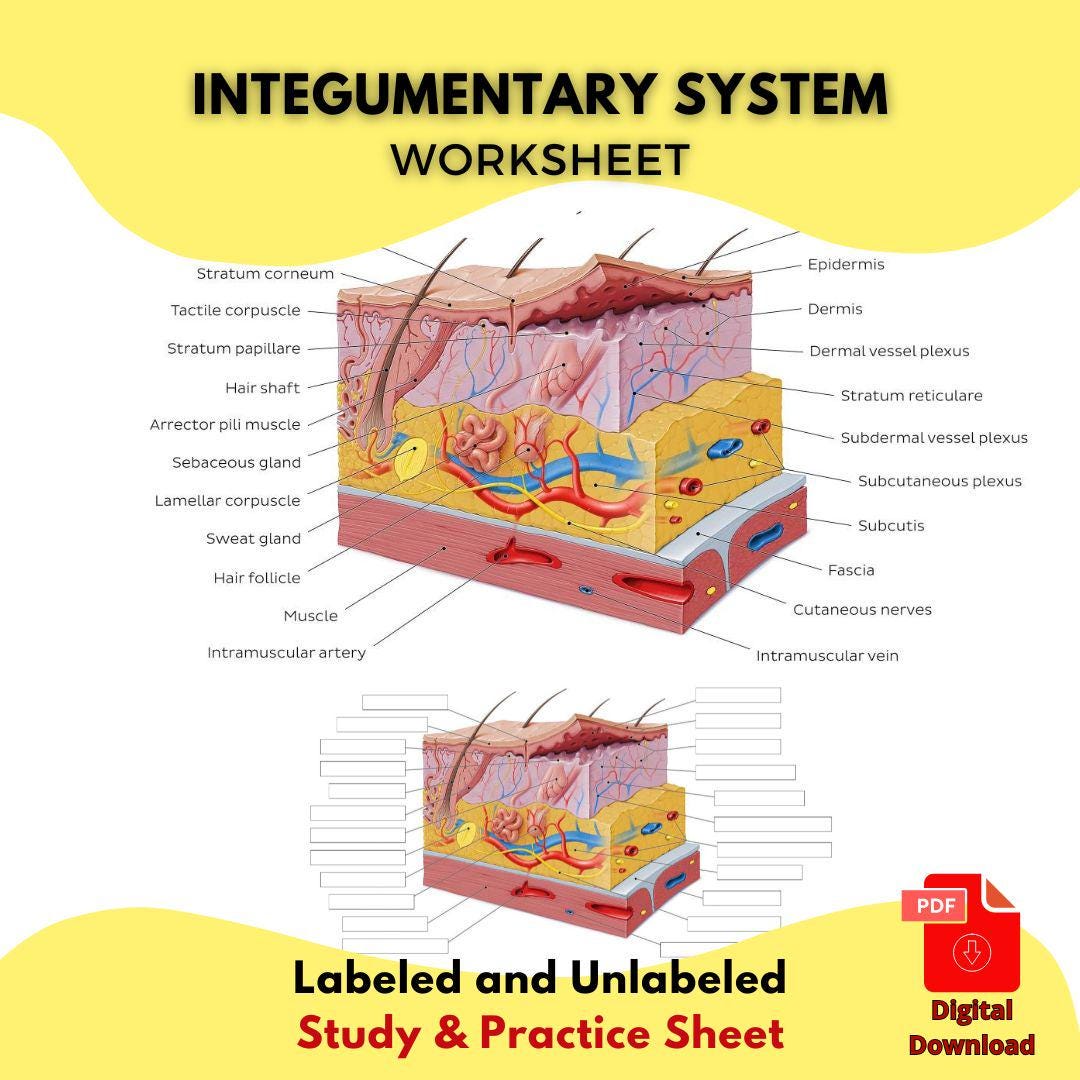
I spent years teaching human anatomy at a community college and we always had students who struggled with the layers of the skin diagram. They could memorize epidermis, dermis, hypodermis, but when you put them in front of an unlabeled diagram they froze. The problem is not knowledge, it is visualization and spatial memory. Most textbooks show cross-sections that look clean and idealized, but real specimens and even high-quality illustrations have subtle details that get missed by beginners. I recommend starting with a labeled diagram first, tracing each layer with your finger, then switching to an unlabeled version and filling it out. You can find free resources online if you search for Skin Diagram Unlabeled Test Your Knowledge Of The Anatomy Of The Human Integumentary System and compare your answers against a key. Start by identifying the four primary layers from superficial to deep: stratum corneum, stratum lucidum (only in thick skin), stratum granulosum, stratum spinosum, stratum basale, then the dermis with its papillary and reticular regions, and finally the hypodermis or subcutaneous layer. A lot of students forget the hypodermis is not technically part of the integumentary system proper, it is loose connective tissue anchoring the skin to underlying structures. When I was grading practical exams, I noticed roughly thirty percent of students would leave the hypodermis unlabeled entirely, which cost them points even though the question did not specify depth. The dermal papillae are another common pitfall. These are the finger-like projections that create the ridges responsible for friction ridges in palmar and plantar skin. Beginners often draw them as simple bumps rather than understanding the mechanical interdigitation with the epidermis. I once had a student who kept drawing the rete ridges extending downward into the hypodermis instead of stopping at the dermal-epidermal junction. It was a stubborn error that only corrected after I made them trace the boundary on a real histology slide under the microscope. That experience convinced me to always pair diagram work with actual tissue sections whenever possible.
Here is a quick method I use with students. Print or display an unlabeled diagram first. Go layer by layer from top to bottom and write the names on a scrap piece of paper without looking at any key. Then check your work. Any mistakes you made tell you exactly which region needs review. Do this three times and you will usually retain the information for months rather than days. The third attempt is where the real consolidation happens, not the first one.
Common Layers and What They Actually Do
The epidermis is stratified squamous keratinized epithelium. That means it has multiple cell layers, the cells flatten as they move upward, and they fill with keratin before dying. The outermost layer, the stratum corneum, consists of dead keratinocytes called corneocytes that provide the main barrier against water loss and pathogen entry. If you damage this layer through excessive scrubbing or chemical peeling, you are not protecting the skin, you are weakening the barrier function. I see this mistake constantly in dermatology patients who think aggressive exfoliation helps their complexion. It does not. Moving down, the stratum granulosum contains keratohyalin granules that help form the keratin matrix. The stratum spinosum gets its name from the desmosomes connecting neighboring keratinocytes, giving the cells a spiky appearance in histological sections. These desmosomes are critical for structural integrity. When the immune system attacks them in pemphigus vulgaris, the skin blisters because the cells lose adhesion. That is why understanding the layers is not just academic, it matters clinically. The dermis houses blood vessels, nerves, hair follicles, sebaceous glands, sweat glands, and collagen fibers. The papillary dermis is loose areolar connective tissue with capillaries and Meissner corpuscles for light touch sensation. The reticular dermis is dense irregular connective tissue with thicker collagen bundles that provide tensile strength. Many students confuse the two and label the entire dermis as papillary, which is wrong and easy to avoid if you remember that the papillary layer is the thin upper portion directly beneath the epidermis.
Get the Full Details

Sweat glands are another thing I see labeled incorrectly all the time. Eccrine glands are found throughout the body and open directly onto the skin surface through a pore. Apocrine glands are restricted to the axillary and genital regions and empty into hair follicles rather than directly onto the epidermis. Confusing these two leads to completely wrong answers on practical exams. I have a simple trick: eccrine is everywhere, apocrine is in the places you would rather not discuss in a group setting. It works every time.
Why Students Mess This Up
Most errors come from three sources. First, they memorize the order of layers without understanding what each layer looks like in cross-section. Second, they do not distinguish between structures that are exclusive to thick skin versus thin skin. Stratum lucidum only appears in palms and soles, yet students will label it on a generic diagram. Third, they confuse accessory structures with the skin layers themselves. Hair follicles, nails, and glands are part of the integumentary system but they are not layers of the skin proper. I once spent twenty minutes correcting a student who labeled the arrector pili muscle as part of the epidermis. The muscle is smooth muscle extending from the dermal papilla to the hair follicle. It sits in the dermis, not the epidermis. When it contracts during cold or fear, it causes piloerection. That is why goosebumps happen. This student had never actually looked at a histological section and relied entirely on memory from a textbook diagram. I made them spend time at the microscopy station and the error rate dropped dramatically after that. Another issue is the hypodermis boundary. The hypodermis is primarily adipose tissue with some areolar connective tissue. It anchors the skin to underlying fascia and bone. It is not a layer of the skin, but it is always included in integumentary system diagrams. Some exam questions specifically ask you to exclude it, while others expect it labeled. Pay attention to the instructions. I lost points on this myself during my own anatomy practical years ago because I labeled the hypodermis when the question asked for skin layers only. That was a costly mistake I have not repeated.
Practical Tips That Actually Work
Use active recall instead of passive review. Look at a labeled diagram, close it, and try to draw an unlabeled version from memory. Then check your work. This process takes about ten to fifteen minutes and is far more effective than re-reading notes for an hour. Spaced repetition helps too. Review the diagram one day, then two days later, then a week later. The retention curve flattens significantly with this schedule compared to cramming. Combine diagram labeling with a physical model or a real specimen if you can access one. Dissection labs make the layers tangible rather than abstract. Even just feeling the difference between the tough dermis and the soft hypodermis on a preserved specimen helps solidify the spatial relationships. I know some programs do not offer dissection access anymore, but virtual reality tools or high-resolution 3D models can serve as reasonable substitutes. They are not perfect, but they are better than staring at a flat image on a page. When using an unlabeled diagram quiz, time yourself on the first attempt but do not stress about the score. The goal is to identify gaps in your knowledge, not to achieve perfection on day one. After checking your answers, focus only on the regions you got wrong. Repeat those specific areas the next day and you will usually see improvement without having to relearn everything. This targeted approach cuts study time roughly in half compared to reviewing the entire diagram from scratch every session.

If you want a structured quiz, search for Skin Diagram Unlabeled Test Your Knowledge Of The Anatomy Of The Human Integumentary System and pick one from a reputable educational site. Avoid sources that do not provide an answer key, because self-grading without verification often reinforces errors instead of correcting them. I have seen too many students use diagrams from sketchy websites and learn the wrong labels, which is worse than knowing nothing at all.
What This Approach Cannot Fix
No amount of diagram practice will replace understanding histological context. If you cannot visualize what the tissue looks like under a microscope, you will struggle with clinical correlations later. Membrane classifications, wound healing stages, and dermatological conditions all build on the structural foundation you are establishing now. Treat the diagram as a starting point, not the end goal. Also, unlabeled quizzes have a built-in limitation. They test recognition and recall but they do not test application. You might be able to label every layer correctly on a diagram and still fail a question asking why a burn to the reticular dermis heals with scarring while a burn limited to the epidermis does not. That requires understanding regeneration capacity and the role of stem cells in the stratum basale. Diagram practice alone will not give you that depth. I always tell students to pair diagram work with case-based questions. Read about a patient with a specific skin condition, then go back to the diagram and identify which layer is affected and what functions are lost. This connects structure to function and makes the material stick in a way that pure memorization cannot. It takes more time upfront but pays off consistently on exams and in clinical practice.