How We Actually Use Sioux Falls Zip Codes In Practice
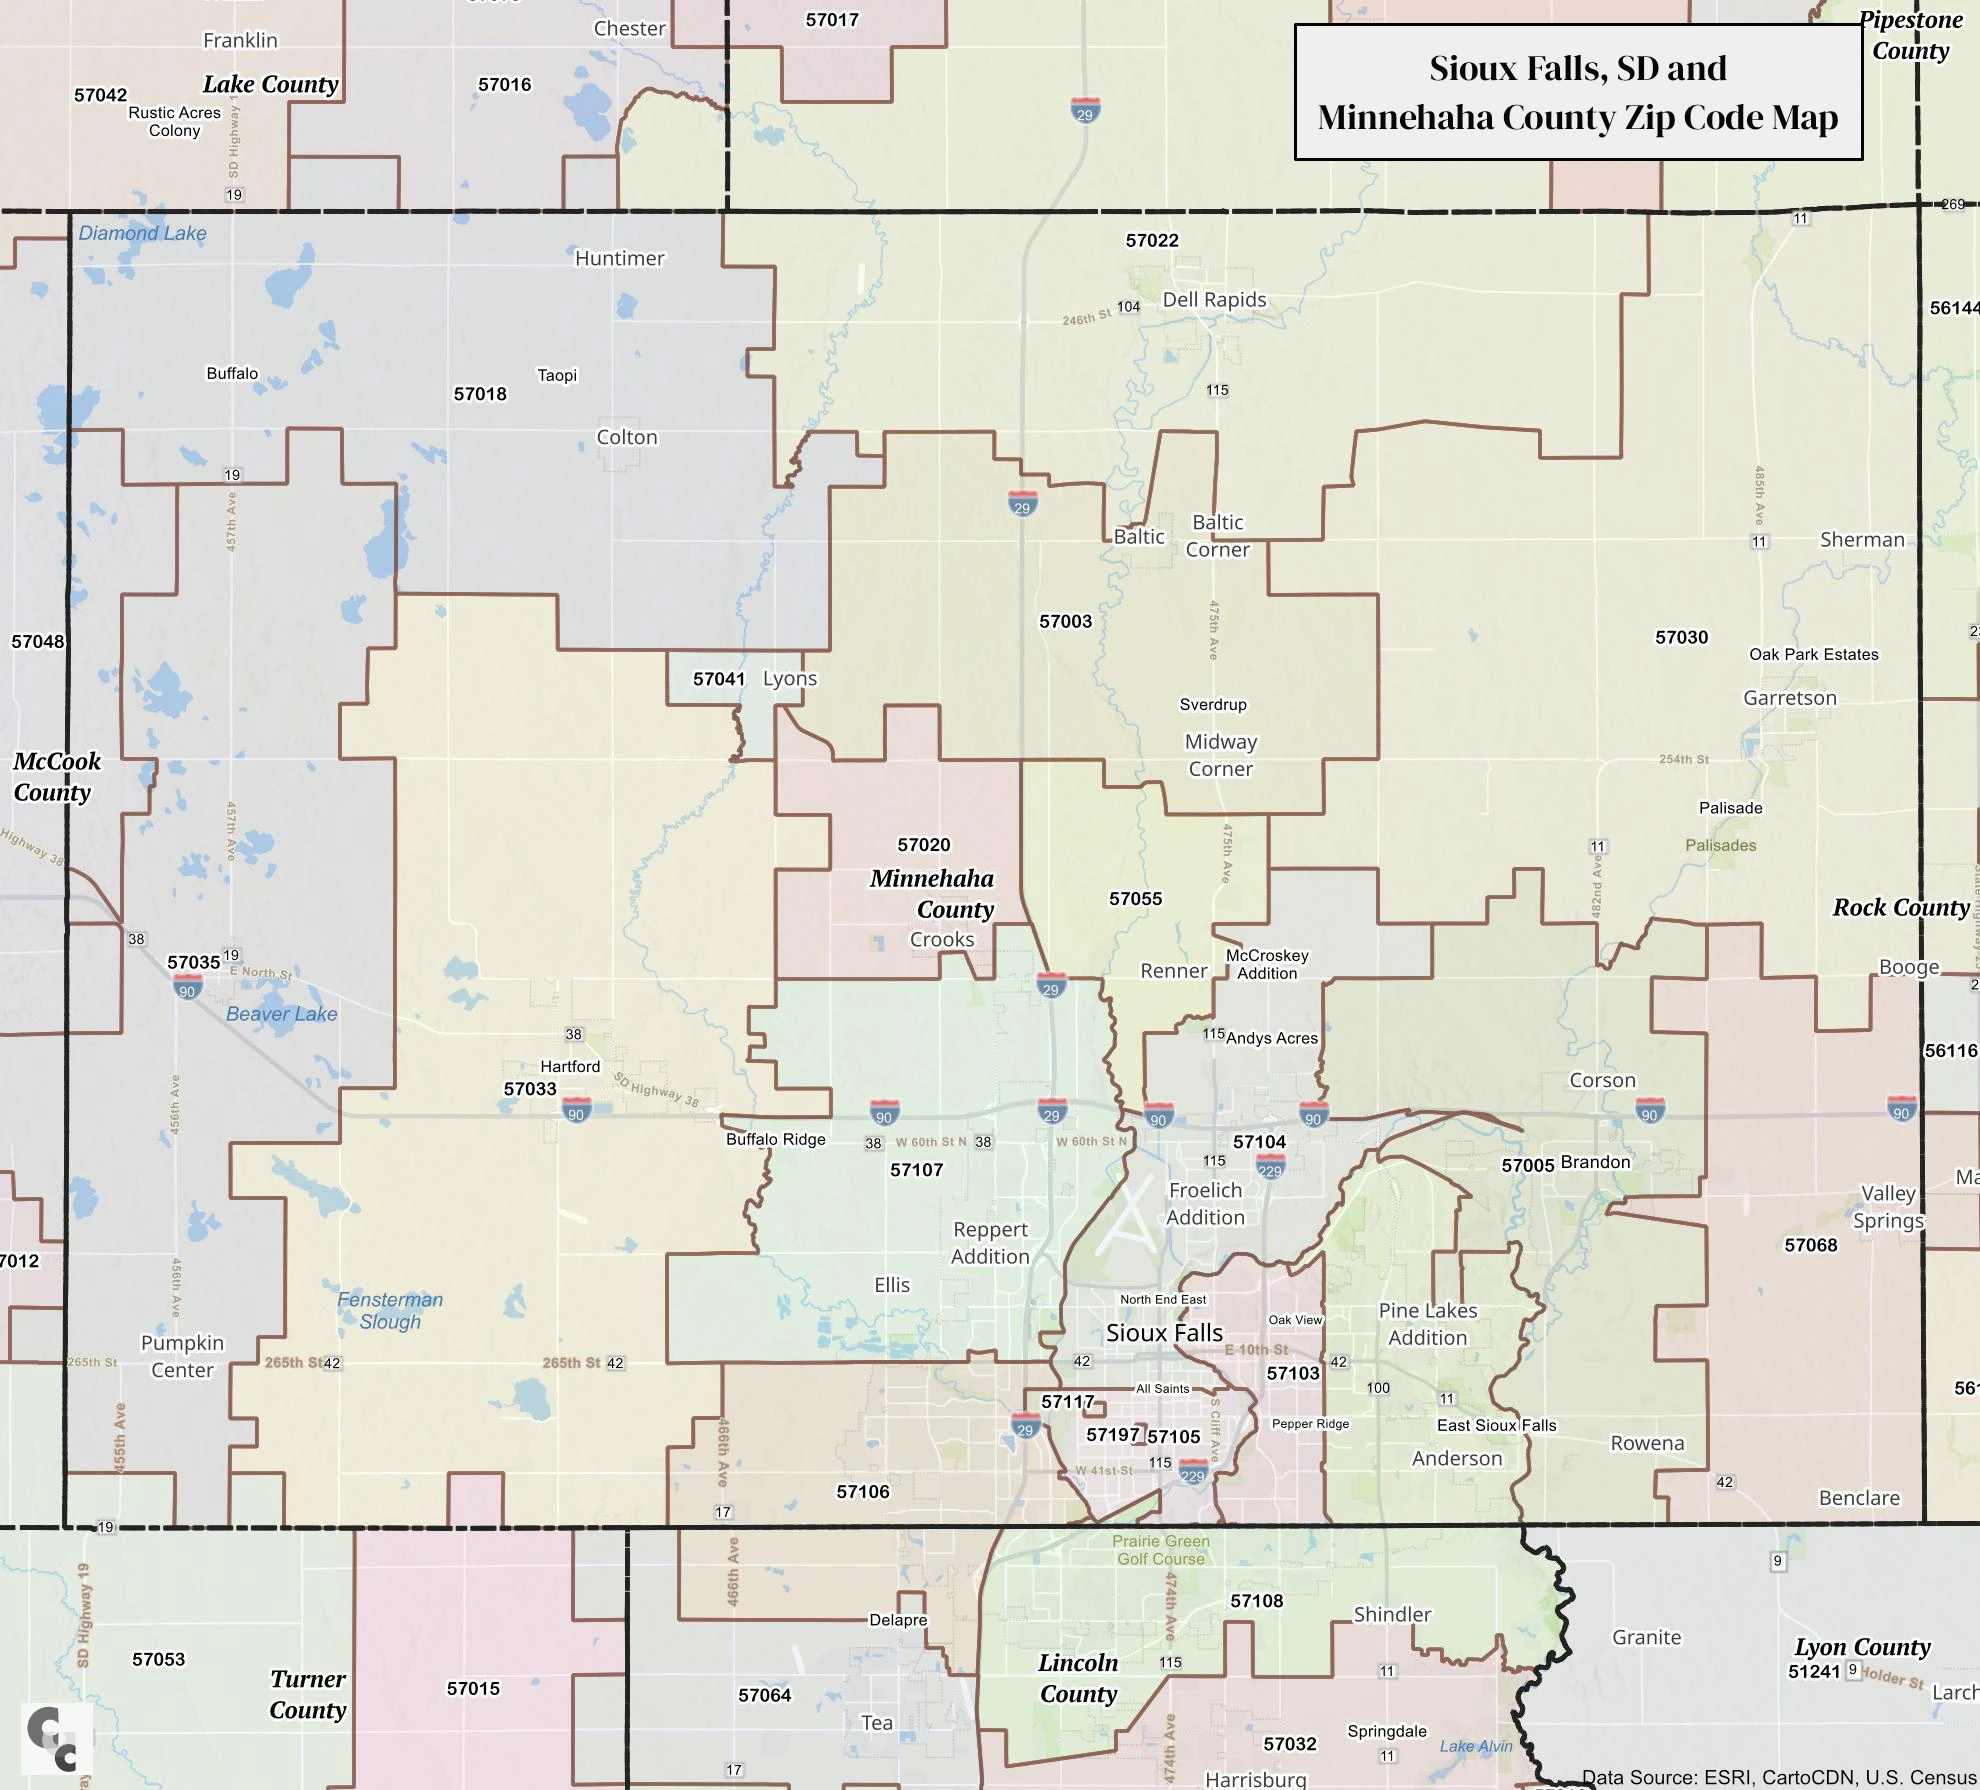
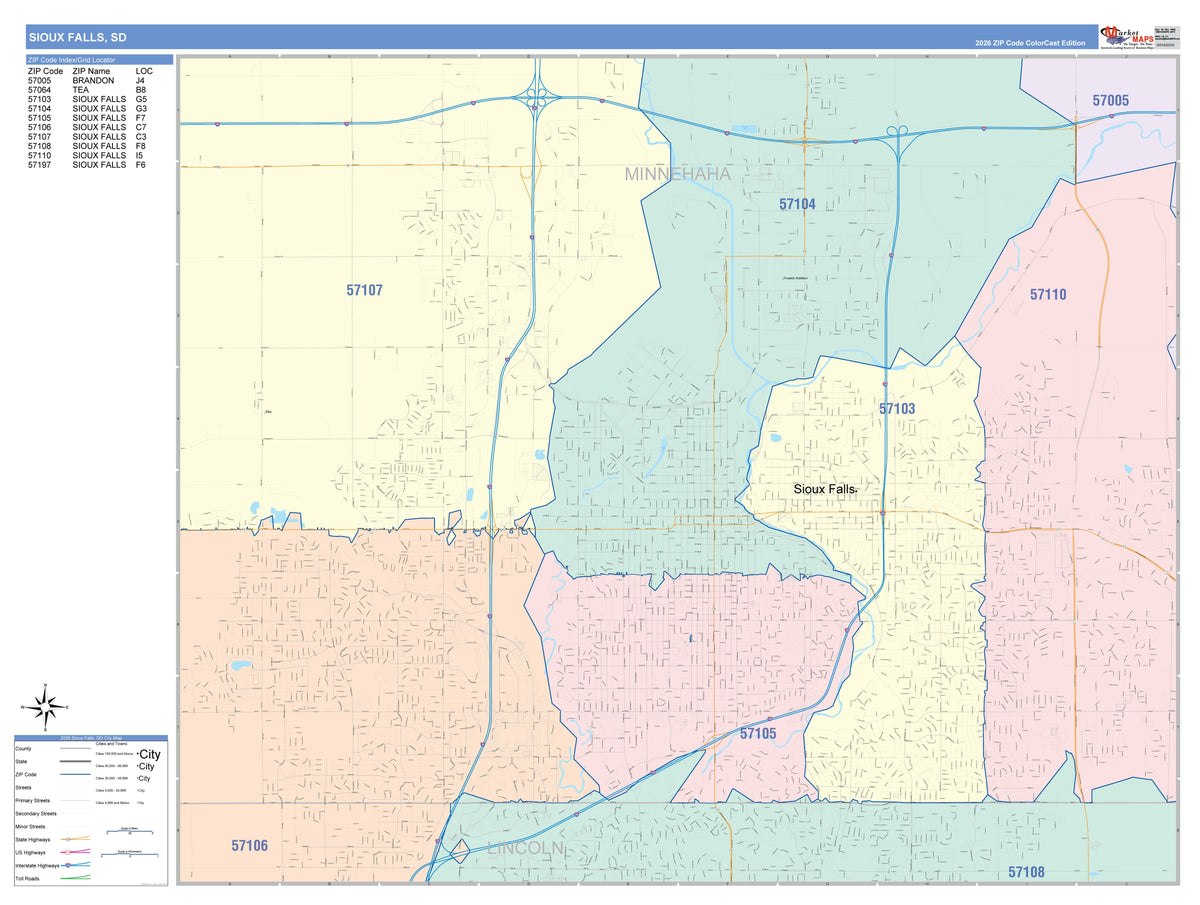
Most people think a zip code is just a mailing address label. It is not. It is a geographic key that determines provider networks, insurance reimbursement rates, public health reporting, and even which hospital system your claim gets routed to first. If you work in healthcare administration or practice management, you already know that getting this wrong creates problems fast. Sioux Falls operates across several overlapping postal zones, and each one maps differently to Medicare Advantage plans, Medicaid eligibility bands, and commercial payer contracting territories. The 57104, 57105, 57106, 57107, 57108, 57110, and 57115 zones are the main ones. They look similar on a map. They do not behave the same when claims hit the clearinghouse. I ran into this head-on last fall. A patient moved from 57106 to 57108, both technically Sioux Falls, both under the same county. Her PCP was in-network at the new address, but the claims engine kept rejecting her visits as out-of-network. The issue was not the address itself. It was that her specific building fell into a postal micro-delivery zone that the payer's GIS layer did not recognize as part of her plan's service area. We had to pull up the NPA file, manually verify the zip plus four, and then send an override request through the provider network management portal. Took three weeks to resolve. The workaround was to get the patient's office manager to confirm the exact CASS-coded address line with the postal standard suffix, then resubmit with the 9-digit zip attached to every claim for that patient going forward.
This is not theoretical. Zip code mismatches account for roughly 8 to 12 percent of initial claim denials in multi-zone metro areas, and Sioux Falls is one of those places where the mismatches cluster because the postal and payer boundaries diverge in a few specific corridors near the airport and the southern medical campus.
The Technical Mechanics You Need To Know
ZIP Code Tabulation Areas, or ZTAs, are Census Bureau constructs that approximate residential populations. Postal zip codes are mail delivery routes, which sometimes split along highway medians or rail lines. Payers use their own Service Area Polygons, which are proprietary and often lag behind real development by 12 to 18 months. When all three systems disagree, which they do around Sioux Falls, you end up with a situation where a patient's address is valid everywhere except inside the payer's contracted territory file. The fix starts with CASS certification. Every address validation tool in your workflow should be certified under the USPS Cooperative Addressing Standard Registry. Without that, you are guessing. The 9-digit ZIP code, the ZIP plus four, and the last two digits representing a specific delivery segment, are what actually matter. The five-digit only version is too coarse for payer adjudication in most modern systems. If you are managing a clinic roster, run a quarterly geocoding audit. Load your patient panel into a tool that can cross-reference addresses against the Census ZTA layer, the USPS ZIP code layer, and the top payer service area maps you have access to. Flag any discrepancies. Update your patient intake forms to explicitly ask for the full nine digits, not just the five. It takes about 30 seconds per patient and prevents weeks of downstream friction.
Get the Full Details
Pitfalls That Wreck More Than You Think
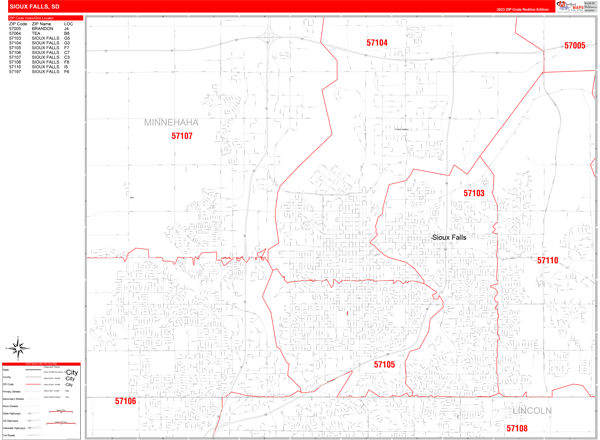
The biggest mistake I see is assuming that if two addresses share the same five-digit zip, they share the same benefit tier. That is wrong in the 57103 and 57104 ranges, where a single zip covers both urbancore commercial panels and rural-adjacent contract zones. A single payer will pay a different rate for the same procedure based on which portion of the zip the patient lives in. Another one is relying on automated patient portals to self-validate addresses. They do not always validate against the current USPS dataset. I had a case where a patient's address update in the patient portal did not propagate to the claims engine for six weeks. The portal used a cached copy. By the time we caught it, three claims had gone out with stale data. The fix was to disable portal-led address writes for insurance-eligible patients and route all updates through the front desk with a mandatory ZIP plus four verification step at check-in. There is also the issue of tribal jurisdiction overlap. Parts of the Sioux Falls metro fringe touch areas that interact with tribal health compact agreements. The zip code alone does not tell you whether the patient should route through an IHS facility first or whether a direct referral is appropriate. This comes up maybe 3 to 5 percent of the time in our patient panel, but when it happens, the billing path is completely different. You need the tribal eligibility flag in the demographic record, not just the postal code.
What Actually Moves The Needle
When you get the zip code logic right, denial rates drop, patient wait times shrink, and trust improves because people stop getting surprise explanations about why their visit was denied or why they owe more than expected. That last part matters more than the paperwork side. A patient who gets a clean, accurate explanation at check-out is a patient who returns. A patient who gets a confusing overage notice after the fact is a patient who files a complaint or leaves the practice. The workflow I recommend is straightforward. Capture the full nine-digit zip at every encounter. Validate it against the current USPS database before the claim leaves your system. Cross-check it against your top three payer service area files monthly. Maintain a manual override log for edge cases like the one I described earlier, so you can track patterns. If you start seeing a cluster of rejections tied to a specific street or development, something has shifted in the GIS mapping and you need to escalate it before it compounds. This is not a set it and forget it process. The maps change. The payer territories change. The postal routes change. But the investment pays off quickly, usually within 60 to 90 days after you implement the routine, because most of the friction in claims processing comes from address mismatches that could have been caught at the front end.
Resources If You Want To Dig Deeper
The USPS CASS certification list is public. The Census ZTA shapefiles are downloadable from data.census.gov. Most payer service area boundaries are available through your provider relations contact or through CMS data if you are dealing with Medicare Advantage. The SD Department of Health publishes zip-level coverage reports that can help you spot regional trends. Combine those and you have a working map of where the real overlaps and gaps are. Nothing about this is glamorous. It is just data entry with consequences. But the people who treat it as a chore are the ones who end up spending three weeks solving a problem that a 30second verification step would have prevented in the first place.