Silver Ions Are Just Charged Atoms, Not Magic
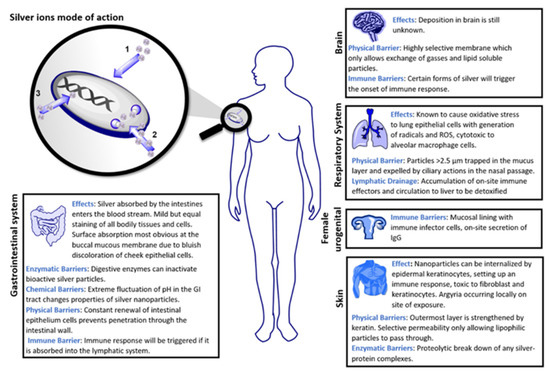
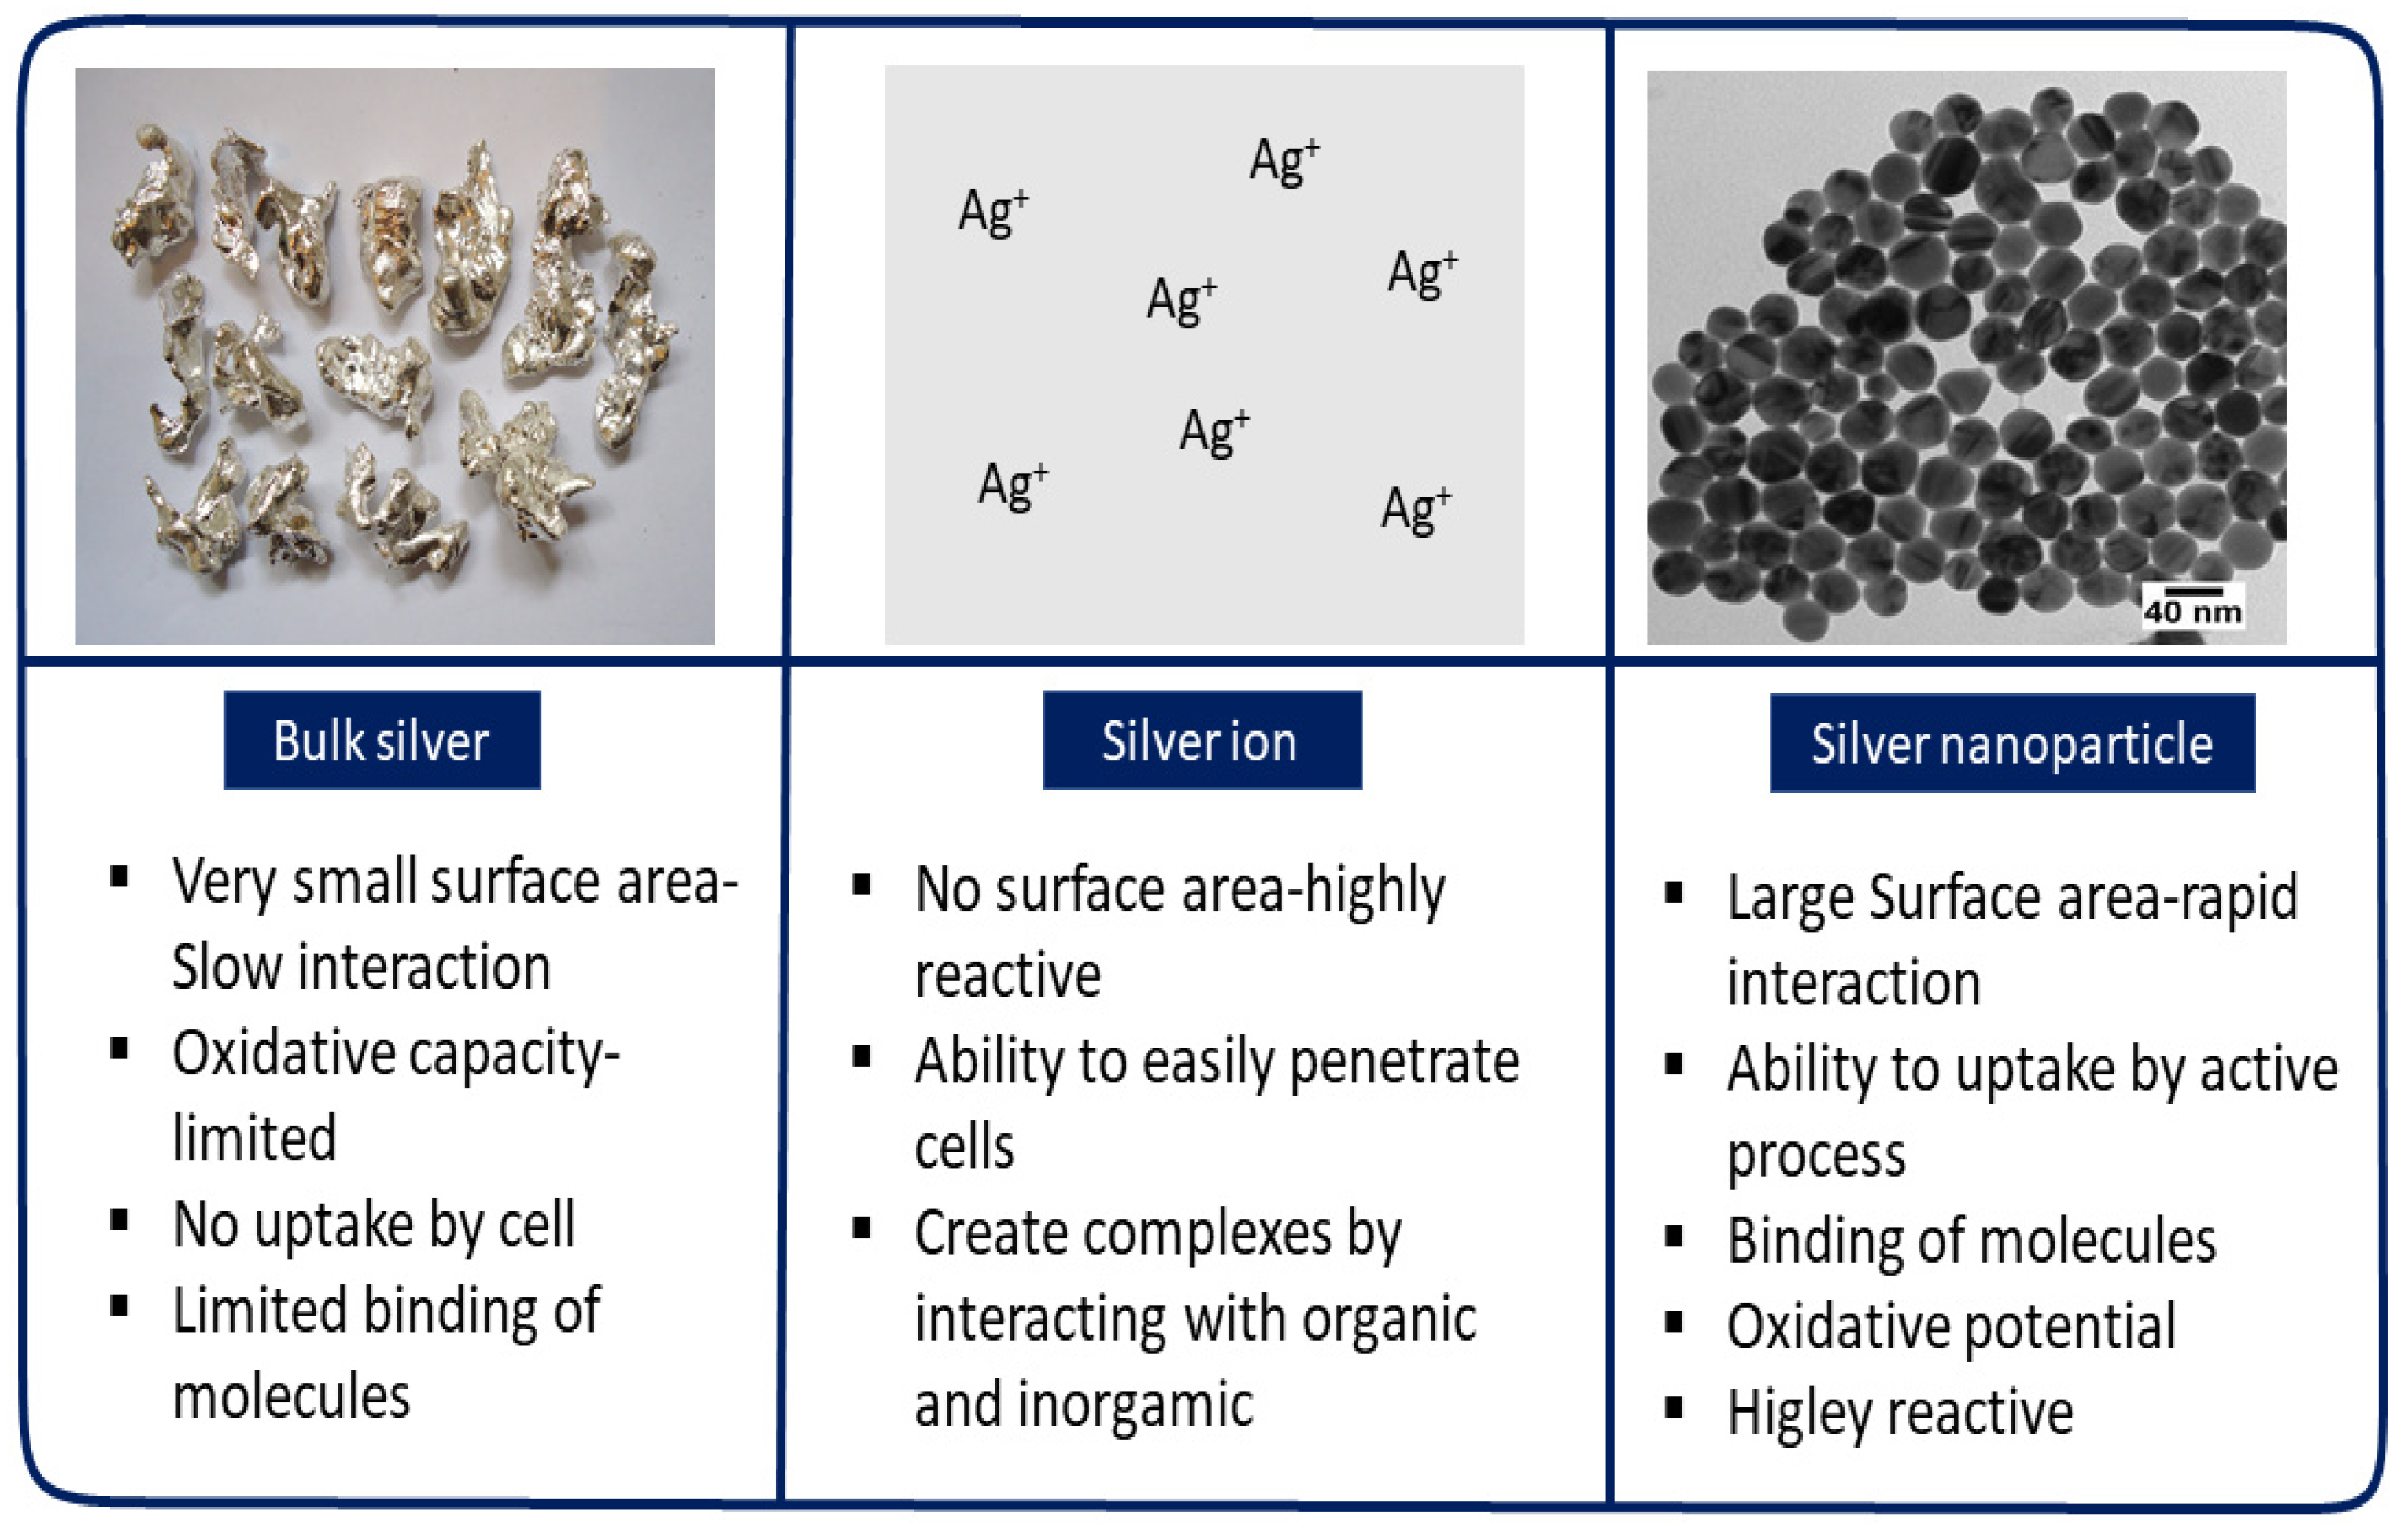
Silver carries a +1 charge when it loses one electron, becoming Ag+. That positive charge is what drives nearly everything about how it interacts with biological systems. Bacterial cell walls are loaded with negative charges from lipopolysaccharides and phospholipid head groups. The silver ion doesn't care about species classification at that level - it just moves toward the strongest negative potential it can find, sticks to it, and starts causing problems for the organism on the other side of that membrane. It's electrostatics, not chemistry in the traditional sense. The mechanism works on multiple levels simultaneously. Silver ions bind to sulfur-containing amino acids in proteins, which disrupts enzyme function. They also intercalate into DNA and RNA, preventing replication. A single silver ion can neutralize roughly 100,000 to 1,000,000 bacterial cells before it gets saturated with negative charges and becomes inactive. That's why even trace concentrations matter in practical applications. Colloidal silver, silver nitrate solutions, silver sulfadiazine cream, nanocrystalline silver dressings - they all deliver the same active species. The difference is in release kinetics and bioavailability. Silver nitrate dissolves instantly and releases a burst of free Ag+ ions that can damage healthy tissue if applied without dilution. I once mixed up a 1% silver nitrate solution thinking it was 0.5%, applied it to a second-degree burn dressing, and watched the patient's wound bed whiten and tighten within minutes. Hypersaline tissue necrosis isn't anything you want to manage on a night shift. The fix was immediate copious irrigation with normal saline for about 20 minutes, then switching to a silver sulfadiazine formulation instead, which releases ions more slowly through the sulfonamide matrix.
That slow release is the key distinction most people miss. Nanocrystalline and ionic silver dressings are designed to maintain a steady low concentration of free silver ions over 24 to 72 hours. The ions don't just disappear when they hit a bacterial membrane - they get partially recaptured by negative charges in the wound exudate and released again later. This creates a sustained antimicrobial gradient rather than a single overdose event. There's a common misconception that higher silver concentration always means better outcomes. In reality, concentrations above roughly 1% in wound dressings start showing cytotoxicity to fibroblasts and keratinocytes. I ran across a study where researchers compared 0.3% silver sulfadiazine against 1% on granulating wounds and found the lower concentration actually promoted faster epithelialization after the first week. The initial bacterial kill rate was comparable between the two, but the higher concentration slowed down the proliferative phase of healing. The data wasn't dramatic, but it was consistent enough that I adjusted my protocol accordingly. Silver resistance is another area where the literature contradicts itself. You'll find papers claiming bacteria develop resistance to silver quickly and others showing it's one of the lowest resistance profiles among antimicrobials. The truth is somewhere in between. Silver's multi-target mechanism - membrane disruption, protein binding, DNA interaction - makes it genuinely difficult for bacteria to evolve comprehensive resistance the way they do against single-target antibiotics like penicillin or ciprofloxacin. However, there are documented cases of silver-resistant strains emerging in chronic wound environments and in hospital ICUs where silver exposure is continuous rather than intermittent. These strains typically carry plasmids with silver efflux pumps, like theSilE andSilP genes found inPseudomonas aeruginosa. They're not common, but they exist, and they tend to appear in settings where silver is used as a preventive measure rather than a treatment.
Argyria deserves mention here. It's the blue-gray discoloration of skin that occurs with prolonged systemic silver exposure. Topical application to intact skin rarely causes it - the silver simply can't penetrate far enough. The cases that made headlines involved people drinking colloidal silver supplements containing variable and often unmeasured concentrations of ionic silver. When you ingest large amounts consistently, silver deposits in the dermis and binds to melanin. It's permanent. The FDA has never approved any over-the-counter colloidal silver product, and they've sent warning letters to companies making therapeutic claims. The ones that are still on the market are largely doing so because enforcement takes time and legal resources. If you're working with silver ion formulations in a clinical or laboratory setting, the practical considerations are straightforward but easy to mess up. Silver solutions degrade when exposed to light - store them in amber glass or opaque containers. Metal containers are a no-go; silver precipitates out when it contacts reactive metals, and you lose concentration over time. Aluminum foil wraps around silver nitrate vials aren't just tradition - they're functional. Plastic containers made from certain polymers can absorb silver ions through complexation, which subtly reduces effective concentration without any visible change to the solution. Silver interacts with chloride ions in physiological fluids to form silver chloride, which is poorly soluble and largely inactive as an antimicrobial. This is why wound exudate containing high chloride levels can reduce the effective concentration of free silver ions over time. In practice, this means silver dressings need periodic replacement even if the wound isn't showing signs of infection. The standard recommendation is every 24 to 48 hours depending on exudate volume, but heavily exudating wounds may require more frequent changes. I track this by measuring the dressing's absorption capacity rather than just following the clock - when the gel layer extends within two centimeters of the outer barrier, it's time to replace it regardless of how long it's been there.
Get the Full Details
The cost factor is worth acknowledging. Silver-impregnated dressings run anywhere from $15 to $60 per unit depending on the formulation and brand. In a hospital setting with insurance coverage, this is a line item. For home wound care without coverage, it adds up quickly. Plain gauze with topical antibiotic ointment costs a fraction of that and works adequately for many low-risk wounds. Silver is overkill for a simple laceration that's closed with steri-strips and healing normally. It's indicated for colonized chronic wounds, burns, surgical site infections with confirmed pathogens, and immunocompromised patients where the consequence of infection is high. I've stopped using silver prophylactically on catheter sites. The evidence doesn't support it, and it selects for resistant organisms in the surrounding skin flora. Instead, I focus on insertion technique and daily site assessment with chlorhexidine prep. That approach has better outcomes and doesn't contribute to the resistance problem. Not every antimicrobial decision should involve silver, even though it's convenient because it's available in so many forms. The chemistry is simple. The delivery is complex. The clinical application requires more judgment than the product labels suggest. Silver ions are effective because of their charge and their multi-target mechanism, but they're not a substitute for proper wound assessment, appropriate dressing selection, and recognition of when a different intervention is warranted. I've seen both excellent results and unnecessary waste from this molecule. The difference usually comes down to whether the person applying it understands what they're actually putting on the wound.