Testing is the only way to know
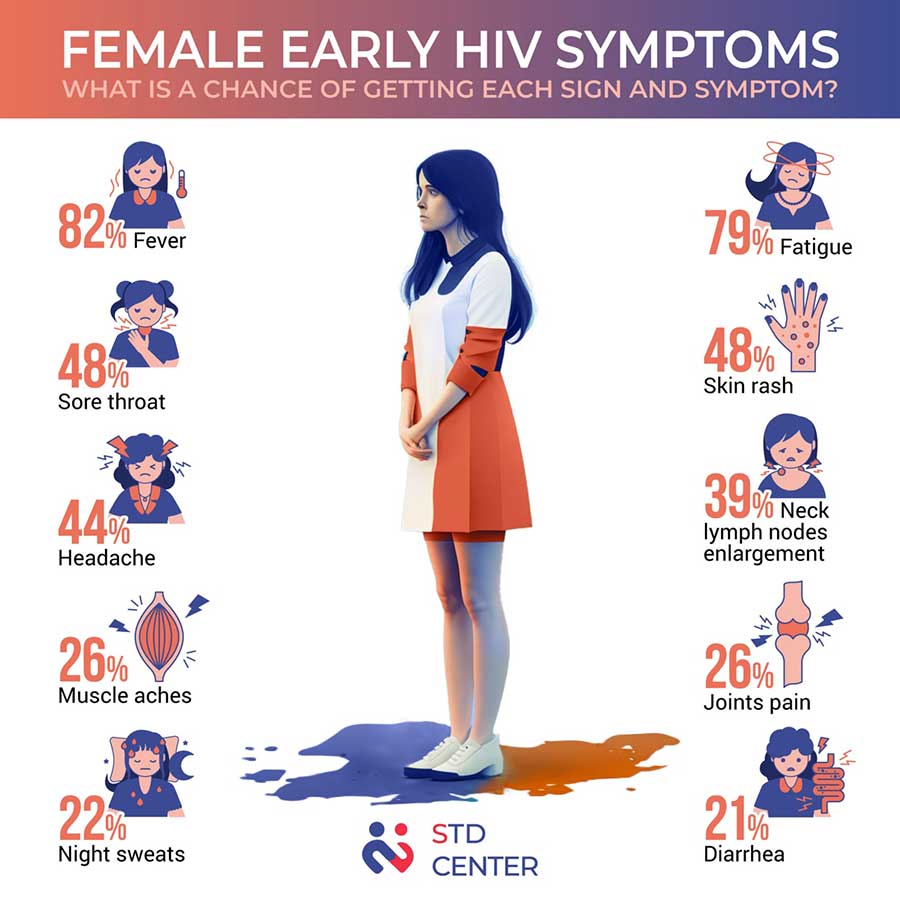
HIV doesn't care about your age, gender, or how many times you've showered. It hides. I'm going to walk you through what actually happens when you start paying attention to your body and when to get tested, because most people wait until there's nothing left to do but panic at an urgent care clinic. Acute retroviral syndrome is what happens about two to four weeks after exposure. You get a fever, swollen lymph nodes, sore throat, maybe a rash on your torso. It feels like a bad case of mono or the flu. I've seen patients blow it off as stress for three weeks straight while their viral load skyrocketed into the millions. That window period is the problem. Standard antibody tests won't catch it yet because your body hasn't made enough antibodies to detect. You need a fourth-generation antigen/antibody combo test or an RNA PCR test during that acute phase. The antigen (p24) shows up before antibodies do. If you're in that two-to-four week window and you've had a high-risk exposure, tell the lab or doctor upfront. Don't assume a negative comes back clean. After acute infection, the virus settles into clinical latency. This is the part that gets people killed. You feel fine. You look fine. You might have zero symptoms for years while HIV quietly destroys your CD4 count. I worked with a guy in his mid-twenties who walked into a clinic with Pneumocystis pneumonia. His CD4 was 42. He'd been "feeling fine" for three years. That's how long untreated HIV can masquerade as nothing before it turns into AIDS-defining illness. The asymptomatic phase isn't a health phase. It's a slow bleed.
The real-world signs to watch for aren't dramatic. They're the ones you dismiss because they're mundane. Unexplained weight loss. Night sweats that soak through sheets. Persistent diarrhea lasting more than a week. Fatigue that doesn't improve with sleep. Recurrent yeast infections in men and women. Thrush that won't go away. Swollen lymph nodes in multiple areas — neck, armpits, groin — that don't resolve. Kaposi's sarcoma lesions, though those usually appear later when the immune system is already compromised. If you're having sex without consistent barrier protection or if you share needles, these symptoms plus a lack of recent testing equals you should be getting tested now, not "soon." There's a common misconception that rapid tests are always accurate. They're not. A rapid oral fluid test has a higher false negative rate than a blood draw, especially during early infection. The oral test detects antibodies, not antigens. If you get a negative from a rapid test at three weeks post-exposure, it doesn't mean you're clear. It means the test couldn't detect it yet. Retest at six weeks with a fourth-generation lab test, then again at three months for conclusive results. That's the standard protocol. Deviating from it is how people miss their diagnosis. Pre-exposure prophylaxis, PrEP, is available through most sexual health clinics and primary care providers. Truvada and Descovy are the main options. Taken daily, they reduce the risk of getting HIV from sex by about 99 percent. If you're sexually active with multiple partners or your partner has an unknown status, this isn't optional advice. It's basic harm reduction. I've lost count of the patients who told me they were "monogamous" right before walking in with a new diagnosis. Monogamy doesn't equal safety unless both people have been tested recently and simultaneously. One person's negative result from six months ago tells you nothing about their status today.
Post-exposure prophylaxis, PEP, is different. It's an emergency medication you start within 72 hours of a potential exposure — a condom break, a needle stick, sexual assault. It's a 28-day course of antiretroviral drugs that can prevent the virus from establishing itself. It's not a morning-after pill. It's not 100 percent effective, and it has significant side effects including nausea, fatigue, and headache. But it works when you use it correctly and in time. I once had a patient who waited five days because he was embarrassed to go to the ER. By day five, PEP was no longer an option. He seroconverted three weeks later. Don't wait. Don't be embarrassed. Go. Undetectable equals untransmittable. This isn't a slogan. It's a scientific fact backed by multiple large-scale studies. If you're on treatment and your viral load is undetectable — meaning less than 200 copies per milliliter — you cannot sexually transmit HIV to a partner. U=U is real. But "undetectable" requires consistent medication adherence and regular monitoring. Missing doses can cause the viral load to rebound. If you're diagnosed, starting antiretroviral therapy immediately is critical. Delaying treatment gives the virus more time to damage your immune system. Modern ART regimens are one pill a day with minimal side effects compared to what we had ten years ago. The goal is suppression, not cure, but suppression means a normal lifespan and normal sexual health. Testing frequency depends on your risk level. If you're in a mutually monogamous relationship and both partners have tested negative within the past six months, annual testing is reasonable. If you have new or multiple partners, test every three to six months. If you inject drugs, test after every exposure event. Sexual assault victims need immediate testing and PEP consideration. There's no universal rule that fits everyone. Map it to your actual behavior, not your aspirations.
Get the Full Details

Free and low-cost testing is available through community health centers, Planned Parenthood locations, and local health departments. The CDC recommends at least one test for everyone between 13 and 64 as part of routine care. Most places don't charge. You don't need insurance. You don't need an appointment at many sites. Some offer walk-in testing with results in 20 minutes. Use them. Stigma around testing is the single biggest barrier to early detection, and it's entirely self-imposed. The staff at these clinics have seen everything. They don't judge. They just want you to know your status so you can act on it. I ran into an edge case recently that highlights how easy it's to miss something. A patient came in with chronic fatigue and mild lymphadenopathy. She'd tested negative three times over eight months using rapid finger-prick tests at various clinics. Her symptoms persisted. I ordered a fourth-generation lab test and an HIV RNA PCR. The antigen/antibody test was indeterminate, and the RNA test came back positive at 89,000 copies per milliliter. She'd been infected for months, possibly over a year. The rapid tests kept missing it because her antibody response was atypical — her body was producing them slowly. This is rare but documented. If you have ongoing symptoms and repeatedly negative rapid tests, push for a lab-based fourth-generation test or PCR. Don't accept the repeated negatives at face value. The bottom line is straightforward. HIV is treatable. It's not the death sentence it was in the 1980s. But treatment works best when you start early. The longer you wait, the more damage accrues, and the harder it becomes to recover immune function. Get tested. Know your status. Use PrEP if you're at risk. Use PEP if you're exposed. And if you're positive, get on treatment immediately and stay on it. Your health, and the health of your partners, depends on it.