How To Decide Whether Your Symptom Needs An ER Visit Without Losing Your Mind
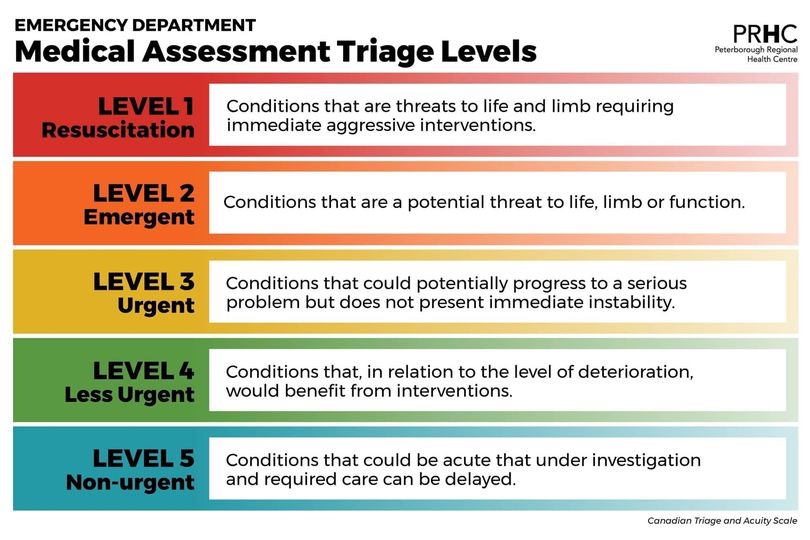
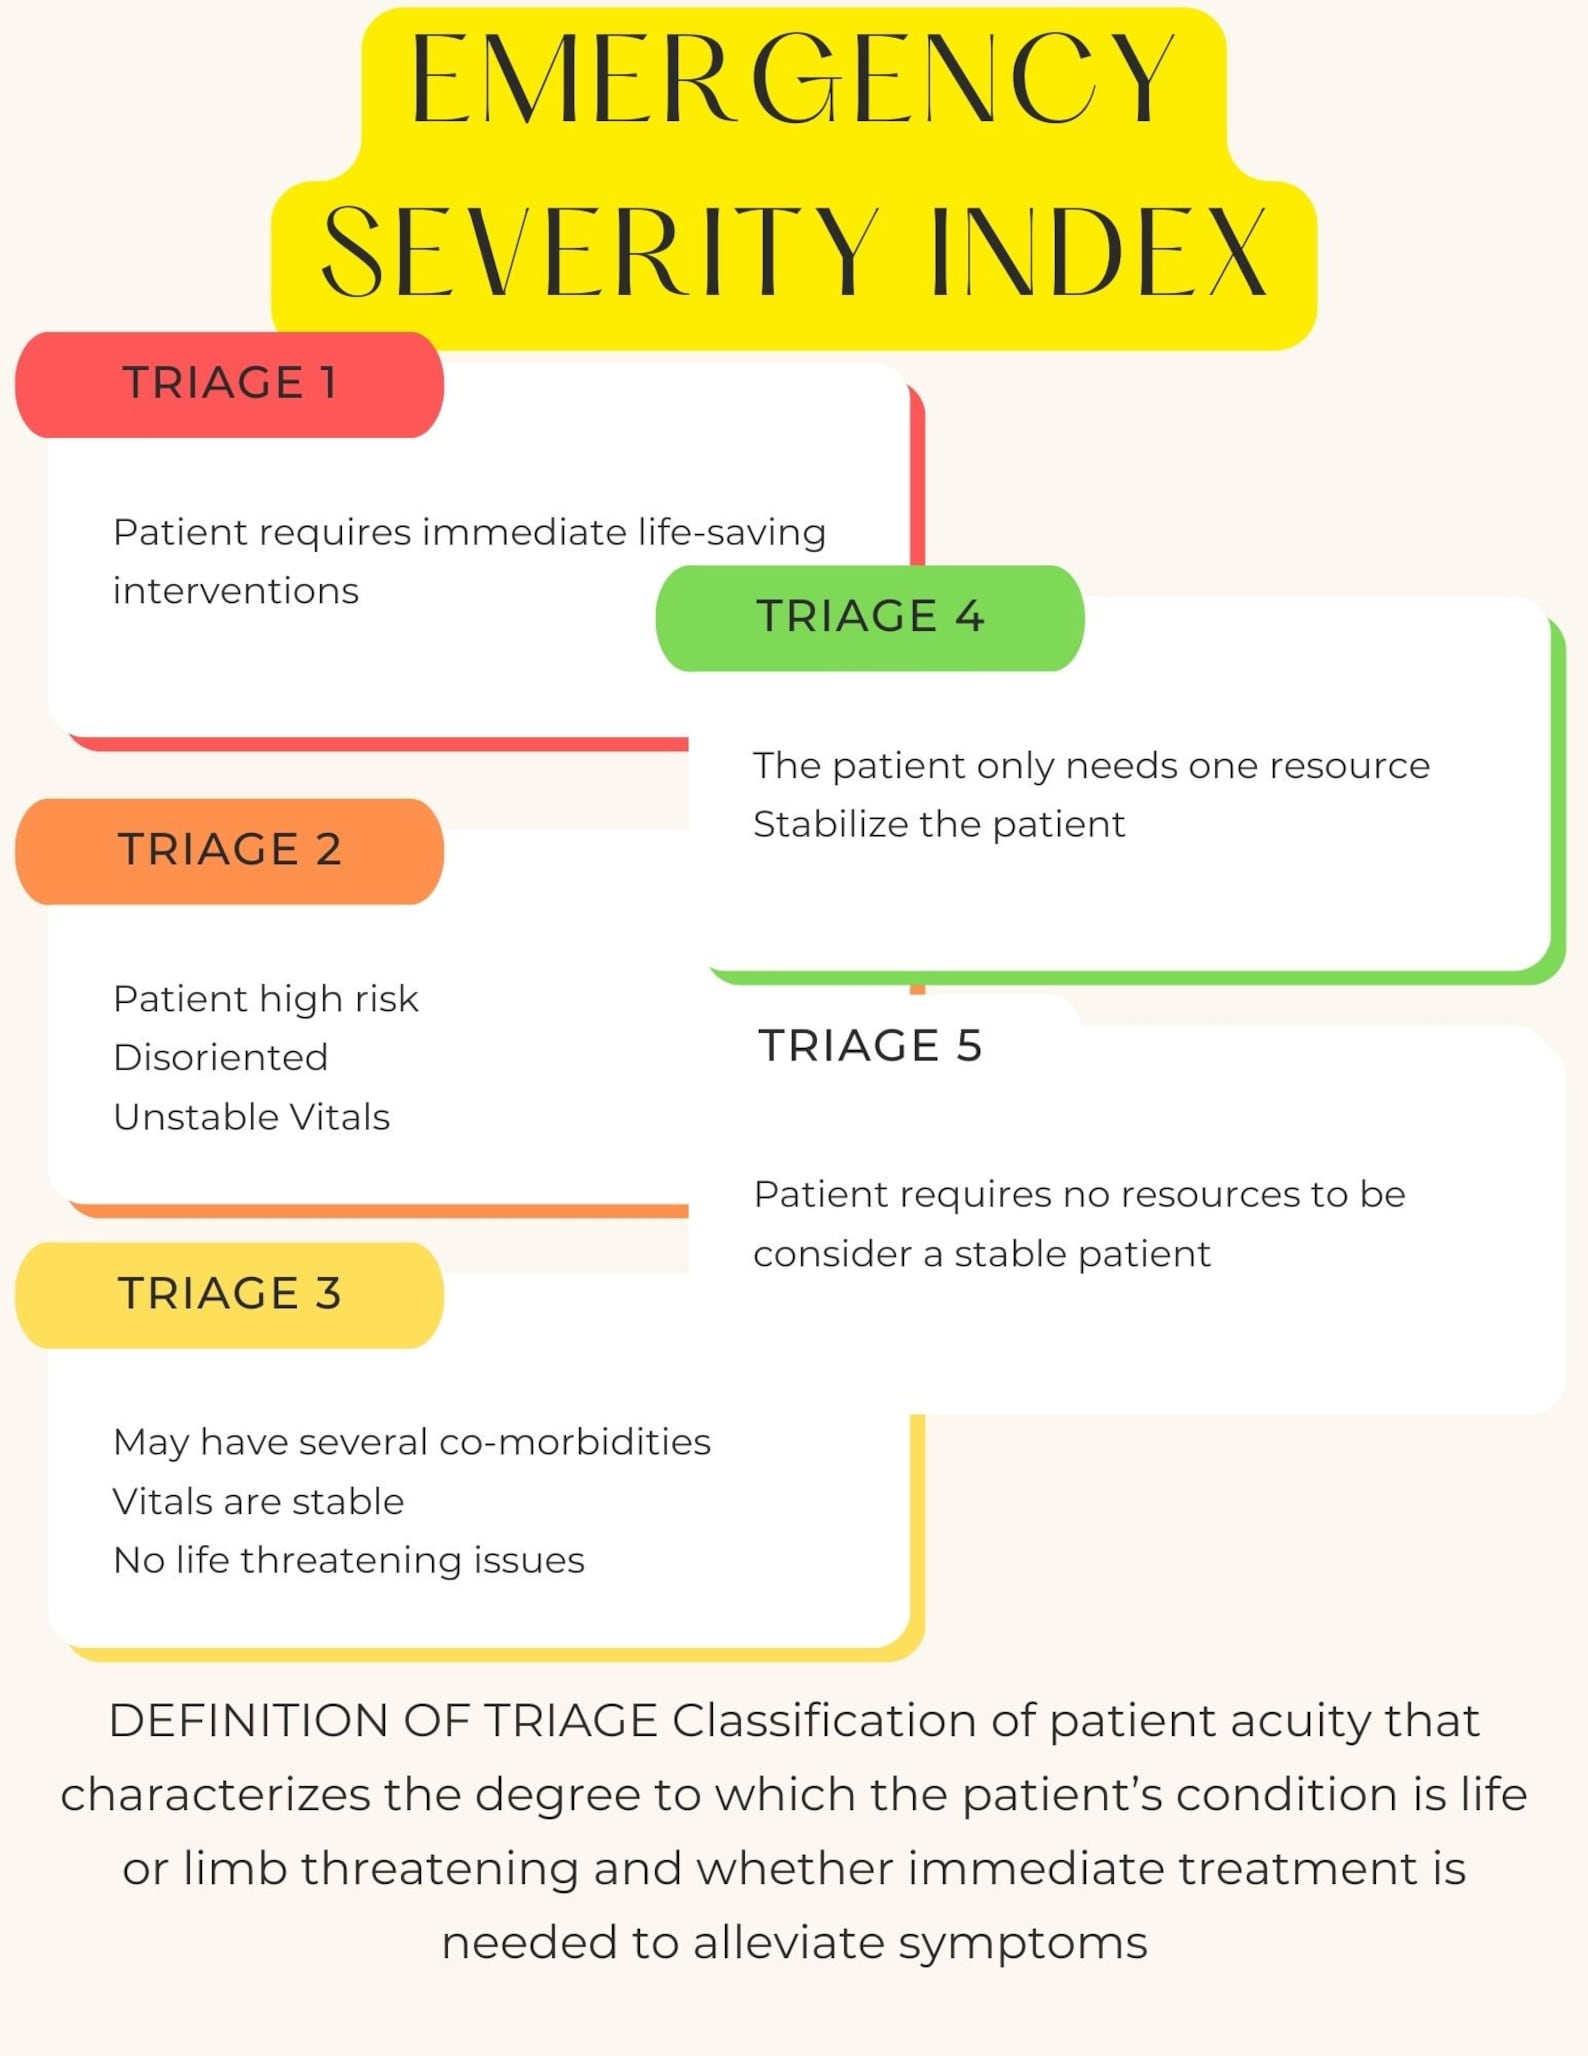
Most people overestimate what warrants an emergency room visit. I spent years working in urgent care and ER triage, and the most common pattern I saw was patients showing up for things that would have resolved with a few days of rest, OTC meds, and a telehealth call. Not saying those visits are pointless, but understanding how triage actually works can save you hours of waiting room time and several hundred dollars in co-pays. The ER does not operate on a first-come, first-served basis. It runs on acuity. A patient with chest pain will be seen before someone with a sprained ankle, regardless of who arrived first. This is the opposite of what most people expect, and it means showing up with a lower-acuity complaint can mean sitting in a chair for four to six hours while critical cases are managed around you.
Should I Go To The Er Quiz A Stepbystep Guide To Triage Decisions At Home
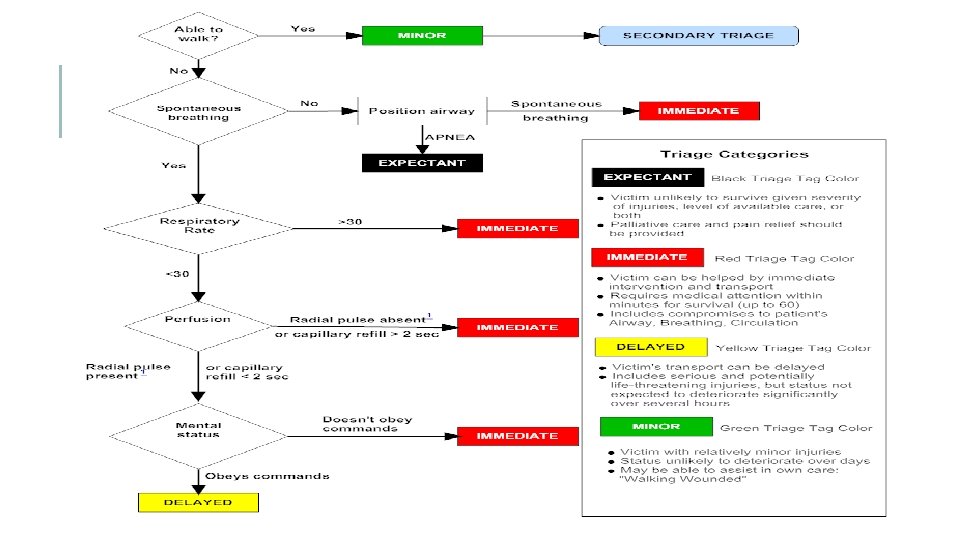
Here is the framework I used to build my own decision tool, and the one that actually makes sense from a clinical triage perspective. The steps follow the same logic that emergency nurses use when they first assess a patient. Step one: Check for immediate life threats. Chest pain that radiates to the arm or jaw. Sudden severe headache described as the worst of your life. Difficulty breathing or inability to speak in full sentences. Uncontrolled bleeding. Sudden weakness or numbness on one side. Confusion or difficulty staying awake. These are not wait-and-see situations. Call 911 or go directly to the nearest ER. Do not drive yourself if any of these apply. Step two: Assess severity using the ABCs. Airway, breathing, circulation. Is your airway clear? Can you breathe comfortably at rest? Are you bleeding in a way that a direct pressure dressing would control? If the answer to any of these is no, you need emergency care now. If yes, move to the next step.
Step three: Evaluate time sensitivity. Some conditions have a narrow treatment window. Stroke symptoms within the last four and a half hours. A suspected broken bone with the skin broken and bone visible. Severe abdominal pain that started suddenly and is worsening. These time-sensitive issues still require the ER, but the urgency threshold is different from something like a mild fever that has been present for two days. Step four: Consider what you have already tried. This is where most at-home triage decisions break down. If you have taken appropriate over-the-counter medication at the correct dosage for at least 24 to 48 hours and symptoms are not improving or are getting worse, that is a signal. Not necessarily an ER signal, but a signal that you need medical evaluation sooner rather than later. An urgent care clinic is usually the right call at this stage. Step five: Factor in your baseline health. A fever of 103 in an otherwise healthy 25-year-old is very different from a fever of 101 in a 68-year-old on immunosuppressants. Comorbidities change the risk calculation significantly. Diabetes, heart disease, chronic lung conditions, chemotherapy, organ transplants, pregnancy, and being under two or over 65 all shift the threshold for seeking emergency care downward. I have seen otherwise minor infections become serious complications in these populations within 24 hours.
Get the Full Details
There is a specific edge case that kept coming up when I first built this into a quiz format. People with anxiety disorders. Health anxiety can make any symptom feel catastrophic, and the ER becomes a temporary relief valve rather than a medical necessity. I had a patient once who came in with what she insisted was a heart attack. Three sets of troponin tests and an EKG showed nothing wrong. She had a panic disorder and had not eaten in two days. The ER stabilized her medically, but the underlying issue required a different kind of treatment entirely. This is not to dismiss health anxiety as fake, but it is worth acknowledging that anxiety can distort risk perception and lead to unnecessary ER visits that drain resources everyone needs.
The Parts Of Triaging At Home That Nobody Talks About
Most online checklists focus on symptoms. They tell you what to look for but not how to weigh it against the realities of the healthcare system. Here are a few things that matter more than any symptom checker app. Pain scale is unreliable. A 9 out of 10 pain from kidney stones is not the same clinical scenario as a 9 out of 10 pain from a migraine. One is extremely uncomfortable but rarely life-threatening. The other could indicate a ruptured aneurysm. Numbers alone do not tell the full story. Describe the character of the pain, where it started, how it moves, and what makes it better or worse. That narrative is far more useful to a triage nurse than a single number. Duration matters more than intensity in many cases. A mild headache that has been present for three weeks is more concerning than a thunderclap headache that resolved after an hour. The first could be a growing intracranial issue. The second, while dramatic, may have been a benign occurrence. Track how long symptoms persist before deciding on the ER.
Progression direction is critical. Is the symptom getting better, worse, or staying the same? A cold that starts mild and progresses to shortness of breath over 48 hours needs evaluation. A cold that peaks on day three and gradually improves does not. Direction of travel through time is one of the most underutilized data points in self-triage. I ran into a real problem when I was putting together a practical home triage quiz. The biggest gap was that most people do not know their own normal vital signs. A heart rate of 110 might terrify someone whose resting rate is 60, while someone whose resting rate is typically 95 might not take it seriously. The workaround I settled on was building in baseline questions: what is your usual blood pressure, resting heart rate, and temperature. Compare current symptoms to your personal baseline, not to some generic textbook average. This cut down false positives significantly in early testing.

Where This Approach Falls Short
Any at-home triage tool has hard limits. It cannot run blood work. It cannot listen to your lungs with a stethoscope. It cannot order a CT scan. If you are on the fence, the safest default is always to seek professional evaluation rather than on a checklist. The tool is designed to help you sort between ER, urgent care, and watchful waiting. It is not a substitute for medical judgment, and pretending it is dangerous. There is also a socioeconomic angle that most guides ignore entirely. In some regions, the ER is the only access point for people without a primary care physician. Going to the ER for a non-emergency might be the rational choice if there is no alternative provider within a reasonable distance. This does not make it ideal, but it makes it a practical reality for millions of people. Any triage guide that assumes universal access to urgent care or telehealth is writing fantasy, not utility. If you find yourself repeatedly using the ER for non-emergent issues because you lack other options, the more sustainable solution is finding a community health clinic or a low-cost telehealth service. These options exist in most areas and cost a fraction of an ER visit. The ER should be your last resort, not your default, even when the system makes it feel like the only path forward.