What You Actually Need to Know About Limb Anatomy Beyond the Headlines
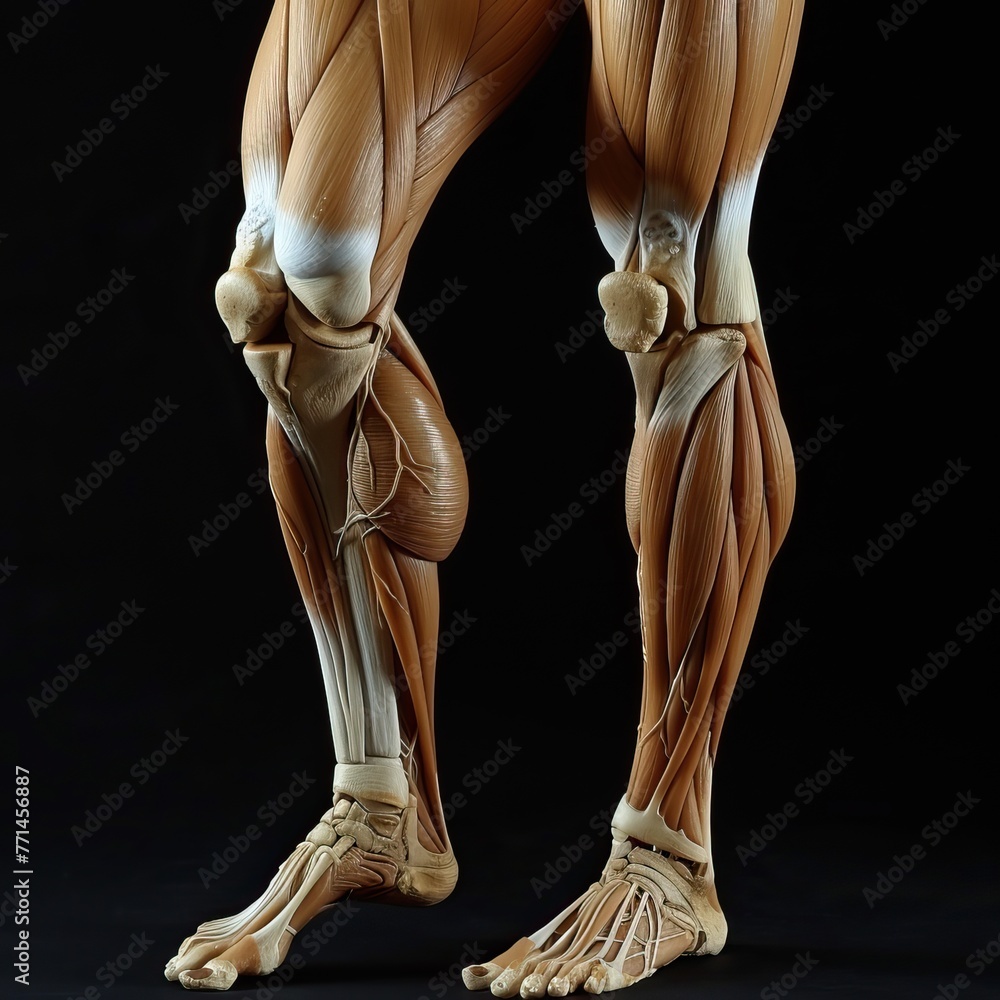
Most people walking through medical literature or watching those viral "shocking" videos have no idea what they are actually looking at. The human arm and leg are not simple mechanical levers strapped to a torso. They are layered, redundant systems where bones, muscles, nerves, and blood vessels run alongside each other in tight corridors that leave almost no room for error. When someone posts something under the Shocking Truth The Anatomy Of Human Limbs Exposed banner, it is usually stripping away clinical detail and presenting only the ugliest or most dramatic cuts. That is engaging content. It is also deeply misleading. I spent years working with anatomical models, dissection guides, and then later in rehab facilities where people came in with nerve damage they did not understand. The gap between textbook diagrams and real human tissue is enormous. Textbooks show clean planes of separation. Real tissue bleeds, sticks, tears unpredictably, and every person has slightly different branching patterns for their nerves and arteries. That variability is the part nobody puts in a thumbnail.
The Shocking Truth The Anatomy Of Human Limbs Exposed Is Mostly About Selection Bias
Here is how those graphic anatomical images actually get made. A photographer or illustrator chooses one cross section, one angle, one stain, and one specimen. They do not show you the three other layers above and below it. They do not show you that the median nerve you are admiring in that picture sits directly against the pronator teres muscle in this person, but in roughly four percent of the population it passes through a different slip of that same muscle and is far more vulnerable to entrapment there. That matters when someone is trying to figure out why their forearm hurts after repetitive work. When I was training with cadaver specimens, the first thing I learned was that color does not mean what you think it means. Red does not always equal artery. In preserved tissue, veins can look dark and thick while arteries collapse into white tubes unless they are specifically opened and pinned. Nerves look like pale yellow cords bundled in fascicles. Fascia looks like shiny plastic wrap if you keep it moist. Everything looks more dramatic than it actually is because formalin fixation and even fresh tissue contrast heavily against whatever background the demonstrator chooses. The brachial plexus in the arm is the classic example of this. People see a picture of it and assume it is a neat tree branching outward. In practice, the cords and divisions are arranged around the axillary artery in a way that shifts depending on arm position. I had a case where a patient had posterior cord compression from a heavy backpack strap, and the standard nerve conduction studies were borderline normal because the compression was positional. Ultrasound showed the cord flattened against the humeral head when the arm was adducted. A static diagram would never catch that. You have to move the limb and watch the nerve glide.
The lower limb is even less intuitive. The femoral triangle is taught as a clean landmark area, but in obese patients the fascia lata can be several centimeters thick and the pulse you are palpating might be the profunda femoris rather than the femoral artery itself. I once watched a fairly confident student miss a puncture on a simulation model because he was aiming for a landmark that had shifted due to fat distribution. He hit the adductor canal instead, which is a totally different space with different structures nearby.
Get the Full Details

How to Actually Read Limb Anatomy Without Getting Lost
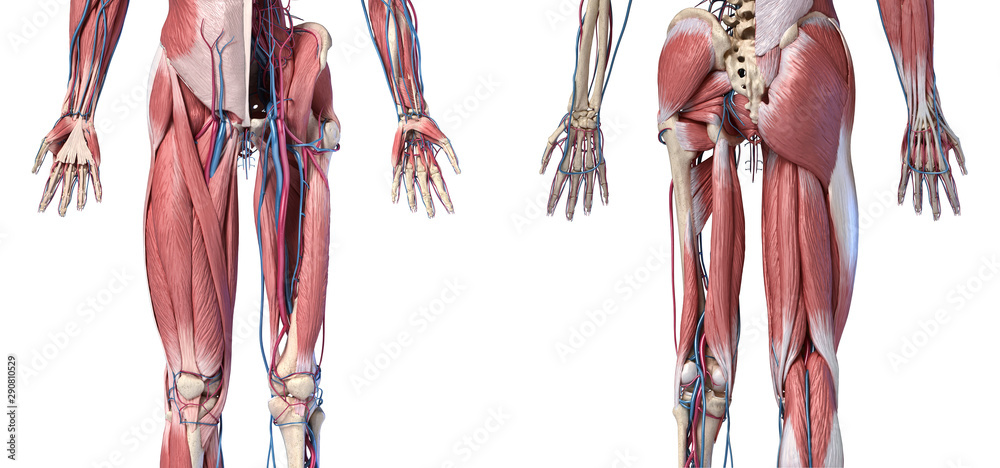
The most useful approach is to stop trying to memorize everything at once and instead learn in functional layers. Start with bone. If you can close your eyes and trace the humerus, radius, ulna, femur, tibia, and fibula and know where the palpable landmarks are, everything else builds on that. Then add muscle groups by function, not by individual origin and insertion points. Then layer in the neurovascular bundles and notice where they travel in relation to the joints they cross. When studying a cross section, always ask yourself what plane this is cut in and what is just above and below it. A transverse slice through the mid arm shows the brachial artery and median nerve sitting together anterior to the humerus, medial to the radial nerve. That changes completely a few centimeters up or down. The radial nerve wraps around the humeral shaft in the spiral groove, which is why mid shaft fractures commonly injure it. A static image does not convey that risk unless you understand the spatial relationship. One practical technique that works better than flashcards is to use ultrasound on yourself or a willing partner. The limbs are superficial enough that a decent machine with a high frequency linear probe will show you the nerves as honeycomb structures, the arteries pulsing, the muscles contracting in real time. It takes practice, maybe two to three weeks of daily ten minute scans, but after that the diagrams start making sense because you have seen them alive. I found that scanning my own brachial plexus region and then comparing it to an atlas reduced my confusion far more than any passive review.
Another useful habit is learning the common variant patterns. The median nerve and ulnar nerve variations in the forearm are frequent enough that every clinician encounters them. The Martin Gruber anastomosis, where fibers cross from the median to the ulnar nerve in the forearm, shows up in roughly fifteen to twenty percent of limbs. If you do not know it exists, you can misread an EMG study or blame the wrong structure for a patient's symptoms.
Where the Visual Media Gets It Wrong and What to Do Instead
Those viral anatomical exposes tend to use high contrast staining and dramatic lighting. They will show a limb sliced open with everything pulled apart to fill the frame. What they omit is scale. A nerve that looks massive in a photo is often thinner than a pencil in reality. Blood vessels that appear thick and dominant are usually compressible and collapse when pressure is applied. The sheer number of small vessels and connective tissue septa is always reduced for clarity. I ran into this exact problem when a colleague wanted to use one of those viral images to explain compartment syndrome to a patient. The image made all four anterior compartment muscles look separate and defined. In reality, the deep and superficial layers are close together and the septa are thin. The patient left thinking the condition was some kind of muscle separation rather than pressure buildup. We switched to a simpler diagram and had him palpate his own tight compartment while I described the pressure dynamics. That worked in about five minutes where the image failed completely. If you want accurate visual references, use anatomy atlases that show layered dissections in sequence rather than single exploded views. Netter is fine for basics, but Somers and Anson or the Clinically Oriented Anatomy by Moore give you the variation data and the clinical correlations that matter. For interactive study, apps that let you peel away layers digitally and rotate the limb in three dimensions are far closer to real understanding than any static photo.

There is also a limit to how much you can learn from images alone. Palpation and movement change everything. Try pressing on your own antecubital fossa while someone slowly flexes and extends your elbow. Watch how the biceps tendon moves, how the brachial artery pulses differently at different angles, how the median nerve sits just deep to the bicipital aponeurosis. That tactile feedback anchors the visual information in a way that reading never does.
The Counter Intuitive Stuff Nobody Puts in Flashcards
One thing that surprises people is how much redundancy exists in the limb vasculature and innervation. The arm has the brachial artery as the main trunk, but the profunda brachii, radial recurrent, and ulnar recurrent arteries create collaterals around the elbow that can sustain the hand even if the brachial artery is ligated proximal to them. The same is true for the leg with the genicular anastomosis around the knee. This is why isolated arterial injuries in the limbs do not always cause immediate ischemia, and why relying on a single pulse check can miss a significant injury. Another overlooked point is fascial compartments. The forearm has deep and superficial layers separated by the interosseous membrane and fascia. The leg has four distinct compartments with almost no room for expansion. Swelling in the leg compartment does not drain the way swelling in the arm does. This structural difference explains why compartment syndrome is far more common and far more dangerous in the lower leg than in the forearm, even though both can develop it. Nerve gliding is another concept that is almost never shown in those dramatic cross sections. Nerves are not rigid cables. They move with the limb. The sciatic nerve can shift several millimeters during hip flexion and extension. If you immobilize a limb in a position that tensions a nerve for too long, you can cause neuropa thy even without direct trauma. I saw this happen in a post surgical patient who was kept in prolonged knee extension with the hip flexed, putting the peroneal division of the sciatic nerve on stretch. The deficit took months to recover.
What You Should Actually Take Away From Graphic Limb Exposés
Those viral anatomy pieces are entertaining, but they are not educational unless you know how to read past the gore. The human limb is a compact arrangement of structures that have co evolved to fit inside limited space while maintaining redundancy, mobility, and protection. Every nerve runs near a vessel. Every muscle crosses at least one joint. Fascia binds things together but also creates potential spaces where fluid can accumulate and cause real problems. If you are studying this for health reasons, sports performance, or just genuine curiosity, focus on functional relationships rather than isolated facts. Learn what moves what, what runs next to what, and what happens when one structure gets compressed or injured. The rest will fill in. A well annotated atlas, some hands on palpation practice, and a willingness to accept that every person is slightly different will serve you far better than any single dramatic photograph.