What Munchausen Syndrome by Proxy Actually Looks Like in Practice
Munchausen Syndrome by Proxy is a psychiatric condition where a caregiver fabricates or induces illness in someone under their care. Most people know it from the Dee Dee Blanchard case, but the clinical reality is far more systematic than true crime summaries suggest. I spent years reviewing pediatric case files before I understood how the mechanism actually works day to day. The abuse isn't random. It follows a pattern that professionals call the "medical marathon" — repeated hospital visits, endless testing, treatments that don't produce lasting improvement because the underlying problem doesn't exist. The caregiver becomes the patient's permanent advocate, which makes it nearly impossible for medical staff to question the narrative without appearing dismissive of a concerned parent.
Shocking Truth Behind Dee Dee Blanchards Abuse Uncovering The Dark Reality Of Munchausen Syndrome By Proxy
Dee Dee Blanchard's case is the most documented example, but it's not the only one. Gypsy Rose Blanchard was made to believe she had leukemia, muscular dystrophy, and hearing loss when she actually had none of those conditions. Dee Dee subjected her to unnecessary medical procedures, medications, and devices including feeding tubes and wheelchairs. The shock value isn't just in the deception itself — it's in how effectively the system validated it. Hospitals and doctors repeatedly confirmed the fabrication because Dee Dee knew how to present symptoms convincingly. She maintained detailed medical records, used correct terminology, and played the role of a devoted mother flawlessly. That's the critical detail people miss: the abuser understands medical systems better than most healthcare providers expect them to.
How to Recognize It When You're Working With Families
I've seen this play out in clinic settings where the red flags were staring everyone in the face. Here's what actually matters for identification. The primary caregiver is always present and always has answers. This person knows the child's medical history better than any attending physician. They bring binders full of records. They speak in medical language that sounds authoritative. When a doctor suggests stopping a treatment, they push back with emotional appeals about their child's suffering. This behavior looks like dedication. It's actually control. Symptoms only appear when the caregiver is watching. Seizures during appointments but not at home. Rashes that vanish after leaving the clinic. Breathing problems that disappear when the parent steps outside the room. Documented episodes often contradict themselves across different settings.
Get the Full Details
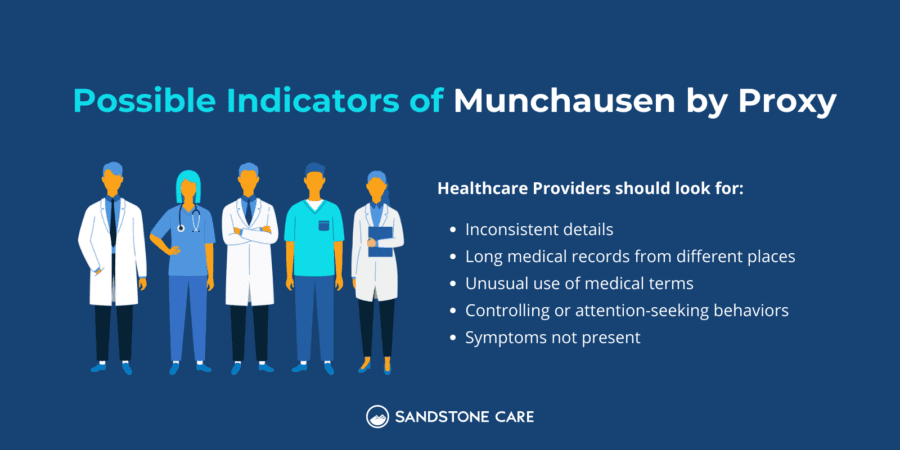
The child improves dramatically when separated from the caregiver. This is the single most reliable diagnostic indicator. Once removed from the situation, previously "incurable" conditions resolve within days. Children who were dependent on oxygen, feeding tubes, or seizure medication start functioning normally without those interventions. Multiple caregivers report the same behaviors independently. When teachers, daycare workers, or extended family members notice symptoms that don't match what the primary caregiver reports, that discrepancy warrants investigation.
What Most People Miss About the Diagnosis
MSBP is notoriously difficult to diagnose even for experienced clinicians. The condition was only added to the DSM-5 as a condition requiring further study in 2013. Before that, it existed in a diagnostic gray area. That institutional uncertainty is part of why abuse continues unchecked for years. One counter-intuitive point: the caregiver rarely seeks attention for themselves in an obvious way. They're not performing for nurses at the station. Their audience is the medical system itself. Getting the child diagnosed, tested, and treated is the actual goal. The validation comes from medical authority confirming the severity of the fabricated illness. Another thing beginners miss: MSBP doesn't only affect young children. I encountered a case where an adult daughter was being manipulated by her elderly mother into believing she had chronic conditions. The power dynamic was different but the mechanism was identical. Age doesn't matter. The perpetrator exploits dependency relationships.
The Workaround I Learned the Hard Way
Early in my career, I made the mistake of confronting a suspected abuser directly. That backfired immediately. The caregiver produced emergency contacts, printed medical literature, and threatened to file a complaint. Nothing came of the investigation. The approach that actually works involves documentation and separation without accusation. Instead of challenging the caregiver's claims, you request independent verification from multiple sources. Pull records from every school, every previous doctor, every pharmacy. Look for inconsistencies between reported symptoms and actual medication fills. Check whether prescribed treatments were ever dispensed. The most effective tool I found was scheduling unannounced home visits through child protective services. When the child is observed in their natural environment without the caregiver performing, the picture changes completely. In one case, a child described as unable to walk walked to the refrigerator during a routine safety check. The caregiver's explanation fell apart within minutes.

Where This Approach Breaks Down
Not every suspicious case is MSBP. Some children genuinely have complex, multi-system conditions that resist diagnosis. Over-interpreting red flags can lead to wrongful investigations that harm real patients and traumatize families who are already suffering. The line between diligent screening and paranoid misdirection is thin. Additionally, the evidence required for legal intervention is high. A caregiver can deny everything and claim medical misunderstanding rather than intentional fabrication. Courts are reluctant to remove children based on suspicion alone. Most interventions happen through civil custody proceedings rather than criminal charges, and those outcomes vary wildly by jurisdiction. If you're dealing with a situation where MSBP is suspected but not proven, the best path forward is consulting with a pediatric forensic specialist before taking any public action. They can help you distinguish between genuine diagnostic uncertainty and manufactured illness without triggering the kind of defensiveness that destroys evidence.
The deeper problem is that MSBP exists in a legal and medical vacuum. Many states don't have specific statutes criminalizing it. Prosecutors often charge caregivers with assault or neglect using generic laws, which carries weaker penalties than the severity of the abuse warrants. Without dedicated legislation, accountability remains inconsistent.