Classifying deaths is harder than it looks
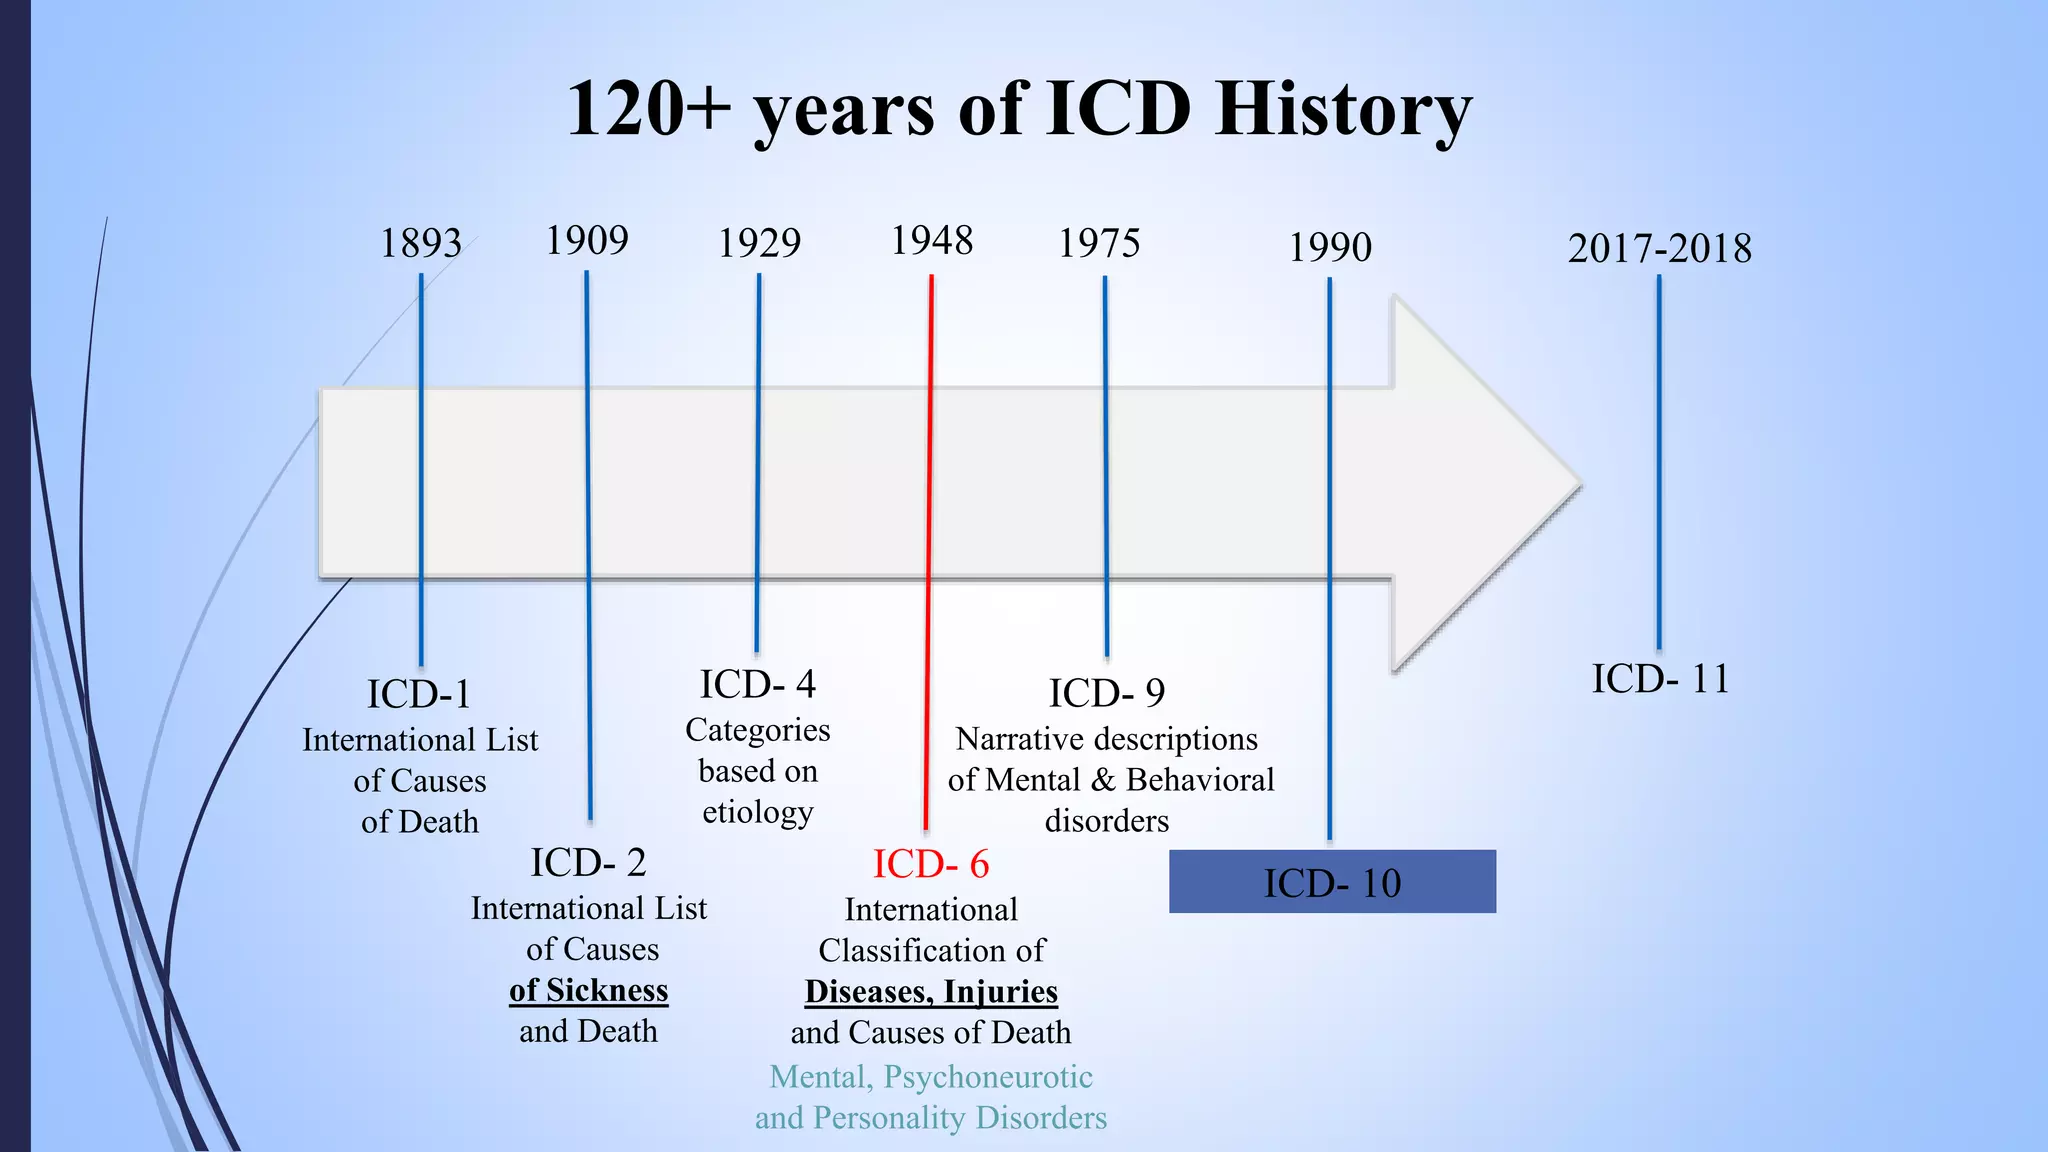
I spent about a decade working in medical records and secondary care data quality. One thing I learned early on is that nobody actually thinks about ICD until they have to fill out a death certificate or a hospital episode statistic form. The Classification System shifts under your feet just enough that you can't get comfortable with any version for long. The NHS has been running on ICD classifications since the 1960s, when the World Health Organization first published the tenth revision. Before that, we were using older British adaptations that didn't map cleanly to anything international. The whole point of standardisation was supposed to be comparability. You could look at mortality data from Birmingham and match it against a hospital in Toronto. That still sounds nice in theory, but the practical reality is messier.
Shifting Gears The Evolution Of Icd Classification System Used By Nhs
The jump from ICD-9 to ICD-10 happened in the UK around 1994. It wasn't just a rename. The coding structure changed fundamentally. ICD-9 had around 13,000 codes. ICD-10 exploded that to over 16,000. NHS trusts had to retrain staff, rebuild their systems, and migrate decades of historical records. Many never completed the migration cleanly. I've seen datasets where the same patient appeared three times under different coding versions because someone in the trust didn't update the mapping table properly. Then came ICD-10-AM, the Australian Modification. The NHS adopted this as the base for its own refinement. But the UK didn't just adopt it and move on. We kept adding our own extensions. ONS variants. NHS adaptations. The coding system started fragmenting in ways that even senior coders found confusing. I remember a case in 2014 where two hospitals in the same region coded the same admission differently because one was using the 2013 OPCS update and the other was on the 2014 revision. The discrepancy showed up in the HES dataset and took six months of manual reconciliation to fix.
How the coding process actually works in practice
When a patient is admitted to hospital, the coder looks at the discharge summary, the operative notes, the pathology reports, and sometimes the patient's primary care record. They assign a code from ICD-10 that captures the principal diagnosis. If there are multiple conditions, secondary codes follow. This sounds straightforward until you hit a case like a patient admitted for hip replacement who also has type 2 diabetes, hypertension, and a history of deep vein thrombosis. The coding guidelines tell you exactly how to sequence these, but the guidelines themselves changed between 2018 and 2021, and the changes weren't consistently rolled out across all trusts. The sequence matters because it drives funding. NNN (National Non-Electricity) tariffs in the Payment by Results system are tied directly to HRG codes, which are generated from the ICD-10 and OPCS-4 combinations. Get the principal diagnosis wrong and the trust either gets underfunded or flagged for an audit. I worked with a mid-size trust in the Midlands that lost roughly £40,000 in a single financial year because a new coder misclassified sepsis as a generic infection. The fix required manual review of every relevant episode over eighteen months.
Get the Full Details
ICD-11 and what the NHS is still figuring out
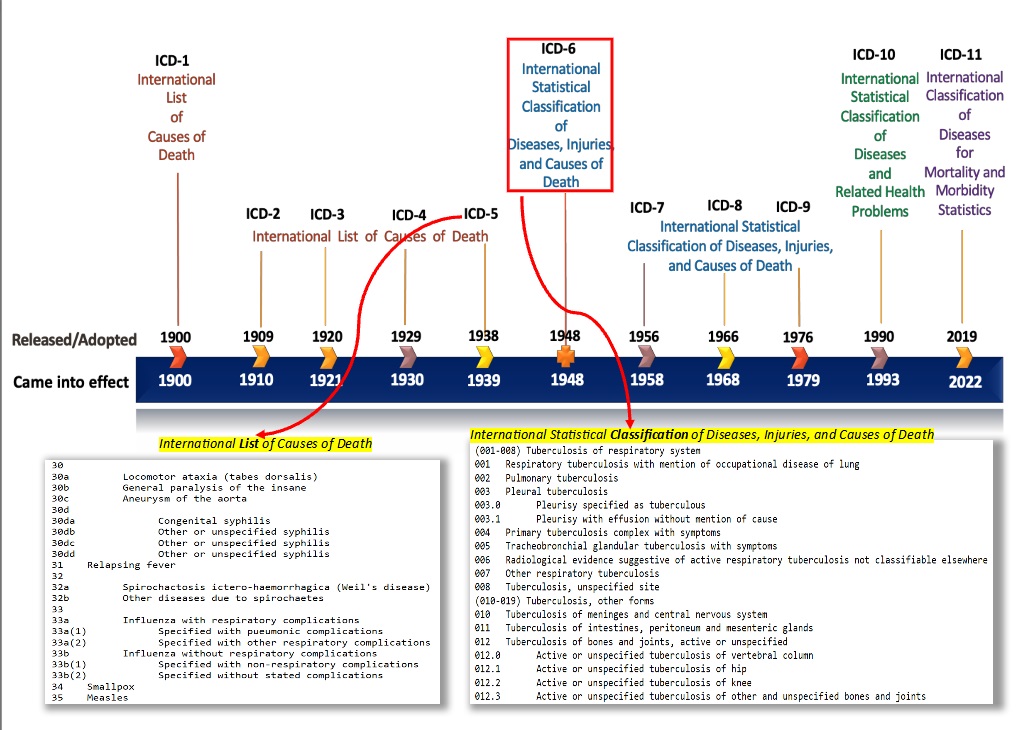
WHO published ICD-11 in 2019. It's structurally very different from ICD-10. The linear array structure replaced the alphabetic index. Multiaxial coding for mental and behavioural disorders became more integrated. The tabular list is now organised around sections rather than chapters in the old sense. The NHS has been preparing for adoption since around 2022, but full implementation is staggered and incomplete. Here's something most people outside the field don't realise: the transition isn't a simple software update. Every clinical system in the NHS has to remap its code sets. CPOE systems, discharge summary templates, cancer registry feeds, mortuary information systems. I consulted for a trust in 2023 that discovered their pathology lab interface hadn't been updated for ICD-11 equivalents. The interface was still pushing ICD-10 codes into a new system that expected ICD-11 structure. Half their lab results were coming through as unmapped. This went on for three weeks before anyone noticed because the error messages were being swallowed by the integration layer. The other issue is backward compatibility. Researchers need to link historical ICD-10 data with new ICD-11 data. The NHS Digital translation tables exist, but they're approximations. A single ICD-11 code can map to multiple ICD-10 codes and vice versa. There's no perfect one-to-one correspondence. If you're doing longitudinal studies spanning the transition, you need to account for this gap explicitly or your effect estimates will be biased.
Common mistakes that still happen regularly
Below specificity is the most frequent error. Coders will assign E11.9 for type 2 diabetes without complications when the notes clearly document diabetic retinopathy. The correct code would be E11.311 or E11.319 depending on laterality. This matters for risk adjustment in stroke and cardiovascular outcomes. Similarly, V-codes for external causes are often omitted entirely. A patient who presents after a fall from stairs should have the fall code as an additional diagnosis, but I've seen trusts where this happened in under 40 per cent of eligible cases. Another persistent problem is late decomposition. When a condition develops during hospitalisation, it should be coded as a complication, not as a pre-existing condition. I audited cardiac surgical outcomes at a London trust and found that post-operative atrial fibrillation was consistently coded as a comorbidity rather than a complication. This inflated their observed risk-adjusted mortality rate by about 12 per cent over two years. The fix was a targeted education programme for the coding team combined with a retrospective recoding exercise.
What the system gets wrong
ICD-10 and ICD-11 were designed for mortality statistics, not for the administrative needs of a modern healthcare system. The coding granularity is adequate for cause-of-death certification but inadequate for many clinical scenarios. Social determinants of health barely feature. Rare diseases have poor coverage. Mental health coding in particular remains frustratingly coarse, especially for complex presentations like personality disorders with comorbid substance misuse. The NHS also faces a structural problem: the coding system is updated annually with minor revisions, but the funding and reporting cycles don't always align with those updates. New codes for emerging conditions like long COVID took months to be formally incorporated into the UK variant tables. During that gap, cases were either miscoded or left unclassified. The data quality hit was real and measurable. For anyone working with NHS data, the practical advice is simple but hard to follow. Always check the version of ICD-10-AM you're using against the fiscal year of the dataset. Don't trust the automated mappings between versions. And when you see a code that looks suspiciously generic, go back to the source document. The code is only as good as the clinical information behind it.