Setting Up Clinical Shift Automation at WakeMed
I started working with Shift Wizard at WakeMed back in 2022 when we were trying to reduce the administrative burden on our nursing staff. The core problem was simple: shift scheduling and clinical workflow handoffs were happening through a patchwork of spreadsheets, emails, and half-trained intuition. Nurses were missing critical patient status updates because those details lived in Slack threads and printed whiteboards that nobody updated consistently. The solution we built around Shift Wizard wasn't magic. It was about creating a single source of truth for shift assignments, clinical task routing, and handoff documentation that actually got used. Most people overcomplicate this by trying to automate everything at once. We started with just three things: shift assignment visibility, task prioritization rules, and the handoff protocol. Everything else came later.
How Shift Wizard Wakemed Revolutionizing Digital Health With Smart Clinical Workflow Automation Actually Works in Practice
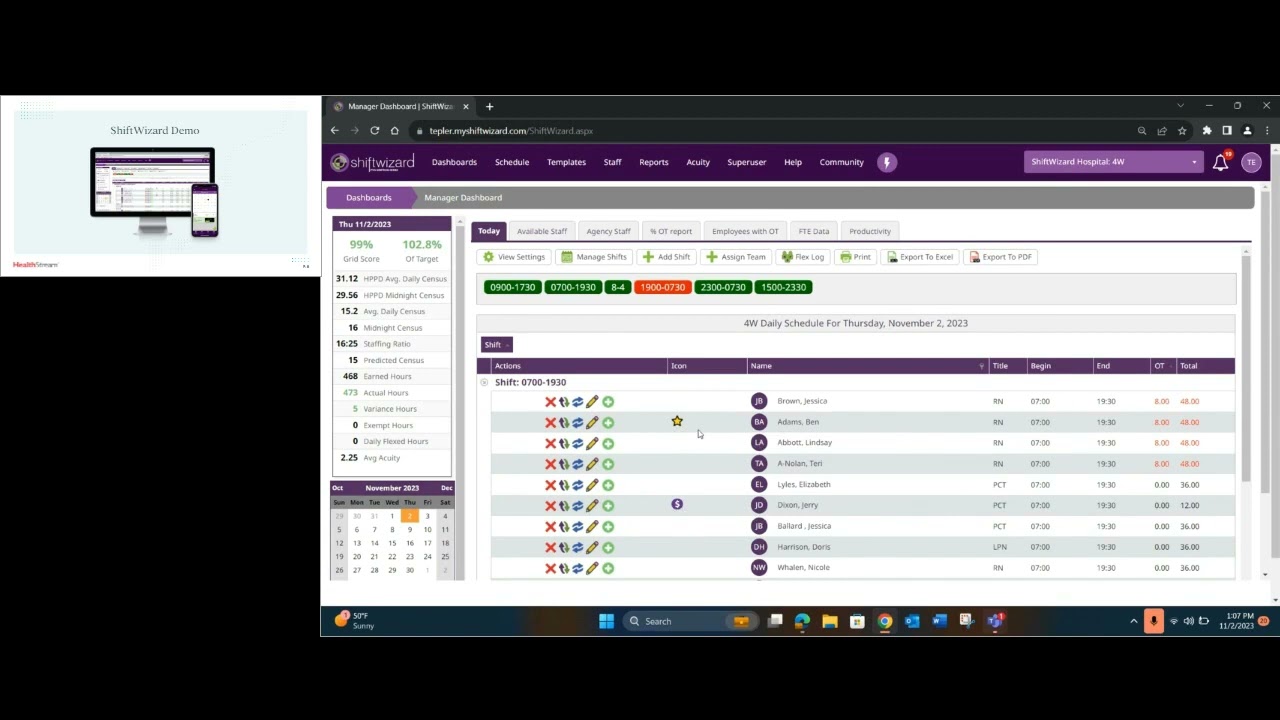
Here is what the day-to-day looks like once you have it running. A nurse clocks in through the Shift Wizard portal or mobile app. The system pulls her assignment from the master schedule, displays her current patient list, and flags any tasks that are overdue or due within the next hour based on the clinical protocols you configured. When she completes a task or updates a patient status, that information propagates to the oncoming shift in real time. No more guessing what happened during the 7a to 7p shift. The automation rules are where most installations stall. You need to define your escalation logic, your task routing hierarchies, and your handoff templates before you go live. I recommend building these with actual frontline staff, not administrators who haven't worked a shift in years. The difference shows up immediately in adoption rates. We configured our rules in about three weeks. The first draft took two days. The second draft, after input from the charge nurses, took another week and a half. That second version is the one that stuck.
Implementation Steps That Actually Matter
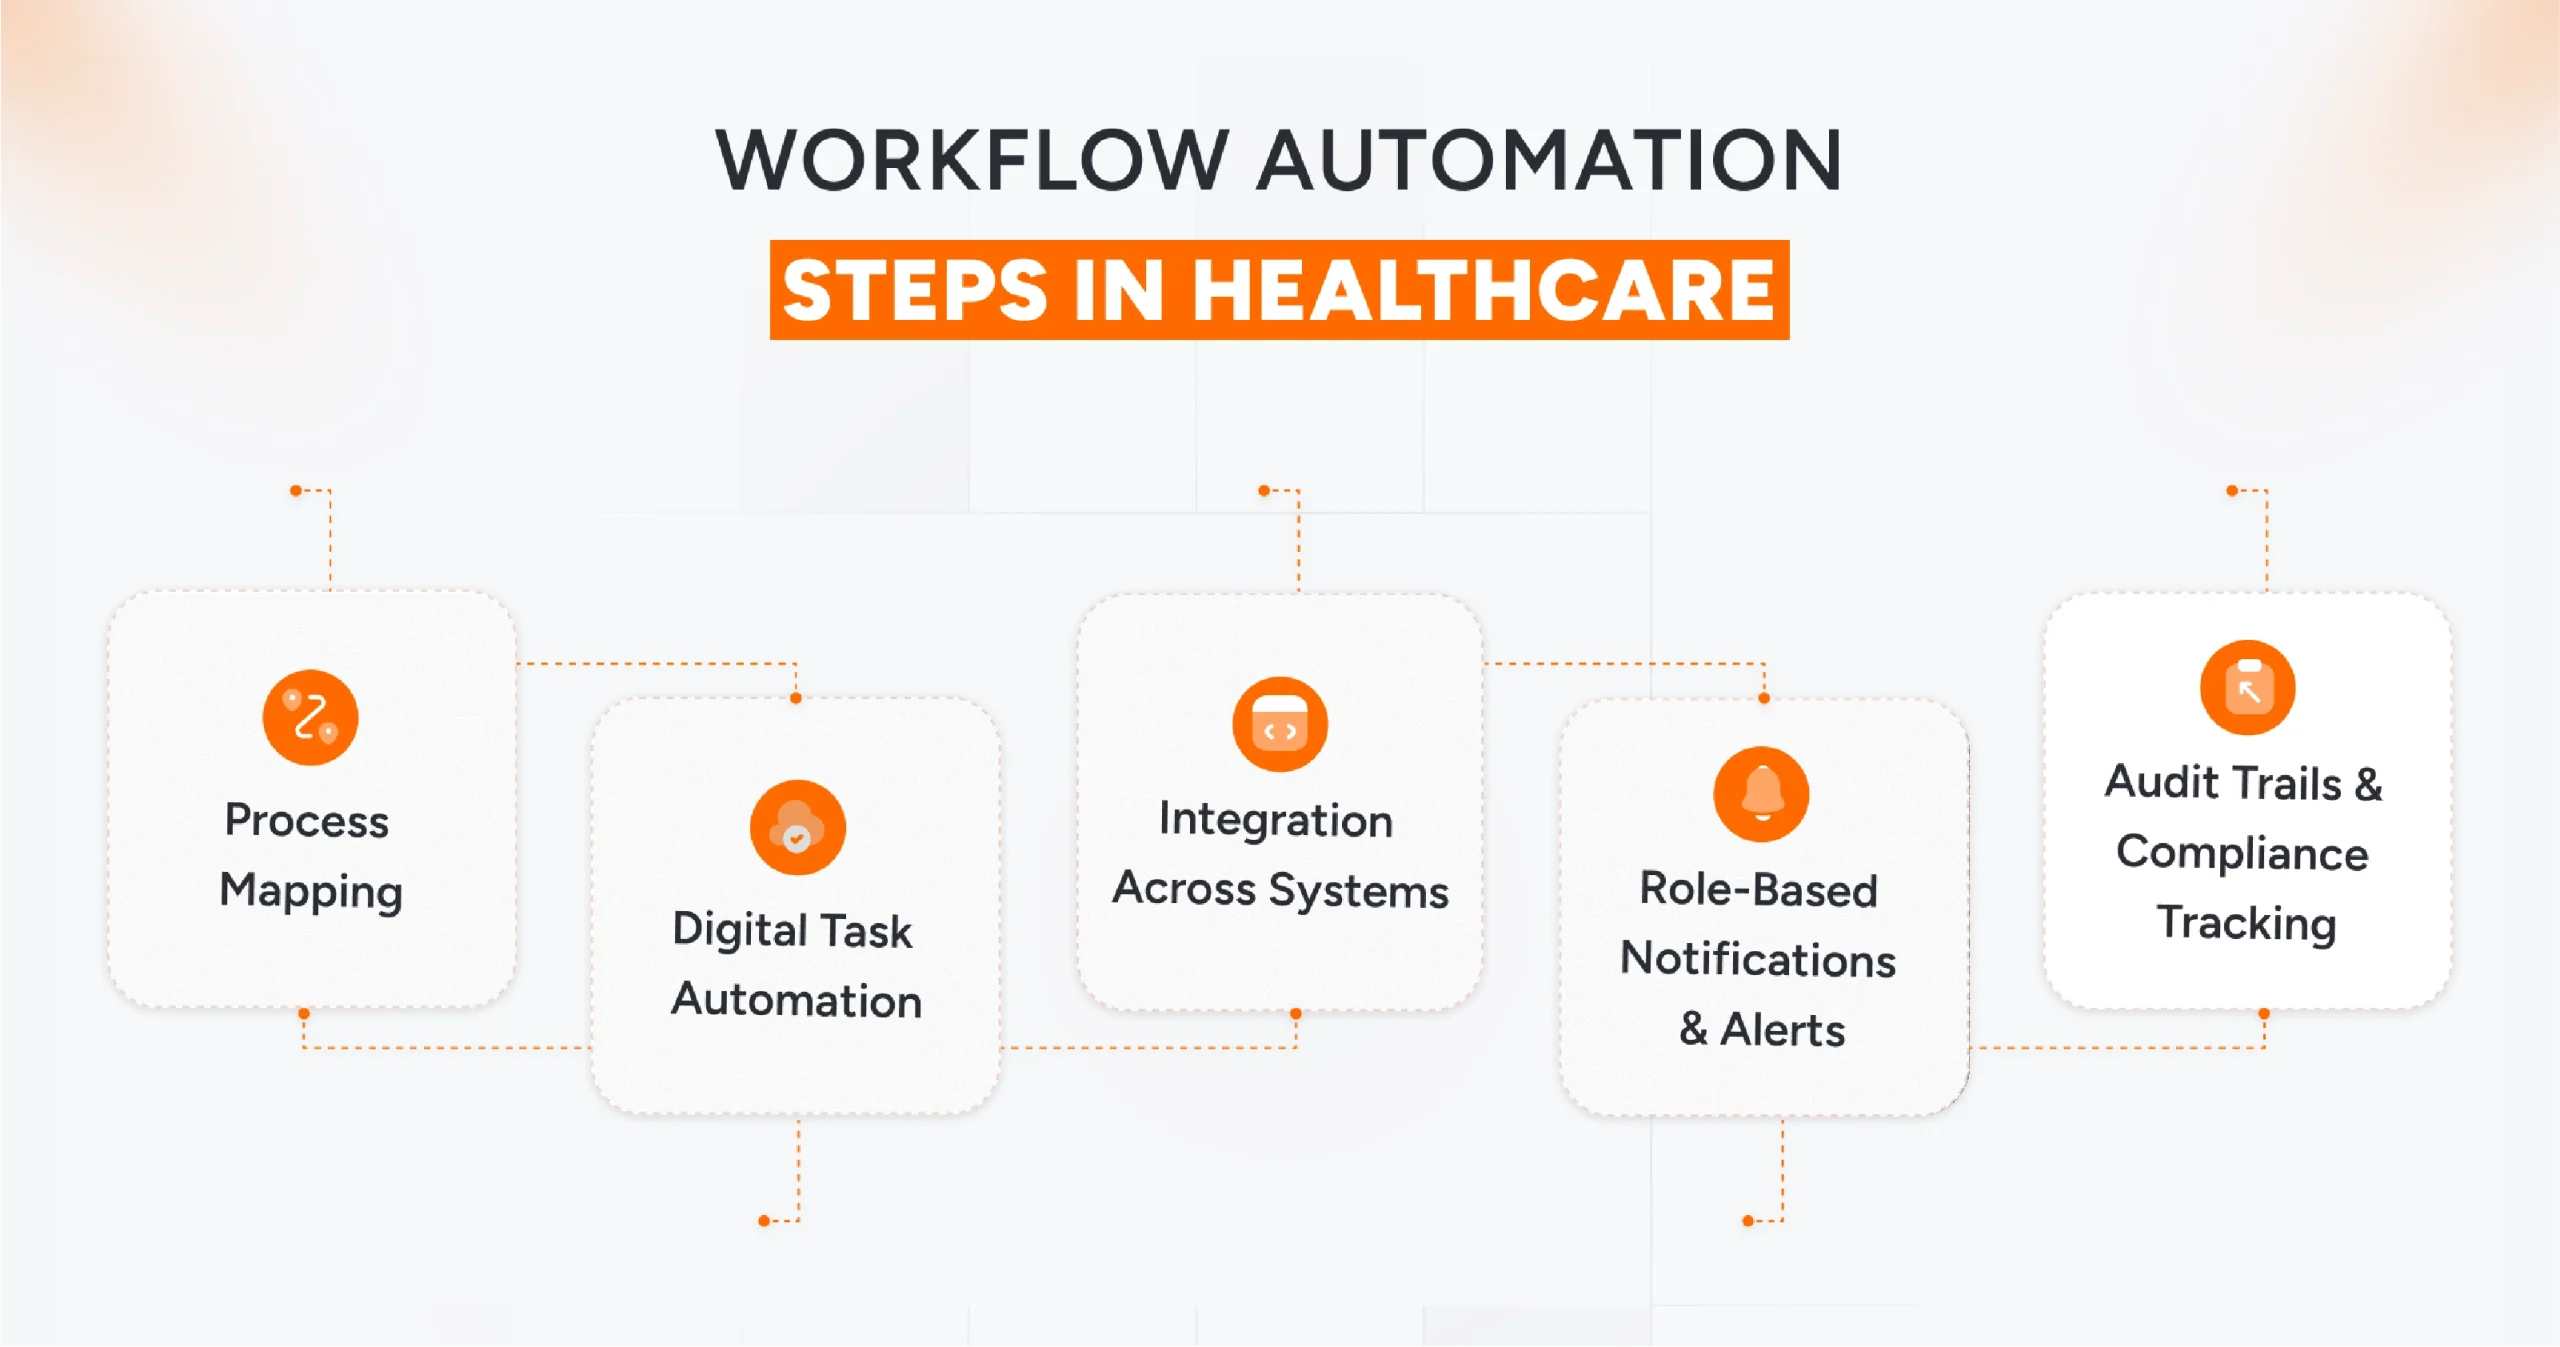
Map your existing workflows first. Write them down step by step, including the steps you skip when you are busy. Those skipped steps are usually the ones causing the errors. At WakeMed, we discovered that our medication reconciliation handoff was being done informally between shift changes about 40% of the time because no one had codified it into the old system. Configure your integration with the EHR. Shift Wizard connects to Epic, Cerner, and a few others, but the integration quality varies by vendor and by how customized your instance is. We had to work with our Epic team to expose the right data fields for the shift tasks. This took about ten business days of back and forth. Don't underestimate this part. Set up role-based access control. Some staff should see patient-level detail. Others should only see shift assignments and task lists. Mixing these permissions up creates compliance headaches and also just makes the interface noisy for people who don't need all that information.
Get the Full Details

Pilot with one unit before rolling out hospital-wide. We started with the medical-surgical floor. It gave us a controlled environment to catch the edge cases without disrupting the entire hospital. Two weeks on med-surg, then we expanded to telemetry and step-down over the following month.
A Specific Problem We Hit and How We Fixed It
About six weeks after going live, we ran into an issue where shift swaps were creating orphaned tasks. When a nurse traded her shift with a colleague through the portal, the tasks assigned to her original shift didn't always transfer correctly. Some would remain linked to the outgoing nurse's ID, which meant the incoming nurse couldn't see them in her dashboard, and the tasks would show as incomplete at the end of the shift even though they had been done. The workaround was to add a manual task reassignment step to our shift swap protocol. When a swap is initiated, both parties have to confirm that open tasks have been transferred. We also built a nightly audit report that flagged any tasks still assigned to an inactive nurse ID at shift end. This caught the remaining edge cases and gave us data to push for a permanent fix, which Shift Wizard delivered in a subsequent update about three months later.
Counter-Intuitive Things Beginners Miss
Most people try to configure Shift Wizard to match their existing process exactly. That is usually the wrong move. If your current process is broken, automating it just makes the broken process run faster. We spent three weeks simplifying our handoff protocol before we even touched the automation settings. The simpler the underlying process, the more the tool actually helps. A streamlined three-field handoff template produced better results than the eight-field version we had been using on paper for years. Another thing: the reporting dashboard is powerful but easy to drown in. We initially enabled every metric the system could track. After two weeks, nobody was looking at it because there was too much noise. We trimmed it down to five key indicators: shift fill rate, task completion rate within expected windows, handoff completion rate, escalation response times, and overtime hours. Five metrics that people actually check daily instead of forty that get ignored.
Where It Falls Short
Shift Wizard is not a complete clinical workflow solution on its own. It handles scheduling and task automation well, but it does not replace your EHR, your medication management system, or your incident reporting platform. If you are expecting it to do everything, you will be frustrated. It works best as an orchestrator that sits on top of your existing systems, not as a replacement for them. The configuration interface also has a learning curve. Our first attempt at setting up custom escalation rules failed because the UI didn't clearly indicate how the conditional logic would evaluate. We ended up calling our account manager and spending an hour on a call walking through the rule builder. For a tool that promises to save time, the initial setup can consume a surprising amount of it. Budget at least three to four weeks of configuration time before you expect meaningful results. Certain complex staffing scenarios, like floating staff across multiple units during a surge, don't integrate cleanly. The system assumes relatively stable unit assignments. When your staffing pattern gets chaotic, which happens in real healthcare environments, the automation logic can produce suboptimal suggestions. In those situations, manual override is necessary, and you should plan for that friction.
If your organization is very small with fewer than two hundred beds, the cost and configuration overhead may not justify the return. We discuss alternative solutions in that case, but the specifics depend heavily on your existing technology stack and budget.
Bottom Line
The tool works when you treat it as a workflow improvement project first and a technology installation second. The software is capable, but its value comes from how thoughtfully you configure it to match the actual work your staff does. Rush the configuration, skip the frontline input, or expect it to fix fundamentally broken processes without changing those processes first, and you will waste money and time. Do it right, and your shift handoffs become reliable, your task visibility improves, and your staff spends less time wondering what they missed between shifts.