What Shadow Health Actually Teaches You About Post-Op Rounding
Hourly rounding in the surgical setting sounds straightforward when you read the policy. Assess the patient, check the vitals, document, escalate if something looks wrong. The simulation platforms make it worse by turning it into a timed checklist exercise. Shadow Health Perioperative Care Hourly Rounds Transforming Surgical Safety And Patient Outcomes is the actual module name your school probably assigned, and I spent way too many hours figuring out how to get past the automated grading. Here is how it works and what trips people up. The simulation drops you into a postoperative patient scenario, usually a generic abdominal or orthopedic case. You move through a structured hourly rounding assessment that covers pain, vital signs, respiratory status, surgical site, intake and output, mobility, and skin integrity. The platform grades you on whether you actually assessed each domain and whether your clinical reasoning connects the dots when something starts to go sideways. Students who treat it like a form-filling exercise score poorly. Students who read the entire case background first tend to do better. Here is what most people miss. The grading rubric rewards early recognition of deterioration, not just catching it after the numbers become dramatic. A patient three hours post-appendectomy with a heart rate creeping from 88 to 102 and a blood pressure dropping from 118 over 76 to 106 over 68 is not yet in crisis. The simulation wants you to notice the trend and intervene before the pulse oximeter reads 88 percent and the nurses call it. That is the difference between a passing score and a good one.
How the Module Actually Works
You launch the case from your course link inside the Shadow Health dashboard. The system loads the patient record, surgical details, current orders, and laboratory values. You then enter the hourly rounding session. The interface gives you tabs or sections for each assessment area. You complete each section by selecting findings from dropdown menus, entering numeric values, or typing short documentation notes. After you finish the assessment portion, you make care decisions. This usually means choosing interventions, adjusting pain medication, requesting a physician call, or modifying the frequency of monitoring. The feedback comes at the end. It breaks down what you did right, what you missed, and where your reasoning went off track. Some schools count this toward a percentage grade. Others use it as a completion requirement. Either way, the module does not give you a second chance to change answers once you submit. The simulation locks your responses when you move forward. Plan your documentation before you advance. I hit one edge case that took me two attempts to figure out. The scenario placed the patient on a clear liquid diet restriction after a bowel resection, and the rounding assessment included a gastrointestinal component where you had to document bowel sounds and abdominal distention. The system marked my documentation incorrect because I wrote that the abdomen was soft and non-distended when the case data showed early ileus signs. The subtle finding was mild tympany on percussion that the simulation expected you to note. I had been focused on the distention visual cue and missed the percussion component entirely. Once I went back through the case data and paid attention to the laboratory values showing rising white blood cell count alongside the bowel sound ratings, I adjusted my documentation to include mild tympany and hypoactive bowel sounds in all four quadrants. The score jumped from a failing range to above 85 percent on that section.
The workaround was simple but not obvious. I stopped treating the assessment as a standalone task and reviewed the entire patient history first. The case included surgical notes, preoperative labs, and anesthesia records. Reading those before starting the rounding session gave me the clinical context I needed to know what findings actually mattered for that specific procedure. Without that background, I was just checking boxes.
Get the Full Details
Common Pitfalls That Drop Your Score
Documentation timing is a silent killer in this module. Students often complete the assessment first and then rush the care decision section. The system expects you to connect the two. If your assessment shows elevated pain and you do not address it in the intervention section, the rubric flags it as a gap. Do not separate the assessment from the action. Make your documentation and your decisions reflect each other in the same pass. Another issue is the false sense of security around normal vital signs. The simulation occasionally presents a postoperative patient whose vitals look acceptable on the surface. Blood pressure is stable. Oxygen saturation reads 96 percent. Heart rate is within the normal range. But the respiratory assessment reveals shallow breaths, decreased depth, and a pattern of splinting from abdominal incision pain. The grading looks for recognition of this combination. A single normal number does not override the rest of the picture. Document the shallow respirations and the pain-related splinting. Recommend positioning adjustments and evaluate whether the current analgesic regimen is sufficient. The system rewards that synthesis. Fluid balance is the third trap. Intake and output documentation often gets treated as an afterthought. If the patient received significant intraoperative fluids and the urine output is trending low relative to that volume, that is a red flag. The simulation expects you to calculate approximate balance and raise concern if the numbers do not align. Do not just enter the numbers and move on. The clinical reasoning component checks whether you noticed the mismatch.
Where This Simulation Falls Short
Shadow Health perioperative rounding is a training tool. It is not a replacement for real clinical experience. The simulated patients respond in predictable patterns that do not match the variability of actual postoperative courses. A real surgical unit has four patients needing attention simultaneously. The simulation isolates one case. Communication with the actual surgical team does not happen. You type a response and click submit. The feedback is automated and follows a fixed rubric. It cannot capture the nuance of a charge nurse stepping in to redirect your approach because the clinical situation demanded something the simulation did not account for. Some of the clinical scenarios feel outdated. Pain assessment still relies heavily on numeric rating scales in the simulation, but contemporary perioperative pathways emphasize functional recovery metrics and multimodal analgesia. The module does not always reflect current enhanced recovery after surgery protocols. If your program uses ERAS guidelines, the simulation may lag behind what your clinical preceptors expect you to practice. Use it as a baseline exercise, not as the final word on perioperative care standards. There is also the issue of scoring rigidity. The automated grading does not distinguish between documentation that is clinically sound but phrased differently and documentation that matches the rubric exactly. You can make the correct clinical decision and lose points because your wording does not align with the expected terminology. This frustrates students who understand the material but struggle with the specific phrasing the system demands. Learning to write in the language the rubric expects is part of the hidden curriculum here.
How to Approach the Module Effectively
Read the entire case before you start rounding. Review the surgical procedure, the anesthesia type, the postoperative orders, and the relevant laboratory results. This takes approximately five to ten minutes upfront and saves you from making incorrect assumptions during the assessment. The background information contains clues about what complications are most likely for that specific patient population. Work through each assessment domain methodically. Do not skip sections to reach the intervention portion faster. The rubric penalizes incomplete assessments. Pain, vitals, respiratory, surgical site, neurovascular status if applicable, intake and output, mobility, and skin each carry weight. Some cases emphasize certain areas over others based on the procedure type. An orthopedic case will weigh neurovascular checks more heavily. An abdominal case prioritizes respiratory function and gastrointestinal assessment. Adjust your focus accordingly rather than applying the same uniform approach to every scenario. When making care decisions, anchor each recommendation to a finding from your assessment. State the clinical reason explicitly. If you are increasing pain medication, reference the pain score and the current medication schedule. If you are calling the surgeon, specify the abnormal finding that triggered the call. The simulation grades the reasoning, not just the choice itself.
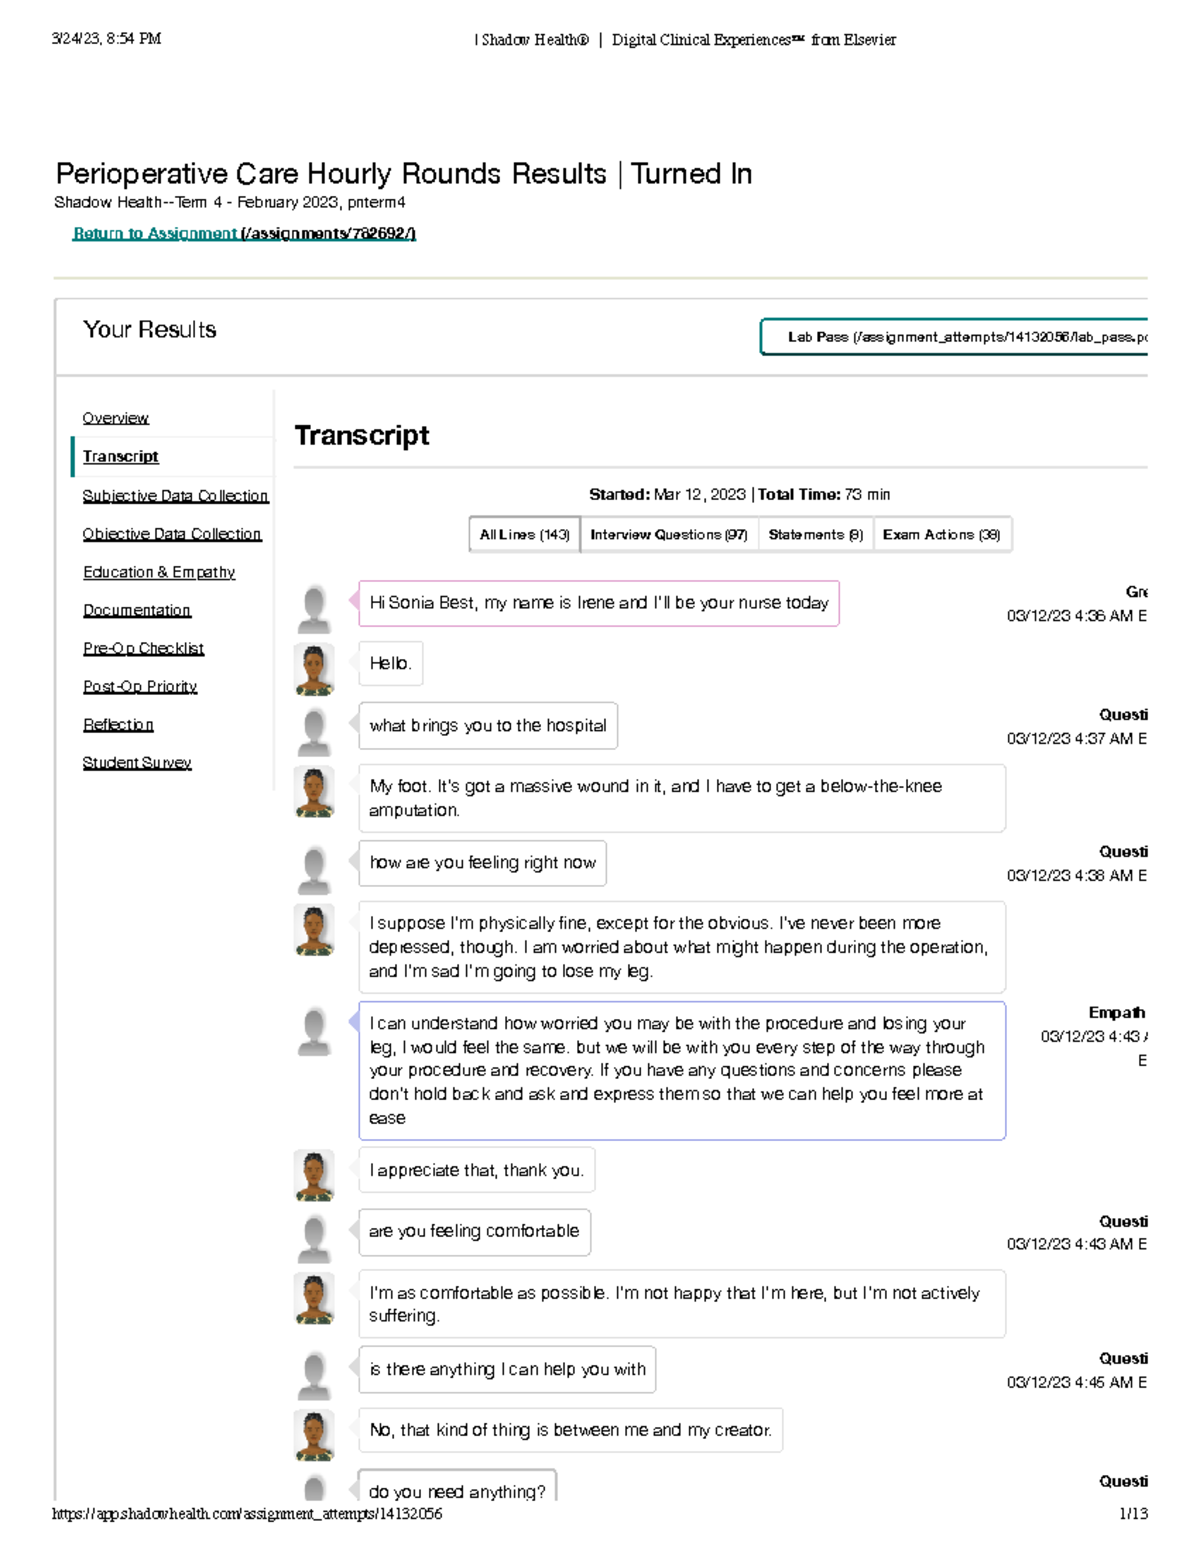
Review the feedback thoroughly after each attempt. The explanation of what you missed contains more educational value than the score itself. Note which domains you consistently underperform on and focus your next attempt on those areas. Most students improve significantly after the second or third run-through because they learn the patterns the simulation rewards. For the download and access question, Shadow Health operates through institutional licensing. There is no direct consumer download. You access the platform through your school login. Check your learning management system or contact your nursing program coordinator for the activation link. The Perioperative Care module is typically included in the standard clinical simulation package that most accredited nursing programs purchase. If your school does not have access, you will need to request it through the department rather than finding a standalone installation file. The simulation has limited utility outside of an academic setting. It is designed for nursing and allied health education, not for practicing clinicians seeking continuing competency. Hospitals use different tools for postoperative rounding standardization. The module is what it is: a graded practice environment that approximates the cognitive demands of postoperative assessment. It builds foundational pattern recognition. It does not replace the complexity of actual patient care. Treat it as structured rehearsal and move on to clinical rotations with whatever framework the simulation helped you develop.