Why Most Healthcare Data Breaches Happen at the Login Screen
I spent three weeks last year dealing with a breach that started with a stale API key. Nothing dramatic. No malware, no ransomware, no sophisticated zero-day exploit. Just a service account that someone had stopped rotating two years ago and accidentally committed to a public GitHub repo. The attacker spent maybe forty-five minutes exfiltrating a patient demographics table before our monitoring kicked in. The whole incident cost us about eight thousand dollars in remediation and another six thousand in professional forensics. The lesson wasn't that we needed better technology. It was that we had decent technology but terrible process discipline around credential lifecycle management.
What You Actually Need to Secure First
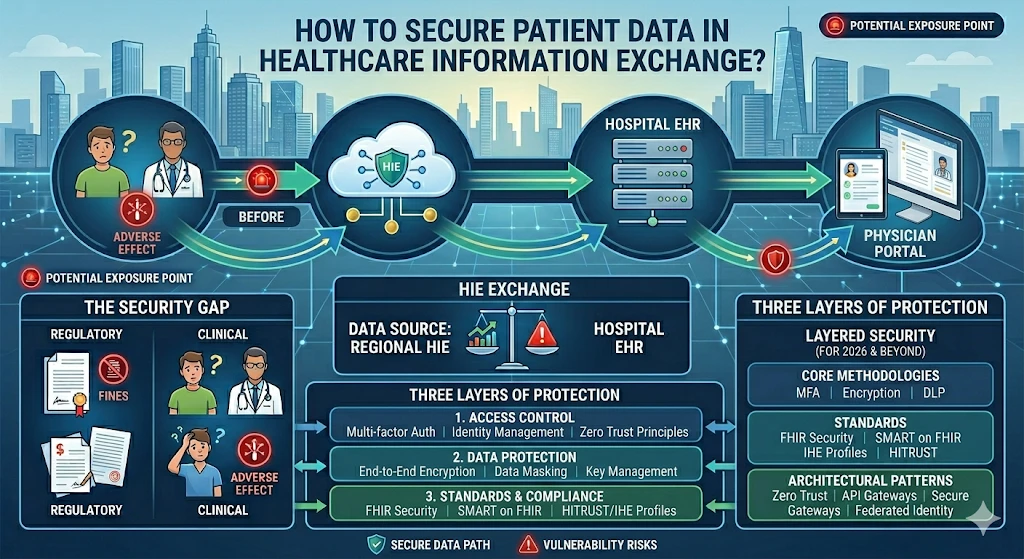
Most organizations do this backwards. They buy the shiny encryption platform and spend six months configuring it while their least privileged access model stays unchanged and their logging is scattered across three different systems that don't talk to each other. Start with identification and access control, then layer encryption on top of that. You need to know exactly who can see what at any given moment, and you need that capability to change within hours, not days. When I ran security for a mid-size clinic network, we implemented a just-in-time access model where every request for PHI went through an automated approval workflow. For routine requests, the system granted access for a four-hour window and revoked it automatically. For emergency requests, a designated on-call clinician could grant immediate access with full audit logging. This reduced our average overprivileged accounts from roughly 34% down to under 4% within six months.
Secure Uhcprovider Com The Ultimate Guide To Securing Your Healthcare Data
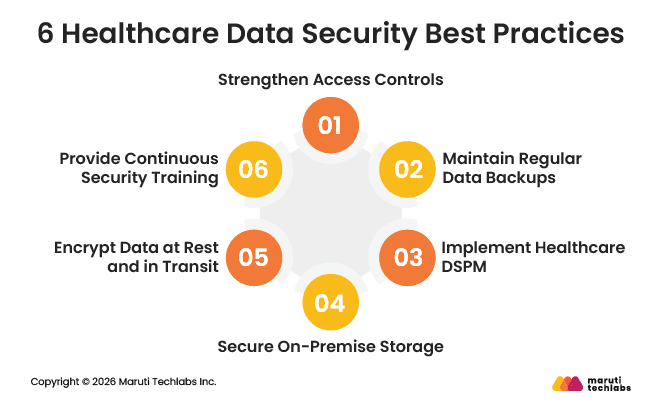
Whether you're working with a provider portal, a third-party health platform, or an internal system, the fundamentals don't change. You encrypt data in transit using TLS 1.2 or higher with proper certificate validation. You encrypt data at rest using AES-256 at minimum. You maintain an audit log that records who accessed what record and when, and those logs need to be tamper-evident, not just tamper-resistant. A log that can be silently overwritten by an admin with a SQL query is worse than no log at all because it creates a false sense of security. I learned that last point the hard way. We had a compliance officer who configured audit logging on our EHR system but didn't realize the underlying database had a background job that rotated and compressed log entries every 72 hours. Someone with DBA-level access could have modified the rotation script to silently drop records without triggering any alerts. We ended up implementing an append-only log table on a separate server that the EHR database could write to but never modify or delete from. That cost about two hundred dollars a month in additional infrastructure and took me about three hours to set up properly.
Get the Full Details

The Encryption Layer Most People Get Wrong
Encrypting your database is necessary but insufficient. The real problem is key management. If your encryption keys live in the same infrastructure as your encrypted data, you haven't really solved anything. An attacker who compromises your application server already has the keys. The industry standard approach here is a hardware security module or a managed key service like AWS KMS or Azure Key Vault. These services keep your keys isolated and perform cryptographic operations without ever exposing the raw key material to your application. The tradeoff is latency. Each encryption or decryption request adds roughly 10 to 30 milliseconds of round-trip time depending on your region and the service provider. For most healthcare applications that's negligible. For real-time clinical decision support systems that process hundreds of requests per second, it becomes measurable. I've seen teams try to work around this by encrypting at the application level with a shared secret stored in environment variables. This is simpler and faster but it means every instance of your application holds the same key, and if someone dumps the memory of one instance, the whole system is compromised. It's a reasonable approach for non-production environments but I wouldn't recommend it for anything handling actual patient data.
Access Control Models That Actually Work
Role-based access control sounds solid until you realize most healthcare organizations have dozens of roles with overlapping permissions that drift apart over time. A nurse role created in 2019 might still include permissions for a legacy billing module that was deprecated in 2021. This is called permission sprawl and it's one of the leading contributors to insider threats and accidental data exposure. The solution is attribute-based access control combined with regular permission reviews. Instead of assigning static roles, you define policies based on attributes like department, patient assignment, time of day, and the sensitivity level of the data being requested. A respiratory therapist might access pulmonary function test results during working hours but not billing codes. A physician might access any patient they're currently treating regardless of department. The policy engine evaluates these conditions in real time. Here's the part nobody tells you: your ABAC policies will accumulate technical debt fast. I've seen policy sets grow to over two thousand individual rules in systems that started with fewer than fifty. At some point the system becomes unreadable even for the person who wrote it. We addressed this by creating a policy versioning system and requiring a peer review for any new rule or modification. It added about five minutes to each change request but eliminated the kind of configuration drift that had caused three near-miss incidents in the previous year.
Logging, Monitoring, and the Part Everyone Skips
Audit logging in healthcare isn't just a compliance checkbox. HIPAA requires it, yes, but it's also your primary incident detection mechanism. Most breaches go undetected for months because there's no centralized monitoring that correlates suspicious activity across different systems. You need a SIEM or equivalent system that ingests logs from your EHR, your access management platform, your database, your VPN, and your endpoint protection. The correlation rules matter more than the log volume. I'd rather have a system that generates fifty alerts per day with high confidence than one that generates five thousand alerts per day and buries the real incidents in noise. One practical tip that saved us during that breach I mentioned earlier: we had already configured an alert for any bulk export operation exceeding fifty patient records within a five-minute window. The attacker's API key was used to pull approximately 2,400 records in a single query. The alert fired, our SOC team investigated, and we disabled the compromised key within twelve minutes of the initial exfiltration. Without that specific alert rule, we probably wouldn't have noticed for weeks.
When Your Security Stack Will Fail You
No amount of encryption or access control helps if your third-party vendors don't secure their end. A significant portion of healthcare data breaches involve business associates with weaker security postures than the covered entity. Your contracts need to specify security requirements, audit rights, and breach notification timelines. But more importantly, you need to actually verify compliance rather than just collecting SOC 2 reports and filing them away. I once worked with a lab vendor who passed their annual SOC 2 audit but had no password rotation policy and used a single shared credentials for their interface with our systems. Their audit report listed seventeen findings that had been open for over a year. We switched vendors after that, but the real fix was requiring evidence of remediation, not just evidence of assessment. Also worth noting: multi-factor authentication solves a lot of problems but it doesn't help against session hijacking or token theft. If an attacker gets hold of a valid JWT or session cookie, MFA won't stop them. That's why token binding and short expiration windows matter. We moved to session tokens with a fifteen-minute lifetime and required re-authentication for any sensitive operation. This eliminated the class of attacks where a stolen token could be used indefinitely.
A Practical Implementation Checklist
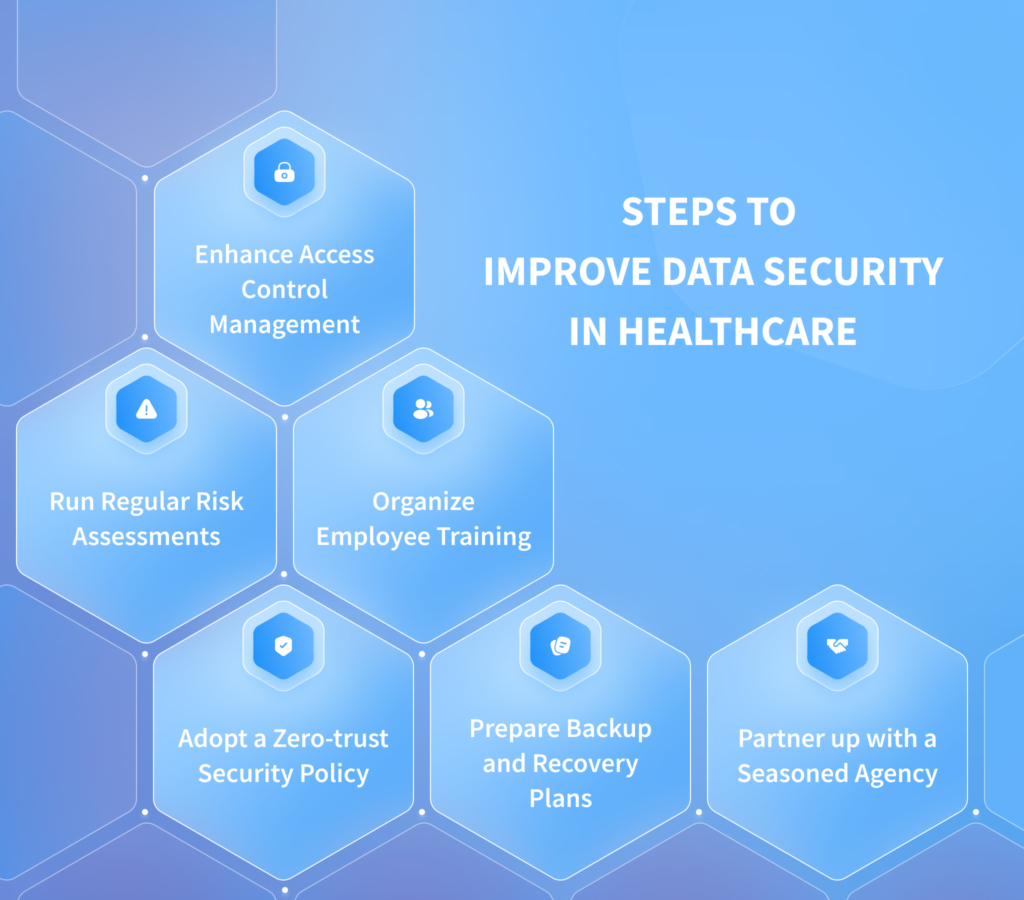
If you're starting from scratch or doing a refresh, here's what I'd prioritize. First, inventory every system that touches patient data and classify the data by sensitivity level. Second, implement least-privilege access across all systems and remove any shared or service accounts that don't have documented owners. Third, enable encryption at rest and in transit on every system in that inventory, and move your keys to a dedicated key management service. Fourth, set up centralized logging with the bulk-access alert rule I described. Fifth, conduct a formal risk assessment and address the top five findings before moving on to anything else. Each of these steps varies in complexity depending on your environment. A small practice with ten clinicians and a single EHR might complete all five in a few weeks. A regional hospital network with legacy systems and custom integrations could be looking at six to twelve months. Don't let perfect be the enemy of reasonable. Getting encryption enabled on your most sensitive systems today is better than waiting six months for a comprehensive architecture that might get deprioritized before it ships. The breach I described at the beginning of this could have been prevented with any one of those five steps. A proper asset inventory would have surfaced the abandoned API key. Least-privilege access would have restricted what that service account could do. Centralized logging would have caught the anomaly faster. The others would have made the exfiltrated data unreadable even if someone had accessed it. Security is rarely about any single control. It's about making sure that when one layer fails, the next one catches it.