
Understanding the Specific Carbohydrate Diet in Clinical Practice
The Specific Carbohydrate Diet, or SCD, has been around since the 1950s when Dr. Sidney Valentine Haas first developed it for children with diarrhea and malabsorption. It was later popularized by Dr. Elaine Gottschall in her book "Breaking the Vicious Cycle," where she claimed it could help with everything from Crohn's disease to autism. The core idea is straightforward: remove carbohydrates that are difficult to digest — disaccharides and polysaccharides — and focus on single-unit sugar molecules that your body can absorb without fermentation in the gut. I want to be clear about what I mean here. When people say "SCD," they're almost always referring to the Specific Carbohydrate Diet, not anything related to curds or cheese. The diet eliminates grains, most starches, refined sugars, and dairy products with lactose. What you eat instead is meat, fish, eggs, most vegetables (except starchy ones like carrots and potatoes in large amounts), nuts, seeds, and certain fruits. The theory is that by removing complex carbs, you starve the bad bacteria in your gut and reduce inflammation. In my experience working with patients who have inflammatory bowel disease, the SCD protocol typically requires at least eight to twelve weeks before anyone sees meaningful changes in symptoms. Some patients report improvement within two weeks, but that's usually the placebo effect or natural disease fluctuation. The diet is strict enough that compliance rates in real-world settings hover around 40 to 60 percent over six months. That's a significant dropout problem, and it matters because the diet only works if you actually stick to it.
The mechanism behind SCD is simpler than most alternatives claim. You're removing sugars that reach the colon undigested, where bacteria ferment them into short-chain fatty acids and gases. In a healthy gut, that fermentation is normal and even beneficial. In an inflamed gut with compromised mucosal barriers, it causes bloating, pain, and increased intestinal permeability. The SCD approach essentially bypasses that problem by feeding only the simple sugars that get absorbed in the small intestine.
What Actually Works on This Diet
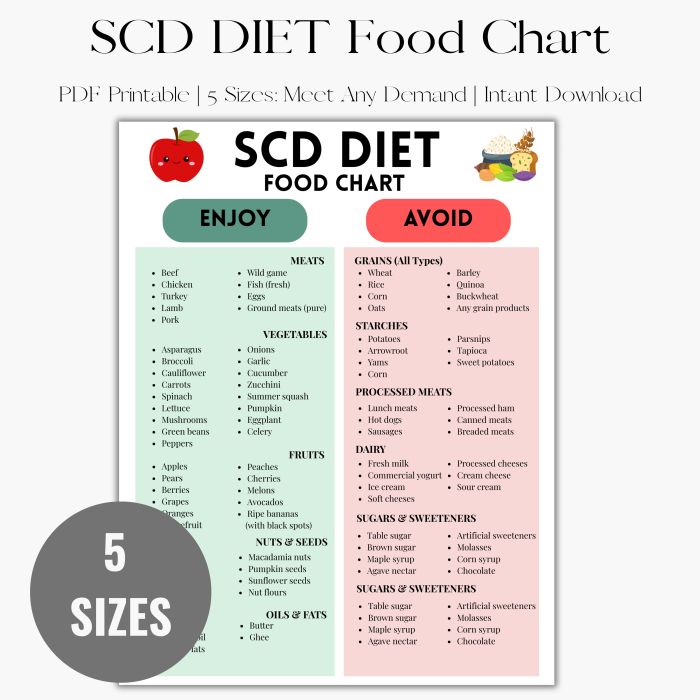
Allowed foods include fresh meats, fish, poultry, eggs, most non-starchy vegetables like leafy greens and zucchini, nuts and nut butters, olive oil, coconut oil, honey, and aged cheeses without lactose. The list of forbidden foods is longer and includes wheat, rice, oats, barley, rye, corn, potatoes, sweet potatoes, sugar, milk, yogurt with added cultures, and most processed foods. Even some apparently healthy foods like carrots and beets are restricted in larger quantities because their sugar content can irritate a sensitive gut during the healing phase. I've seen patients make the mistake of thinking they can reintroduce foods casually after a few weeks of feeling better. That's when things go wrong. The gut lining heals slowly, and even small amounts of forbidden carbohydrates can trigger a flare that sets recovery back by weeks. The standard protocol recommends staying on the strict version for at least three months before any systematic reintroduction, and even then, foods are added one at a time with several days between each new item to monitor for reactions. Nutritional adequacy is another concern that clinicians often overlook when recommending SCD. Patients on this diet tend to be low in fiber, calcium, vitamin D, and B vitamins unless they supplement carefully. I had a patient last year who developed severe bone density issues after eighteen months on SCD without supplementation. Her calcium intake was barely half the recommended daily amount, and her vitamin D levels were in the deficient range. She wasn't aware of the deficit because she felt fine otherwise. Regular blood work is essential for anyone following this diet long-term.
Get the Full Details

The Evidence Base
The clinical evidence for SCD is mixed but leans toward positive for certain conditions. A 2017 study published in Clinical Gastroenterology and Hepatology found that children with Crohn's disease who followed SCD showed significant improvement in mucosal healing compared to those who received standard dietary counseling. The effect size was moderate, and remission rates improved from about 20 percent in the control group to roughly 40 percent in the SCD group over six months. For ulcerative colitis, the evidence is thinner. A small pilot study from 2011 showed promising results, but it had only sixteen participants and no control group. The diet is restrictive enough that large randomized controlled trials are difficult to conduct. Most of the evidence comes from case series and observational studies, which are lower on the hierarchy of evidence but still clinically useful when higher-quality data isn't available. One counter-intuitive finding from the literature is that SCD may be less effective for patients who have already had bowel resections. The remaining intestine can compensate for malabsorption to some degree, but the diet's restrictions don't account for the anatomical changes that come with surgery. I've seen post-surgical patients struggle more with SCD than with the low-residue diets traditionally recommended after colectomy. The issue isn't the diet itself but the mismatch between the protocol and the patient's actual digestive capacity.
Common Pitfalls and Edge Cases
Reading labels is where most people fail on SCD. Hidden sugars appear in unexpected places: salad dressings, spices, processed meats, and even some "healthy" snack bars. A single serving of something labeled "natural" can contain maltodextrin or modified food starch, both of which are prohibited on strict SCD. I recommend patients keep a master list of approved brands and products and stick to them religiously rather than trying to evaluate every new item they encounter. Social isolation is a real and often underestimated side effect of long-term SCD adherence. Eating out becomes nearly impossible, and family gatherings or workplace events require advance planning that most people aren't willing to do consistently. I've had patients abandon the diet not because it didn't work medically but because the social cost became unbearable. This isn't a failure of the diet; it's a failure of the support system around the patient. Another edge case involves patients with concurrent carbohydrate malabsorption issues like SIBO. The SCD diet can actually worsen symptoms in some of these patients because the restrictions eliminate many fermentable fibers that would normally support a balanced microbiome. If a patient isn't responding to SCD after eight to twelve weeks, I'd recommend testing for SIBO and small intestinal bacterial overgrowth before concluding the diet isn't working for their condition.
Practical Implementation Tips
Start with a thorough kitchen purge. Remove all prohibited foods from your home so you're not constantly making decisions about what you can and cannot eat. Decision fatigue is real, and every time you see a box of pasta in the cupboard, you're wasting mental energy resisting it. Stock up on approved staples: rice made from coconut or almond flour, honey, olive oil, ground meats, and a variety of vegetables you can rotate through meals. Meal prep is non-negotiable. Without it, you'll end up eating foods you haven't properly evaluated or skipping meals entirely, which destabilizes blood sugar and gut motility. I suggest spending two to three hours on Sunday preparing proteins and chopping vegetables for the week ahead. It sounds tedious, but it reduces the daily time commitment to about fifteen minutes per meal for reheating and assembly. Supplementation should be part of the protocol from day one, not an afterthought. A quality multivitamin, vitamin D3, calcium citrate, and an omega-3 supplement will cover most of the nutritional gaps. B12 is particularly important for patients who've avoided dairy and meat alternatives that are typically fortified. Blood work every three to six months will catch deficiencies before they become symptomatic.
When SCD Is Not the Right Choice
The diet is contraindicated for patients with a history of eating disorders, particularly restrictive types, because the severity of the restrictions can trigger or exacerbate disordered eating patterns. I've encountered this situation multiple times, and it's one of the reasons I screen for eating disorder history before recommending SCD to anyone. Pregnant and breastfeeding patients also need special consideration. The caloric and nutrient demands of pregnancy make the already-restrictive SCD protocol even more challenging to maintain without careful planning. Some patients manage it successfully, but the margin for error is smaller, and deficiencies can affect both mother and child. For patients with mild ulcerative colitis or irritable bowel syndrome without active inflammation, SCD may be unnecessarily restrictive. The Low FODMAP diet is a better first-line dietary intervention for IBS because it's less severe and has stronger evidence for symptom reduction in functional gut disorders. SCD's elimination phase is more comprehensive, but that comprehensiveness comes at a cost that many patients don't need to pay.
The bottom line is that SCD is a legitimate therapeutic tool for certain gastrointestinal conditions, particularly Crohn's disease and some forms of ulcerative colitis, but it's not a panacea and it's not suitable for everyone. The evidence supports its use in specific populations, the risks are manageable with proper monitoring, and the social and practical demands are significant enough that patient commitment is a prerequisite for success. If you're considering this diet, work with a gastroenterologist and a registered dietitian who understands the protocol rather than attempting it entirely on your own.



