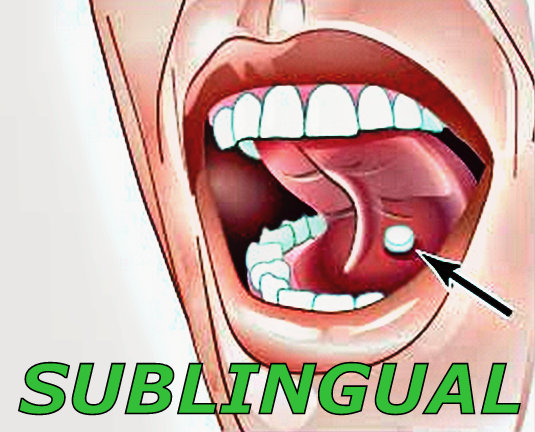
Sublingual Absorption Isn't Something You Learn In Intro Pharmacology And Then Forget
I spent years watching people swallow everything and wonder why their electrolyte protocols were inconsistent. Most of us learned about first-pass metabolism in college and moved on, but the gap between theory and what actually hits your bloodstream is where this topic lives. Sublingual delivery bypasses the hepatic portal system entirely. The mucous membranes under the tongue have a rich capillary network that empties straight into the superior vena cava. What you put there goes systemic within minutes, not hours. Salt under the tongue works differently than salt on your food. When you dissolve sodium chloride — or more usefully, a combination of sodium, potassium, and magnesium salts — beneath your tongue, the ions cross the mucosal barrier directly. This matters most in two specific scenarios: acute electrolyte depletion during endurance efforts and morning cortisol management for people who struggle with blood sugar crashes.
Salt Under The Tongue The Critical Role Of Sublingual Exposure In Health And Performance
Here is the practical breakdown of how to actually use this, because the instructions you find online are usually either dangerously vague or sold by people who've never had to deal with the side effects. You need a fine-grain salt, preferably unrefined with trace minerals. table salt will still work for sodium delivery but you're missing the co-transported minerals that make sublingual absorption smoother. Put roughly one sixteenth to one eighth of a teaspoon under your tongue. Let it sit. Don't swallow it immediately. You want it dissolved and absorbed over at least sixty to ninety seconds. If you swallow it within ten seconds, you've just made yourself drink salty water and you might as well have done that from a glass. The taste is unpleasant. It is supposed to be. The sharp saltiness triggers salivary gland activation, which increases blood flow to the sublingual area and actually improves absorption rates. This is not a side effect to avoid. It is part of the mechanism.
What Actually Works And What Doesn't
During a hard effort — let's say a ninety-minute ride or a long hike in heat — placing salt under the tongue every twenty to thirty minutes can blunt the creeping onset of hyponatremia symptoms: headaches, nausea, brain fog, that heavy feeling in your limbs. Most people wait until they feel terrible before reaching for salt. By then you're already behind. The difference between placing salt preemptively and reactively is noticeable within the same session. For morning use, the same approach under the tongue about ten minutes before coffee can stabilize blood sugar response in people who are insulin resistant or running on overnight depleted glycogen stores. I found this out accidentally when I started using it during a period of high training load and low calories. The fatigue that used to hit me around 10:30 AM stopped. Not completely. But enough to matter.
Get the Full Details

A Problem I Ran Into
Early on I was using coarse pink salt granules and getting burning sensations along the lateral borders of my tongue. Turns out the crystalline edges were causing micro-abrasions on the delicate mucosa. Once I switched to a fin milled Himalayan salt that dissolves faster, the irritation went away completely. The tradeoff is that fine salt disappears into your saliva quicker, so you have to be more deliberate about holding it under the tongue long enough. I started using a on my phone for the first few weeks until the habit locked in. Ninety seconds, no swallowing, just let it sit and dissolve. Another thing nobody mentions: if you've recently brushed your teeth, the residual mint oils and surfactants in toothpaste can interfere with mucosal absorption. The sublingual membrane gets coated and permeability drops. Wait at least thirty minutes after brushing before doing sublingual salt, or skip it that morning and just take your electrolytes orally with a proper meal.
Limitations
Sublingual salt is not a cure-all. It does not replace oral rehydration when you are genuinely dehydrated. If you are vomiting, severely depleted, or dealing with a medical electrolyte disturbance, you need clinical-grade rehydration with balanced fluids and possibly medical supervision. Salt under the tongue is a maintenance and performance tool, not an intervention for acute pathology. It also does not work well for large doses. The sublingual mucosa can only absorb so much before the excess just rolls down your throat. If your protocol calls for five hundred milligrams of sodium or more, take it orally with water. Save the sublingual route for smaller, targeted doses where the speed and first-pass avoidance actually matter. People with certain oral conditions — lichen planus, severe dry mouth from medications, recent dental surgery — should avoid sublingual salt entirely. The mucosal surface needs to be intact for this to work safely and effectively. If your mouth is irritated for any reason, skip it.
What To Buy
You don't need anything expensive. A two-dollar jar of fine milled Himalayan pink salt from the grocery store works fine. If you want to step up, look for brands that sell pre-measured sublingual electrolyte tablets with sodium, potassium, and magnesium in roughly a 2:1:0.5 ratio. These dissolve faster and give you consistent dosing. The cost is higher but the consistency removes the guesswork. Whatever you use, check the ingredient list. Some sublingual salt products contain fillers like dicalcium phosphate or silicon dioxide that leave a gritty residue and slow dissolution. Those are added for manufacturing reasons, not performance reasons. You are better off with a single ingredient salt and a stopwatch.

The Bottom Line
Sublingual salt exposure is a straightforward mechanism with real physiological backing. It is underutilized because it is simple and because the people who understand it tend to sell complicated versions of it. The actual practice is nearly trivial. Fine salt under the tongue, hold it for ninety seconds, don't swallow early, don't do it right after brushing your teeth, and don't expect it to fix problems that require clinical intervention. That is it.