How The Rule Of Nines Actually Works In A Burn Bay
I have spent more years than I care to count watching clinicians estimate burn surface area under chaotic conditions. The Rule Of 9s Burns The Lifesaving Framework That Defines Critical Care, but not in the way most textbooks present it. It is a quick estimation tool, not a precision instrument, and treating it like one has cost patients fluid resuscitation adjustments more times than I can count. Here is the practical reality of how the rule functions and where it breaks down on the floor.
Rule Of 9s Burns The Lifesaving Framework That Defines Critical Care
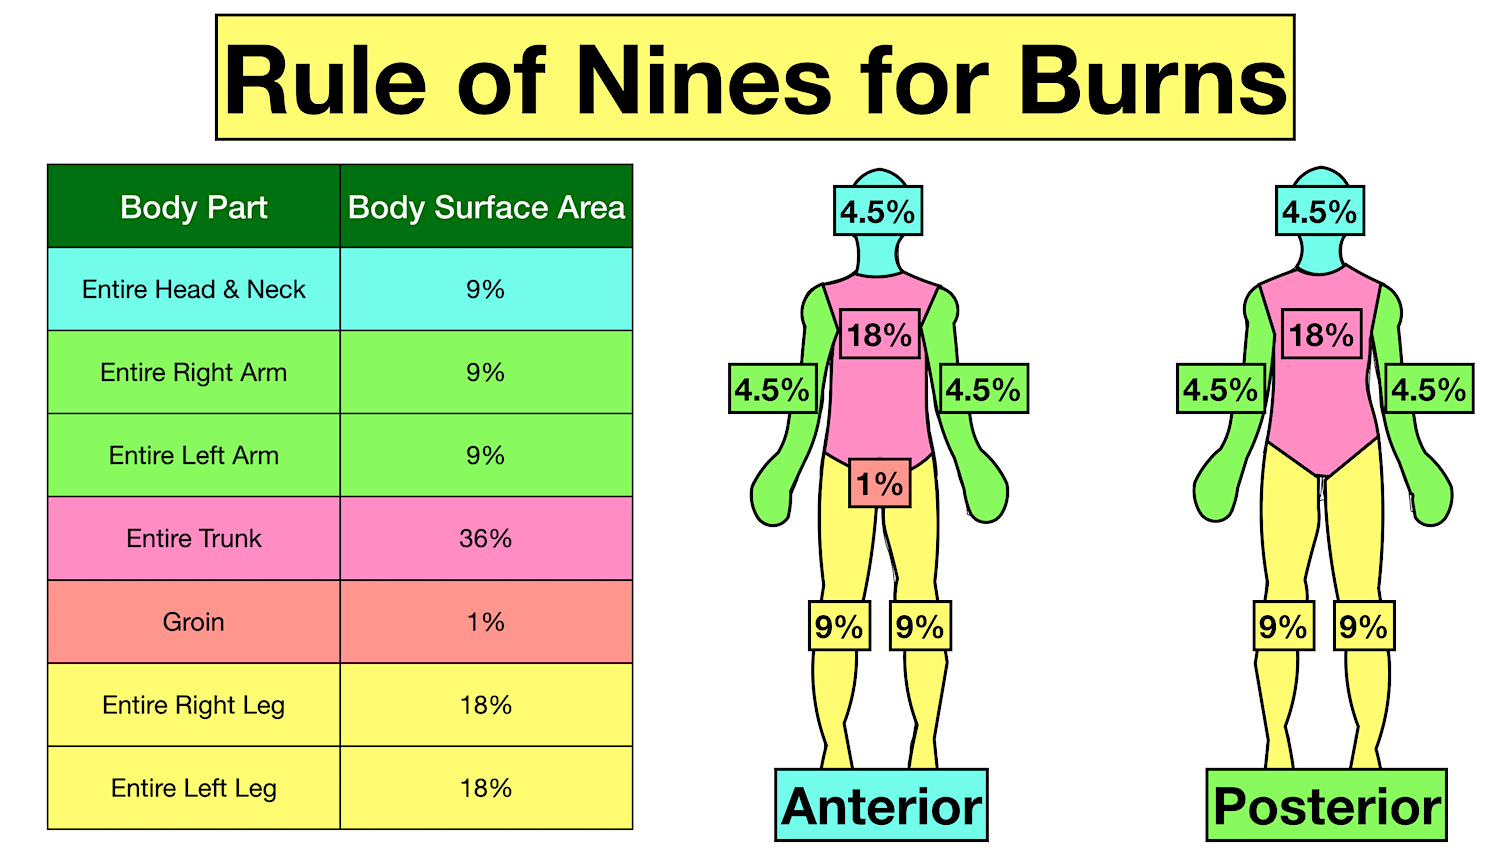
The core concept is simple enough that you learn it in week one of medical training. The adult body gets partitioned into segments, each assigned a percentage value based on the total body surface area. Anterior trunk is 18 percent. Posterior trunk is 18 percent. Each entire arm is 9 percent. Each entire leg is 18 percent. The head and neck together account for 9 percent. The perineum is 1 percent. That 1 percent is there because leaving it at zero introduces small but consistent error in large burn calculations. The formula most people actually use for fluid resuscitation after that estimation is the Parkland equation: four milliliters of lactated Ringer's per kilogram of body weight per percent of total body surface area burned, given over the first twenty-four hours. Half of that volume goes in during the first eight hours from the time of burn injury, not from the time of arrival. This timing detail matters enormously. I watched a resident calculate the entire Parkland volume before realizing they had been measuring from admission instead of from injury, which put the patient at risk of fluid overload in the early phase and under-resuscitation later. Pediatric patients do not follow the same percentages. Their heads are proportionally larger and their legs smaller. The modified Lund-Browder chart is the standard adjustment here, and if you are still using the adult rule of nines on a child over twelve kilograms without modification, your TBSA estimate will be systematically wrong.
The Work In Practice And The Problems You Will Hit
Estimating burns with the rule of nines on paper is straightforward. Estimating them on a real patient who is agitated, bleeding, and covered in debris is different. The anterior surface of a leg is roughly 9 percent and the posterior surface is another 9 percent. That sounds clean until you realize the patient has a circumferential burn around the entire thigh and your mental model of "front and back" no longer applies cleanly. You have to approximate anyway, and approximation is the whole point of this rule. I ran into a specific problem last year that I still think about. A construction worker came in with partial-thickness burns across his right arm from wrist to shoulder, his anterior and posterior trunk, and the dorsum of his left foot. The rule of nines would assign the entire right arm as 9 percent, the anterior trunk as 18 percent, and roughly 1 percent for the foot. That gave a rough TBSA of around 28 percent. But the burn on his right arm was not uniform. The volar forearm was deeply involved while the dorsal aspect was only erythematous. Using the full 9 percent for the arm overestimated the actual burn by maybe 3 to 4 percent. Over a 90-kilogram patient, that translates to roughly 1.2 liters of additional fluid that may or may not have been necessary in the first eight hours. The workaround I used was to apply the rule of palm as a secondary check. The patient's own palmar surface, including fingers, represents approximately 1 percent of their total body surface area. I mapped the non-uniform areas against that reference and adjusted the estimate downward before locking in the Parkland calculation. It added maybe ninety seconds to the assessment and probably prevented a fluid creep situation later.
Get the Full Details

Where The Rule Fails Completely
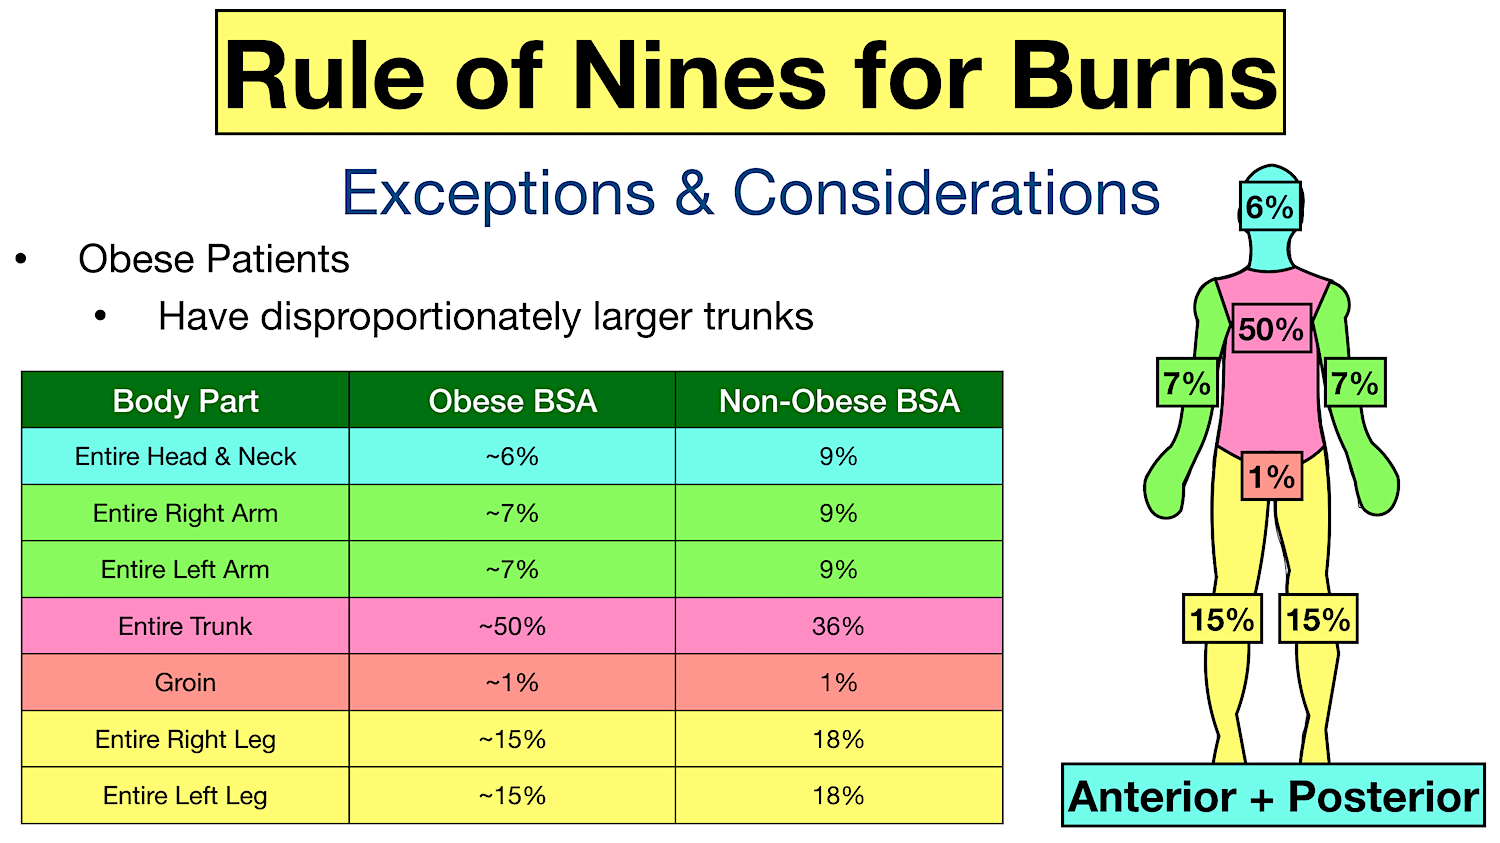
There are scenarios where the rule of nines is simply not useful and relying on it alone is dangerous. Irregularly shaped burns scattered across multiple body regions do not conform to clean anatomical zones. A patient who fell onto a hot surface and sustained splash-type burns along the lateral chest, the anterior neck, and the upper inner thighs will not yield a clean estimate from this method. The Lund-Browder chart is better for scattered burns because it uses detailed segmental diagrams. Another failure mode is obese patients, where anatomical landmarks shift and surface area distributions do not match the standard percentages. The rule also does not account for age-related changes beyond the pediatric modification, so elderly patients with significant sarcopenia and skin changes carry the same estimation error risk. If you are managing burns in a resource-limited setting where Lund-Browder charts are not available, the Wallace diagram or even a quick hand-reference method is an acceptable fallback. The goal is always reasonable estimation, not false precision.
What You Actually Need To Know Beyond The Percentages
Most people memorize the percentages and stop there. The things that actually matter clinically are much less obvious. The first is depth. The rule of nines estimates surface area only. It says nothing about how deep the burn is. A superficial burn covering 20 percent is a very different clinical picture from a full-thickness burn covering 20 percent. Depth determines whether the patient needs surgical intervention, fluid management intensity, and transfer decisions. Do not let the percentage estimate create a false sense of completeness. The second thing is inhalation injury. A patient with 15 percent TBSA burns and significant inhalation injury may require substantially more fluid than the Parkland equation predicts in the first twenty-four hours. Airway edema from inhalation injury drives capillary leak independently of the skin burn surface area. I have seen patients whose calculated Parkland volume looked adequate on paper but who developed respiratory compromise and hemodynamic instability within hours because nobody factored in the inhalation component. Third, the rule of nines gives you a starting point for resuscitation. It does not tell you when to stop or adjust. The modern approach uses dynamic monitoring: urine output targeting 0.5 milliliters per kilogram per hour in adults, heart rate, blood pressure, mental status, and base deficit. If your patient is burning at 35 percent TBSA and your initial Parkland infusion is making their urine output climb to 1.5 milliliters per kilogram per hour, you are over-resuscitating regardless of what the formula said. Fluid creep is real and it causes abdominal compartment syndrome, respiratory failure, and worse outcomes. The formula is a starting dose, not a prescription.
Fourth, electrical burns are almost impossible to estimate accurately with surface rules. The external burn may look small, but the current path through tissue can cause extensive deep damage that is invisible externally. A 5 percent external burn from a high-voltage accident may conceal compartment syndrome in the arm or leg. You need a low threshold for fasciotomy assessment and serial compartment pressure measurements in these cases. Fifth, chemical burns continue to cause damage until the agent is fully removed. Washing takes priority over estimation. I had a patient where we spent the first twenty minutes irrigating hydrofluoric acid exposure before we ever pulled out a worksheet. The burn kept progressing during that time, and by the time we estimated, the TBSA was already higher than it would have been with immediate decontamination.
Quick Reference For The Adult Rule Of Nines
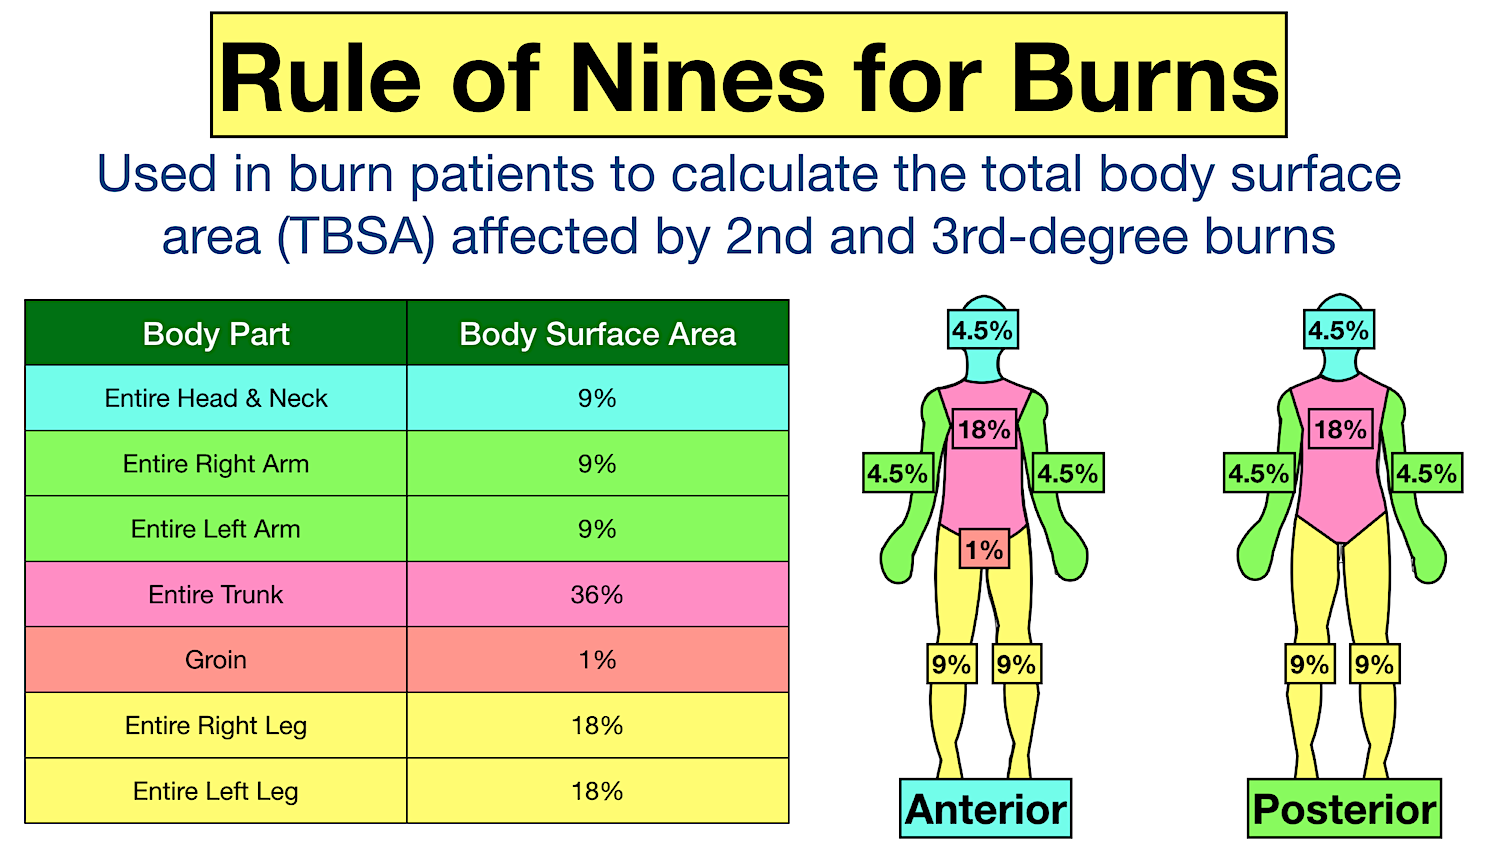
Head and neck: 9 percent total, divided into anterior and posterior. Each entire arm: 9 percent. Anterior trunk: 18 percent. Posterior trunk: 18 percent. Each entire leg: 18 percent, with anterior and posterior each contributing roughly half. Genitalia and perineum: 1 percent. These values are for adults. Pediatric values differ significantly and require the modified Lund-Browder chart for accuracy. The rule of nines remains one of the most widely taught and used tools in burn care because it is fast and requires no special equipment. It is also imprecise by design. The clinical value comes from using it as an initial estimate, checking it against other methods when possible, adjusting for patient-specific factors, and then pivoting to physiologic endpoints for ongoing management. Anything less turns a lifesaving framework into a number on a chart that does not reflect what the patient actually needs.