How We Got Here With Baseline Suppression
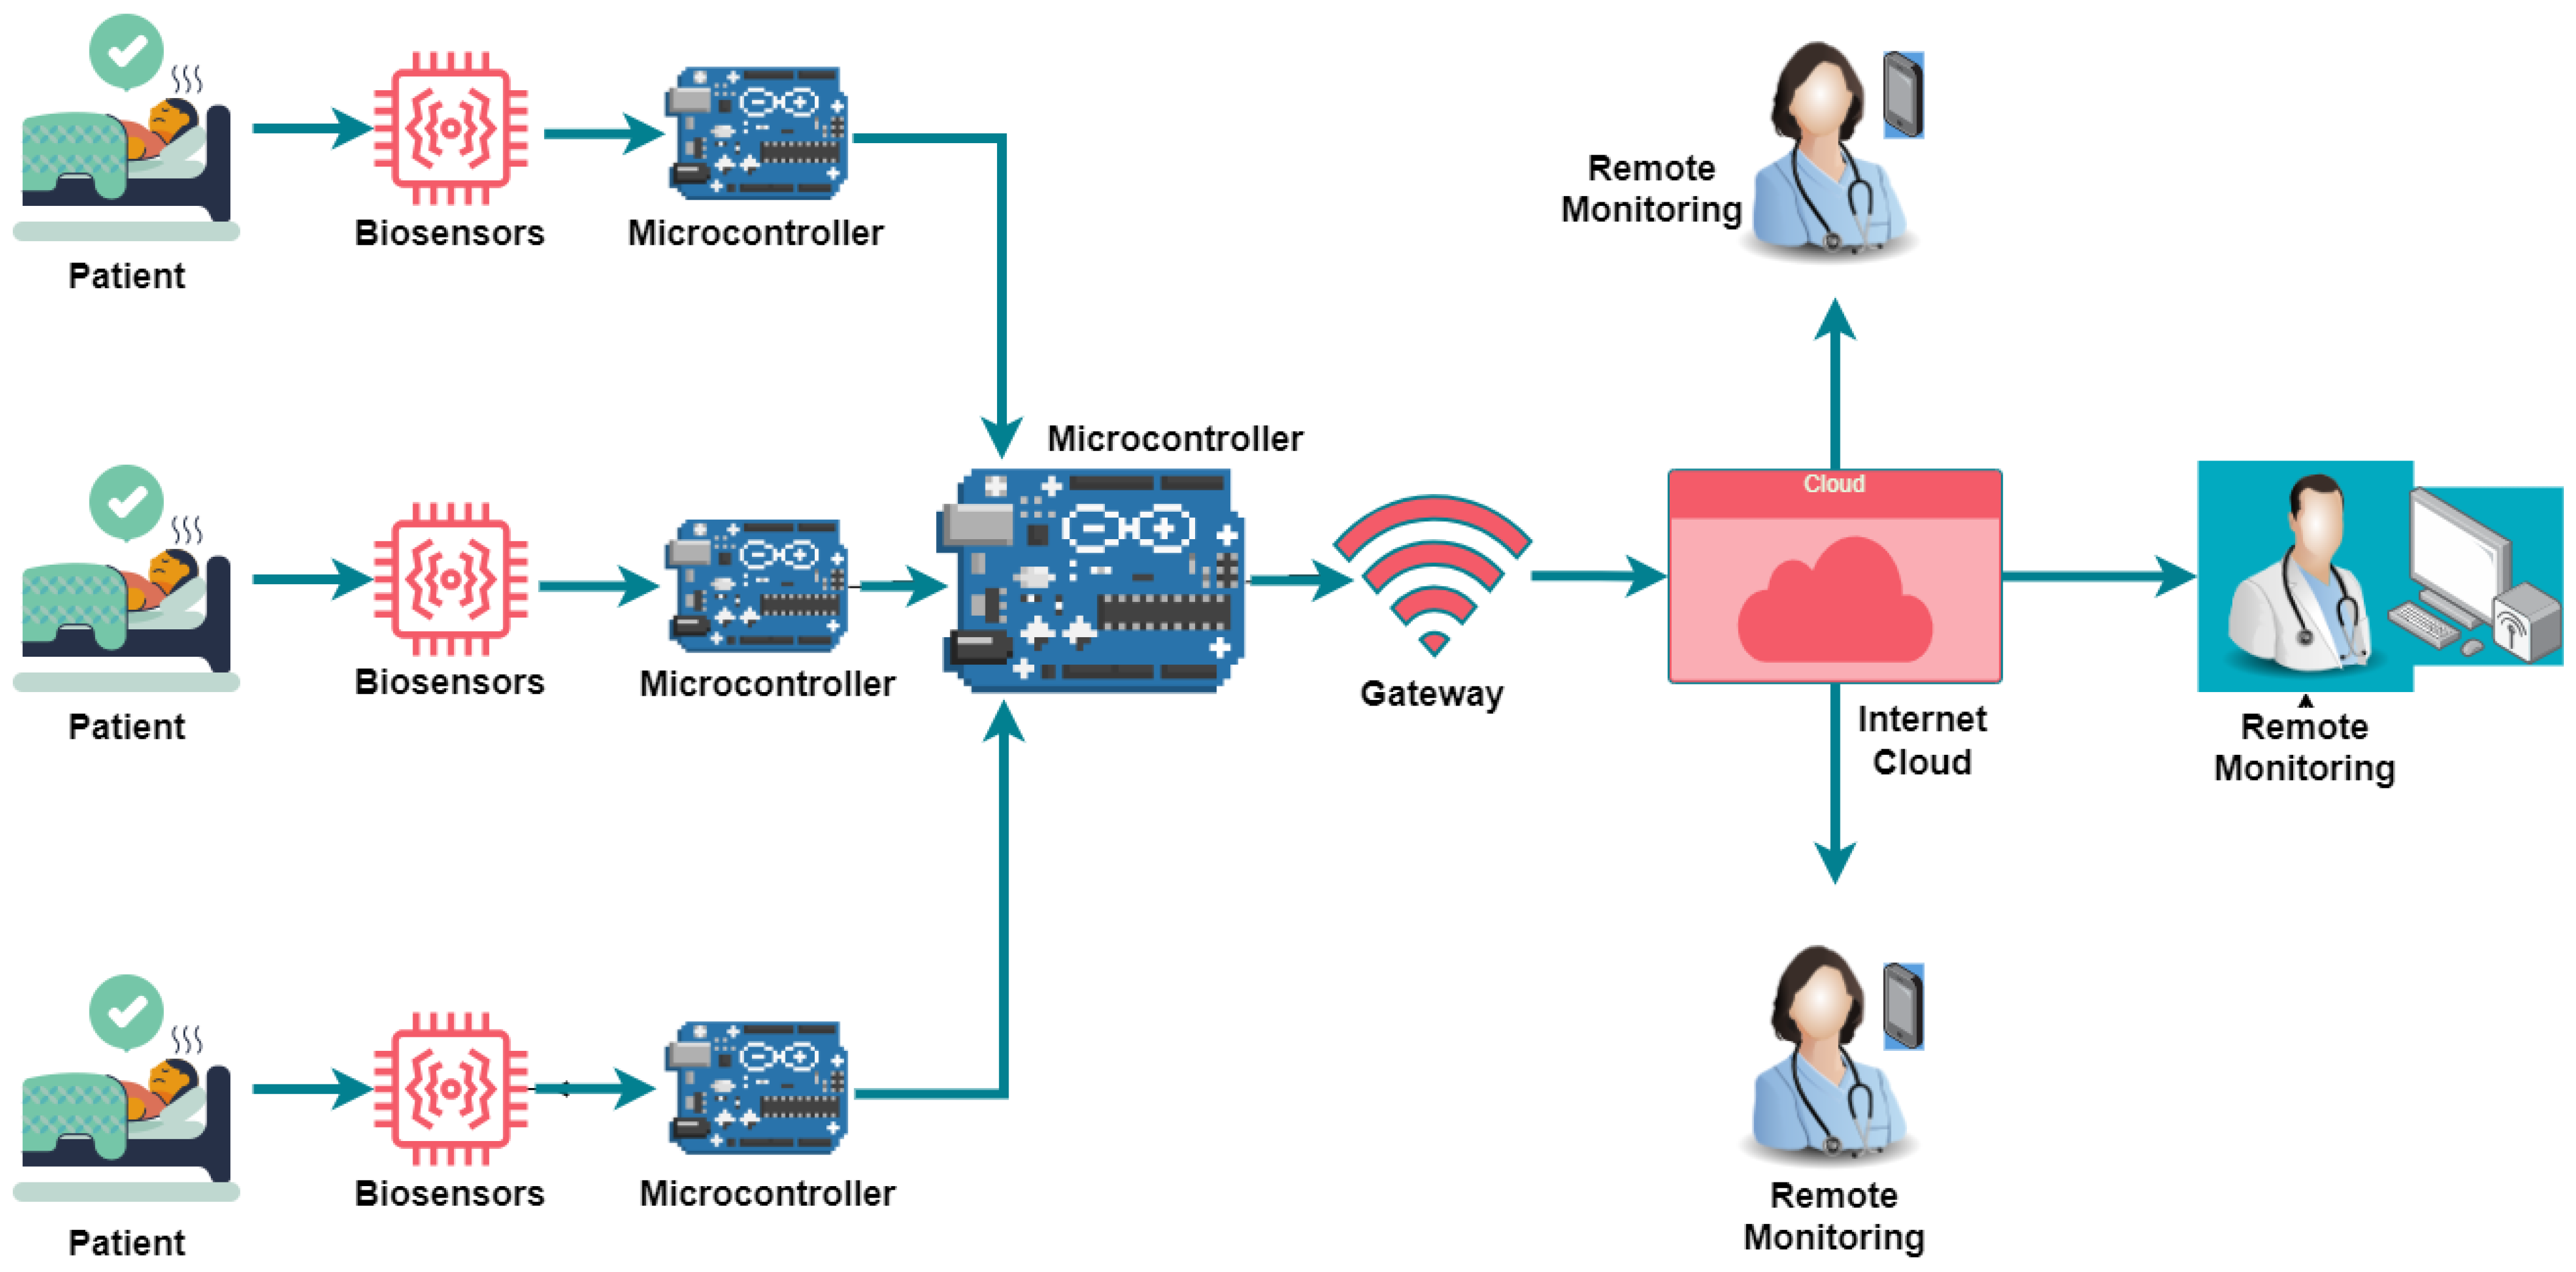
Three years ago I was troubleshooting a patient monitoring system at a regional hospital and noticed something odd. The heart rate traces would look completely normal for hours, then spike into arrhythmia territory, and the alarms never fired. The monitor wasn't broken. It was suppressing the critical baseline and treating the suppression as valid data. That was the moment I realized most people working in clinical monitoring don't understand what's actually happening underneath the waveform display. At its core, the mechanism works by establishing a rolling statistical baseline from recent patient vitals. When a reading deviates beyond a configured threshold, the algorithm flags it for suppression rather than alarm activation. This isn't inherently bad. In a noisy ICU environment with motion artifacts and electrode shifts, constant false alarms desensitize nurses to the point where real emergencies get ignored. The Suppress Critical Baseline function exists to reduce alarm fatigue, which is a documented problem affecting thousands of clinicians daily. The problem emerges when the baseline itself becomes pathological. I saw this firsthand with a post-surgical patient whose blood pressure gradually declined from 110 over 70 down to 85 over 55 over six hours. The monitor was logging that drop perfectly. But because each hourly reading was still within the individually configured "normal" window for that patient, the cumulative trend was being suppressed. The alarm threshold had been set based on the initial reading, not the trending trajectory. By the time I noticed the flatline-style stability on the chart, the patient was already in compensated shock.
Configuring the System Properly
The setup process starts in the monitor's clinical configuration menu, which varies slightly between manufacturers but follows the same general structure. You need to access the alarm settings, locate the suppression parameters, and adjust both the baseline window width and the suppression delay timer. Most systems default to a five-minute baseline window with a thirty-second suppression delay. Those defaults are fine for general ward monitoring but insufficient for ICU or step-down units where trends matter more than single readings. For critical care environments I recommend setting the baseline window to three minutes and the suppression delay to ten seconds. This creates a tighter feedback loop while still filtering out transient artifacts. You also need to enable trend-based alarm escalation, which most monitors have but nobody configures. Without it, a suppressed reading stays suppressed indefinitely even as the underlying condition worsens. The trend escalation feature adds a secondary layer that overrides suppression when a directional pattern is detected across multiple data points. I've found that adjusting the sensitivity parameter separately from the suppression threshold gives you better control. The sensitivity value determines how much deviation triggers a flag. The suppression threshold determines whether a flagged reading gets silenced. Running both at high values simultaneously creates a dangerous blind spot where significant physiological changes slip through without any alert. Set sensitivity to medium and suppression threshold to low, then tune from there based on your patient population.
Edge Cases and Workarounds
Here is a scenario that nearly caused an adverse event in my unit. A patient on continuous renal replacement therapy had their potassium levels monitored through the central system. The lab values came back intermittent, every two hours instead of every hour as ordered. The monitor was suppressing the gaps between values and displaying a smooth interpolated line that looked stable. The attending physician reviewed the chart and saw normal potassium throughout. The actual lab results showed dangerous swings between 3.1 and 6.8 that the suppression algorithm had smoothed over completely. The workaround was straightforward once I understood the root cause. I disabled the interpolation feature in the monitor's data logging settings and switched to a gap notification protocol. When a reading is missed beyond a configurable time threshold, the system now generates a data integrity alert instead of silently filling the space with estimated values. This adds roughly twelve alerts per shift per patient, which is annoying but prevents the kind of clinical blindness I described. You can also export raw uninterpolated data from the monitor's service menu for audit purposes. Another issue I encounter regularly involves wearable pulse oximeters used during transport. These devices establish their own baseline independently of the central monitor. When a patient moves from bed to stretcher to ambulance, the wearable recalibrates its suppression algorithm to the transport conditions. Upon return to the room, the central system and the wearable are operating on different baseline assumptions. This mismatch can cause the central alarm to fire on legitimate readings or fail to fire on actual abnormalities. The fix is to manually reset the baseline on both devices whenever the patient transitions between monitoring environments.
Get the Full Details

What This System Cannot Do
Suppression algorithms cannot distinguish between artifact and genuine physiology. They can only identify statistical outliers and decide whether to flag them. If a patient's vital signs legitimately shift into a new stable range, the algorithm will eventually adapt and suppress alarms for what were previously critical deviations. This is by design but it means the baseline is always lagging behind the patient's current state. In conditions like sepsis, where hemodynamic parameters change rapidly over hours, the suppression lag can span the entire critical window. Additionally, the system performs poorly with patients who have chronic conditions affecting their baseline. A patient with long-standing hypertension may have a "normal" baseline of 160 over 95 according to historical data. When that patient presents with a systolic drop to 110, the suppression algorithm may treat it as noise rather than a significant event. There is no automatic way to account for this without manually adjusting the baseline reference point, which most nurses don't have time to do during a busy shift. If your unit relies heavily on automated suppression without periodic manual review, you should implement a daily chart audit. Review the previous twenty-four hours of alarm logs and compare them against nursing notes and physician assessments. Discrepancies between what the monitor suppressed and what the clinical team documented are the earliest warning sign that your suppression parameters need adjustment. This audit typically takes about twenty minutes per nurse per shift and catches the majority of problematic suppressions before they become patient safety issues.
Implementation Checklist
Before deploying this configuration across your unit, verify the following. Confirm that trend escalation is enabled on every monitor. Test the interpolation override with a simulated gap in data feed. Calibrate all wearable devices against the central monitor simultaneously. Document your suppression parameter values in the unit protocol binder. Train nursing staff to recognize when suppression may be masking a developing condition. Schedule the first chart audit within one week of go-live. The technology behind realtime patient monitoring has improved significantly over the past decade. Baseline suppression is one of those improvements that solves one problem while introducing another. Understanding both sides of that tradeoff is what separates competent monitoring from negligent monitoring. The difference between a system that keeps patients safe and one that quietly fails them often comes down to whether someone on staff actually understands what the suppression algorithm is doing and when to override it.