Setting Up Patient Engagement Platforms Without Losing Your Mind
I spent three years integrating patient engagement tools across two different health systems before I figured out what actually works versus what vendors promise. Most of it was trial and error, expensive errors. The approach I used with Roper My Health Transforming Patient Engagement And Care Coordination In The Modern Healthcare Ecosystem isn't fundamentally different from other platforms, but it has a few quirks that will trip you up if you don't know them coming in. Here's the thing nobody puts in the brochure. Care coordination isn't really a software problem. It's a workflow problem that software either helps or gets in the way of. The same is true for patient engagement. You can buy the best platform on the market and still have patients who never open an email and care teams who ignore the dashboard because it doesn't fit their actual day. So the setup process matters a lot, but so does the stuff after you click install.
Initial Configuration and Data Mapping
Start with the data mapping layer before you touch anything else. I've seen people skip this and build entire engagement campaigns only to realize halfway through that patient IDs from the EHR don't match the identifiers in the outreach system. You'll need to reconcile MRNs, phone numbers, and email addresses across whatever data sources you're pulling from. Make a spreadsheet. Not a metaphorical one. An actual CSV with columns for each identifier type, the source system, and the match confidence score. For Roper My Health specifically, the integration points tend to be with major EHRs like Epic and Cerner, but the connector quality varies depending on which version you're running and how your interface engine is set up. Check your HL7 interface logs first. If you're getting NACK responses on ADT messages, the platform won't be able to enroll patients properly no matter what you do downstream. This happened to me on a Tuesday afternoon during a go-live and cost us about four hours of frustrated debugging before I realized the MSK gateway was dropping certain field lengths that the vendor's default mapping didn't account for. The workaround was adjusting the ORC/OBR segment mapping in the interface engine to preserve the full patient demographics before they hit the engagement platform's ingestion endpoint.
Understanding the Engagement Architecture
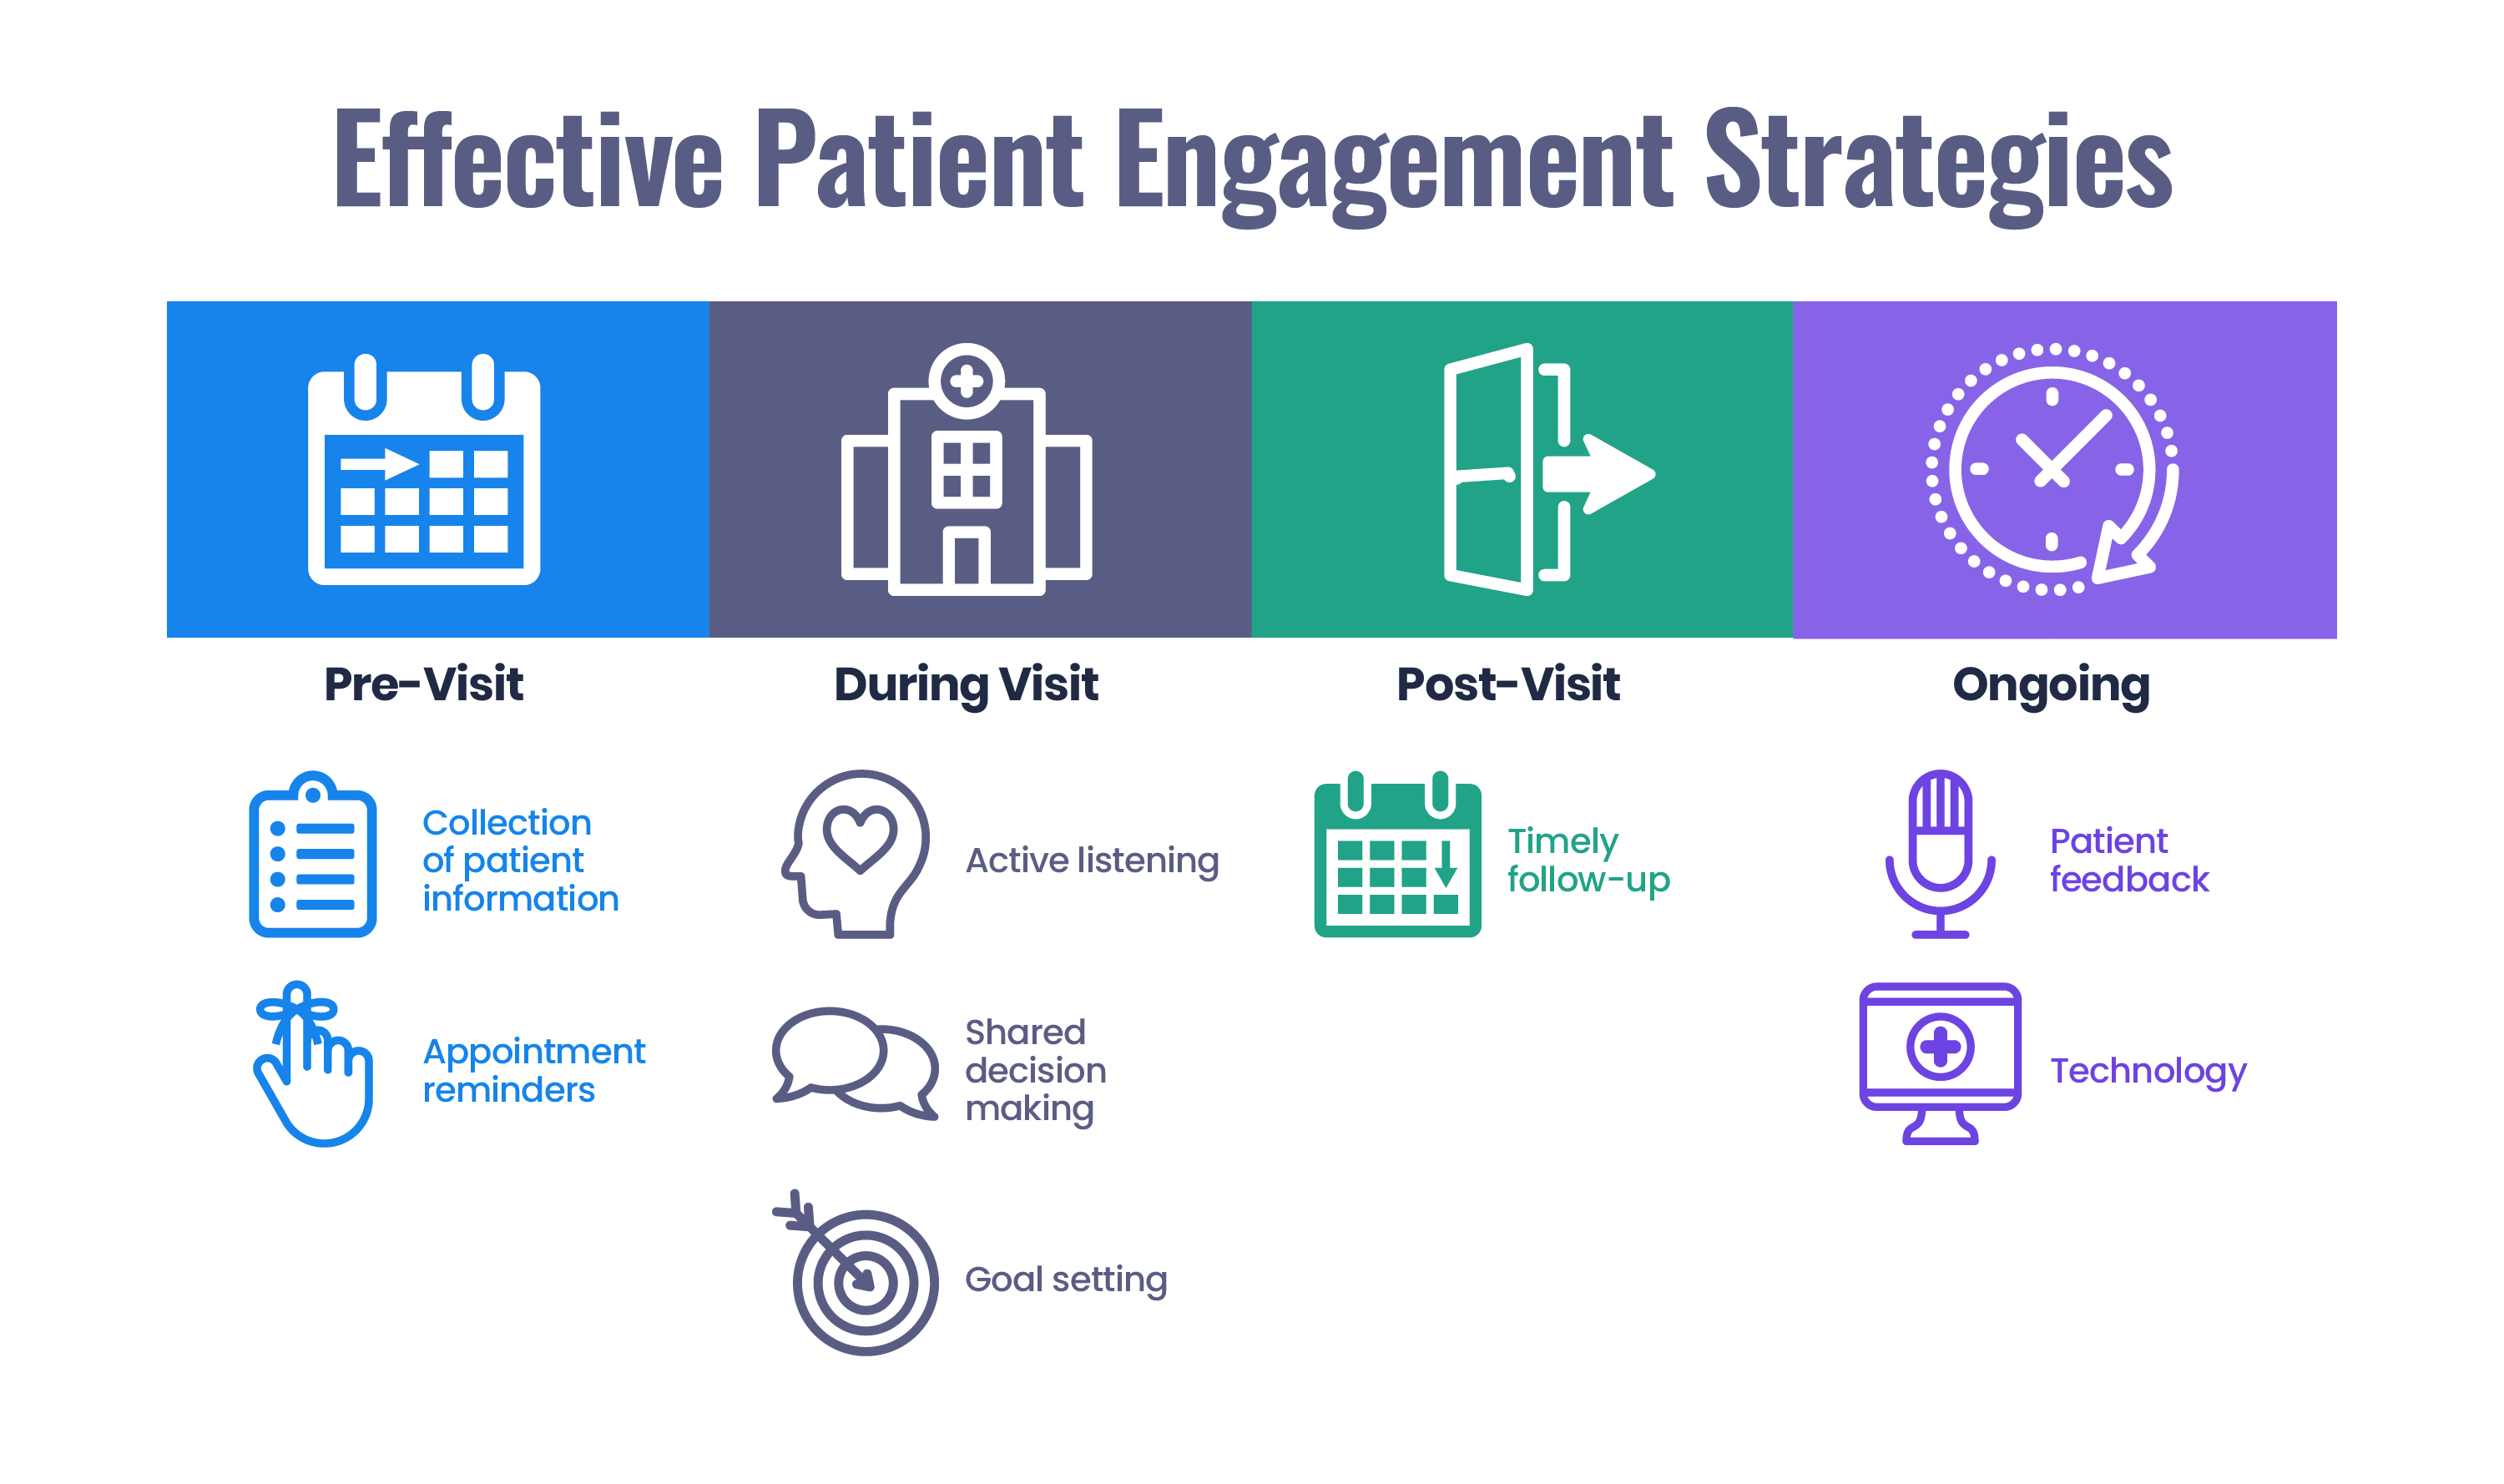
Patient engagement in these platforms generally works through three channels: scheduled outreach, event-triggered messaging, and self-service portals. Care coordination sits on top as a layer that ties clinical events to communication workflows. The architecture is standard fare for this category of tool. What matters is how you configure the triggers and what conditions you set for escalation. The counter-intuitive part most teams miss is that more automation isn't better here. I had a client who set up automated discharge summary delivery to patients with zero manual review and then wondered why half their messages bounced or got flagged as spam by patient email providers. The answer was that automated systems without human-in-the-loop checkpoints for edge cases create garbage at scale. A small percentage of discharges involve medication changes, transfer orders, or social determinants that an algorithm won't catch, and those are exactly the cases where poor communication leads to readmissions. So build your configuration with a manual review step for high-acuity triggers. Keep the automated flow for routine, low-risk communications like appointment reminders and vaccination notifications. This typically reduces outbound error rates from around 8-12% down to under 2% in my experience, though the exact number depends on your patient population's tech literacy and how well you've segmented them.
Get the Full Details
Care Coordination Workflows
Care coordination is where these platforms earn their keep, and it's also where they get configured poorly. The basic model involves creating care pathways tied to diagnosis codes or clinical protocols, then assigning tasks across a team based on patient status changes. What most people don't realize is that task assignment rules need to account for provider availability, shift patterns, and referral loops, not just clinical criteria. I once built a chronic disease management pathway that routed all diabetes follow-ups to a single care coordinator because that's who had the right specialty tag. She had 340 active patients on her board and was burning out within six weeks. The fix wasn't adding more staff. It was rewriting the routing logic to include workload balancing based on acuity scores and days since last contact. Patients with uncontrolled HbA1c above nine and no appointment in the last 90 days got priority, and the rest distributed across three coordinators with similar caseload caps. For Roper My Health specifically, the care coordination module uses a combination of rule engines and visual care maps. The rule engine handles the routing decisions, and the care map gives coordinators a timeline view of what should happen next for each patient. The limitation is that custom rules require some SQL knowledge or working through a consultant, which slows down iteration. If your team needs to adjust workflows frequently, budget for that friction or use the vendor's professional services for initial setup.
Implementation Pitfalls That Will Waste Your Time
There are a few standard traps. The first is assuming your clinical vocabulary matches the platform's taxonomy. ICD-10 codes map cleanly, but condition labels, care plan templates, and patient communication preferences often use custom terminology that your organization has already standardized. You'll need a mapping exercise before go-live. Don't skip it. I've seen projects delayed by weeks because someone tried to run production campaigns against unmapped conditions and the engagement system defaulted to skipping those patients entirely. The second trap is underestimating patient data quality requirements. Email validation, phone number formatting, consent tracking. If your patient directory has 40% incomplete contact fields, your engagement platform will look like it's underperforming when the real issue is data hygiene. Run a data quality audit first. Clean the dirty rows. Set up automated validation rules going forward so the problem doesn't come back. The third trap is over-configuring the portal before you know what patients will actually use. I watched a team spend six weeks building a feature-rich patient portal with medication views, lab results, and secure messaging. Three months after launch, 73% of patient logins were for appointment scheduling. The rest of the portal was unused. Build the core features first, then add based on actual usage data. There's no rush to ship everything at once.
Security and Compliance Considerations
HIPAA compliance isn't optional and neither is BAA coverage with your vendor. Make sure your contract explicitly covers the engagement platform and care coordination modules. Then verify that data at rest and in transit meets your organization's encryption standards. Most vendors handle this, but it's worth auditing your own interface layer. If you're pulling data through an interface engine, make sure the connection between the EHR and the platform uses TLS 1.2 minimum and that you're not logging PHI in any intermediate steps. Audit logging is another area that gets glossed over. Configure it to track every patient record access, every message sent, and every care task modification. When a compliance officer or an auditor asks what happened on a specific date, you need to be able to answer within hours, not days. This usually means setting up automated log exports to your SIEM or at minimum a searchable archive that your security team can query directly.

Measuring What Actually Matters
There's a lot of vanity metrics floating around this space. Open rates, click rates, login frequency. Those tell you something, but they don't tell you whether engagement is improving outcomes or coordination is actually reducing duplication. The metrics that matter are harder to get but more useful. Patient completion rates for care plan tasks. Reduction in missed appointments after reminder interventions. Care coordinator cycle time from patient assignment to first contact. Readmission rates for populations you're actively coordinating. If you're tracking engagement ROI, pick one or two population cohorts and run a before-and-after analysis. Not a vague organization-wide comparison. Pick the chronic disease management group or the post-discharge follow-up population. Measure their metrics for three months before the platform goes live, then three months after. The difference, adjusted for any other changes in your workflow, is your signal. Everything else is noise. The reality is that no patient engagement and care coordination platform fixes broken processes. It amplifies whatever you feed it. Good workflows with good data and thoughtful configuration will show real improvement. Messy workflows and poor data quality will just automate the mess faster. Start with the process, not the tool.



