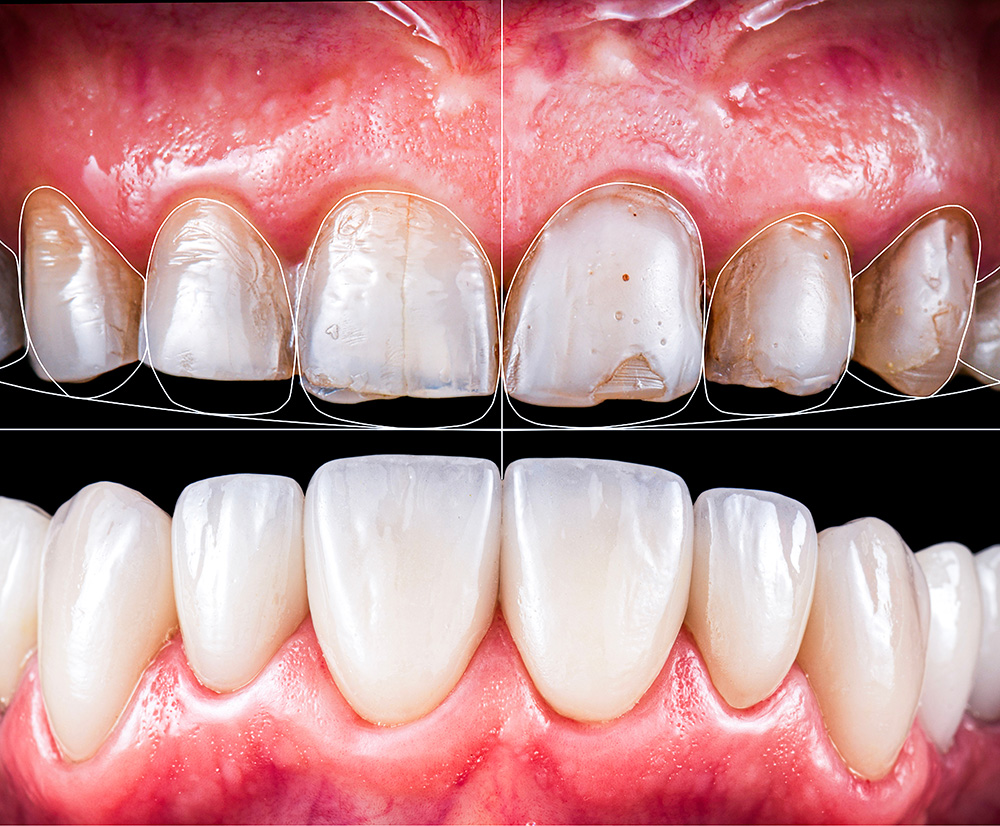
The Reality of Running a Digital Dental Lab Workflow
Most people entering digital dentistry think buying a scanner and a mill means they are set. It does not work that way. The gap between scanning a case and delivering a crown that fits is where the actual work happens. I have spent enough years watching labs fail at this part to know what usually goes wrong. The workflow starts before any software opens. You need an optical strategy. That means picking a scanner that actually matches your case mix. Full-arch implants require different camera parameters than single crown prep scans. If you run an intraoral scanner designed for general restorative cases on complex implant prosthetics, your margin capture will degrade. The software interpolates too much between points. You end up fabricating crowns that seat with visible gaps at the gingival junction. I learned this the hard way about three years ago. We took on a full-arch All-on-4 case with a referral dentist who had just bought a mid-range scanner. The scan looked clean on screen. I sent it to our CAD software and everything appeared normal during virtual wax-up. The milled framework tried a screw-retained bridge using zirconia. When the prosthetic arrived at the clinic, the passive fit test failed on two of the four abutment connections. The framework would rock. Adjusting it was not viable since the internal tolerances of zirconia do not allow for selective grinding without compromising structure.
The workaround involved going back to the clinical team and running a custom tray with registration putty. We had the dentist take a conventional bite registration using a dual-cure silicone material instead of trusting the scanner's default bite capture. We then used a separate scan body for the implant positions and merged that dataset into the original scan using a manual landmark match in the software. This took about 40 extra minutes of technician time but eliminated the interpolation error in the implant position data. The second framework seated passively on the first try. This kind of problem is common enough that it is worth documenting properly. Here is how the actual workflow should run when it is set up correctly.
Setting Up a Reliable Digital Workflow Step by Step
Start with hardware calibration. This is the part nobody mentions in marketing videos. Your scanner needs a daily calibration check using the manufacturer's verification artifact. If the artifact falls outside the specified tolerance, every scan from that day is suspect. Do not skip this. A scanner that has been bumped or dropped even slightly will introduce systematic errors that compound across multiple cases. Scanning protocol matters more than the brand of scanner you own. When scanning a prepared tooth, you need the proper scanning powder or use a wet-scanning mode if your device supports it. Dry enamel scatters light differently and creates noisy surface data. The powder fills micro-scratches and provides a consistent reflective surface. Without it, you get scattered point clouds around the margin area. This directly causes poor marginal fit on the final restoration. After scanning comes the export process. Most labs receive STL files. The problem is that STL is an approximation format. It uses triangles to represent curves, and the triangle count varies by manufacturer default settings. Always request files with a minimum vertex count or export at the highest resolution your scanning software allows. A low-resolution scan of a Class II preparation with a distal box will lose the internal line angles entirely. You cannot recover that data later.
Get the Full Details

The CAD phase is where digital workflows separate from analog ones. In traditional dentistry, a adjusts wax with his hands. In digital, the software makes those adjustments through Boolean operations and surface reconstruction. Understanding how your specific CAD platform handles free-form editing is critical. Some systems auto-generate occlusion based on a digital articulator setting. Others require manual interdigitation setup. Know which one you have and master its parameters before taking on complex cases. Milling or printing choices depend on the restoration type. Zirconia mills are the standard for posterior bridges and implant frameworks. Lithium disilicate works well for anterior crowns. For long-span fixed prosthetics, milled PMMA or PEEK blanks may be necessary. If you are doing Chairside same-day restorations with a milling unit in the office, the material selection shrinks significantly. You are limited to what fits in the mill's tool carousel and blank capacity. The sintering process for zirconia requires a programmed thermal curve. Rushing this step by shortening the cycle to save time will produce under-sintered blocks with reduced mechanical properties. The crown might look acceptable immediately after milling but will crack within months under functional load. Follow the manufacturer's sintering chart exactly. Do not eyeball the temperature or duration.
After sintering, the restoration goes through finishing and glazing. Automated polishing programs exist but they often leave the margin area unfinished because the brush cannot access it properly. Always verify margin integrity under magnification before glazing. A polished margin that is over-contoured will cause gingival inflammation. The patient will not complain about the polish. They will come back six months later with bleeding on probing.
Where Digital Workflows Actually Break Down
I need to be straightforward about the limitations because the industry sells this as a magic solution. It is not. The largest bottleneck is soft tissue management during scanning. If the gingiva is inflamed or swollen, the scanner cannot reliably capture the preparation margin. The software will either ignore the margin area or interpolate over it. Neither option produces a usable scan. You have to control the soft tissue first. Use a retraction cord or a hemostatic agent before scanning. This adds 5 to 10 minutes per case but prevents the entire workflow from failing downstream. Another failure point is improper file handoff between the dentist and the lab. Dentists often scan, export to STL, and email the file without checking the data quality. They do not know what to look for. The scan might appear complete on their screen but contain missing triangulation near the margin. When the lab receives it and tries to design the crown, the software throws errors or the margin geometry is incorrect. This wastes everyone's time. Require dentists to use a scan verification checklist before exporting. Include margin visibility, occlusal table capture, and soft tissue artifact review. Digital impressions also struggle with subgingival margins deeper than 1.5mm. Traditional impression material flows into those spaces better than any current optical system. If a margin is 2.5mm below the gum line and there is any bleeding, do not bother scanning. Take a conventional PVS impression instead. No amount of software enhancement will reconstruct that level of detail from a compromised scan.

The cost factor deserves honest attention too. A mid-range intraoral scanner runs between 15,000 and 40,000 dollars. A chairside mill is 60,000 to 120,000. Add a sintering oven, a scanning software license, and CAD/CAM licensing and you are looking at well over 100,000 in startup costs before you mill a single crown. For a small practice doing 5 to 10 restorative cases per week, the economics often do not work out compared to outsourcing to a qualified lab. You save money by using an external lab like Rite Smile Dental Lab rather than trying to bring everything in-house. The lab spreads its equipment costs across hundreds of practitioners.
What Actually Improves Patient Outcomes
The real advantage of digital workflows is not the speed alone. It is the consistency. A digitally milled zirconia crown maintains the same marginal gap range across every case, whereas a hand-injected wax pattern has variance that depends on the technician's technique that day. Studies show average marginal gaps of 70 to 120 microns for milled restorations versus 100 to 180 microns for conventional pressed or milled ceramic crowns made through analog processes. That difference matters clinically over a ten-year span. Patient comfort improves because the scan takes seconds instead of minutes of impression tray time. Patients with a strong gag reflex who could never tolerate a PVS tray can usually handle a brief intraoral scan. This expands the pool of patients who can receive quality restorative care. Treatment time drops from two weeks with temporary crowns and traditional impressions down to a single appointment or at most two visits for same-day cases. The temporary crown phase is eliminated entirely. This reduces the risk of transient pulpitis from temporary cement exposure and prevents the patient from breaking a temporaries during the waiting period.
The digital record itself is a significant improvement. Physical study models degrade, chip, and take up storage space. Digital scans are stored on a server and can be retrieved instantly for future reference, modifications, or comparisons over time. If a patient returns five years later for a replacement crown, the original prep scan is still there. You can compare the tooth structure changes and adjust the new design accordingly. The workflow is powerful when you understand where it fails and plan around those failure points. It is not about buying equipment. It is about knowing when to use it and when to fall back to analog techniques. The best practitioners and labs I have worked with do not treat digital as the only option. They treat it as one tool in a broader toolkit and apply it where it actually adds value.