
Isotretinoin Basics: What It Actually Does To Acne
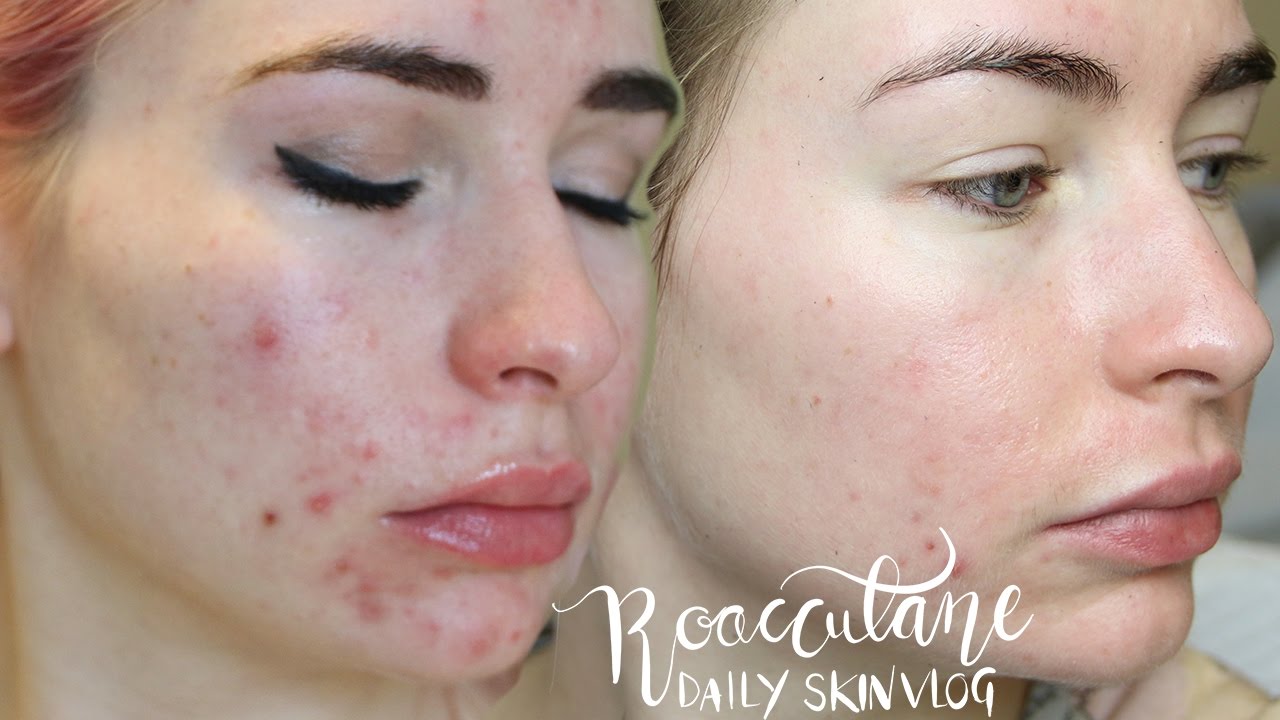
Most people know it as Roaccutane, Accutane, or generically as isotretinoin. It is a retinoid derived from vitamin A. The drug targets every known pathogenic factor in severe acne: sebum production, follicular hyperkeratinization, Cutibacterium acnes proliferation, and inflammatory signaling. I have spent years watching this drug prescribed, off-labeled, and sometimes abused by patients who want quick fixes without understanding the biology. The mechanism is straightforward but not simple. Isotretinoin shrinks sebaceous glands dramatically, sometimes by up to eighty percent after a full course. It normalizes keratinization so pores do not clog. It reduces bacterial load secondarily because the environment becomes hostile. The anti-inflammatory effects appear through modulation of gene transcription via retinoic acid receptors.
Rise Of Roacutan How It Works Its Magic On Your Skin
When I first encountered a patient who insisted Roaccutane was some kind of cosmetic miracle cream, I had to explain that it is actually a systemic medication with serious teratogenicity and monitoring requirements. The drug does not work locally. It circulates through the bloodstream and affects multiple organ systems. That is why you cannot skip blood tests. The typical protocol involves a cumulative dose calculated by body weight. Most dermatologists aim for sixty to one hundred twenty milligrams per kilogram over the treatment course, usually spanning four to six months. Dosing strategies vary between daily low-dose regimens and traditional higher-dose pulsed approaches. The evidence supports both, but the side-effect profiles differ noticeably. I remember one patient who developed severe headaches and blurred vision at week three of therapy. She had not reported her concurrent use of tetracycline antibiotics, which combined with isotretinoin to produce benign intracranial hypertension. We stopped the medication immediately, started acetazolamide, and her vision returned to normal within two weeks. This is why comprehensive medication reconciliation matters before you even write the first prescription.
The Realistic Timeline And What To Expect
Most patients notice initial worsening during the first two to four weeks. This "purge" phase occurs because the drug mobilizes deep comedonal material faster than the epidermis can shed it. I usually tell patients to expect increased dryness, cheilitis, and sometimes a flare before improvement becomes apparent. The flare typically resolves by week six if the dose is appropriate. Skin hydration decreases significantly. Sebaceous gland output drops so rapidly that many patients describe their skin as feeling "tight" or "waxed" rather than oily. This is not a temporary adjustment period. It is the pharmacological endpoint we are targeting. The dryness often persists throughout the entire course and may continue for weeks after discontinuation. Response assessment usually occurs at week eight. If inflammatory lesions have decreased by fifty percent or more, the course is working. If not, dose adjustment or alternative therapy requires consideration. I have seen patients continue for twelve months without achieving clearance, only to respond dramatically after switching from daily to pulsed dosing. The biology is individual, and rigid protocols occasionally miss nuanced presentations.
Get the Full Details

Limitations And When It Fails Completely
Isotretinoin does not work for everyone. Rosacea, perioral dermatitis, and fungal folliculitis frequently mimic acne but respond differently or not at all to retinoids. I once treated a patient for six months with isotretinoin who ultimately had Malassezia folliculitis. The diagnosis changed only after I performed a potassium hydroxide prep and culture. This is why initial diagnostic confidence matters more than therapeutic enthusiasm. Relapse rates after completion range from twenty to forty percent, depending on cumulative dose and patient demographics. Higher cumulative doses generally correlate with lower relapse, but the relationship is not linear. Some patients require second courses, while others remain clear indefinitely after a single treatment cycle. There is no reliable predictor before therapy begins. Pregnancy prevention remains the most critical limitation. Isotretinoin causes severe congenital malformations including craniofacial, cardiac, and central nervous system defects. The iPLEDGE program in the United States exists precisely because one mistake can destroy a life. I have counseled dozens of patients through this requirement, and the compliance burden is real but non-negotiable.
Practical Monitoring Requirements
Blood tests typically include liver function panels and lipid profiles at baseline, week four, and periodically thereafter. Transaminase elevations occur in approximately ten to twenty percent of patients, usually mild and reversible. Triglyceride increases affect a similar proportion and may require dietary modification or fibrate therapy if severe. Mood changes remain controversial. Some studies suggest association with depression and suicidal ideation, while others find no causal relationship. I monitor mood carefully but avoid alarming patients unnecessarily. If significant psychological symptoms emerge, discontinuation and psychiatric referral warrant consideration regardless of statistical debates. Musculoskeletal complaints including arthralgia and myalgia affect approximately five to fifteen percent of patients. These symptoms usually resolve with dose reduction or temporary discontinuation. I rarely encounter myopathy, but patients reporting severe weakness require creatine kinase measurement and rheumatologic evaluation before continuing therapy.
Alternatives When Isotretinoin Is Not Viable
For patients who cannot tolerate isotretinoin or have contraindications, several alternatives exist with varying efficacy. Oral antibiotics like doxycycline or minocycline provide anti-inflammatory effects but require prolonged courses and carry resistance concerns. Topical retinoids remain foundational but rarely achieve clearance in severe nodulocystic disease alone. Hormonal therapies including combined oral contraceptives and spironolactone offer viable options for females with androgen-mediated acne. These approaches work through different mechanisms and may require three to six months before maximal benefit appears. I combine hormonal therapy with topical retinoids routinely, reserving isotretinoin for refractory cases or severe scarring potential. Procedural interventions including chemical peels, laser therapy, and extraction techniques provide adjunctive benefits but should never replace systemic therapy in severe presentations. I have watched patients pursue aggressive cosmetic procedures while ignoring underlying inflammatory disease, only to return months later with worse scarring and persistent active lesions.
Storage And Handling Considerations
Isotretinoin capsules require protection from light and moisture. Exposure to humidity degrades the active ingredient more rapidly than manufacturers initially reported. I store medications in original containers with desiccant packets intact and advise patients to avoid transferring pills to daily organizers that expose them to ambient conditions. Disposal of unused medication requires careful consideration. Flushing creates environmental contamination concerns, while take-back programs remain underutilized. I recommend patients return medications to pharmacy collection containers whenever possible and avoid disposing them in household waste that enters municipal landfills. Drug interactions deserve attention beyond the tetracycline combination I mentioned earlier. Oral contraceptives may have slightly reduced efficacy during isotretinoin therapy, though the clinical significance remains debated. St John's Wort induces metabolic enzymes and may accelerate clearance, potentially requiring dose adjustment. Always review supplement use thoroughly before initiating treatment.
The medication works, but it demands respect for its potency and unpredictability. Patients who approach it as a casual solution rather than a serious therapeutic intervention rarely achieve optimal outcomes. Understanding the biology, monitoring for adverse effects, and maintaining realistic expectations separates successful courses from disappointing ones. I have seen both outcomes repeatedly, and the differences usually come down to preparation and follow-through rather than drug efficacy alone.


