What Actually Happens When You Traumatize a Knee Joint
A traumatic arthrotomy is essentially a wound that breaches the joint capsule and creates an open communication between the outside environment and the synovial space. The right knee is no different anatomically from the left in terms of what the pathology is, but the side matters when you're operating and when someone's writing a chart. People see a laceration near the knee and assume the joint isn't involved until proven otherwise. That assumption costs time. The mechanism tells you where to look. A direct blow from a fall onto a flexed knee can rupture the capsule without any external wound at all - that's a closed traumatic arthrotomy. A stab wound, a shard from a broken window, a gunshot, or even a dog bite near the patella all carry real risk of joint penetration. Sports injuries account for a smaller percentage than you'd think. Most of the ones I've seen come from sharp penetrating trauma in younger males and blunt trauma in older patients with degenerative changes making the capsule more vulnerable. I once had a patient who came in with what looked like a superficial scratch from a bicycle chain on the anteromedial right knee. He was walking on it fine. But when I probed with a sterile hemostat, the tip passed about eight millimeters and then met clear resistance - that was the capsule. There was synovial fluid visible in the wound track. We took him straight to the OR for irrigation and repair. Had we assumed it was superficial based on appearance alone, we would have missed an open joint entirely. The chain laceration looked trivial from the outside. It wasn't.
Right Knee Traumatic Arthrotomy Causes Diagnosis And Treatment Unpacked
How You Figure Out If the Joint Is Actually Open
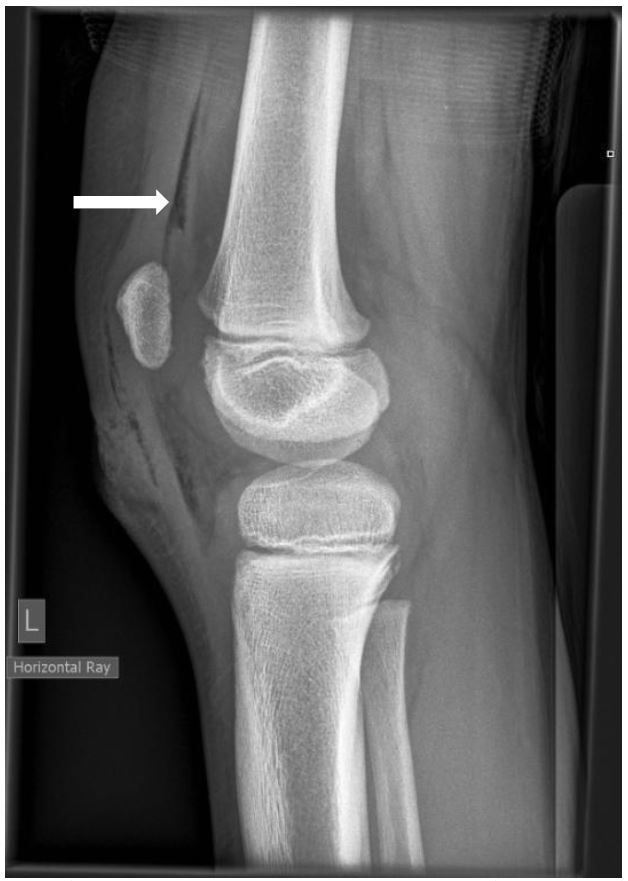
The gold standard historically was probing the wound with a sterile blunt instrument under local anesthesia. If you can pass the probe beyond the subcutaneous tissue and into the joint space, or if you see synovial fluid, you've got an arthrotomy. But probing has real limitations. Deep wounds, bleeding that obscures the field, and patient discomfort all make it unreliable. Studies show probe sensitivity ranges anywhere from 30 to 80 percent depending on who's doing it and how the wound presents. Ultrasound has become the more practical first-line tool in most emergency departments now. A trained operator can visualize the capsule, detect fluid collections, and assess whether a tract communicates with the joint space in real time. It takes about ten minutes, doesn't require radiation, and avoids the discomfort of probing an already painful wound. The operator dependency is the real caveat here - if your ED doesn't have someone comfortable with musculoskeletal ultrasound, you're back to clinical judgment and imaging. X-rays are mandatory but they'll mostly tell you what's broken, not whether the capsule is open. You're looking for intra-articular fractures, foreign bodies, and soft tissue gas that might suggest deeper communication. CT arthrography is overkill for most cases but useful when the diagnosis remains unclear after ultrasound and the clinical picture is ambiguous. You inject contrast into the joint and scan - if it leaks out through a defect, you've got your answer. Takes about twenty minutes and exposes the patient to more radiation and iodinated contrast.
MRI is the most sensitive modality for detecting capsular injuries and associated soft tissue damage, but it's rarely the right next step in an acute setting. You're not going to get an MRI ordered for an acute traumatic arthrotomy at 2 AM. It has its place in the workup of chronic or indeterminate cases, particularly when you suspect concomitant ligamentous or meniscal injury that will change surgical planning.
Get the Full Details

What You Do Once You Confirm the Diagnosis
Treatment splits into two parallel tracks: preventing infection and repairing structural damage. The infection part is where most mistakes happen. An open joint is a direct pathway for bacteria to reach synovial tissue, which has poor vascular supply compared to skin and muscle. Once organisms establish themselves in the joint space, they form biofilms that are nearly impossible to eradicate without repeated surgical intervention. Immediate irrigation and debridement is the standard. The classic teaching is within six hours, but that window is more aspirational than absolute. What matters more is how thoroughly you clean the joint and how promptly you start antibiotics. Tetanus status needs to be addressed - if the wound is contaminated and the patient hasn't had a booster in ten years, you give it. For dirty wounds, that's five years, not ten. Antibiotic choice depends on the mechanism. A clean knife wound gets covered differently than a wound from a object that was lying in dirt or water. I typically start with a first-generation cephalosporin for clean penetrating trauma. If there's soil contamination or a farm animal bite, you add coverage for anaerobes and gram-negative organisms. Pseudomonas becomes a consideration with puncture wounds through rubber-soled shoes, though that's more relevant to foot infections than knee wounds. Still, if the mechanism involves stepping on something through a sneaker, you keep it in mind.
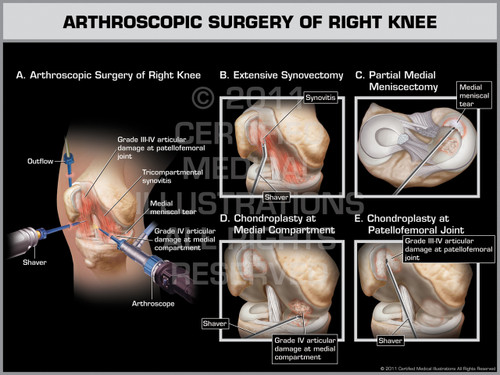
Surgical repair of the capsule follows the debridement. Capsular defects larger than two centimeters generally require primary closure to restore joint stability and prevent recurrent effusion. Smaller defects can sometimes be managed conservatively with rest and compression, but you're taking a risk either way. In one case, I encountered a patient with a degenerative meniscal tear that was incidentally discovered during arthrotomy repair. The original trauma had been a simple fall, but the pre-existing meniscal pathology made the capsule unusually vulnerable. We repaired the capsule and performed a partial meniscectomy through the same arthrotomy. The patient recovered faster than if we'd staged a separate arthroscopy later. The biggest pitfall I see is underestimating the associated intra-articular injuries. A traumatic arthrotomy often coexists with ligament tears, meniscal injuries, and osteochondral fractures. If you close the capsule and send the patient home without a thorough assessment of joint stability and structural integrity, you'll be seeing them again in three weeks for persistent swelling and mechanical symptoms. A focused ligamentous exam after the acute pain subsides and an MRI before discharge if there's any suspicion of internal derangement will save everyone involved a lot of follow-up visits.
What Actually Goes Wrong
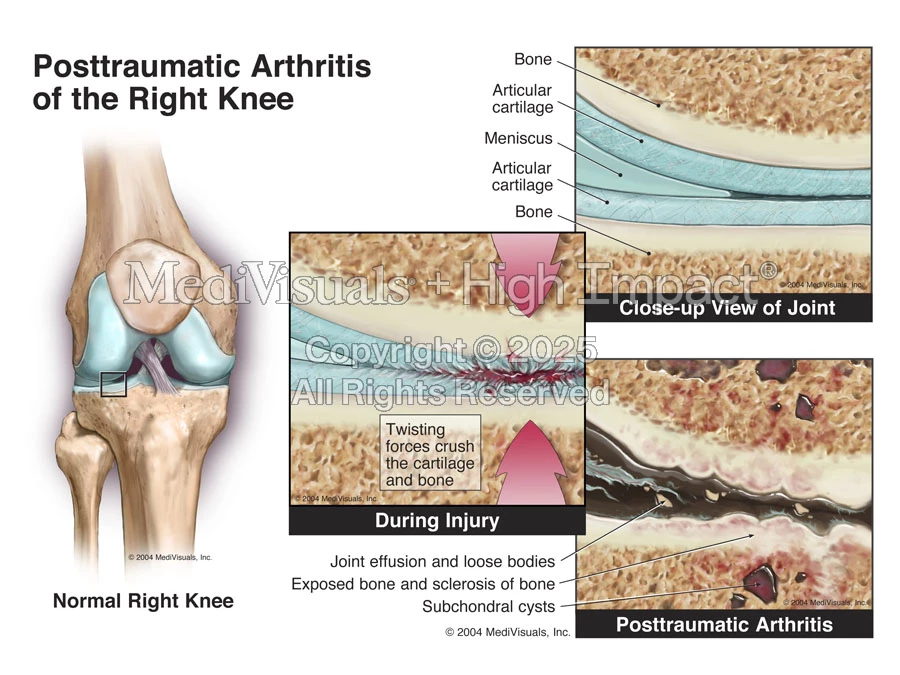
Septic arthritis is the worst-case scenario and it's more common than the literature suggests. Up to 10 percent of penetrating knee wounds that communicate with the joint develop infection if not properly managed. The mortality rate from septic arthritis isn't high, but the morbidity is significant - cartilage destruction can occur within days, leading to early post-traumatic osteoarthritis that may require joint replacement within a decade. Stiffness and arthrofibrosis are the more common problems. After any intra-articular trauma and surgery, scar tissue forms. The knee loses extension first, then flexion. Early aggressive physical therapy starting within days of surgery is the standard recommendation, but compliance is terrible. Patients don't want to push through pain. The ones who do, even reluctantly, have significantly better outcomes at six weeks. Cosmetic concerns are surprisingly significant for some patients. A laceration near the patella that required surgical repair and subsequent capsular suturing leaves a scar. For young patients, especially females, this can be a source of ongoing distress. Wound care education and silicone sheeting recommendations are worth mentioning at discharge, even if most patients won't follow through on them.
There's also the issue of chronic sinus tracts. If a small amount of foreign material - a fragment of clothing, a piece of glass, a bit of cartilage - remains in the joint after debridement, the body will wall it off and create a draining tract. This can present months or even years later as a recurrent issue. Thorough irrigation and removal of all identifiable debris during the initial procedure is non-negotiable. If you're unsure whether you got everything, you go back and look again. The re-operation rate for retained foreign bodies in traumatic arthrotomies is higher than you'd want it to be. Prognosis for most patients is good if the joint is identified and treated promptly. Delayed diagnosis beyond 24 hours significantly increases infection risk and worsens functional outcomes. The patients who fare worst are those with delayed presentation, contaminated wounds, pre-existing joint pathology, or inadequate initial surgical management. For the average otherwise healthy patient who presents within hours of injury and gets appropriate irrigation, debridement, and repair, return to baseline function within six to eight weeks is the expected trajectory.