The ICD-10 code for rheumatoid arthritis isn't as simple as looking up M06.9 and moving on. Most coders get this wrong on the first try, and then the claim comes back with a denial that takes three weeks to sort out.
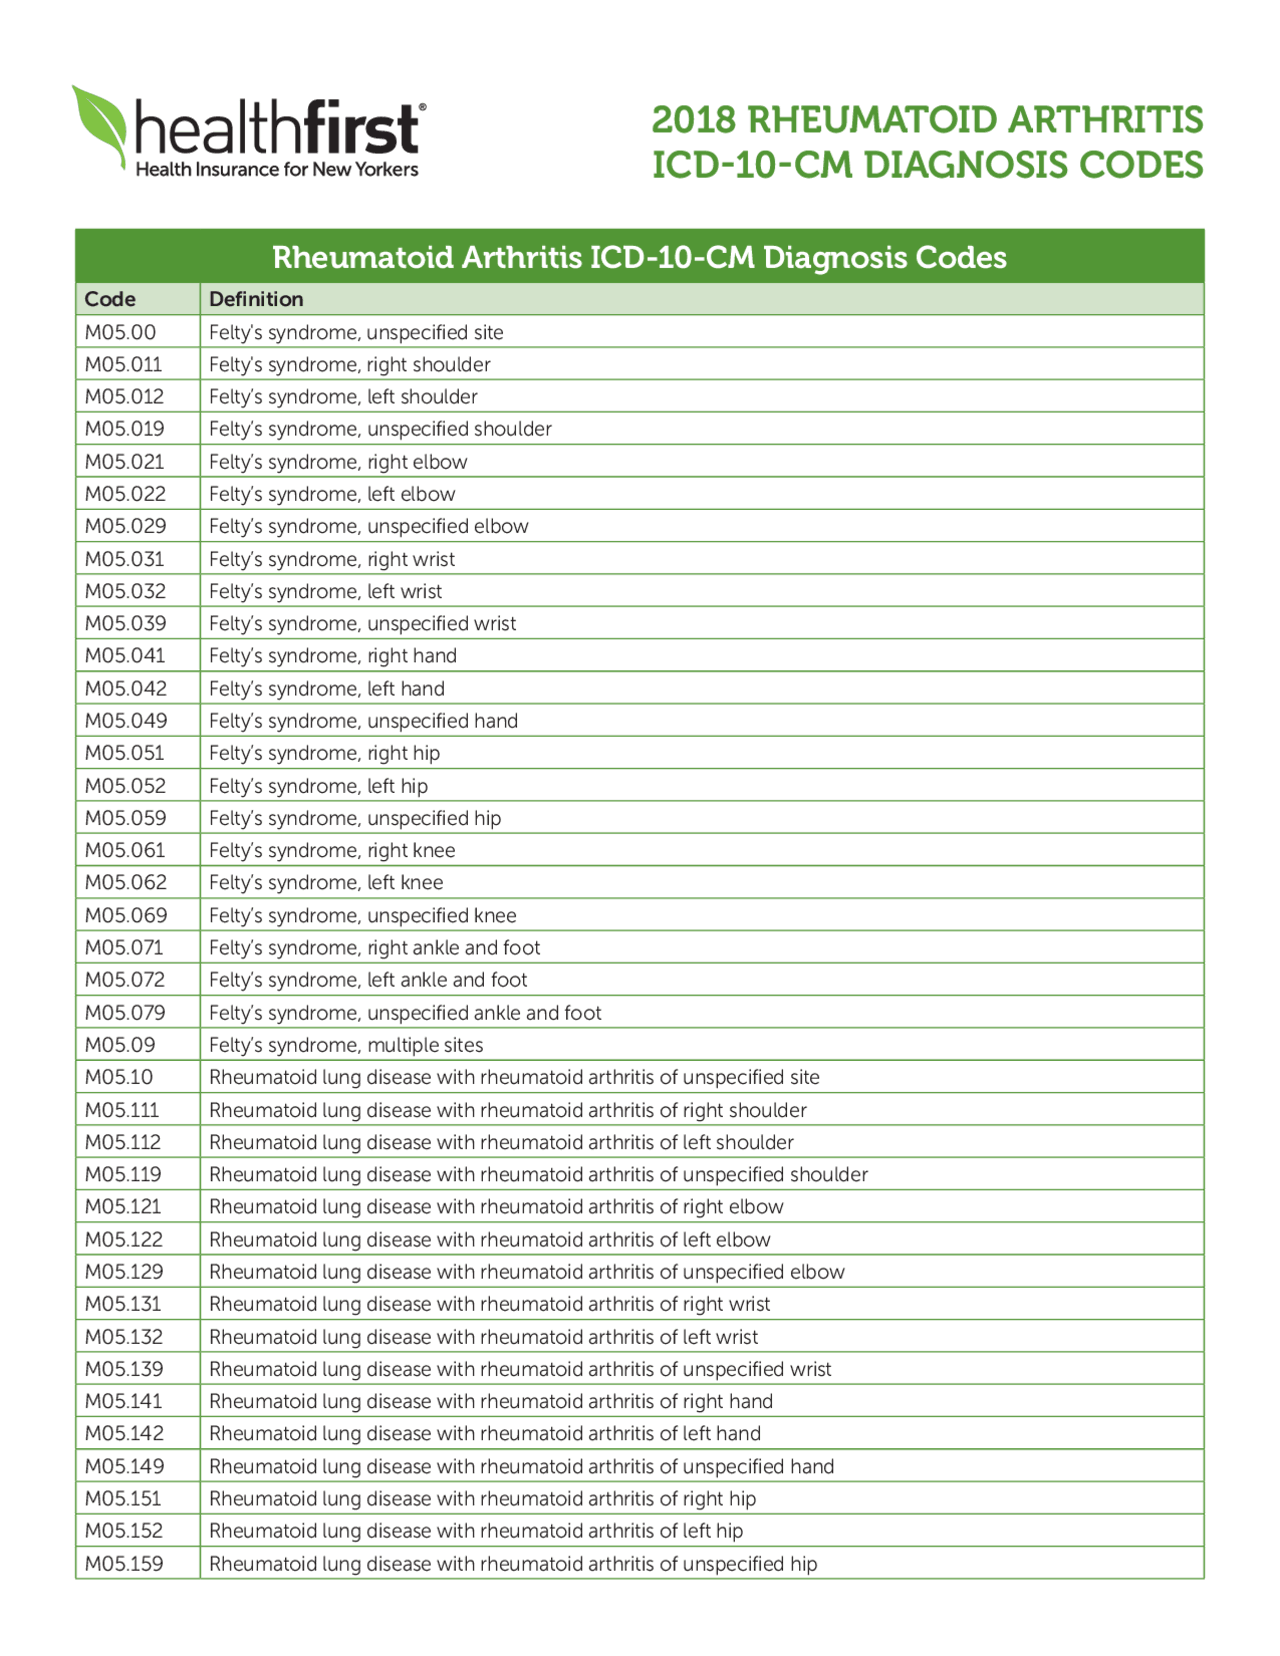
The basic code is M06.9 for unspecified rheumatoid arthritis, but that's the lazy code and it raises flags with some payers who want to see specificity. If the chart documents seropositive status, you're looking at M05 codes instead. M05.0 is Felty's syndrome, M05.2 includes vasculitis, M05.3 is secondary sicca syndrome, and M05.8 covers other seropositive variants with organ or system involvement. M06 is the non-seropositive bucket, and again M06.9 is the default when nothing else fits. M08 is for juvenile-onset, which is a completely separate tracking line. What most people miss is that ICD-10-CM has explicit combination coding guidance here. If a patient has RA with extra-articular manifestations, you code both the RA manifestation AND the specific organ involvement. So rheumatoid lung disease isn't just M05.3 or M06.9 - you also need J84.1 or whatever the appropriate pulmonary code is. Same thing for cardiac involvement. Payors will deny these as incomplete if you only list the RA code. I ran into this on a case last year. The physician had documented "RA with bilateral knee effusions" but didn't explicitly note whether the patient was seropositive or seronegative. I queried the provider and they confirmed the patient was on a biologic - which strongly implies seropositive status - but there was no lab documentation of RF or anti-CCP results in the chart. I coded M06.9 to be safe, flagged the query, and noted that the lack of serology documentation was a problem for the record. The claim went through but I had a feeling it would get challenged later.
It did. Six weeks after submission, the payer sent an RAR (request for additional records) asking for serology confirmation because the patient's medication history suggested M05 coding. Since there was no lab work in the chart, we couldn't support M05. This was a classic documentation gap that the coder shouldn't have to clean up, but the system doesn't work that way. Here's another thing that catches people off guard. The M05 subcodes aren't just about serology. M05.2 for rheumatoid arthritis with rheumatoid lung disease, M05.4 for rheumatoid myopathy, M05.5 for rheumatoid polyneuropathy - each of these requires specific documentation in the medical record. You can't assume the diagnosis based on the medication list or the physical exam notes alone. The chart needs to explicitly state the manifestation. I've seen cases where the provider wrote "RA patient with peripheral neuropathy" and the coder assumed M05.5. Wrong. The neuropathy needed to be specifically attributed to rheumatoid arthritis, not just present concurrently. That distinction matters for coding, and it matters for the payer's assessment of medical necessity for certain treatments.
The impact on reimbursement is real. M05 codes typically command higher RVUs in many payment models because they signal more complex disease management. A patient on methotrexate for M06.9 looks less severe than a patient on infliximab for M05.2 with documented pulmonary involvement. The difference shows up in utilization review, prior authorization outcomes, and sometimes even in referral patterns. There's also the matter of chronic disease management tracking. Medicare and many commercial plans use specific ICD-10 codes to identify patients for quality programs and care management outreach. If you code M06.9 when the patient actually has M05.3, you might be pulling them out of a rheumatology quality metric that affects the provider's compensation. It sounds small but it adds up across a practice population. One practical tip that saves time: keep a quick reference sheet for the M05 and M06 subcategories on your desk. Not the full ICD-10-CM index, just the RA-specific section. When you're scanning through charts at the end of the day and your eyes are glazing over, having that list in front of you cuts the coding time from maybe five minutes per complex RA case down to two. That's not nothing when you're closing out a full panel.
Get the Full Details

The biggest failure point I've seen is when coders don't verify the serology status before assigning M05 versus M06 codes. You need RF and anti-CCP results in the chart to justify M05. Without them, M06 is the defensible code even if the clinical picture suggests otherwise. I once worked with a physician who insisted his patient was seropositive because he'd seen positive results years earlier. The charts said otherwise. The audit caught it, and the practice took a hit on the recovery. Another issue is downcoding. Some organizations push coders toward M06.9 to avoid the perceived risk of M05 coding audits. This is short-sighted. If the documentation supports M05, you code M05. The risk of undercoding is real - it affects risk adjustment scores, quality metrics, and can look like revenue leakage on any audit. I'd rather have a coder defend a well-documented M05 assignment than defend a consistent pattern of downcoding across the entire rheumatology panel. There's no downloadable tool that fully automates this. You can buy ICD-10 lookup software or subscribe to coding services, but the judgment calls - is this neuropathy attributed to RA or coincidental? Does the chart document seropositivity or am I inferring it? - those still come down to a person reading the record. The software will give you the code list. It won't tell you which code fits the specific documentation in front of you.
The codes themselves change slightly every October with the annual ICD-10-CM update. M06.9 has been stable for years, but I've seen modifications to the neurological and musculoskeletal sections that occasionally affect how certain RA manifestations are classified. It's worth checking the annual update if your practice handles a high volume of rheumatology cases. The time investment is about twenty minutes and it prevents you from shipping a bunch of outdated codes into the next fiscal year. If you're a coder just starting out with rheumatology, pick up one good RA case and walk through it methodically. Pull the labs, check the medication list, read the progress notes for manifestation language, then assign the code. Do this five times with real charts and you'll stop second-guessing yourself on the basics. After that, the patterns are straightforward enough to handle without constant lookup.