Understanding RA When You're Already in Pain
Rheumatoid arthritis hits hardest in the morning. Your hands feel stiff and swollen before your feet even touch the floor. I spent years watching patients waste months trying different supplements and lifestyle changes while their joint damage kept progressing quietly underneath. The actual clinical picture is messier than most patient handouts show. RA is an autoimmune condition where your immune system attacks the synovium - that's the lining around your joints. It's not a simple wear-and-tear problem like osteoarthritis. The autoimmune attack triggers inflammation that eventually destroys cartilage and bone. Current research points to a combination of genetic markers like HLA-DR4 and HLA-DR1, environmental triggers like smoking and certain oral bacteria, and hormonal factors. Women get it about three times more often than men, and onset typically happens between ages 30 and 60. I had a patient in her early forties who came in convinced her RA was caused by the artificial sweetener she'd been using for years. She'd read enough forums to fill a book. The truth was more boring and more complicated. Her genetic predisposition combined with a period of heavy smoking in her twenties was the actual driver. Focusing on diet alone won't stop the autoimmune process once it's running.
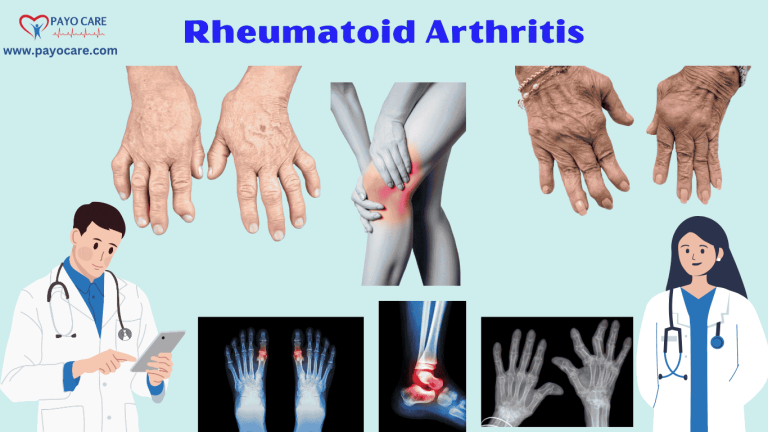
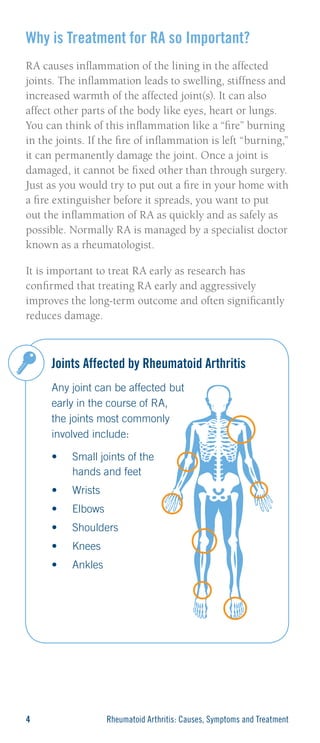
The symptoms usually start insidiously. You might notice fatigue that feels different from normal tiredness. Small joints in your hands and feet get tender and swollen symmetrically - both wrists, both knuckles, not just one. Morning stiffness lasting more than an hour is the classic red flag. Some people develop rheumatoid nodules under their skin. Advanced cases show up in the lungs, heart, and eyes. About 30 percent of RA patients eventually develop secondary Sjogren's syndrome with severe dry eyes and mouth. Diagnosis relies on a combination of clinical criteria, blood work, and imaging. Your doctor will check for rheumatoid factor antibodies and anti-CCP antibodies. The latter is more specific to RA. ESR and CRP tell you how much inflammation is happening. X-rays might look normal in early disease, which is why ultrasound and MRI matter for spotting synovitis before structural damage appears. The 2010 ACR/EULAR classification criteria score things like joint involvement, serology, symptom duration, and inflammatory markers. Treatment has changed dramatically over the last two decades. The old approach of starting with NSAIDs and waiting to see what happened is basically dead. Current guidelines emphasize treating to target - getting remission or low disease activity within three to six months of diagnosis. Disease-modifying antirheumatic drugs are first-line. Methotrexate remains the anchor drug for most patients. It's cheap, well-studied, and effective for the majority.
When methotrexate alone isn't enough, you add biologics or JAK inhibitors. TNF inhibitors like adalimumab and etanercept work for many people. Non-TNF biologics like tocilizumab and abatacept target different inflammatory pathways. JAK inhibitors like tofacitinib and upadacitinib are oral alternatives that work quickly but carry black box warnings for blood clots and cardiovascular events. The choice depends on your disease severity, comorbidities, and insurance coverage. Here's something most guides don't mention clearly. Biologics can lose effectiveness over time - a phenomenon called secondary failure. Your body develops antibodies against the drug, or the disease finds another inflammatory pathway. I've seen patients who responded beautifully to adalimumab for three years then suddenly flare. Switching to a different mechanism usually works, but it costs time and money. Monitoring drug levels and antibodies can help predict this before a flare happens. NSAIDs still have a role for symptom relief but don't modify the disease. Corticosteroids like prednisone can bridge the gap while DMARDs kick in, but long-term use causes bone loss, diabetes, cataracts, and hypertension. The goal is always to get off steroids as fast as safely possible. Physical therapy helps maintain function but won't slow joint damage. Surgery like joint replacement or synovectomy is reserved for end-stage destruction.
Get the Full Details

Pregnancy in RA patients requires special planning. Many drugs are teratogenic. Methotrexate absolutely must be stopped before conception - usually three months prior. Some biologics are safer during pregnancy, particularly certolizumab pegol which doesn't cross the placenta significantly. Disease activity often improves during pregnancy due to immune modulation, then flares postpartum when hormones shift back. Planning this transition with your rheumatologist prevents catastrophic flares. Vaccination matters more for RA patients than the general population. You should be up to date on flu, pneumococcal, shingles, and hepatitis B vaccines before starting immunosuppressants if possible. Live vaccines are contraindicated on most RA medications. The risk-benefit analysis shifts when you're on biologic therapy. Monitoring involves regular assessment of disease activity using tools like DAS28 or CDAI. Blood work tracks inflammatory markers and drug side effects. Liver function and blood counts matter with methotrexate. Chest X-rays and pulmonary function tests are reasonable before starting certain biologics. Dental exams help catch infections that could flare during immunosuppression.
Cardiovascular risk is significantly elevated in RA patients independent of traditional risk factors. Chronic inflammation damages blood vessels. Statins, blood pressure control, and smoking cessation aren't optional extras - they're essential parts of RA management. This is one area where rheumatologists sometimes underemphasize the connection. The reality is that RA management requires patience and regular follow-up. Finding the right medication combination can take months. Flares happen even with good treatment. New drugs emerge constantly. Cost and insurance barriers are real problems that determine what treatments are actually accessible. The comprehensive approach combines pharmacotherapy, monitoring, lifestyle modification, and patient education. There is no shortcut that replaces consistent rheumatology care.