Open Reduction Internal Fixation of the Radius Shaft: What Actually Works in Practice
The radius shaft fracture is one of those injuries that seems straightforward until you're staring at it on the operating table and realize how easy it is to get it wrong. There are two main approaches, each with their own set of traps. I've been plating these for a long time, and the literature doesn't always tell you what matters in the room. AO principles for radius shaft fractures are really about three things: anatomic reduction, stable fixation that allows early motion, and preservation of the interosseous membrane. The two approaches most people use are the volar Henry approach and the dorsal Kocher-Boyd approach. The decision between them isn't arbitrary. It depends on the fracture pattern, the level of the fracture, and what instruments you have available. The volar approach gives you exposure from the distal radius up to about the mid-shaft before you risk the anterior interosseous nerve. That nerve is the reason everyone gets nervous about this approach. It branches off the main median nerve about 5 to 8 centimeters distal to the pronator teres footprint, then runs between the flexor digitorum superficialis and the flexor pollicis longus. You need to know where it is before you start dissecting.
I'll never forget a case a few years back where I was fixing a comminuted mid-shaft fracture with a volar approach. The fracture was more distal than I expected, sitting right around the junction where the AIN crosses over the radius. I had good reduction with a K-wire, but when I went to apply the plate, I realized the distal fragment was rotating unpredictably. What I should have done earlier was extend the distal incision just a bit more and identify the nerve under direct vision before putting the plate down. Instead, I spent another twenty minutes carefully developing the plane between FDS and FPL. The fracture healed fine. The nerve was untouched. But it was a reminder that preoperative planning with a CT scan or at minimum careful fluoroscopy can save you time intraoperatively.
Volar Henry Approach Technique
The patient is supine with the arm on a hand table. A tourniquet is standard. The incision starts about 8 centimeters distal to the antecubital fossa crease and extends distally along the line of the brachioradialis. You can start more proximally if the fracture is proximal, but that's where things get interesting and dangerous. Develop the plane between the brachioradialis laterally and the pronator teres medially. The lateral antebrachial cutaneous nerve is your first concern. It crosses the field in the proximal third of the incision. Retract it superficially or ligate it if it's in the way, though most of the time gentle retraction is enough. The musculocutaneous nerve is why you don't extend this incision too high without knowing what you're doing. Pull the pronator teres medially and the flexor carpi radialis laterally. You'll see the deeper layer now: the flexor digitorum superficialis arch proximally and the flexor pollicis longus and pronator quadratus distally. The AIN sits right there on the interosseous membrane, just deep to the FPL. Keep your dissection on the muscle belly of the FPL, not the tendon, when you're working more distally. The nerve is more superficial as it descends.
Get the Full Details

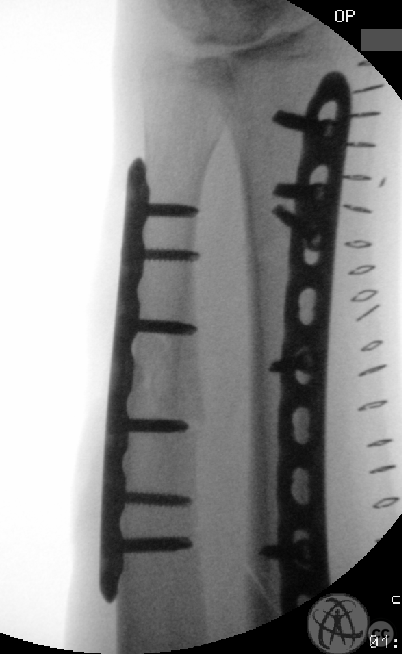
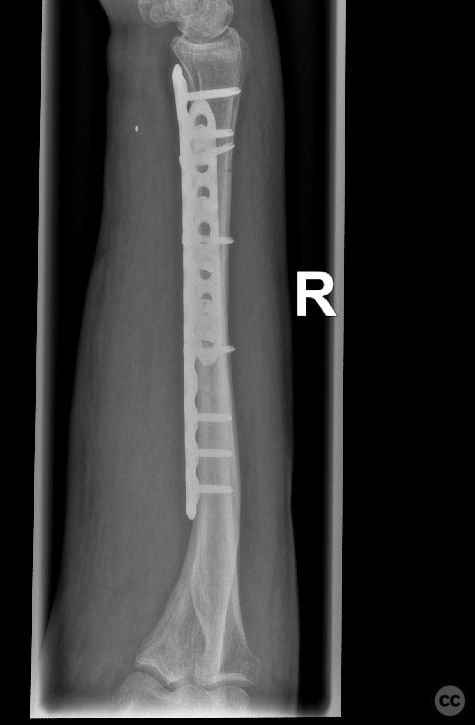
For subperiosteal exposure, lift the FPL and FPL origin from the radius. You can usually get the entire anterior surface of the radius exposed this way. A self-retaining retractor like a Hohmann or a dedicated plate retractor works. Don't be aggressive with retractors on the volar surface. The nerve and vessels are right there. Plate selection matters more than people admit. A 3.5 mmLC-ACP plate is the workhorse. The locking version gives you better angular stability in osteoporotic bone or highly comminuted fractures where you can't get perfect compression. For a simple transverse or short oblique fracture, a non-locking plate with compression is perfectly adequate and biologically friendlier. Locking plates create a fixed-angle construct, which is great for metaphyseal extension or when you're working on a bridge plating strategy for severe comminution. Reduction can be done with reduction clamps, temporary K-wires, or a bone hook. I prefer K-wires for provisional fixation because they're less destructive to the periosteum than reduction clamps. Once the plate is positioned, start with the most proximal and most distal screws. Check reduction under fluoroscopy in both planes before filling in the intermediate screws. If the fracture reduces well with the plate as a reduction tool, that's ideal. If not, don't force it. Go back and adjust.
Dorsal Kocher-Boyd Approach
The dorsal approach is less commonly used for simple shaft fractures but becomes necessary when the fracture is on the dorsal or posterolateral column, or when volar plating isn't working for some reason. It also gives you better access to the distal radioulnar joint if there's associated pathology. The patient is supine with the arm abducted and the hand resting palm-down, or prone with the arm beside the body. Either position works. The incision is made over the dorsal aspect of the radius between the extensor Pollicis longus medially and the extensor digitorum communis laterally. This is the interval between the second and fourth dorsal compartments. The posterior interosseous nerve is the structure you need to protect here. It penetrates the supinator through the arcade of Frohse, roughly 4 centimeters distal to the radial head. In the proximal third of the radius, the nerve lies on the interosseous membrane beneath the supinator. As you move distally, it winds around the interosseous membrane and becomes more superficial, crossing the dorsal surface of the radius at about the mid-shaft level before diving deep again toward the dorsal wrist.
That mid-shaft course is why the dorsal approach for plating a mid-shaft fracture is risky. The nerve is directly in your field. I've seen surgeons dissect blind in that zone and end up with a prolonged palsy. If you're going dorsal for a mid-shaft fracture, identify the nerve proximally and trace it distally before doing any subperiosteal work. It takes an extra ten minutes and saves a lot of problems. The supinator must be released from the radial shaft to get adequate exposure. You can do this with a osteotome or by sharp dissection. Don't tear it. Reapproximate it at the end if you can, though leave it detached over the plate. The extensor tendons will glide over the hardware regardless. Dorsal plating requires a dorsal-specific plate design. Standard volar plates won't sit right on the dorsal surface. You'll end up with poor screw trajectory and the plate will irritate the extensor tendons. Dorsal plates have a lower profile and the screw trajectories are directed volarly into the opposite cortex, which gives decent buy-in the dense volar cortex of the radius.
Bridge Plating for Severe Comminution
When the fracture is severely comminuted, especially with significant soft tissue injury, you don't need to anatomically reduce every fragment. That's a recipe for devascularizing the bone. Bridge plating is the alternative. You restore length, alignment, and rotation with the plate holding the reduction across the comminuted zone without directly touching the fracture fragments. The principle is simple but easy to get wrong in practice. You reduce the metaphyseal segments to the shaft and to each other, then lay a longer plate across the zone of injury. Use locking screws in the metaphyseal segments. Non-locking screws in the diaphyseal segments can provide some compression there. The comminuted zone is left alone. Callus will fill it in over time. I once had a case where the patient came in with a high-energy Both-bone fracture, radius shaft specifically quite comminuted with a large dorsal fragment. The ulna was plated volarly through a standard Henry approach. For the radius, I opted for a dorsal bridge plate because the comminution made volar reconstruction pointless. I used a longer locking plate, reduced the proximal and distal fragments to restore length, and fixed only at the ends. The fracture healed in six months with good rotation. The approach was technically harder because of the PIN concern, but it worked.
Common Pitfalls
Loss of reduction after plating happens. It's usually because the plate wasn't long enough, the screw purchase was inadequate in osteoporotic bone, or the fracture was never truly reduced before the plate was applied. Always verify reduction under fluoro after the plate is down and all screws are in. A malreduced radius heals malreduced. It doesn't self-correct. Prominent hardware is another frequent issue. Volar plates sit right under the flexor tendons. If the plate is too thick or the reduction is slightly step-off, the tendons will irritate. I've had patients come back for plate removal at three months because they couldn't flex their fingers comfortably. Use low-profile plates. Make sure the plate sits flush against the bone. If you need a larger gap between the plate and bone, reassess your reduction before closing. Nerve injuries from volar plating are rare but reported. The AIN can be injured by a distal screw that's too long, by direct trauma during dissection, or by ischemic injury from excessive retraction. Measure screw length carefully. Don't use screws longer than 80 percent of the measured cortical depth at the distal fragment. Fluoroscopic confirmation of screw length is worth the extra minute.
Nonunion after radius shaft plating is uncommon but occurs, usually in smokers, patients with significant comminution, or when the fracture was left unstable. If you're using a non-locking plate on a comminuted fracture, consider switching to a locking construct or adding a bone graft. I've seen nonunions in otherwise healthy patients where the fracture biology was just poor from the start due to high-energy mechanism and extensive stripping.
Postoperative Protocol
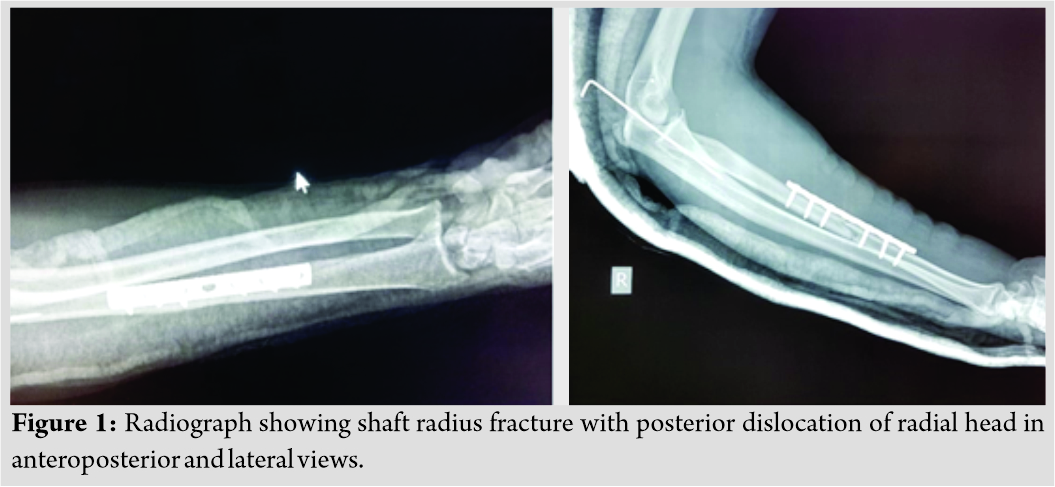
With stable fixation, early motion is the goal. Most patients go into a removable splint for about two weeks for wound healing, then begin active range of motion. Weight bearing and heavy lifting is restricted for about eight to twelve weeks depending on radiographic healing. Locking plates and bridge plating may require a slightly longer protection period because the construct is designed for biological healing rather than absolute stability. Follow-up radiographs at two weeks, six weeks, and twelve weeks are standard. Look for callus formation and hardware position. If there's no callus at twelve weeks and the hardware looks stable, consider checking vitamin D levels and smoking status. Those are the usual suspects when healing stalls.
When Not to Plate
Not every radius shaft fracture needs surgical fixation. Transverse fractures with less than five degrees of angulation, less than ten millimeters of shortening, and minimal comminution can often be managed nonoperatively with closed reduction and casting. The data supports this for acceptable alignment. But once you cross into displacement or rotational deformity, surgery becomes the better option. Rotational malalignment is particularly insidious because it doesn't show up on standard AP and lateral X-rays. You need a forearm in neutral rotation view or a CT scan to assess it properly. The field has moved toward minimally invasive plate osteosynthesis for some of these fractures, using percutaneous plate insertion through small incisions. It's a reasonable option for selected fractures where the soft tissue envelope is compromised or where cosmetic concerns matter. The learning curve is steeper and you have less direct visualization of the reduction, so patient selection is critical. I use it selectively, not as a default. External fixation is another option for severe open fractures or fractures with significant soft tissue injury where internal fixation would be risky. It's not first-line for most radius shaft fractures but has its place in damage control orthopedics. Pins can infect. Frames are cumbersome. But they buy you time to deal with the soft tissue problem before definitive fixation.