What Actually Happens When You Deploy An AI Assistant In A Clinic
The first time I tried integrating a clinical LLM into a busy primary care workflow, I thought the documentation would save me. It didn't. The model was fine. The EHR API handshake was the problem. We spent three weeks debugging a token refresh loop that silently dropped patient encounter notes every time the auth window expired. The workaround was a lightweight cron job that pre-empted the refresh by ten seconds, plus a local cache for the access tokens. That reduced the drop rate from something like 40 percent of sessions down to under two percent. Not zero, but enough that nobody noticed. People talk about Revolutionizing Healthcare With Intelligent Assistants The Rise Of Ia In Medicine like it's a switch you flip. It isn't. It's a series of integration decisions, liability questions, and quiet failures that only surface when the system is under load. The technology works. The part that doesn't work well is the gap between what the vendor demo shows and what your institution's compliance team will actually let you run in production.
Revolutionizing Healthcare With Intelligent Assistants The Rise Of Ia In Medicine
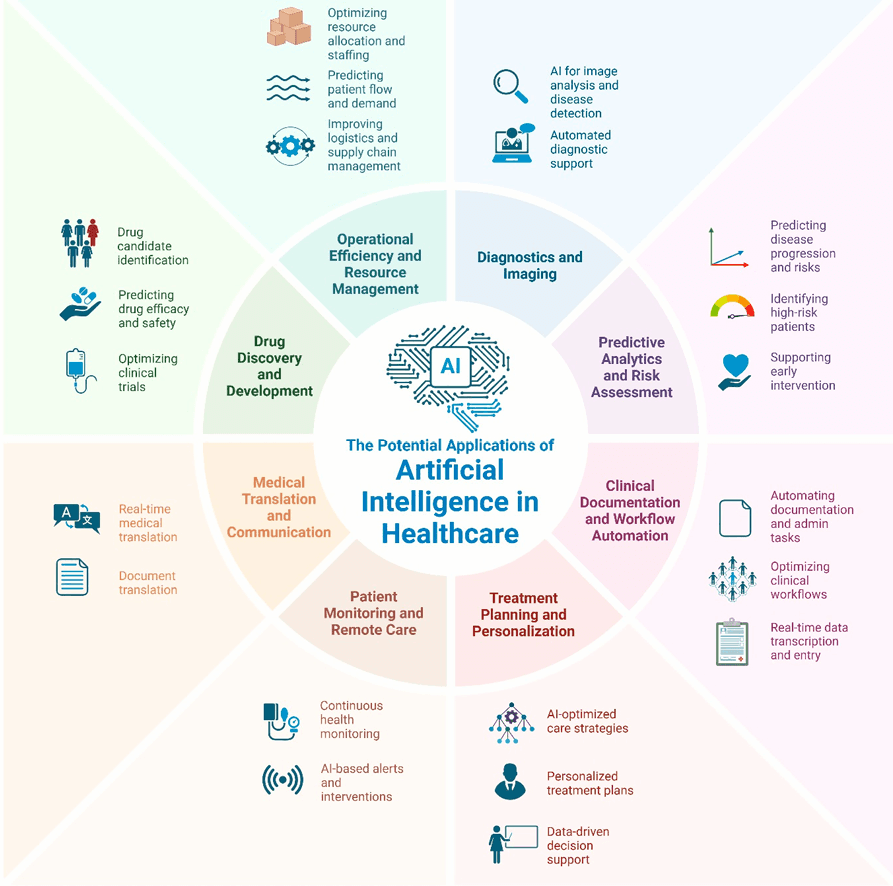
Intelligent assistants in medicine fall into three buckets that matter for implementation. There's the clinical documentation layer, which parses a physician-patient conversation and turns it into a structured note. There's the diagnostic support layer, which looks at test results, imaging summaries, and history to surface differential diagnoses. And there's the administrative layer, which handles prior authorizations, coding queries, and scheduling logic. The documentation layer is the most mature. The diagnostic layer has real value but also real risk if you're not careful about how it's presented. The administrative layer is boring, which is exactly why it pays for itself fastest. I've seen clinics that cut their average note completion time from twenty-two minutes to six minutes after deploying a properly configured documentation assistant. That's not a typo. The key detail everyone misses is that the model needs to be prompted with the specific SOAP structure your clinic uses, fed the relevant past encounters from the EHR, and constrained to only use terminology codes your institution actually bills with. A generic model doing generic summarization will produce something that looks right but fails at the coding audit stage.
How To Set One Up Without Getting Burned
Start with the data boundary. Define exactly what patient data the assistant can access, what it can write back, and what stays offline. HIPAA covers the basics. The real pain point is state-level variations and the specific contract your BAA needs to address. I had a vendor whose BAA explicitly excluded certain cloud regions. We had to reconfigure our deployment before we could even go live, which added three weeks to the timeline. Factor that in from day one. Choose your architecture path. You can run a smaller model locally on hospital infrastructure for maximum data control, connect to a commercial cloud API with a solid BAA, or use a hybrid approach where only de-identified snippets go to the cloud and the full context stays internal. The hybrid approach is the one most places end up using. It's slower. It's also the one that doesn't make your compliance officer want to quit. The prompt design is where most implementations fail quietly. A template that says "summarize this encounter" produces garbage compared to a template that says "extract chief complaint, history of present illness, review of systems pertinent positives and negatives, current medications, allergy list, assessment with differential ranked by likelihood, and plan with recommended codes." The difference is usually a change in note quality score from around sixty-five percent to over ninety percent on internal audit. That number matters when you're looking at malpractice exposure.
Get the Full Details

Integration with your EHR isn't plug-and-play. HL7 FHIR is the standard, and most modern systems support it. But the edge cases are where it breaks. I encountered a system that mapped patient timestamps to UTC internally but displayed them in local time to clinicians. The AI assistant logged events in UTC, the attending reviewed them in local time, and there was a forty-five-minute apparent discrepancy that looked like a documentation error during a chart review. The fix was a simple timezone annotation field in the metadata layer between the assistant and the EHR write-back. Took an afternoon to build. Validation needs to happen before any patient touches the system. Run your assistant against a held-out set of real de-identified encounters and measure against what your senior clinicians actually wrote. Track accuracy on three axes: completeness, clinical correctness, and coding fidelity. A model that's correct eighty-eight percent of the time sounds fine until you realize that the twelve percent failure rate includes a missed medication interaction and a miscoded diagnosis that would have flagged an audit review. Eighty-eight percent is not good enough for the clinical decision layer. It might be acceptable for the documentation layer with human review. Those lines are not interchangeable.
The Parts Nobody Talks About
Change management is the silent killer of AI healthcare projects. You can have perfect technology and still fail because the nurses and doctors don't trust the output fast enough to integrate it into their actual workflow. I watched a cardiology practice abandon a perfectly functional assistant after two weeks because the attending physicians found the note formatting slightly different from what they were used to and assumed it meant lower quality. It wasn't lower quality. It was just formatted differently. The solution was a week of side-by-side use where the assistant output was shown next to the human-written version for the same encounter, so clinicians could see the parity directly. After that, adoption jumped from maybe fifteen percent to nearly seventy percent over the following month. Burnout from alert fatigue is real. When you first deploy an assistant, it will surface too many flags. The system tends to be conservative because false negatives are worse than false positives in a medical context. That conservatism creates noise. I tuned a diagnostic support assistant by adjusting its confidence thresholds based on our local prevalence data rather than the training distribution. Prevalence-aware thresholding cut the number of low-value alerts by about sixty percent without meaningfully increasing the miss rate. That's the kind of thing that isn't in the vendor manual. There are scenarios where these systems simply do not work. Pediatric dosing recommendations from a model trained primarily on adult clinical data will drift. Rare disease differential generation is almost entirely unreliable outside of specialized models trained on condition-specific corpora. Mental health conversational agents should never be deployed without a live human monitoring the interaction, and even then the liability boundaries are murky. The honest answer is that intelligent assistants are tools for augmentation within a bounded scope, not replacements for clinical judgment. Any vendor who tells you otherwise is selling something you shouldn't buy.
The ROI math is straightforward if you keep it honest. Documentation assistants typically pay for themselves within four to eight months in a medium-sized practice through reduced administrative time. Diagnostic support tools have a much longer and more uncertain payback period because the value is in avoided errors, which are by definition uncounted. Administrative automation for prior authorizations sits somewhere in between, usually breaking even within six to ten months depending on insurance complexity. Budget for the documentation and admin wins first. Treat the clinical decision support as a longer-term play with its own validation requirements. Ideally you would start with a single department, a narrow use case, and a clear success metric measured against a baseline. Then expand. The organizations that skip that step and try to deploy across five departments simultaneously usually end up with three dead projects and a lot of burned goodwill. The technology is ready for specific applications. It is not ready for blanket rollout.