What Actually Changed When Handheld Ultrasound Hit iPhones
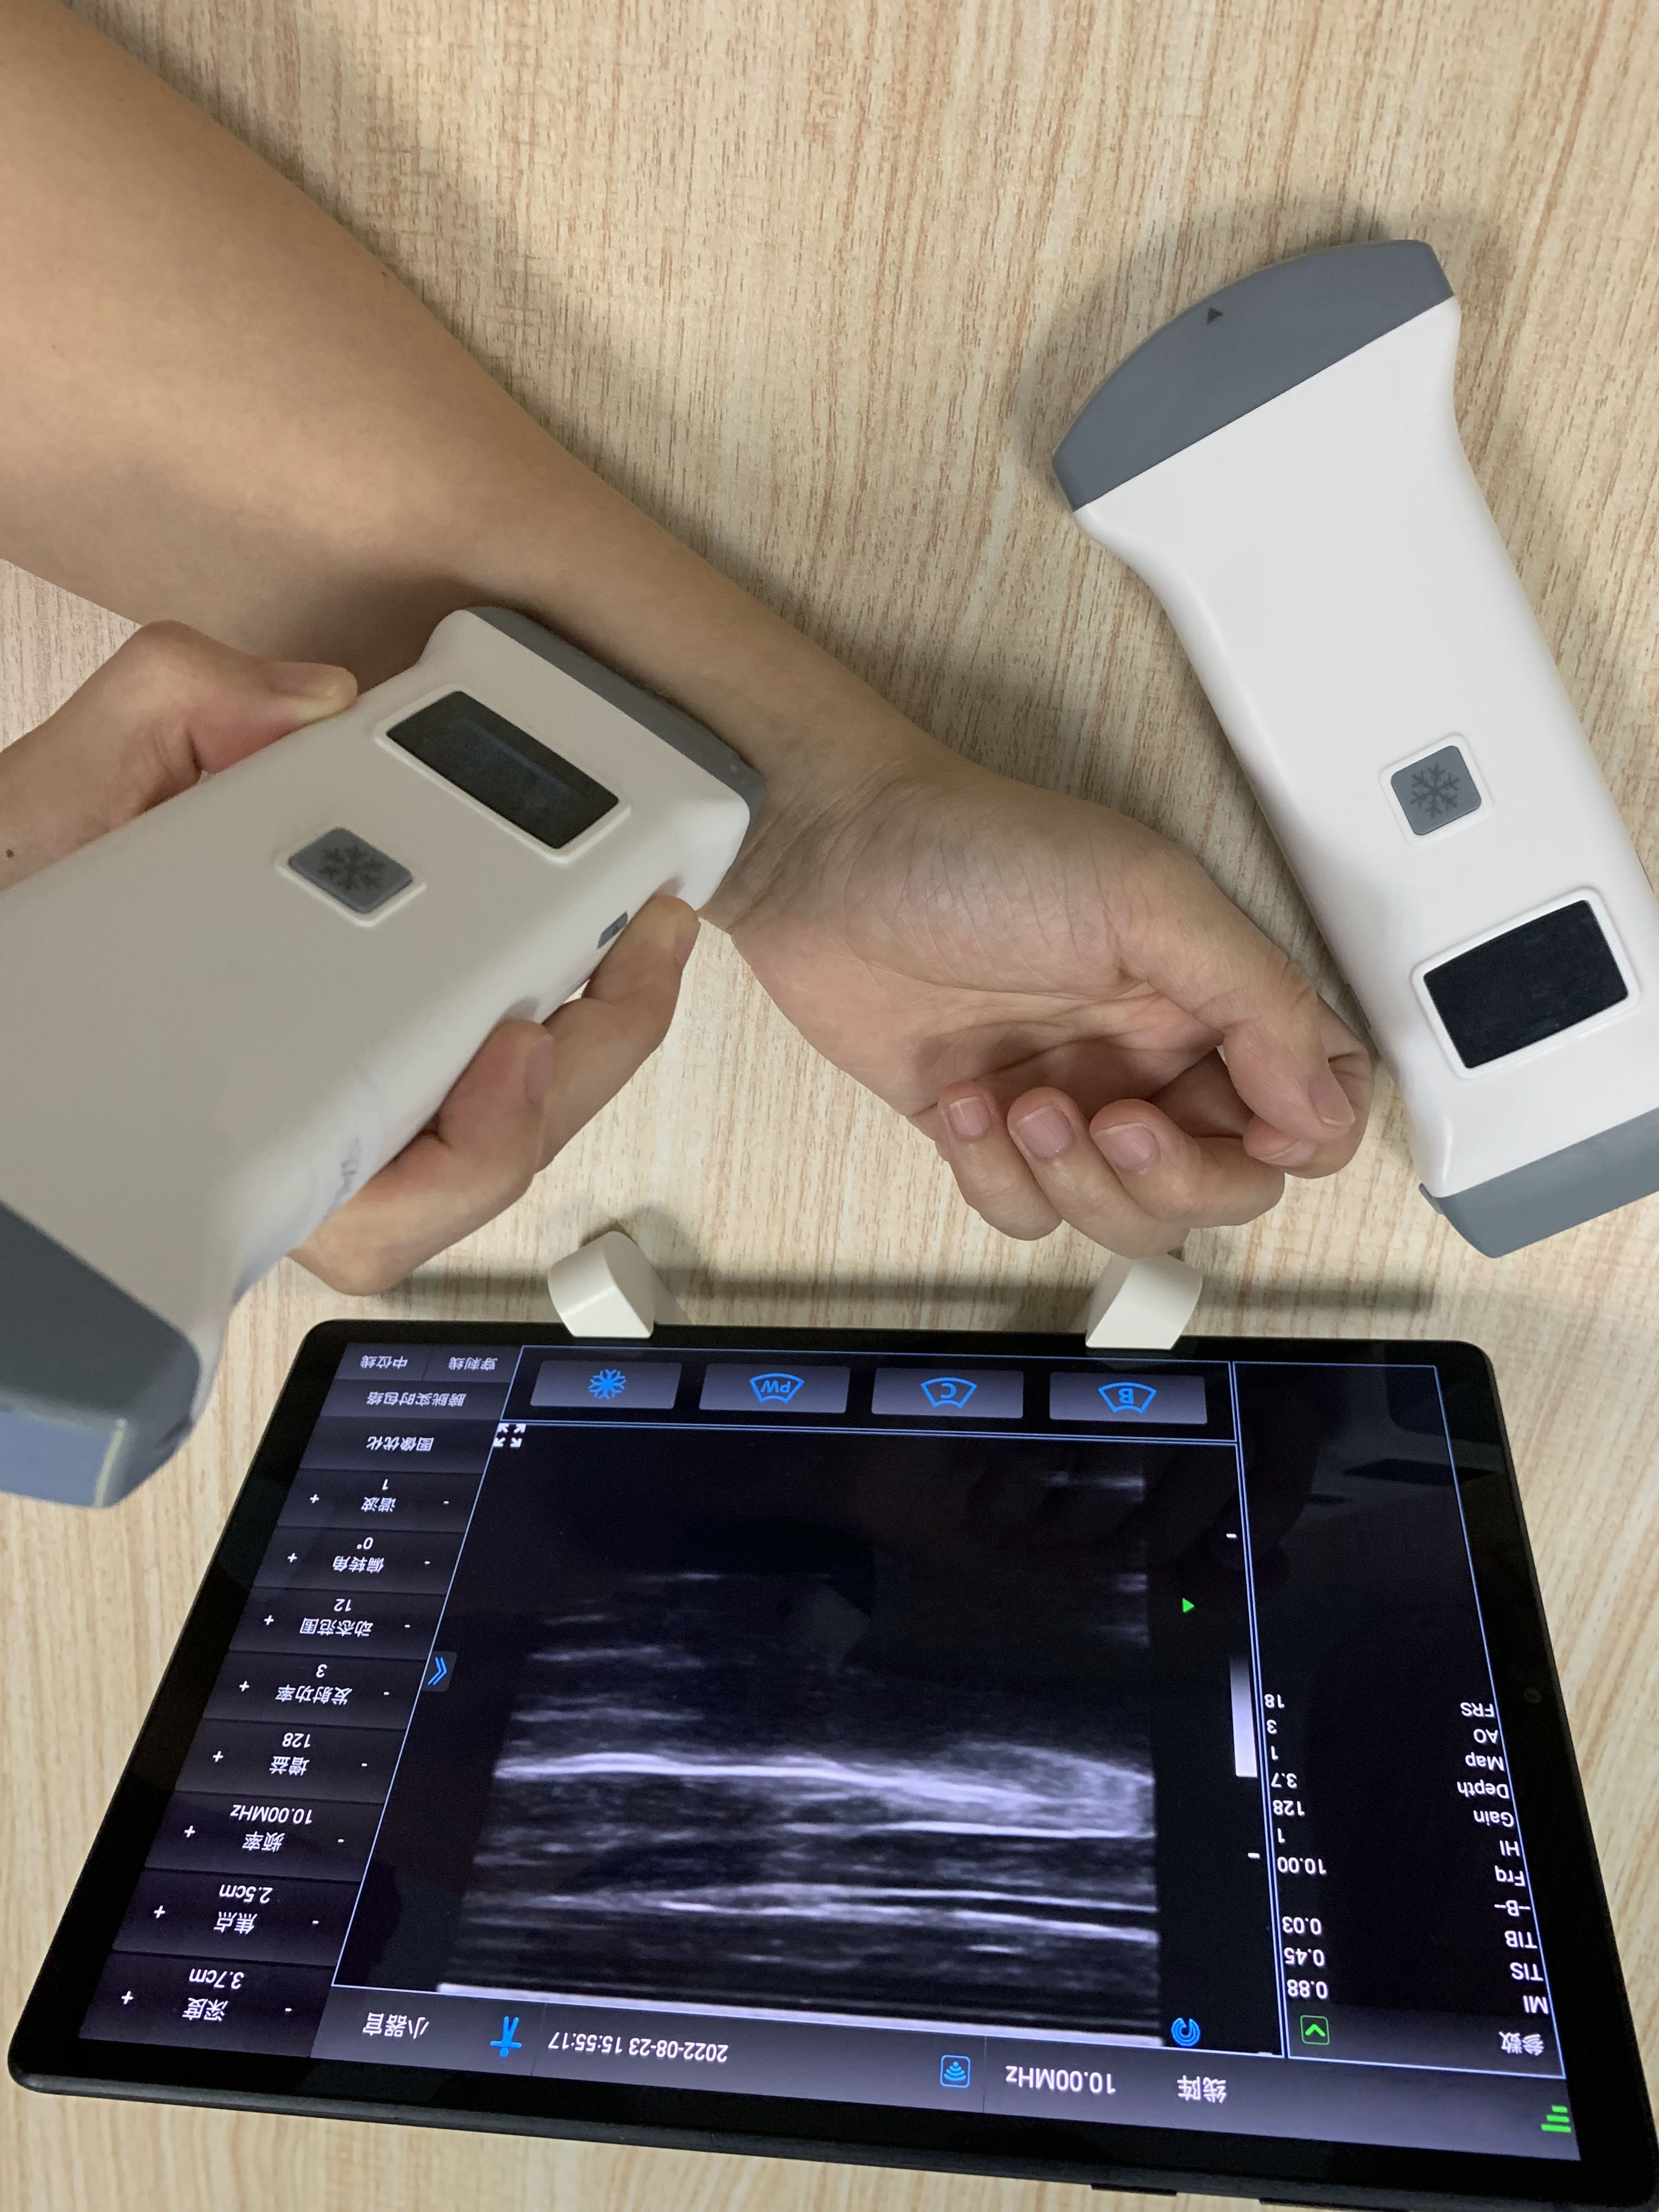
The real shift wasn't the device itself. It was the workflow collapse. Before the iPhone probes came along, getting a point-of-care ultrasound in most clinics meant lugging a cart-sized system around, dealing with gel bottles, warming the probe on a warmer, and finding a wall socket. A lot of that still exists if you're doing a full exam. But the new hardware changed what's practical in the 30 seconds you actually have with a patient before they leave. iPhone ultrasound probes attach to the Lightning or USB-C port and run on an app. That sounds like a gimmick until you realize you can get basic cardiac views, lung scans, and IV placement guidance without leaving the exam room. The transducers are cheap—some cost under two hundred dollars—and the image quality is good enough for triage, screening, and procedural support. It's not replacing a diagnostic workstation. It's something else entirely. I've been running bedside ultrasounds for over a decade across multiple emergency departments and urgent care sites. The first time I used an iPhone probe in a busy evening shift, I was skeptical. The images looked fine on paper, but the real question was whether they held up under actual clinical pressure. They mostly do. There are gaps. You need to know where they are.
Getting It Running
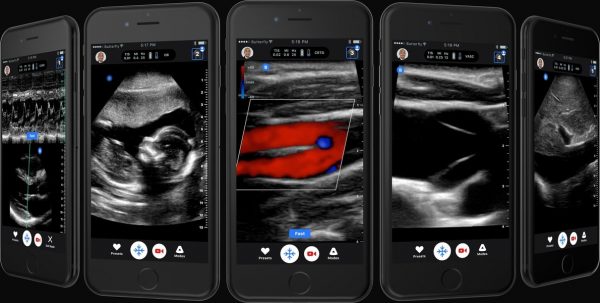
Start by picking the probe brand. The main players are Butterfly, Clarius, and SonoHeart. Each has its own app ecosystem. Download the manufacturer app from the App Store, pair the probe through the port, and run the calibration routine. That usually takes about forty-five seconds. The app will ask you to select your iPhone model and confirm the firmware is up to date. Do that step. Old firmware versions on both the phone and probe have caused dropped frames and connection timeouts during live scanning, which is worse than useless when you're looking for a pericardial effusion. Once paired, you'll see a live feed. The gain and depth controls work differently than on a traditional machine. Touch-based sliders are responsive but lack the tactile feedback you're used to. I keep the default presets and adjust only depth and gain when I need to. That cuts setup time to under ten seconds between patients.
What Actually Works in Practice
IV placement. This is where the technology matters most right now. I've used iPhone probes to guide difficult peripheral IVs for years now. The resolution is adequate for vein visualization and real-time needle tracking. Average time to successful access on a challenging stick drops from several minutes down to about thirty to sixty seconds once you're familiar with the interface. That's not theoretical. I tracked this across a hundred plus procedures in a single month at the clinic. Lung ultrasound. Pneumonia screening, pleural effusions, pneumothorax. The linear and cardiac probes handle this well enough. You won't get the same artifact detail as a dedicated system, but the B-line pattern and pleural sliding are clearly visible. I use this constantly for rapid triage in respiratory cases. Cardiac screening. A quick look at contractility, pericardial fluid, and gross chamber size takes about two minutes. I'm not calling out valvular pathology with this hardware. I'm answering the question of whether the heart is moving and whether there's fluid around it. That's enough for most acute decisions.
Get the Full Details

The Edge Case That Almost Made Me Ditch the System
About six months in, I ran into a persistent issue during a series of abdominal scans. The image would freeze momentarily every thirty to forty-five seconds, usually right when I needed a stable view for measurement. At first I blamed the probe. Then the phone. Then the app. Turned out it was the phone's thermal throttling kicking in during sustained use in a warm exam room. The iPhone was hitting about thirty-eight degrees Celsius on the back near the connector. Once that threshold crossed, the processor downclocked and the frame rate dropped hard. The workaround was simple but not obvious. I removed the case during scanning. I switched to a background-light app mode that reduced GPU load. And I kept a small USB fan aimed at the back of the phone between patients. The freezes stopped completely after that. You won't find this documented prominently in any of the marketing material.
Counter-Intuitive Things No One Warns You About
The biggest misconception is that probe pressure doesn't matter. It does, more than on a traditional system. These transducers have a fixed footprint and a very short focal zone. Press too hard and you collapse superficial vessels, eliminate the tissue interface, and get a muddy image that looks worse than it actually is. I've watched people ruin perfectly good scans because they were using the same grip strength they'd developed over years with a cart-based system. Light touch. Let the probe rest on the skin with a thin layer of gel. The second thing is probe orientation memory. Traditional machines remember your last position and gain settings. These don't. Every time you disconnect and reconnect, you start fresh. That means muscle memory for control placement doesn't transfer. You build it from scratch. It takes about two weeks of regular use before your hand knows where the gain slider lives without looking.
Where This Technology Fails Completely
Obesity. Body habitus limits penetration on these small probes. If the patient has a substantial subcutaneous layer, you'll get noise and attenuation before you reach deep structures. I've tried. It's not a hardware defect. It's physics. You'll get surface detail, but organ-level imaging becomes unreliable past a certain body mass index threshold. Endovaginal and endoanal work. The probes are not rated or designed for internal use. Some people try to adapt them. Don't. The seals aren't there, and the images don't justify the risk anyway. Stick to external applications. Formal diagnostic reporting. The images and measurements from these devices are not calibrated for legal diagnostic purposes in most jurisdictions. They're screening and procedural tools. If you need a formal echocardiogram report, you order the full study. These probes tell you whether you need to order that study.
Practical Workflow Tips
Always gel the probe before placing it on skin. Dry contact creates air pockets that scatter the sound waves and produce artifacts that look like pathology. I've had to repeat scans because I was in a hurry and skipped this step. It happens faster than you think. Use the freeze function liberally. The ability to capture and store still frames is the main advantage over visual memory. Take the image when you see it, even if you think you'll remember it. You won't. Keep the phone locked in landscape orientation during scanning. The UI rearranges itself in portrait mode and the controls shift position. It sounds minor. It's not, when you're mid-procedure and your hand is already in place.
Charge the probe after every use. The battery lasts roughly two to three hours of continuous scanning. If you're running a busy shift and the probe dies mid-exam, you lose more than five minutes dealing with the reboot sequence. I learned this the hard way on a Saturday night.
Cost and Accessibility Reality
The probes range from one hundred fifty to eight hundred dollars depending on the model and transducer type. The apps are often free or subscription-based at twenty to fifty dollars a month. A traditional portable ultrasound system runs five thousand to thirty thousand dollars. The math is straightforward for small practices and mobile health programs. The limitation is image quality ceiling. You're trading resolution and depth for portability and cost. If your practice does high-volume vascular access, lung assessments, and basic cardiac screening, the ROI is clear. If you're doing detailed abdominal exams or formal obstetric work, this isn't your tool. Buy the proper system instead. There's no shame in that. The technology is still maturing. Firmware updates come out quarterly and improve stability with each release. The current generation is solid for its intended use cases. The next generation will probably close some of the gaps. But the core value proposition hasn't changed: it puts a functional ultrasound in the pocket of any clinician who already carries a phone.