Building a Patient Advocacy Practice Without Burning Out
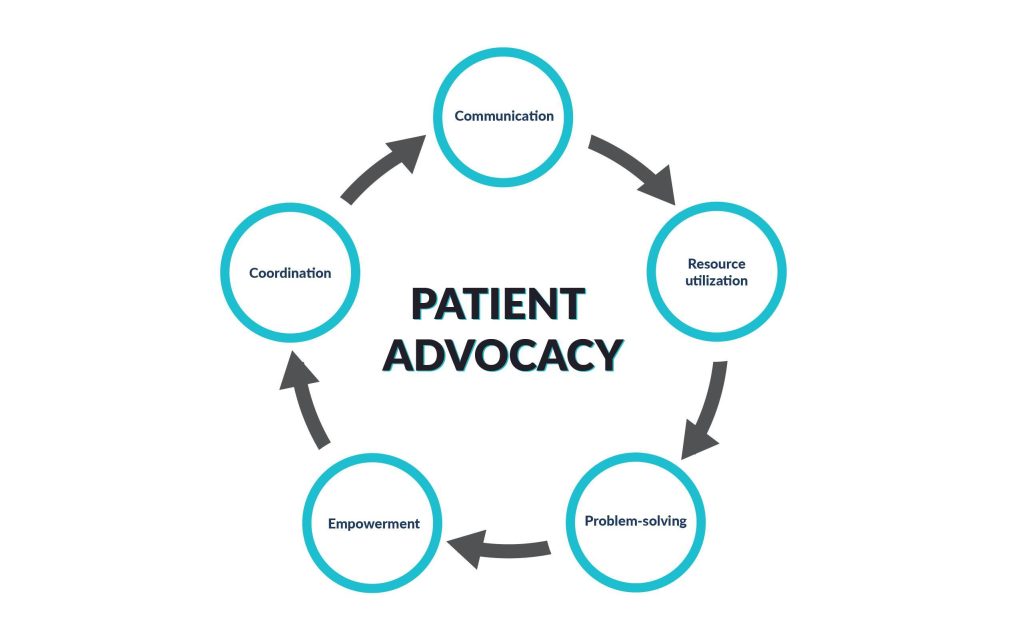
Cheryl Alley spent years inside the oncology system as a patient before deciding that the standard model wasn't working. She didn't start as a thought leader. She started because she needed someone to help her understand her own care plan, and nobody was volunteering. That frustration is the foundation of what she eventually built, and it's also the foundation of anything worth doing in patient advocacy today. The current landscape rewards people who can translate between medical jargon and plain language, but it doesn't pay them well for it. It rarely pays them at all. You do it because the alternative is watching the same mistakes happen to other people over and over. The core of Alley's approach is that advocacy isn't a personality trait. It's a methodology. When she started, most patient support was either purely emotional or purely informational. She treated it as operational. A diagnosis is not just a medical event. It's an administrative one. Insurance authorizations, prior appeals, scheduling conflicts between specialists, pharmacy benefit disputes, clinical trial eligibility screening, transportation logistics for infusion visits. These are the actual problems patients face, not the abstract concept of "getting better." Alley organized around the operational side. That shifted the conversation in a way that still isn't widely replicated outside of specialized organizations. I learned this the hard way. A few years back I was helping a client navigate a CAR-T cell therapy authorization through a regional PPO. The clinical criteria were met. The physician submitted everything. The plan denied it twice using a catch-all "experimental and investigational" clause that had no actual basis in the peer-reviewed literature for that specific regimen. The standard workaround was to file a formal appeal with journal citations. That took about six weeks and had roughly a forty percent success rate with that particular plan. Instead, I pulled the plan's own evidence-based coverage policy document from their provider portal, found the specific carve-out for hematologic malignancies, and submitted a parallel external review request under state mandate while the internal appeal was still processing. The external review forced a binding decision in fourteen days. They approved it. It's not a perfect solution, and it only works if you know how to read your state's insurance code and the plan's own contractual language. Most advocates don't bother learning either one.
The methodology breaks down into several practical components. First is documentation discipline. Every conversation, every fax transmission, every representative you speak with, and every reference number you receive should be logged in a single timeline. I use a simple spreadsheet with date, time, representative name, company, topic, and outcome. It sounds trivial until you're in month three of an appeal and need to prove that you followed a specific procedure exactly as the plan requires. Second is understanding the hierarchy of recourse. Internal appeal, external review, state department of insurance complaint, employer EAP intervention if applicable, and in some cases FDA compassionate use pathways. Most people stop at step one. The system is designed to make stopping at step one feel like giving up. It isn't. It's the first layer of a multi-layer process. Third is the concept of medical necessity documentation. This is where most advocacy work fails. A doctor's letter saying "this treatment is necessary" means almost nothing to an insurance reviewer. The letter needs to cite specific clinical guidelines, reference the patient's particular diagnosis codes, explain why alternative treatments have been exhausted or are contraindicated, and include peer-reviewed studies that support the off-label or novel aspect of the therapy. I've seen physicians spend forty-five minutes on a handwritten note that got rejected in twelve seconds because it didn't map to the plan's coverage criteria. Training clinicians to write these properly has saved my clients more time than anything else I do. It usually takes one thirty-minute call to reframe how they approach these letters. After that, turnaround time for responses drops from an average of three weeks to about four business days. There are real limitations to this approach, and they matter. It depends entirely on the patient having the cognitive bandwidth and emotional capacity to engage with it, which is not always available during active treatment. It depends on the insurance plan being operating in good faith, which is increasingly rare with the rise of narrow networks and algorithmic utilization management. And it depends on the advocate having access to the actual policy documents, not just the summary of benefits that plans are legally required to provide in simplified language. The gap between the summary and the full policy is where denials live. If you only read the summary, you're being advocated against by design.
Another thing nobody talks about is the burnout factor. I've watched competent advocates quit after two years because the system rewards incremental progress at best and deliberate obstruction at worst. There's no sustainable funding model for individual advocates. Organizations like Alley's Existential Angels provide structure and community resources, but they can't scale to meet the volume of people who need this kind of support. The closest thing to a practical solution is training patients and families to do basic navigation themselves. Not everything requires a professional advocate. Most prior authorization disputes can be resolved with a well-constructed phone call and a copy of the plan's own clinical policy bulletin. The problem is that nobody teaches this. It's assumed to be either common knowledge or professional-only knowledge. Both assumptions are wrong. If you want to actually engage with this work, start by getting your hands on your own health plan's clinical policy bulletins. They're usually available on the provider education section of the insurer's website. Search for the CPT codes related to your condition. Read them. Then read the exclusions. Then read the appeal rights section in your state's employee benefit plan disclosure, if you have an employer-sponsored plan. This gives you the actual rules of the game instead of the marketing version. Then build your documentation system. Then practice on a low-stakes issue like a prescription tier exception before you need it for something critical. The process takes about two to three hours of focused work upfront and saves an average of eight to twelve hours per major dispute downstream. Cheryl Alley's contribution isn't a program you can download. It's a proof point that treating patients as participants rather than recipients changes outcomes. The operational advocacy framework she helped normalize is now available through several patient navigation programs at major cancer centers, but the quality varies enormously. Some are staffed by trained navigators. Others are volunteer positions with no standardized training. Your best bet is to ask specifically about credentials, turnover rate, and case load before committing to any program. The ones that work well tend to have navigators who stayed in the role for at least three years and have access to legal resources for appeal support.
Get the Full Details