Activity-Based Costing in Healthcare: A Practitioner's View
Most hospitals and healthcare systems I've worked with haven't actually implemented activity-based costing correctly. They set it up, run it once, get confused by the numbers, and abandon it. I've been doing this work long enough to know where it breaks and how to keep it from collapsing.Revolutionizing Healthcare Costs Unleashing The Power Of Activitybased Costing
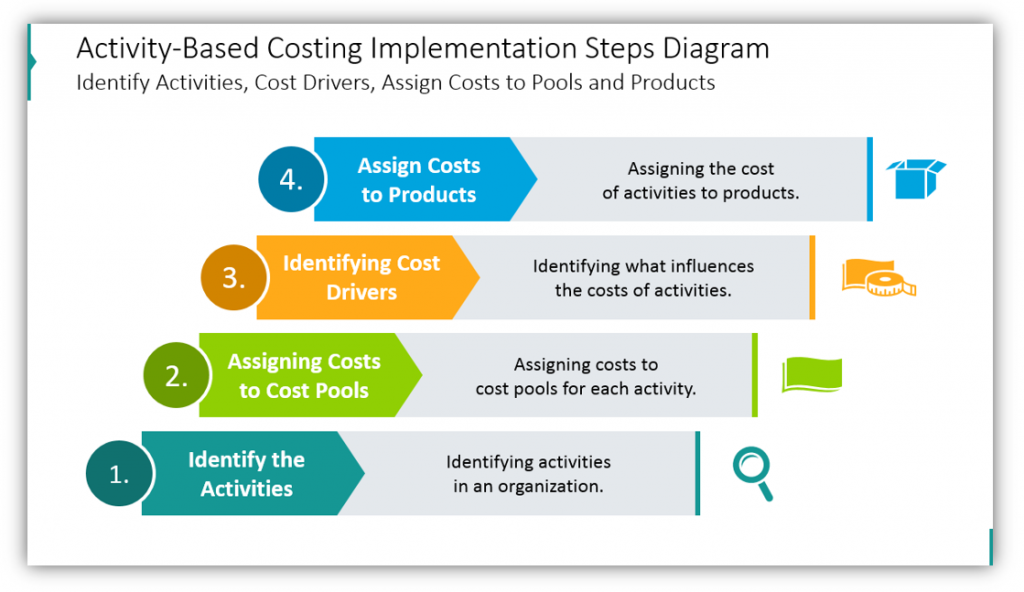
Activity-based costing assigns overhead costs to specific clinical and administrative activities rather than spreading them evenly across departments. The method traces resource consumption through cost drivers — things like patient minutes, procedure counts, supply triggers, and equipment usage — to build a accurate picture of what each service actually costs. The traditional approach uses departmental overhead rates. You take total department expenses and divide by a volume metric like outpatient visits or bed days. That produces a single blending rate for everything in that department. It sounds reasonable until you realize a complex oncology infusion takes significantly more nursing time and overhead than a routine vaccination. Both are billed through the same departmental rate. ABC solves this by mapping activities to resources. Here is how you actually do it in practice.
Building the Model
Start with your general ledger. Pull twelve months of expense data broken down by cost center. Finance teams usually have this already. The problem is they tend to stop there. You need to go further. Create an activity dictionary. This is a list of every discrete task performed across your organization. Not high-level departments. Actual tasks. Examples include scheduling appointments, preparing examination rooms, processing lab specimens, administering medications, managing equipment sterilization, handling insurance verification, and processing claims. The granularity matters. If you lump too many tasks together, your cost assignments become inaccurate. If you create thousands of micro-activities, the model becomes unmaintainable. I've seen teams struggle with this balance. One hospital I advised spent three weeks debating whether "wound care" should be split into dressing changes, debridement, and patient education sessions. They ended up with five separate activities within wound management. It added precision but also added complexity that their data system couldn't handle without custom development. The workaround was creating parent activity groups with child activity codes inside them. The reporting rolled up cleanly while the detail stayed accessible for anyone who needed it.
After building the activity dictionary, assign resources to activities. This means determining how much time, supplies, and equipment each activity consumes. Time studies are the most reliable method. Send trained observers into clinical workflows and record what actually happens. Self-reported time estimates from staff are notoriously unreliable. They tend to overestimate by thirty to fifty percent according to multiple validation studies in healthcare settings. The second step after resource assignment is identifying cost drivers for each activity. A cost driver is the factor that causes cost to change. For lab specimen processing, the driver might be the number of specimens. For imaging services, it could be the number of scans or minutes of machine operation. Pick drivers that have a causal relationship to cost, not just convenience metrics. Calculate activity rates by dividing total activity cost by total driver volume. Then apply those rates to patients or procedures based on their actual activity consumption. A patient who receives three lab tests, two imaging studies, and one consultation will carry a different cost burden than a patient who receives only the consultation.
Get the Full Details

Counter-Intuitive Realities
One thing most people miss about ABC implementation is that the initial model is always wrong. Your first pass will misallocate costs in ways that surprise you. I've never seen a clean first implementation. The first version typically has errors ranging from ten to twenty-five percent on major cost centers. This is normal. The model improves with each iteration as you refine activity definitions and validate driver selections against actual resource consumption patterns. Another common mistake is assuming ABC works equally well across all service lines. It doesn't. ABC provides the highest accuracy gains for complex, high-overhead services like surgery, oncology, and specialty clinics. For straightforward primary care or simple diagnostic services, the cost of building and maintaining the model often exceeds the value gained. The return on investment drops significantly when clinical workflows are standardized and overhead components are small relative to direct costs. I encountered a specific edge case at a regional medical center that still sticks with me. They were trying to use ABC to evaluate the profitability of a new interventional radiology program. The model showed the program was losing money. When I dug into the data, I found that the cost allocation for radiology suite turnover between cases was being assigned based on average turn time across all specialties. The interventional radiology team actually had shorter turn times due to streamlined protocols, but the model couldn't capture that because they'd used a department-level average rather than an activity-level driver. Once we switched to procedure-type-specific turnover tracking, the program showed positive contribution margin. The activity itself was fine. The cost assignment was wrong.
Data Requirements and Common Pitfalls
ABC requires detailed data that many organizations don't currently capture in structured form. You need activity-level volume data, time studies, resource consumption records, and reliable cost accounting systems. If your current ERP or financial system doesn't support multi-dimensional cost tracking, you'll need to build workarounds or upgrade your platform. This adds time and cost to the implementation. Another pitfall is organizational resistance. When ABC reveals that certain services are less profitable than previously believed, stakeholders push back. They argue the model is flawed. Sometimes it is. Often it isn't. The model shows reality. Accepting that reality requires leadership willingness to make difficult decisions about service line viability, pricing, and resource allocation. Health insurers increasingly require detailed cost data for value-based contracting and reimbursement negotiations. ABC provides that data more accurately than traditional costing methods. Organizations that have implemented it report better negotiation positions and more accurate internal pricing decisions. The improvement in cost visibility typically pays for the implementation within eighteen to twenty-four months through better resource allocation and reduced waste identification.
The biggest limitation of ABC remains its maintenance burden. Every time your service mix changes, your pricing structure shifts, or new equipment is added, the model needs updating. A static ABC model becomes inaccurate within six to twelve months as conditions evolve. Budget ongoing effort for model maintenance, ideally dedicating at least one full-time equivalent per year for a mid-sized hospital system. Without that commitment, the model decays and loses credibility among decision-makers who then discard it entirely. For smaller clinics and practices with limited administrative staff, the maintenance cost often outweighs the benefits. In those cases, simpler departmental costing with periodic review cycles may provide adequate visibility at a fraction of the effort. ABC is a powerful tool but it is not universally appropriate. Match the method to the scale and complexity of your organization before committing resources to implementation.