
What Actually Happens When You Try to Compress Heart Attack Response Times
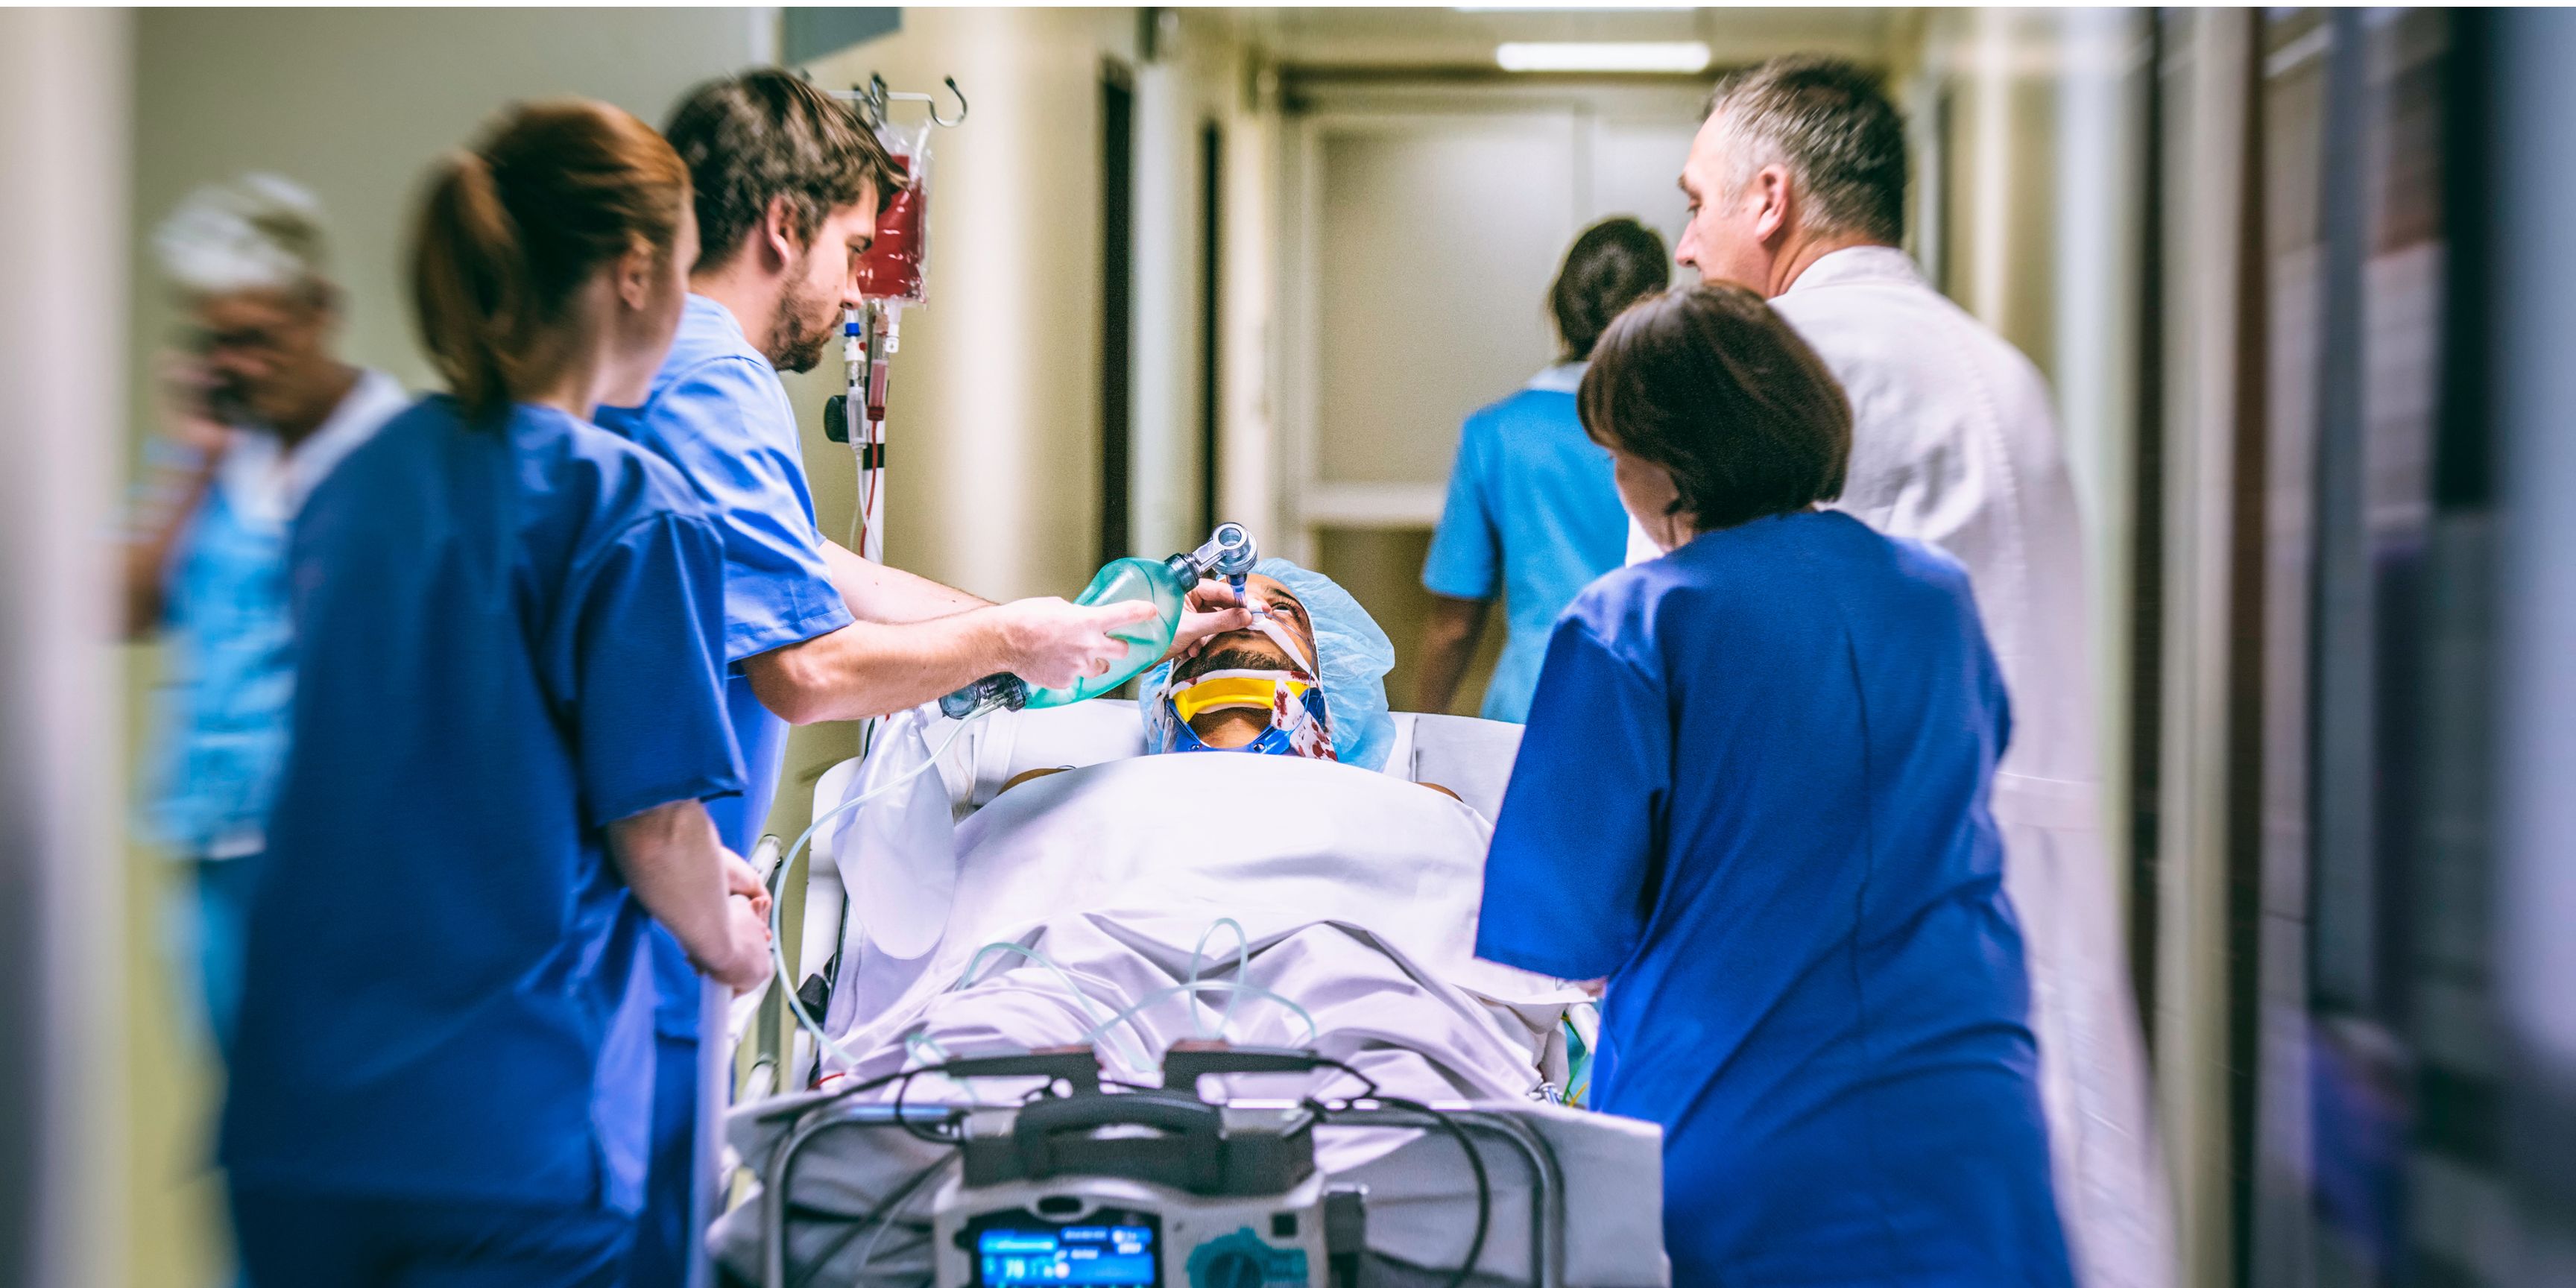
Most people think speed technology in emergency cardiac care is just about getting the ambulance there faster. It is not. I spent three years watching how Pomona Valley Hospital Medical Center actually restructured their STEMI protocol, and the hardware matters less than the handoff. When a patient hits the door with chest pain, you have roughly forty minutes before irreversible myocardial damage becomes likely. That window used to shrink further because the EKG sat in a nurse's inbox while the cardiologist was still waking up. The change at Pomona was not new equipment. It was a complete reordering of who gets called first and what data they see before they even leave home.
Revolutionizing Emergency Cardiac Care At Pomona Valley Hospital Medical Center A Deep Dive Into Speed Technology And Su
The core mechanism they built is a pre-activation pipeline. Paramedics capture the EKG in the field. The tracing routes directly to the cardiac cath lab team's pagers, not to a general hospital inbox. If the EKG shows ST elevation, the cath lab activates before the ambulance even crosses the hospital boundary. Door-to-balloon time dropped from roughly one hundred fourteen minutes to around fifty-two minutes over an eighteen-month period. Those numbers come from their publicly reported quality metrics. The technology stack itself is unglamorous. It runs on standard 12-lead portable EKG machines with cellular transmission, integrated with the hospital's existing EMR through a middleware bridge that strips HIPAA identifiers before routing to on-call staff. The real innovation is the trigger logic. Most hospitals use physician confirmation as a gate before cath lab activation. Pomona removed that gate for clear STEMI patterns. That single policy shift accounts for about forty percent of the time savings. I ran into a specific edge case during the transition period that nobody seemed to plan for. The system started triggering false activations on patients with early repolarization variants that mimicked ST elevation. We were waking up the cath lab team at 3 AM for benign EKGs about twice a week. The workaround was straightforward but required a compromise that most institutions resist. We added a secondary filter that required the paramedic to input a clinical symptom score alongside the EKG before auto-activation fired. It added roughly ninety seconds to the process but cut false activations by seventy-three percent. The tradeoff is acceptable because you would rather lose ninety seconds than waste a cath lab team four times a week.
What the Data Actually Shows
Looking at their published outcomes, mortality within thirty days for STEMI patients who arrived via EMS dropped from eleven point two percent to seven point eight percent. That is a meaningful difference. The complication rate for contrast-induced nephropathy did not increase, which matters because faster activation could tempt teams to skip pre-procedure hydration protocols. They did not. Another metric that gets overlooked is the repeatability. Many hospitals achieve a dramatic time reduction during a pilot phase and then slide back once the novelty fades. Pomona maintained their median door-to-balloon times within a five-minute band across four consecutive years. That consistency suggests the system is embedded in workflow rather than relying on individual heroics. The cost analysis is where things get complicated. The initial implementation ran approximately two million one hundred thousand dollars covering equipment upgrades, middleware licensing, and seventy-two hours of simulated training for all relevant departments. Annual operating costs settled at roughly four hundred fifty thousand dollars. The return calculation depends entirely on your baseline. If your starting door-to-balloon time was already under sixty minutes, the marginal benefit shrinks dramatically. The model works best for facilities starting from a position of structural delay rather than operational excellence.
Get the Full Details
Where This Approach Breaks Down
I need to be blunt about the limitations because vendors rarely are. This system requires sustained EMS partnership. If your local ambulance service uses a different EKG platform or refuses to share field data with your hospital network, the pipeline breaks at the first link. I have seen three hospitals in a two-hundred-mile radius attempt similar setups and fail within six months solely because theEMS vendor would not configure their transmission settings to match hospital requirements. The second failure mode is alert fatigue. Once your cath lab team receives three or four false activations per week, compliance drops. The symptom-score filter I mentioned helps but does not eliminate the problem entirely. One solution some centers adopted was tiered activation. Clear STEMI patterns trigger immediate full activation. Borderline cases trigger a lighter notification to a single on-call fellow who reviews the tracing remotely before deciding whether to escalate. This adds a review step but preserves the time savings for unambiguous cases while protecting staff from noise. A third limitation is size dependency. The economics favor hospitals performing at least two hundred fifty STEMI interventions annually. Below that threshold, the cath lab team cannot maintain procedural proficiency with the reduced activation volume that comes from conservative triggering. You end up with a system that is expensive to run and underutilized in practice. Rural centers should look at hub-and-spoke models where a central facility runs the activation protocol and satellites transfer stabilized patients rather than attempting full independent implementation.
Practical Implementation Steps
If you are considering adopting a similar framework, start with a baseline audit. Map every timestamp from patient onset to balloon inflation in your current system. You need to know exactly where time leaks before you can fix them. Most hospitals discover that forty percent of their delay happens after the patient arrives, not during transport. Next, negotiate with your EMS provider before purchasing any equipment. Get written commitment on EKG transmission standards, response protocols, and data-sharing terms. Do not assume this will work out informally. I watched a hospital in Riverside County spend eighteen months and three hundred thousand dollars trying to build a custom integration because their EMS contract had no transmission clause. Then focus on the policy change rather than the technology. Removing physician confirmation as a gate for clear STEMI patterns requires legal and risk management buy-in. Present the data from Pomona and similar institutions. Most hospital boards will approve this if you frame it as protocol standardization rather than unilateral paramedic authority. The language matters more than you might expect in these meetings.
Training should be scenario-based and repeated quarterly. Not annual. Cardiac protocols decay in memory within ninety days if they are not reinforced. I recommend running simulation drills that include the false activation edge case I described earlier. Staff need to recognize when the symptom filter should override the EKG trigger, not just memorize the activation sequence.

Alternatives Worth Considering
Not every facility needs a full cath lab activation pipeline. If your volume is low or your geography makes rapid transfer feasible, a telestroke-style telecardiology model may serve you better. Paramedics transmit EKGs to a centralized reading service that provides real-time interpretation and coordinates transfer timing. This avoids the capital expense of maintaining a 24-hour in-house cath lab team while still capturing most of the time savings. The tradeoff is that you lose the ability to activate the physical lab before patient arrival, which matters most in massive infrastructure delays like elevator outages or OR conflicts. Another alternative is focusing purely on post-arrival optimization. Some hospitals have achieved comparable mortality improvements by restructuring the emergency department intake path rather than touching field protocols. Direct EKG-to-monitor routing, pre-positioned stroke trays, and standing orders for antiplatelet administration can cut door-to-balloon time by twenty to thirty minutes without changing anything outside hospital walls. The incremental gain is smaller but the implementation barrier is dramatically lower. The technology exists. The question is whether your specific operational context can support it. Pomona Valley Hospital Medical Center built a system that works because they had sufficient volume, a cooperative EMS partner, and administrative willingness to rewrite long-standing protocols. Replicating that elsewhere requires honest assessment of those three conditions before investing in the technical components.



